Why Most People Mess Up Simple Columnar Epithelium at the Microscope
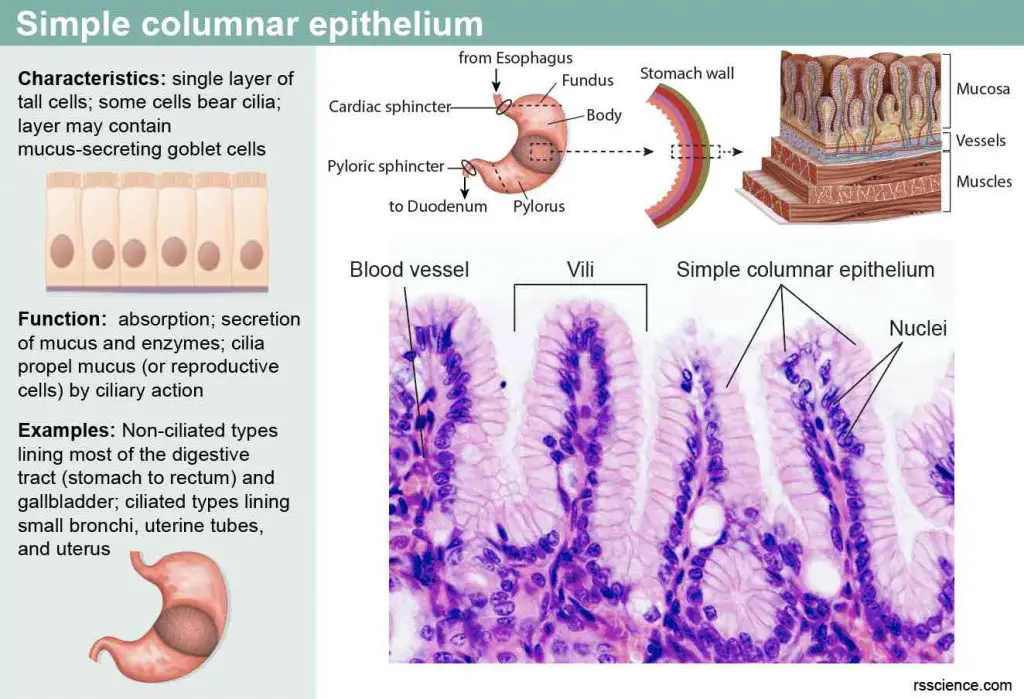
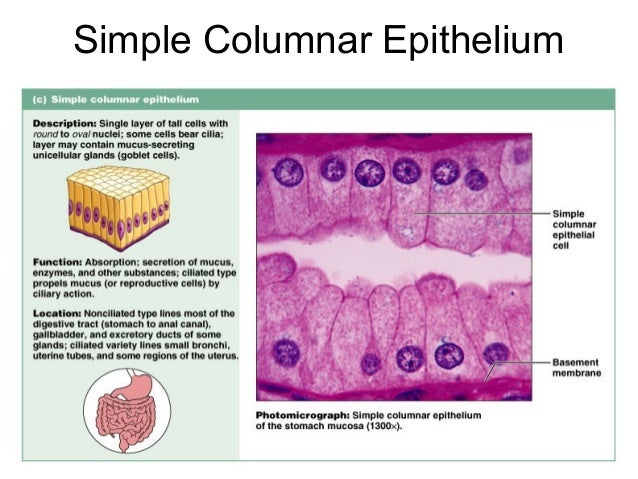
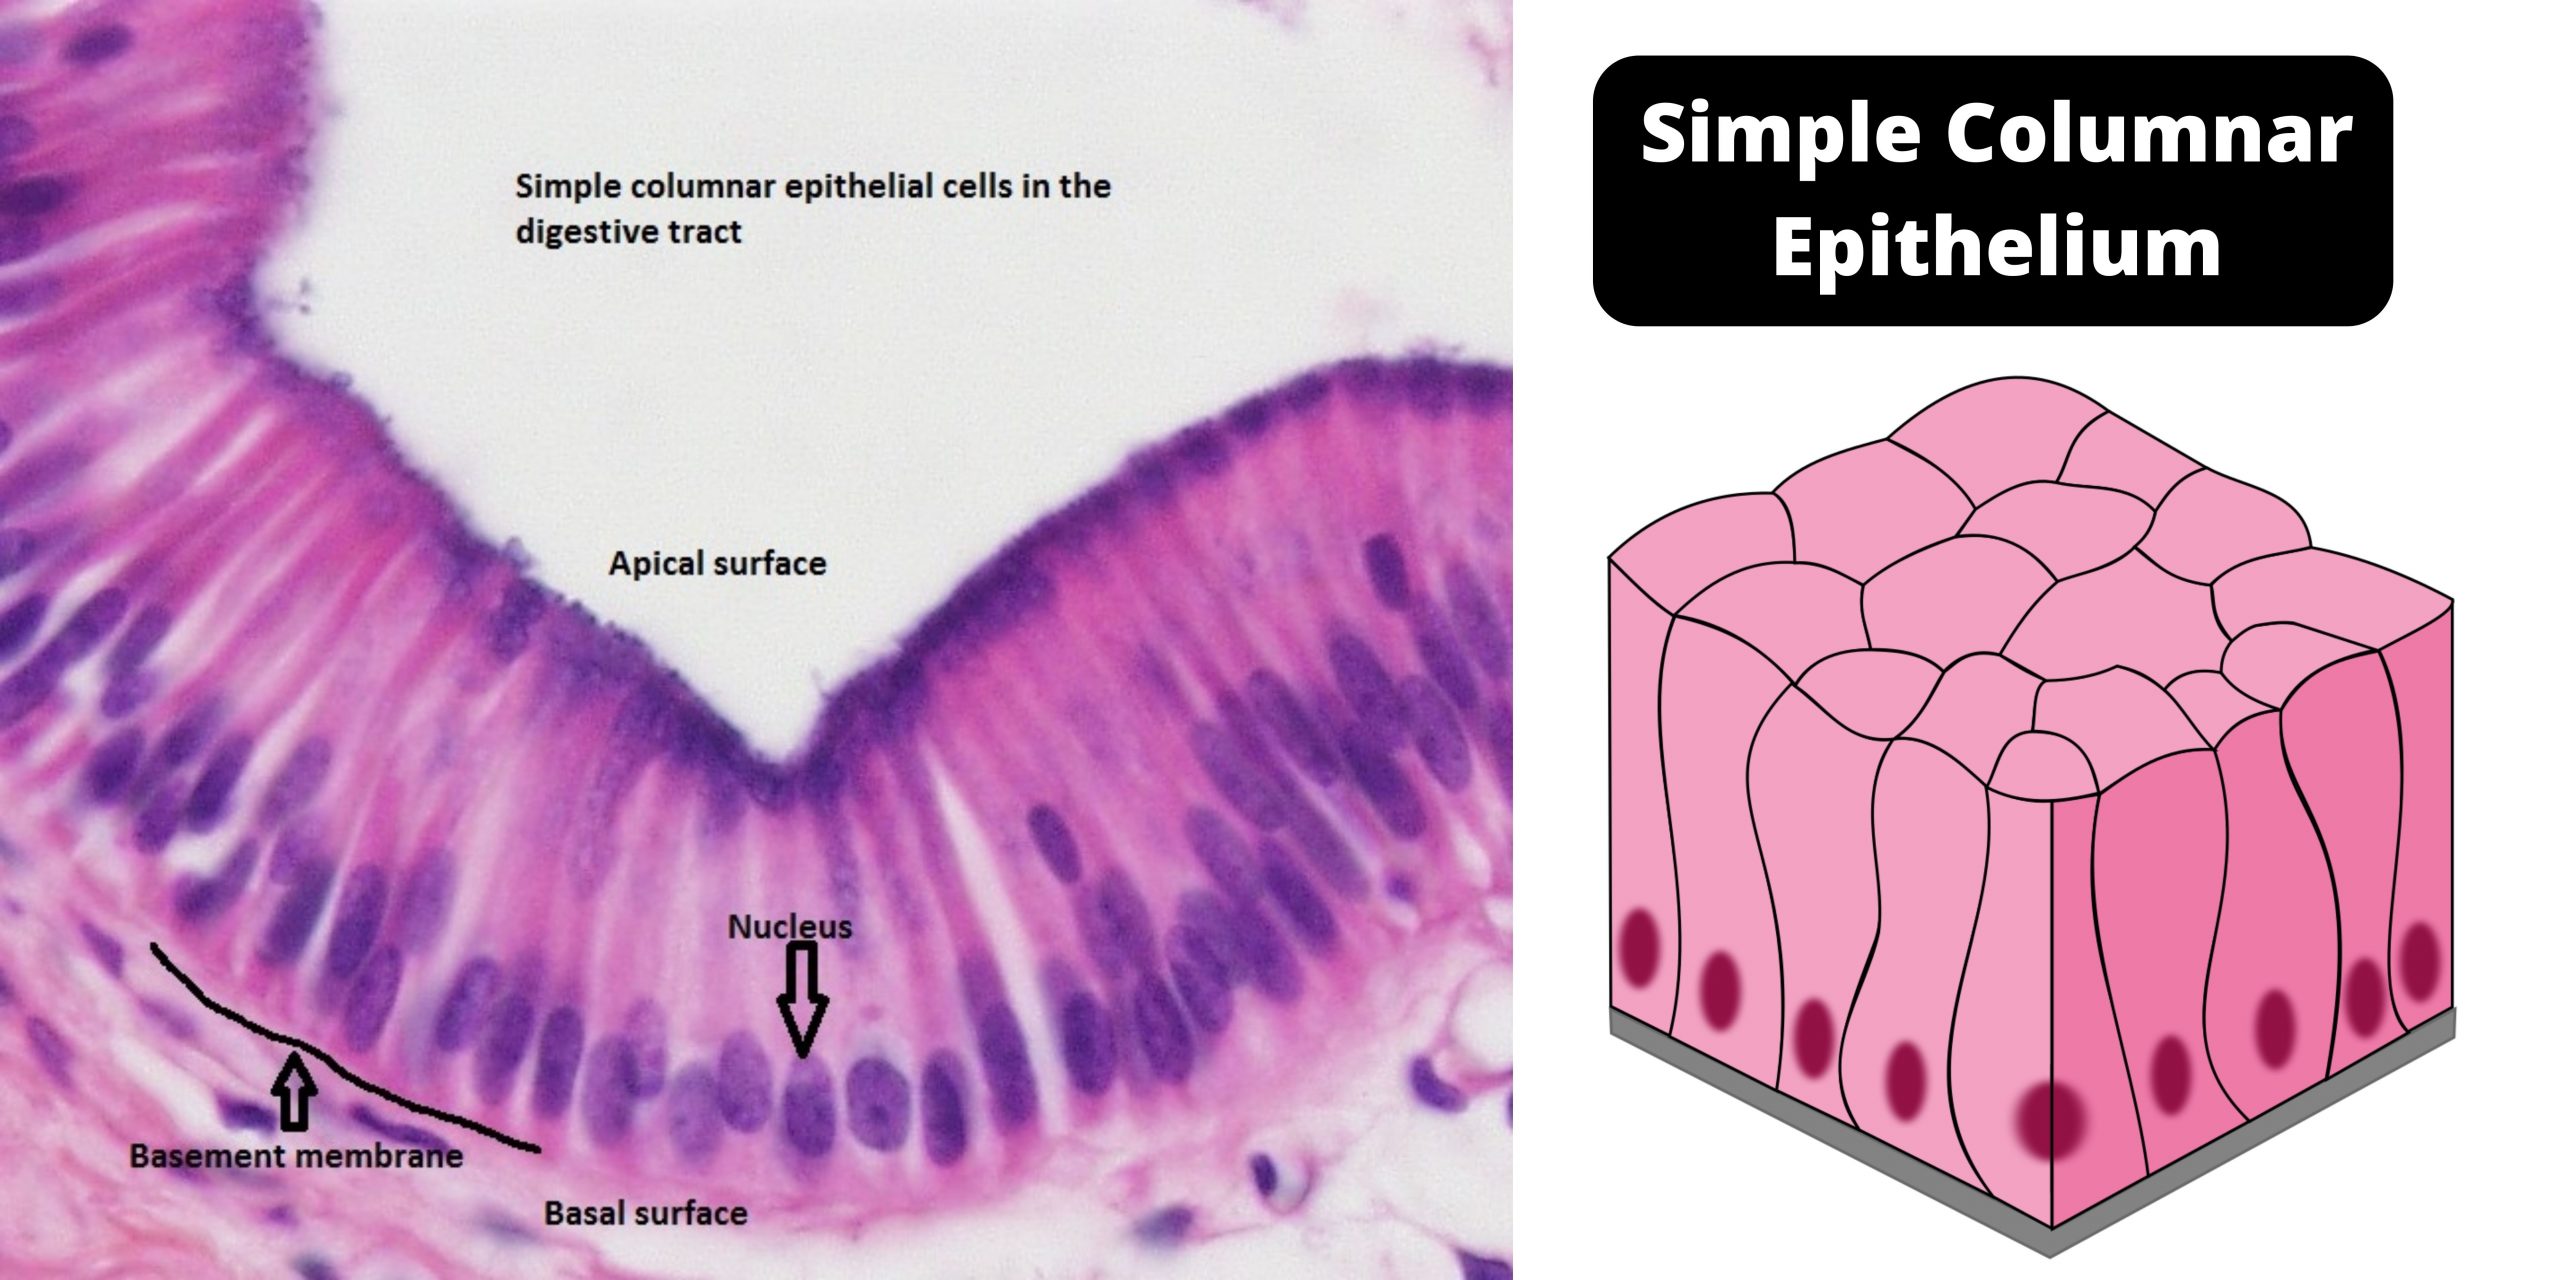
I've been going through histology slides for about twelve years now. The stuff that trips people up isn't the complicated tissues. It's the simple columnar epithelium, and not for the reason you'd think. Everyone learns the textbook definition, but actually identifying it under a scope, especially when the tissue isn't perfectly prepared, is a different problem entirely. Simple columnar epithelium is a single layer of tall, narrow cells sitting on a basement membrane. The nuclei are usually oval and positioned near the base of the cell. You'll find it lining the stomach, small intestine, and parts of the large intestine. It also lines the gallbladder and some of the smaller bronchioles. That's the basic version from any textbook. What they don't tell you is what happens when the tissue is fixed poorly or sectioned at the wrong angle. I was doing routine GI biopsies last year and kept getting confused samples where the epithelium looked almost cuboidal. Turns out the endoscope biopsy forceps were grasping the tissue at a tangential angle, so the section was cut obliquely through the columnar cells instead of perpendicular. The cells looked shorter than they actually were. My workaround was to look at the nuclear arrangement across multiple fields and check if the nuclei formed a consistent basal line. When they did, I knew these were columnar cells viewed at an angle, not cuboidal epithelium. That single trick saved me from misclassifying half a dozen slides.
The key structural feature that actually matters in practice is the brush border, or microvilli. In the small intestine, these are densely packed and create that eosinophilic striated border you see on H&E staining. But here's the counter-intuitive part that most students miss: the brush border isn't what makes the tissue columnar. The cell shape is. The microvilli are just an adaptation on top of it. I've seen people describe goblet cells as the defining feature of intestinal simple columnar epithelium. They're not. Goblet cells are interspersed within the epithelium, yes, but the columnar absorptive cells are what define the tissue type. You can have simple columnar epithelium without goblet cells, like in the gallbladder. Another thing nobody emphasizes enough is the lateral cell border. In well-prepared sections, you can see distinct cell margins because the junctions are fairly tight. In poorly fixed tissue, those borders disappear and the epithelium looks like a syncytium. When that happens, you fall back on nuclear positioning. Basally located, uniformly sized oval nuclei in a single row is your signal. If the nuclei are stratified or randomly scattered, you're probably looking at something else entirely, like pseudostratified columnar epithelium. The functional side is where this tissue gets interesting. Absorption and secretion are the main jobs, but the mechanism varies significantly by location. In the small intestine, the apical surface area is amplified roughly fortyfold by the combination of microvilli and the folding of the mucosa into villi. That amplification is why simple columnar epithelium here is so efficient at nutrient uptake. In the stomach, the same tissue type is doing something completely different. It's secreting mucus and hydrochloric acid, not absorbing anything. The cells look similar under the microscope, but their functional apparatus is entirely different. The gastric surface mucous cells have a pale, vacuolated cytoplasm because of the mucin content. The enterocytes in the intestine have more eosinophilic cytoplasm because of all the organelles involved in absorption.
I ran into a case recently where a pathology resident was struggling to differentiate between intestinal metaplasia and normal gastric epithelium in a chronic gastritis biopsy. The trick wasn't in the overall architecture. It was in the nuclear detail. The metaplastic columnar cells had more basal chromatin condensation and slightly more prominent nucleoli than the native gastric mucous cells. Also, the presence of Paneth cells at the base of the crypts was the giveaway. Paneth cells don't normally exist in the stomach. Finding them in gastric biopsy tissue means metaplasia has occurred. That's a finding with real clinical implications because intestinal metaplasia in the stomach is a precancerous change. There are limitations to relying on light microscopy alone for this tissue. If you need to assess the microvilli structure itself, H&E won't cut it. You need scanning electron microscopy for that, or at minimum, a special stain like PAS to highlight the glycocalyx covering the microvilli. Standard histology can tell you the brush border is present, but it can't show you individual microvilli. For research purposes where that level of detail matters, you'd also want immunohistochemistry for markers like villin or cytoplasmic actin to confirm the differentiated state of the absorptive cells. One more practical note about preparation. When you're processing these tissues for teaching or reference, formalin fixation is standard, but over-fixation can make the cytoplasm look overly dense and distort the nuclear morphology. I've found that eight to twelve hours of fixation in ten percent neutral buffered formalin gives the best balance for routine H&E. Longer than that and the nuclei start to shrink, which makes assessing nuclear position much harder. That's the kind of detail that only comes from actually grinding through hundreds of slides over several years.
Get the Full Details