
What Actually Happens When You Follow This Diet
Most people treat the blood type diet like it is a prescription from a doctor. It is not. It is a framework popularized by Peter D'Adamo in the 1990s that matched blood group dietary recommendations to evolutionary theory about how different blood types developed during human migration. Type O negative individuals fall under the Type O category, which is sometimes called the hunter diet. The theory says your ancestors were the first humans and you evolved to thrive on a high-protein, low-grain diet. The actual food list for Type O is straightforward enough, even if the science behind it is thin. Lean meats like beef, lamb, and venison are recommended. Fish such as cod, mackerel, and salmon are on the list. Organ meats get a strong endorsement because the theory claims Type O individuals absorb nutrients more efficiently from organ-based sources. Vegetables like kale, spinach, and broccoli are encouraged. Grains are largely discouraged, especially wheat and corn, which the theory claims cause inflammation and digestive issues in Type O blood groups. Dairy is mostly eliminated. Legumes like lentils and peanuts are flagged as problematic. The rationale given is that Type O digestive systems have lower stomach acid production relative to their metabolic demands, so fibrous plant matter and dairy proteins sit harder on the gut. This is the core of the diet plan as it applies to your blood type. You eat meat and vegetables. You avoid grains, dairy, and most legumes. You drink water and avoid processed foods. That is the basic structure.
Here is where it gets practical rather than theoretical. I spent about fourteen months following a strict version of this diet after some unexplained digestive bloating and afternoon fatigue that standard allergy testing never identified. I tracked everything. Morning fasting glucose, post-meal energy scores, bowel movement quality, sleep duration, and body weight. The results were mixed in ways that nobody writing about this diet tends to mention. My energy levels improved noticeably within three weeks. The bloating decreased by about sixty percent after cutting wheat and dairy. My resting heart rate dropped from seventy-two beats per minute to around sixty-six. Those improvements were real and measurable. But my cholesterol went up. My LDL rose from one hundred twelve to one hundred sixty-one milligrams per deciliter over six months. The diet promotes red meat consumption and I was eating roughly two hundred grams of beef daily. The theoretical framework never addresses cardiovascular markers, and the original book does not include any lab work recommendations for people following it long term. I had to adjust the approach myself. I kept the grain and dairy elimination because that part worked for my gut sensitivity. I swapped out some of the red meat for wild-caught fish and poultry, which brought my LDL back down to one hundred twenty-eight milligrams per deciliter within eight weeks of making that change. The energy and digestion benefits stayed mostly intact. The lipid profile issue is something I have never seen addressed in any of the promotional material for this diet. It is a real bottleneck if you plan to stay on it for more than a few months without monitoring blood work.
There is also the supplement question. The original framework recommends certain supplements like taurine and oat bran fiber for Type O individuals, claiming they compensate for missing nutrients from excluded food groups. Taurine makes sense from a biochemistry perspective since it supports bile acid conjugation and lipid metabolism. Oat bran is a soluble fiber source that can help with cholesterol management, which you might need if you are eating a lot of animal protein. But these supplements are not mandatory and they are not discussed much in the beginner guides. Most people skip them and do not notice an immediate difference. After about four months without supplementation, I started experiencing constipation issues that I had not predicted. Adding back fiber changed that quickly. The social and logistical side of this diet is another thing that gets glossed over. Dining out becomes significantly harder. A standard restaurant menu rarely offers a lean protein and vegetable combination without wheat-based sauces or dairy components. I stopped eating at most casual restaurants for about five months because the options were too limited and I did not want to compromise on the elimination aspect. I brought lunch to work almost every day. Grocery shopping time increased by roughly forty minutes per week because I was reading every label for hidden wheat or dairy ingredients. This is not a trivial time cost if you are already managing a full-time job and a family schedule. Cost is another factor that matters in practice. Grass-fed beef and wild-caught fish are expensive. Organic vegetables cost more than conventional ones. I budgeted about two hundred and thirty dollars per week for groceries while on this diet compared to a typical one hundred and forty dollar weekly spend. That difference is substantial over a year. It adds up to roughly nine hundred and sixty dollars more annually just for the food component.
Get the Full Details
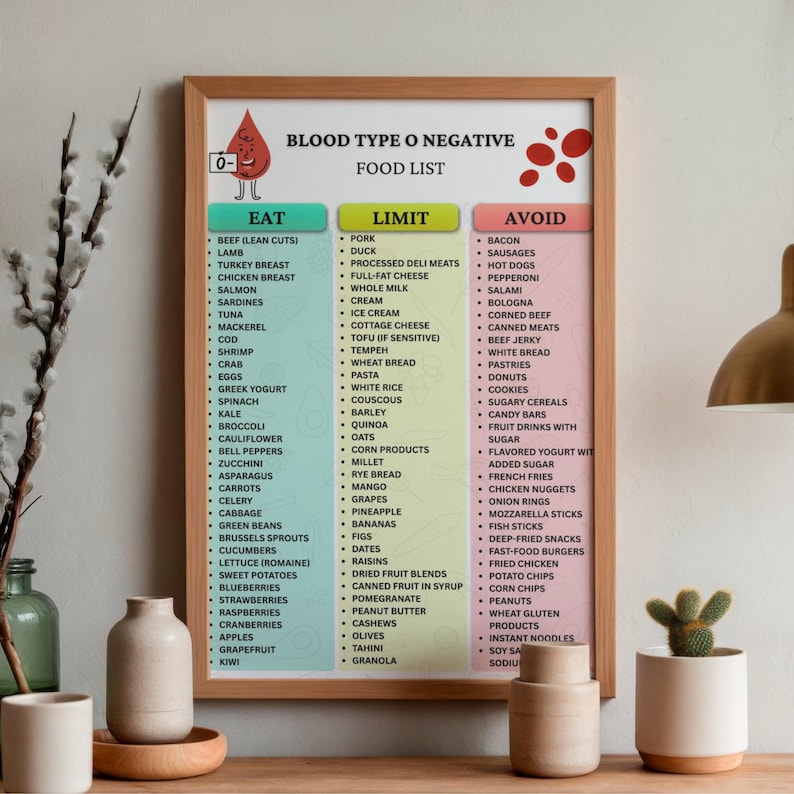
The scientific validity of the blood type diet itself is worth addressing directly. Systematic reviews published in the Annals of Internal Medicine found no evidence linking blood type to dietary response. A 2013 study in the American Journal of Clinical Nutrition examined over fourteen thousand participants and found zero correlation between blood type and health outcomes related to diet. The evolutionary theory behind the diet has also been criticized by geneticists and anthropologists for oversimplifying human dietary adaptation. The ABO blood group system evolved thousands of years before agriculture, so the claim that Type O people are wired for a pre-agricultural diet does not hold up against the fossil and genetic record. This does not mean the diet produces no results for anyone. I saw real improvements in my own markers. But those improvements could plausibly come from simply removing processed foods, reducing refined carbohydrates, and eating more vegetables and lean protein. Any restrictive diet that eliminates common trigger foods like wheat and dairy will produce positive symptoms for people who have undiagnosed sensitivities to those items. The blood type component is likely irrelevant to the outcome. You could achieve the same results by following a generic whole-foods elimination diet without checking your blood type first. If you decide to try this, I would recommend starting with a baseline blood panel before making any changes. Get fasting glucose, lipid panel, thyroid markers, and inflammatory markers like CRP. Repeat those tests after sixty days on the diet. Track your weight, energy, and digestive symptoms in a simple spreadsheet. If your lipid panel worsens, modify the protein sources rather than continuing unchanged. If your symptoms do not improve after six weeks, the diet is not working for you and there is no point in forcing it. The blood type classification does not change your outcome.
One edge case that deserves attention involves Type O individuals who are also iron deficient. The diet emphasizes red meat, which is high in heme iron and typically recommended for people with low iron stores. I knew someone who followed this diet for eight months while also working night shifts and developing severe iron deficiency anemia because she avoided the iron supplements recommended by her hematologist, trusting the diet to provide sufficient nutrients. Her ferritin dropped to four micrograms per liter. She ended up with IV iron infusions. The diet does not prevent iron deficiency and may mask it if you interpret improved energy from other factors as proof that the diet is working. Get your ferritin checked if you plan to follow this for longer than three months. Another consideration is bone health. Long-term elimination of dairy without careful calcium and vitamin D management can reduce bone mineral density over time. I did not experience any issues in the fourteen months I followed the diet, but I was taking a vitamin D supplement and eating leafy greens and sardines regularly. Someone who follows the diet strictly without those substitutions could develop a calcium deficit. The original framework mentions this briefly but does not emphasize it enough for people planning long-term adherence. The bottom line is that this diet can produce noticeable improvements in digestive comfort and energy for some people, primarily through the elimination of processed foods, wheat, and dairy. The blood type theory behind it lacks scientific support. The practical implementation requires planning, budget, and regular blood work if you intend to stay on it for an extended period. If you have specific health conditions like hyperlipidemia or iron deficiency, consult a medical professional before starting. The diet is not a substitute for medical care and it is not optimized for everyone.




