Joint injections aren't magic, but they work when you understand what they actually do
Most people think cortisone shots or PRP are one-size-fits-all solutions for knee pain or shoulder issues. They're not. I've seen patients come back month after month asking for another injection because the first one gave them three weeks of relief and they thought it was broken. The problem isn't the injection technique. The problem is picking the wrong injection for the wrong diagnosis. Here's how the whole process actually works in practice. You walk into a clinic, get imaged first — ultrasound or fluoroscopy, not just a plain X-ray unless you're screening for arthritis — and then the provider chooses between corticosteroid, hyaluronic acid, PRP, or sometimes stem cell depending on what's actually going on. The injection itself takes about two minutes. The needle goes through skin and subcutaneous tissue into the joint capsule. Once you feel that pressure shift inside the joint, you know it's in the right place. I had a case last year where a patient kept coming back with "knee pain" and getting steroid injections every six weeks. Three months of the same thing. I ran an ultrasound and found the real problem wasn't intra-articular at all — it was pes anserine bursitis on the medial side, totally outside the joint. The steroid was going into the joint space every time while the actual inflamed bursa sat right there untouched. Once we switched to a targeted bursal injection with a smaller gauge needle, the pain dropped significantly within a week instead of the usual two-week steroid onset window.
What each type actually does
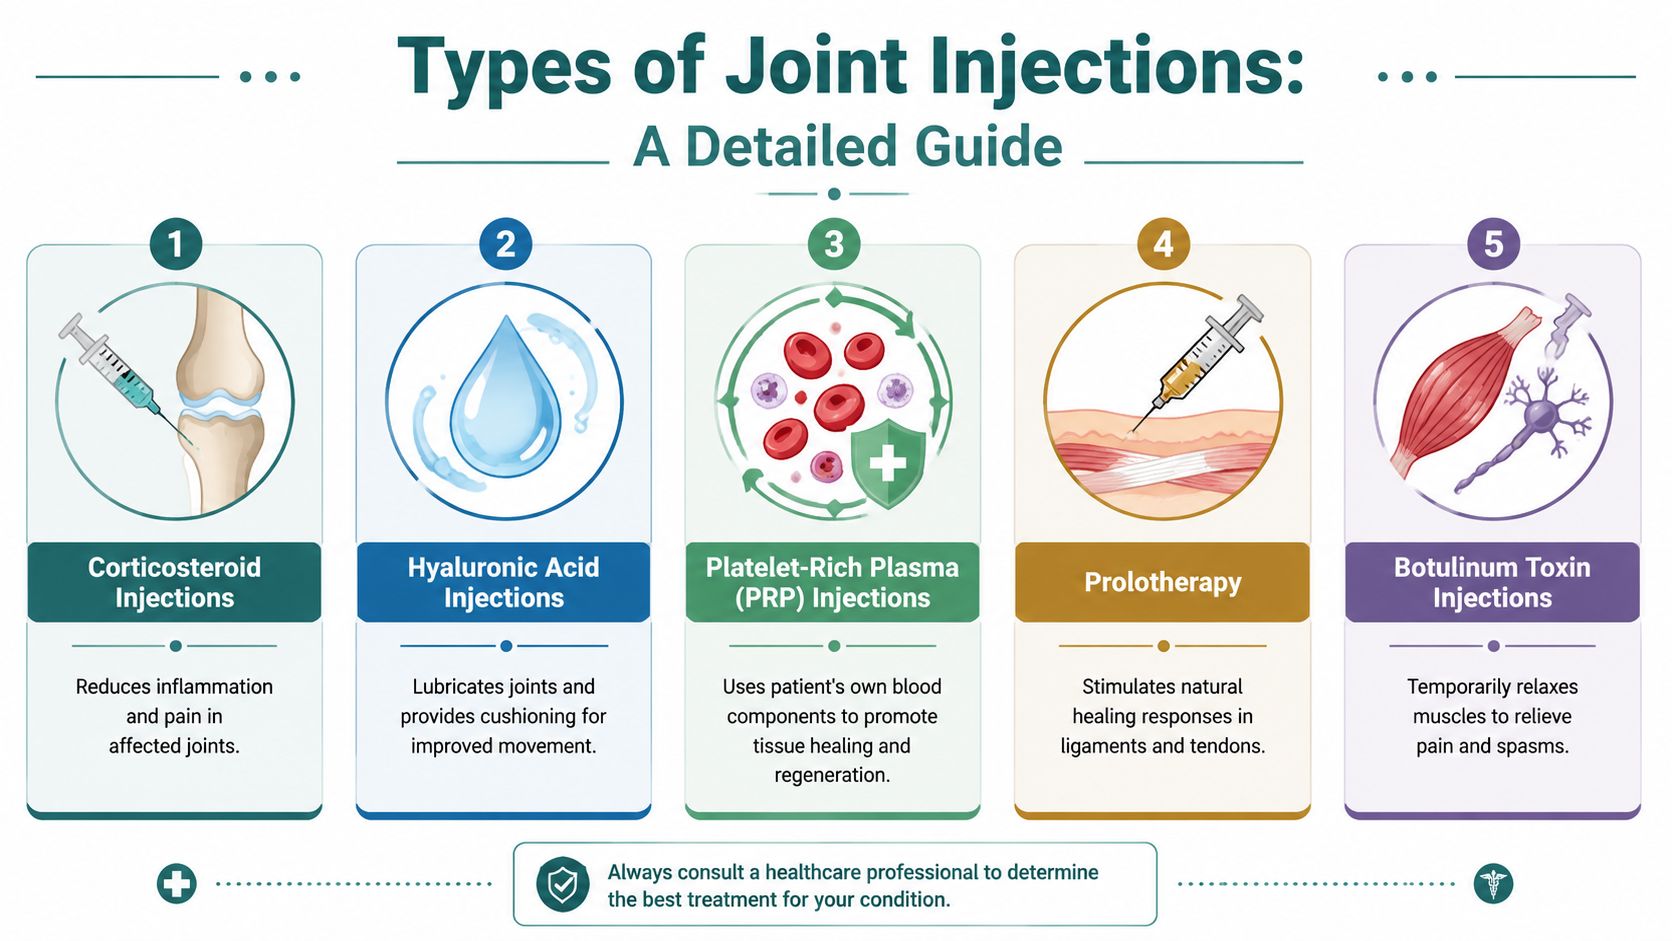
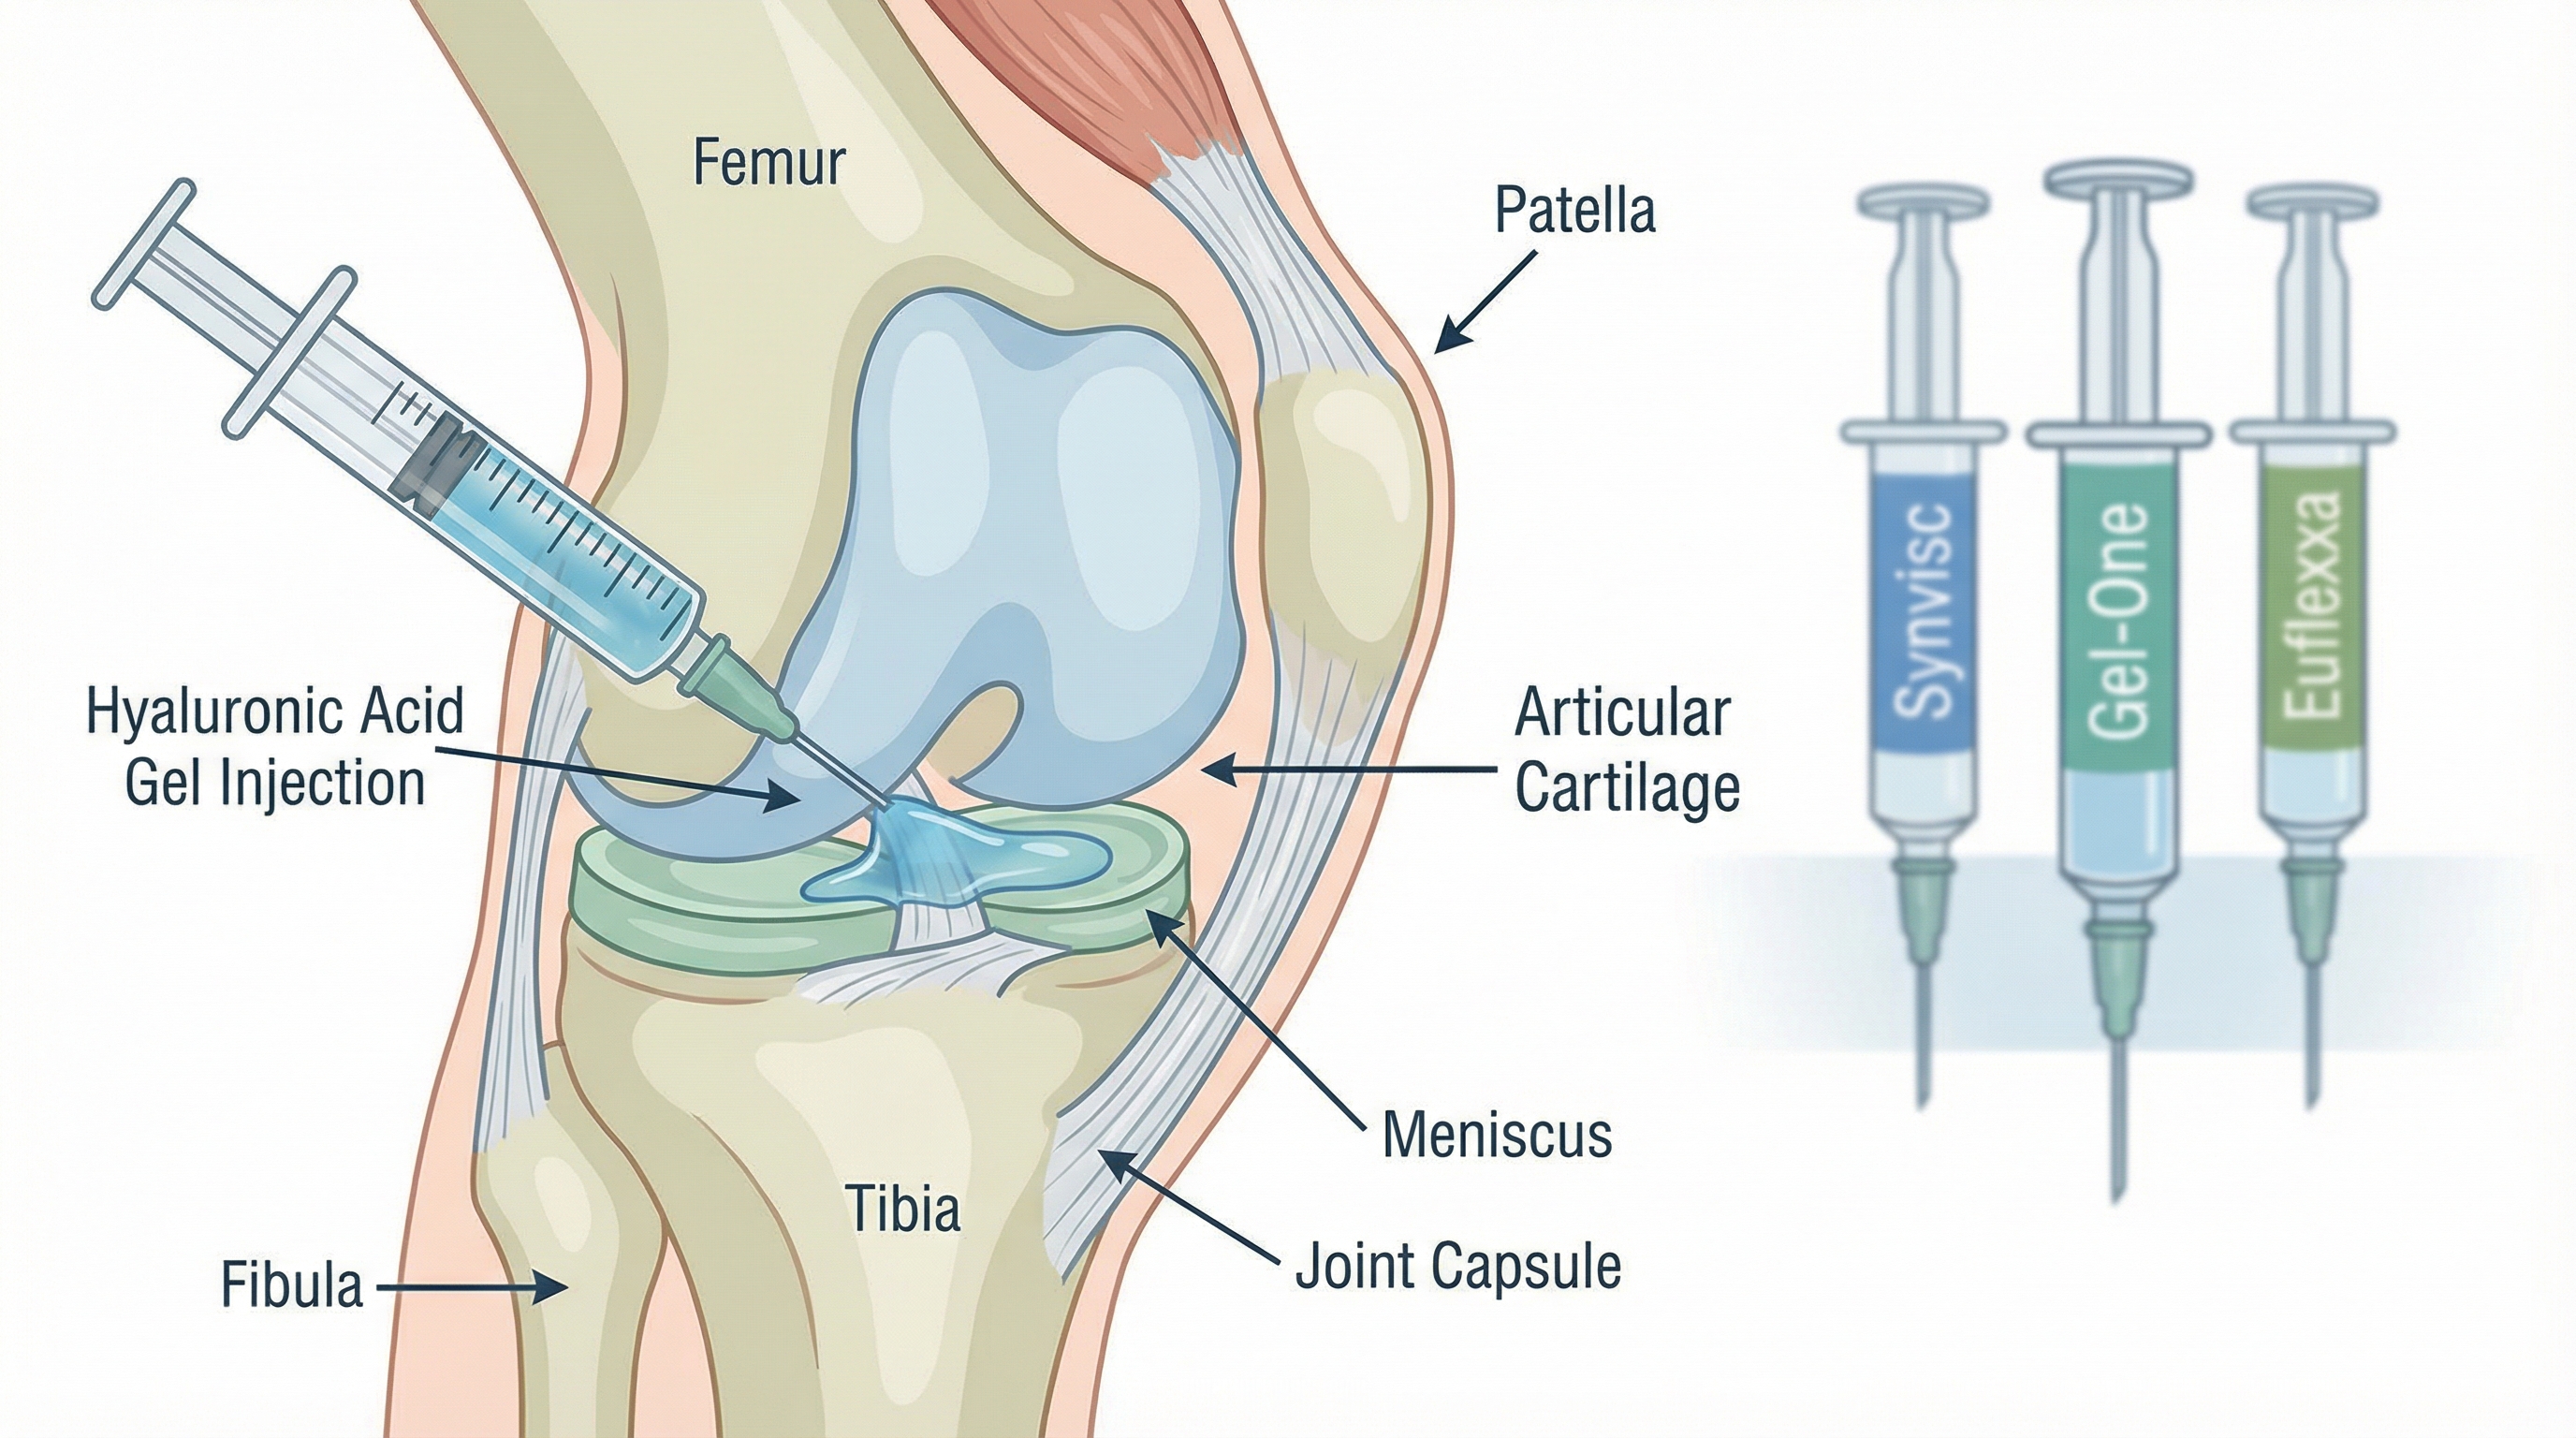
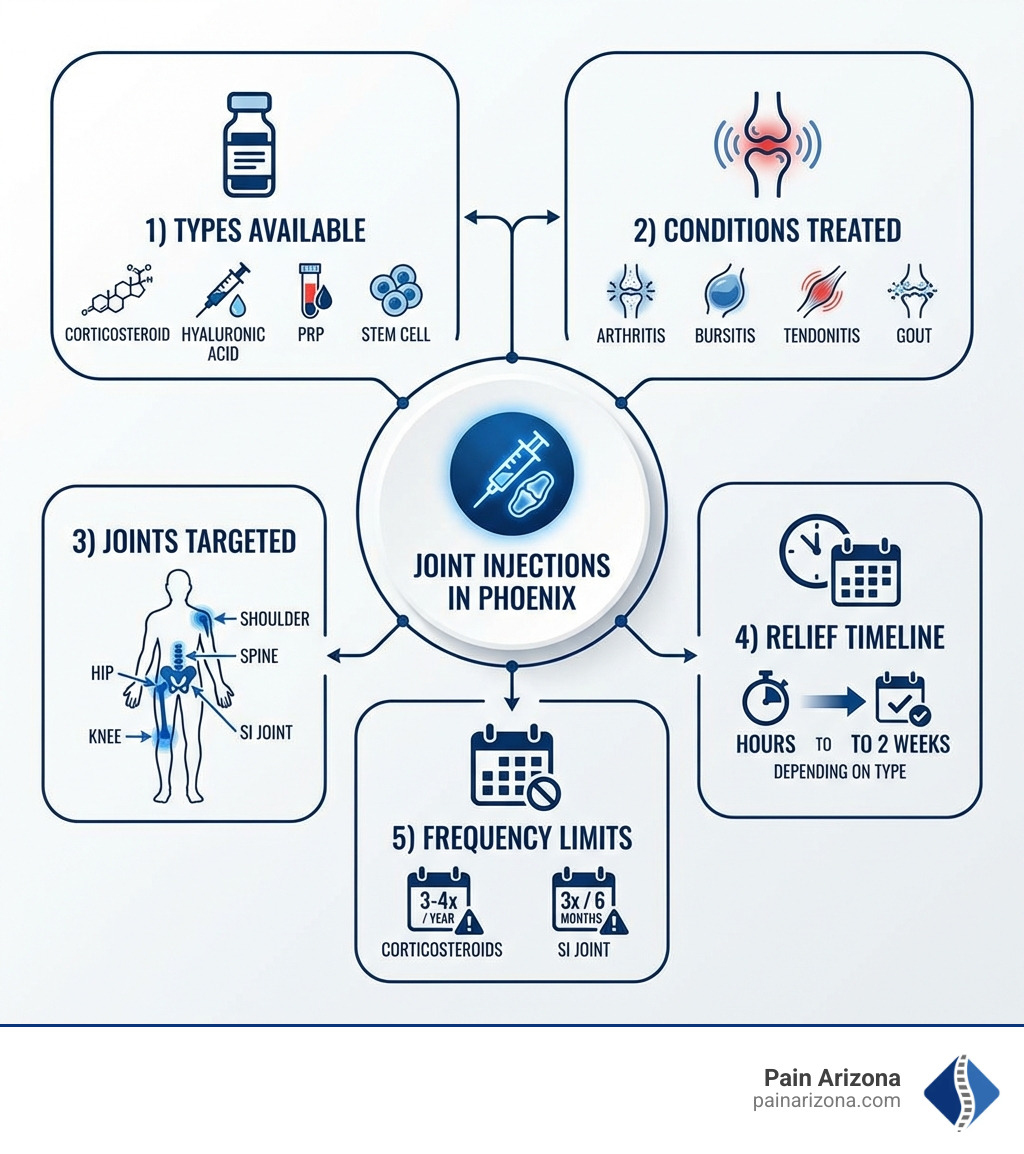
Corticosteroid injections reduce inflammation by suppressing the immune response locally. Onset is fast — usually 24 to 72 hours for full effect — but the duration is limited. Most studies show meaningful relief lasting anywhere from two to twelve weeks depending on the joint and the underlying condition. Repeat injections are generally capped at three to four per joint per year because cartilage degradation becomes a real risk with repeated exposure. I've seen patients who got eight or nine injections into the same knee over two years and then needed a total knee replacement at 52. That's not the steroid's fault alone, but it's a factor worth considering. Hyaluronic acid, or viscosupplementation, works differently. It's meant to restore the viscosity of synovial fluid. The data on effectiveness is mixed. Some meta-analyses show minimal benefit over placebo, especially in mild to moderate osteoarthritis. But in real clinical practice, I've had patients with moderate knee OA report six to twelve months of decent function after a series of three weekly injections. It's not instant relief. It's cumulative. And it doesn't work for everyone. If you have inflammatory arthritis like rheumatoid, HA injections are basically useless. PRP is the big one people ask about now. You draw your own blood, spin it in a centrifuge to concentrate the platelets, and inject the platelet-rich plasma back into the damaged area. Growth factors in the platelets theoretically promote healing. The science is still developing, but for tendinopathies and mild-to-moderate osteoarthritis, the evidence is leaning positive. A single PRP injection for lateral epicondylitis — that's tennis elbow — can show improvement over eight to twelve weeks that outlasts steroid injections after the three-month mark. Steroids give faster short-term relief. PRP builds something more durable if your body responds well to it.
The setup and aftercare nobody tells you about
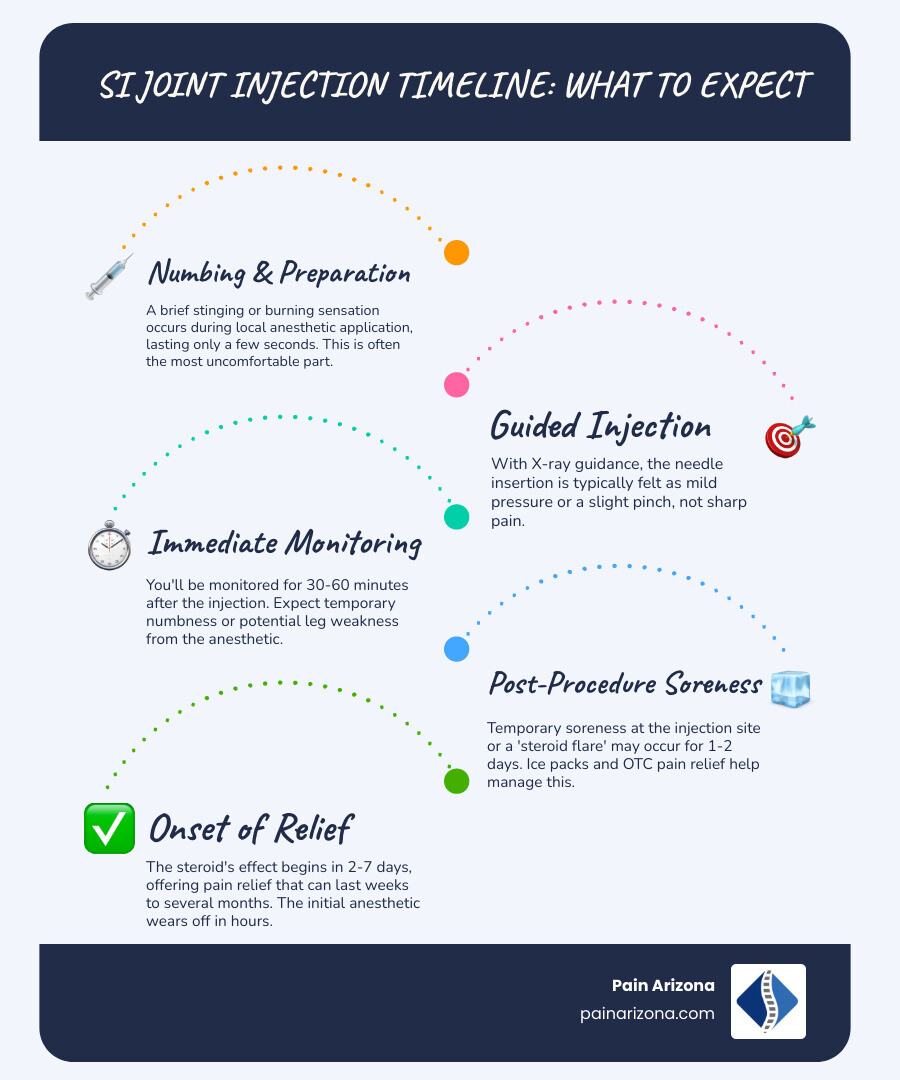
Before the injection, most providers will tell you to stop NSAIDs for about a week prior. Ibuprofen and similar drugs can interfere with the inflammatory cascade that steroids and PRP rely on. I had a patient who kept taking naproxen for her lower back pain and wondering why the epidural steroid injection wasn't working as expected. Once she stopped it five days before, the response was noticeably better. Also, if you're on blood thinners, most clinics won't touch you without coordination with your prescribing physician. The risk of hemarthrosis — bleeding into the joint — is real even with a small needle. After a corticosteroid injection, you should plan on no heavy loading of that joint for 48 to 72 hours. The steroid itself can cause a flare in the first day or two where pain actually gets worse before it gets better. I tell patients to expect a post-injection flare and to ice it for the first day rather than panicking and thinking the procedure failed. With PRP, the same flare is common, sometimes more pronounced, because you're introducing concentrated growth factors and the local tissue reaction is stronger. Ice, rest, and avoid anti-inflammatories for a full week after PRP. NSAIDs blunt the healing response you're trying to kickstart.
Get the Full Details
When injections are the wrong call
If you have an active infection in or around the joint, absolutely no injections. That's a hard line. Septic arthritis combined with a corticosteroid injection can turn bad very fast because you're suppressing local immunity in an already infected space. Same with uncontrolled diabetes — steroid injections can spike blood sugar for days or even a week, and if your diabetes management isn't stable, the metabolic disturbance outweighs any joint benefit. Advanced structural damage is another scenario where injections hit a ceiling. If you have bone-on-bone arthritis with significant joint space narrowing on imaging, no amount of hyaluronic acid or PRP is going to regenerate that cartilage. The best you're going to get is modest symptom modulation for a few months. In those cases, focusing on weight management, physical therapy, and surgical consultation makes more sense than cycling through injections that provide diminishing returns. There's also the psychological trap of chasing relief with repeated injections. I see it constantly — patients who get addicted to the temporary window of good pain-free weeks and delay addressing the root mechanical issue. The injection buys time. It doesn't fix the biomechanics. If your knee pain comes from malalignment or a meniscal tear, injecting the joint without addressing the underlying structural problem is like putting a bandage on a leaking pipe and waiting for the next flood.
What to ask before you get injected
Ask what guidance they're using — ultrasound, fluoroscopy, or landmark-only. Landmark-only injections have a higher miss rate, especially in deeper joints like the hip or shoulder. Ask about the specific product being used, the concentration, and how many injections they're recommending in a series. Ask what the expected timeline is for relief and how long it should last. If they can't give you concrete numbers, that's a yellow flag. Most importantly, ask what the alternative is. If they're pushing an injection as the primary treatment without discussing physical therapy, activity modification, or weight management first, that's worth questioning. Injections have a place. They're just not usually the only place you need to be.