What Tumid Lupus Actually Looks Like In Practice
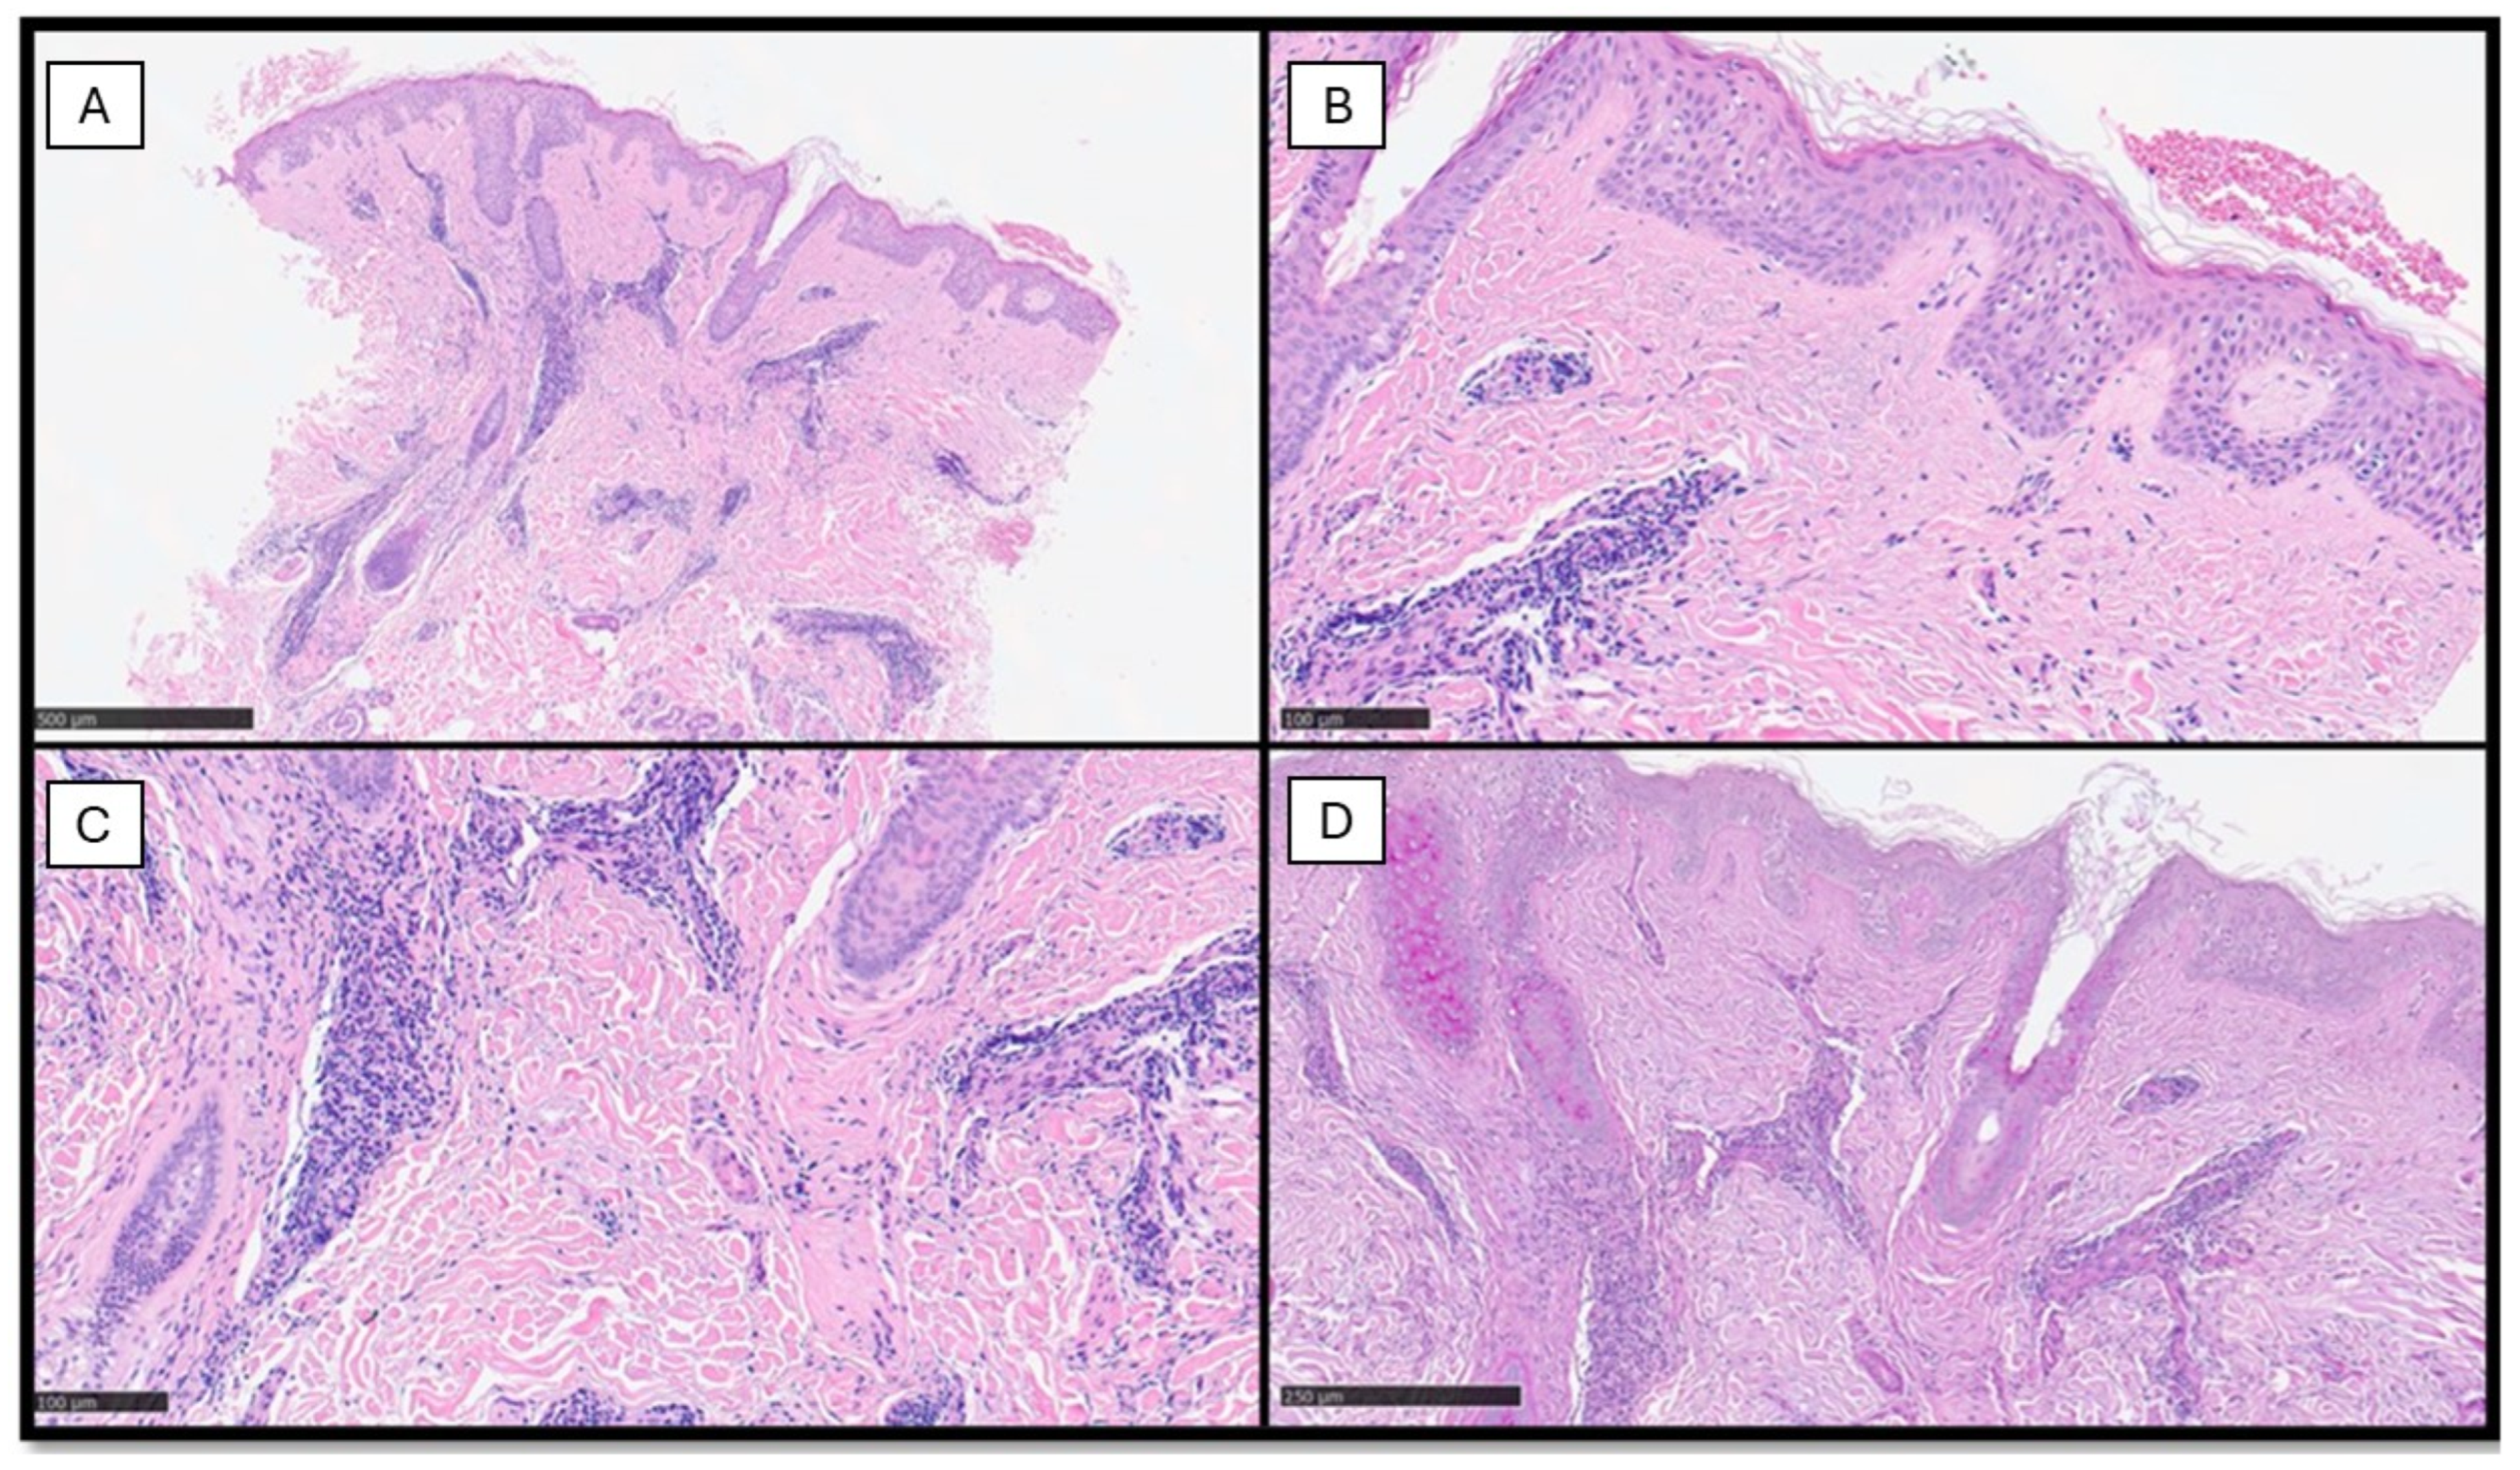
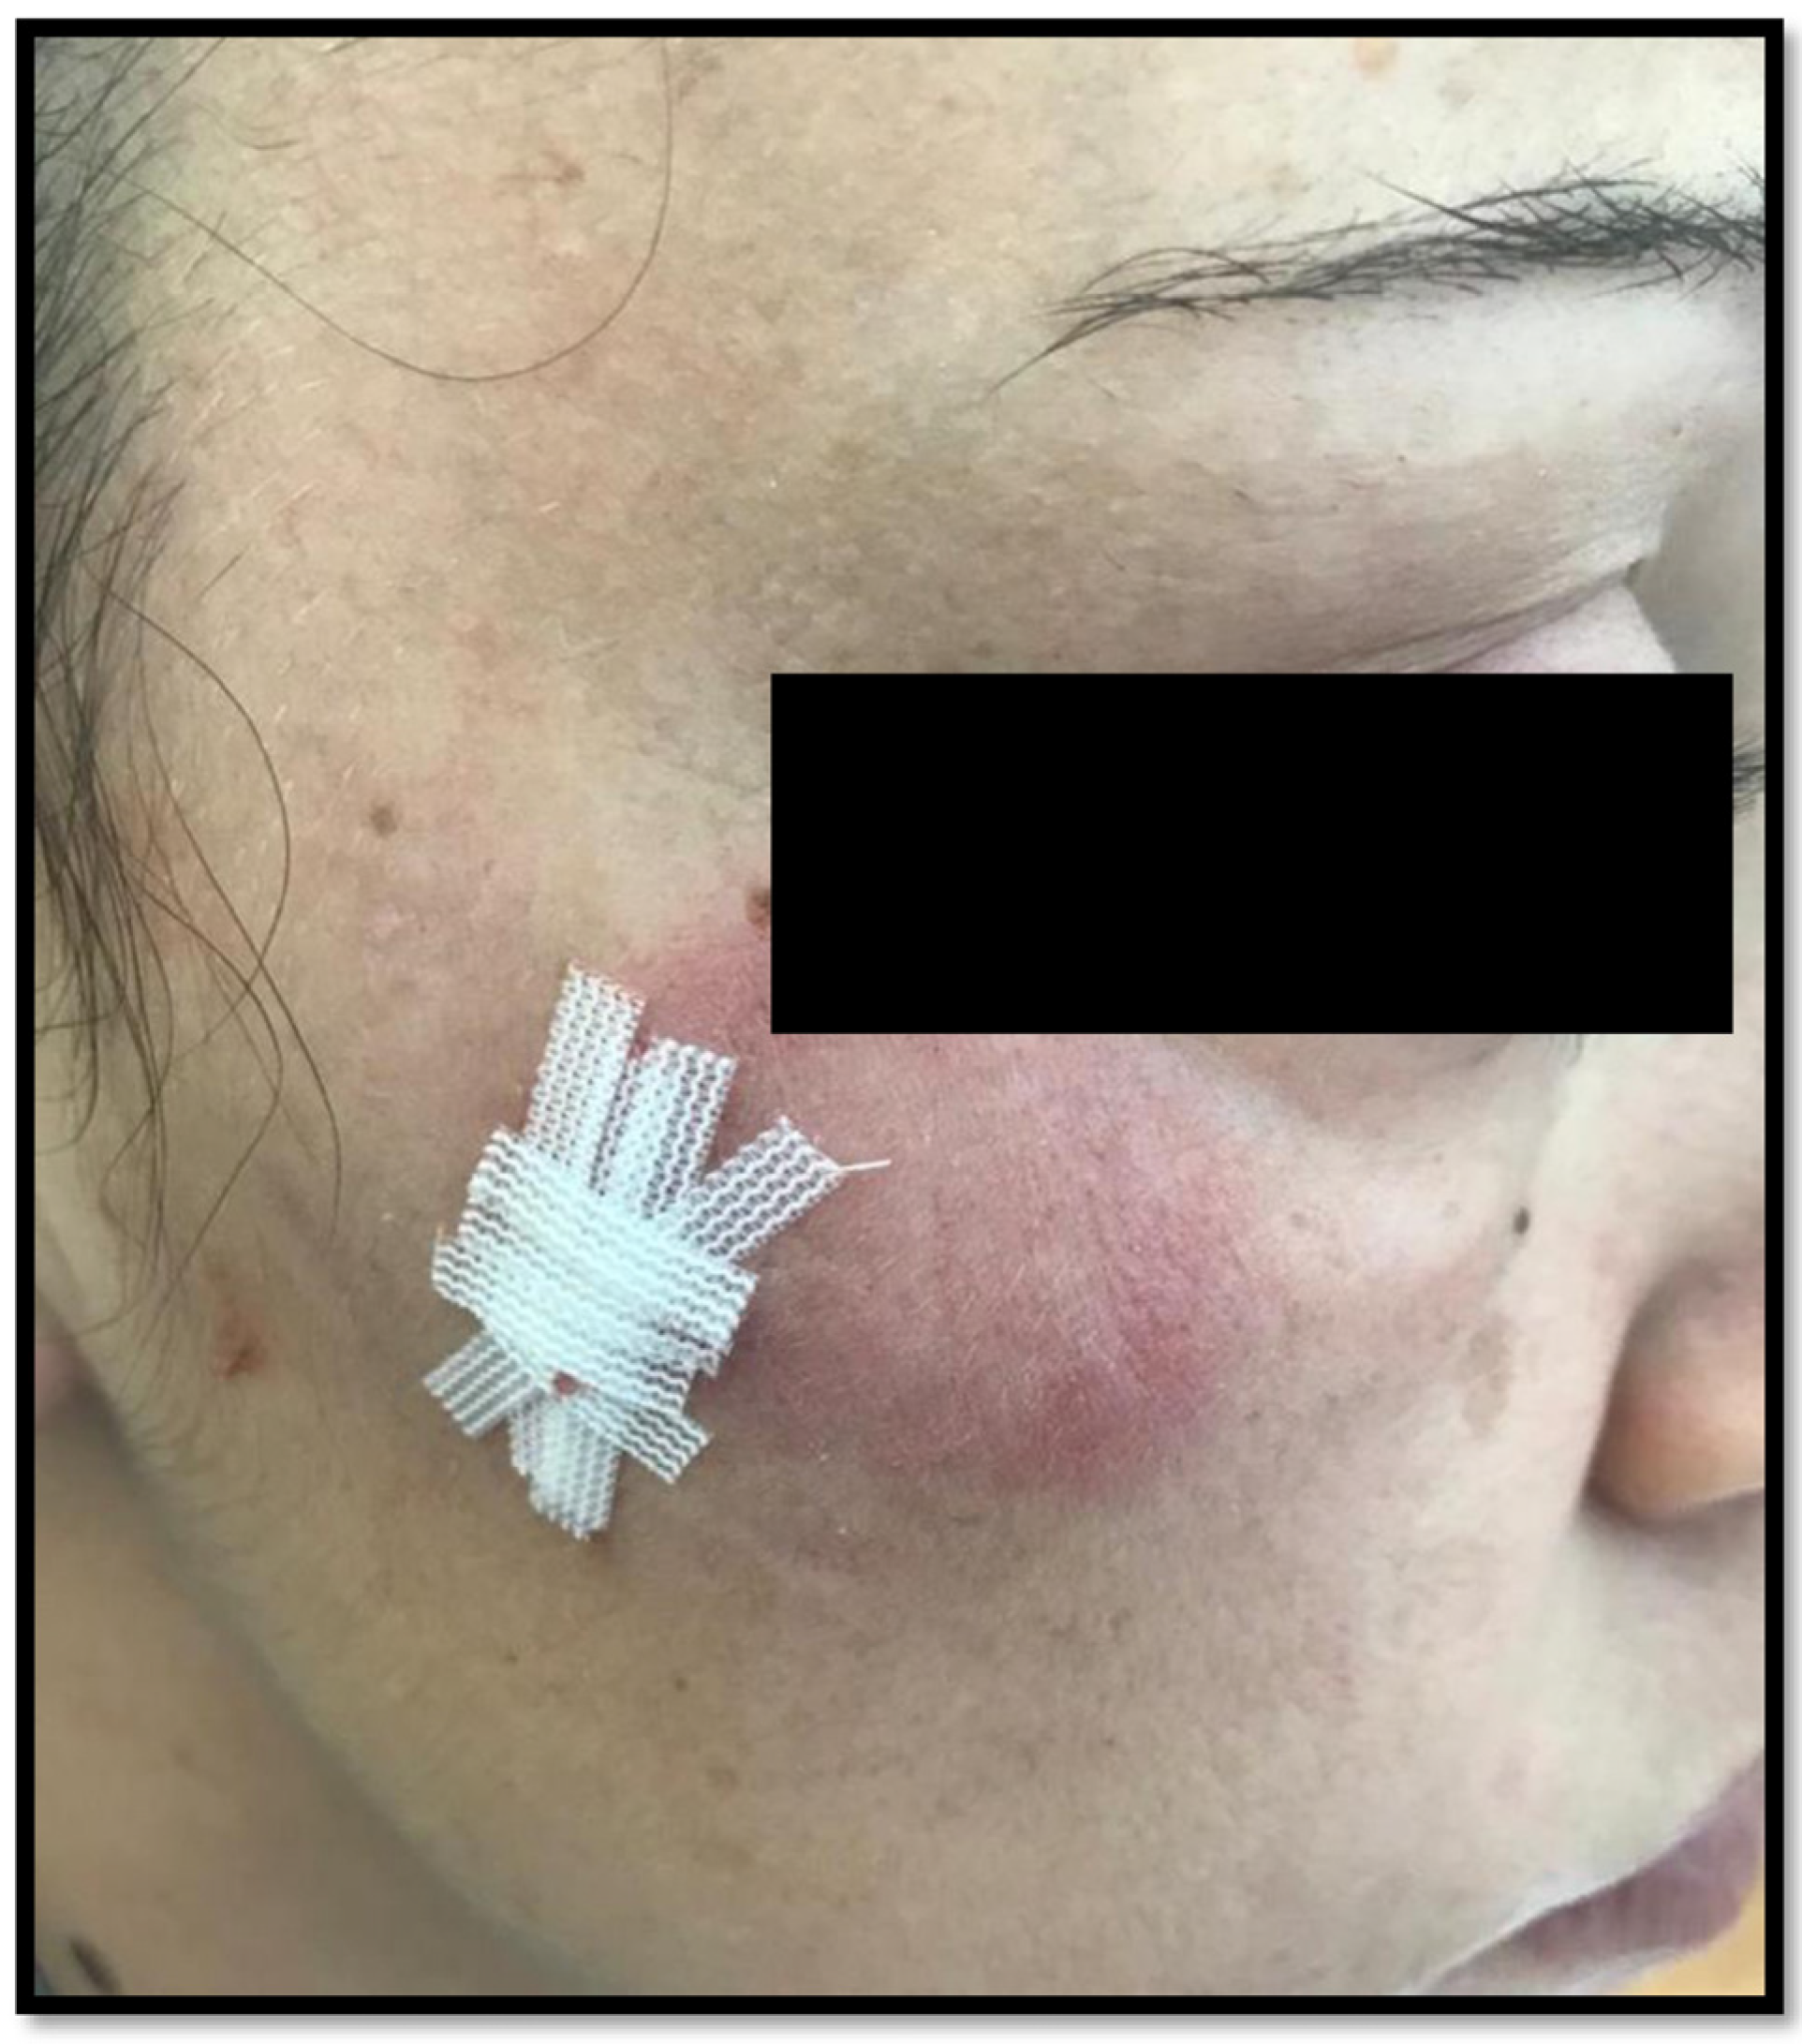
Tumid lupus is a uncommon variant of cutaneous lupus erythematosus that dermatologists barely spend time covering in residency. The lesions present as smooth, raised, edematous plaques that are typically annular or polycyclic. They show little to no scaling, which is what sets them apart from discoid lupus and makes clinical diagnosis messier than it should be. Patients notice the bumps show up on sun-exposed skin — face, chest, upper back, shoulders — and they flare specifically after UV exposure. That photosensitivity is the strongest consistent pattern, though not universal. Historically, tumid lupus was considered a subset of subacute cutaneous lupus erythematosus (SCLE). Modern classification has moved it toward being treated as its own distinct entity within the spectrum of chronic cutaneous lupus. It carries one of the highest rates of negative or borderline direct immunofluorescence among all cutaneous lupus variants, which complicates biopsy interpretation significantly. I have watched cases get misread as psoriasis, granuloma annulare, or even fungal infection because the histology lacks the classic interface dermatitis features you see in other lupus subtypes. A deep incisional biopsy is necessary. Punch biopsies often miss the perivascular and periadnexal lymphocytic infiltrate that characterizes this condition because the inflammatory cells sit deeper in the dermis than standard 4mm punches reliably capture. The pathology report will typically describe a dense superficial and deep perivascular lymphoid infiltrate with mucin deposition in the dermis. Mucin is the key. You want to see that confirmed with Alcian blue or colloidal iron stain. Without mucin demonstration, the diagnosis becomes much less secure.
ANA is positive in roughly 30 to 50 percent of cases, which is far lower than systemic lupus. That low positivity rate is why many clinicians dismiss the diagnosis when they see a negative ANA. A negative ANA does not rule out tumid lupus. Anti-Ro/SSA positivity is more common but still only present in about half of patients. When I run into a case with negative serology and ambiguous histology, I order a broad cutaneous lupus panel including ENA, dsDNA, complement levels, and a dermatology-guided workup for overlap syndromes. It takes time and money but it prevents years of misdiagnosis. I had a patient who presented with recurrent annular plaques on the chest for four years before anyone connected it to lupus. She was being treated with topical antifungals the entire time.
Treatment Approach That Actually Works
First-line treatment remains strict photoprotection and topical or intralesional corticosteroids. Sunscreen alone is not sufficient for most patients — I recommend physical blockers with zinc oxide or titanium dioxide at 20 percent concentration minimum, reapplied every two hours during outdoor exposure. The difference between weak chemical sunscreens and thick physical blockers is clinically meaningful for tumid lupus patients. This usually cuts flare frequency by about 60 to 70 percent when combined with protective clothing. Hydroxychloroquine is the standard systemic treatment. The typical dosing is 5 mg/kg/day based on real body weight, though some dermatologists push to 7 mg/kg in resistant cases. Retinal toxicity screening with octopus perimetry or spectral-domain OCT is standard before initiation and annually thereafter. About 60 to 70 percent of patients respond to hydroxychloroquine, but response can take three to six months to become apparent. Patients often discontinue the medication prematurely because they do not see improvement in the first four weeks. That is the wrong expectation. If there is no meaningful improvement after four months at therapeutic dose, switching to or adding quinacrine or methotrexate is the next step. I ran into a case recently where a patient had complete treatment failure on hydroxychloroquine at 5 mg/kg, quinacrine, and methotrexate. We tried mycophenolate mofetil at 2 grams daily and saw clearance within eight weeks. Biologics like belimumab have case report-level evidence at best for tumid lupus specifically. The literature is thin. Do not expect a miracle from the newest agent if first-line and second-line options have already failed.
Get the Full Details

Systemic Involvement Risk
The progression rate from isolated tumid lupus to systemic lupus erythematosus is generally estimated at under 5 percent, which is lower than many other cutaneous lupus subtypes. That makes it relatively favorable in terms of systemic risk. However, I have encountered a few cases where renal involvement developed after five or more years of skin-limited disease. Annual monitoring with urinalysis, serum creatinine, and a complete blood count is reasonable even when initial workup is negative. Most patients will never develop systemic disease, but the consequence of missing early renal involvement is high enough that routine surveillance is not excessive. The visible nature of the plaques on exposed skin creates significant psychological burden. Depression and anxiety screening should be part of routine follow-up, not an afterthought. Patients often request cosmetic camouflage solutions while they are waiting for systemic treatments to take effect. Semi-permanent camouflage makeup with high pigmentation coverage helps more than patients expect. It is a small practical intervention that improves daily functioning immediately. Relapse upon discontinuation of hydroxychloroquine is common. I counsel patients that this is likely a chronic condition requiring long-term management rather than a one-time treatment course. Setting that expectation upfront prevents frustration and medication abandonment later. The disease can go into prolonged remission for some patients, but predicting who will achieve that is not currently possible with available clinical tools.