Why Surface Anatomy Is The First Thing You Learn And The First Thing You Forget
Most medical students spend weeks learning where structures sit beneath the skin before they ever touch a real patient. That is backwards, but it is also how the system works. I learned superficial anatomy by actually using it, not by reading about it. The difference matters more than you would expect.Unlock The Layers Of The Body Understanding Superficial Anatomys Critical Role In Health And Medicine
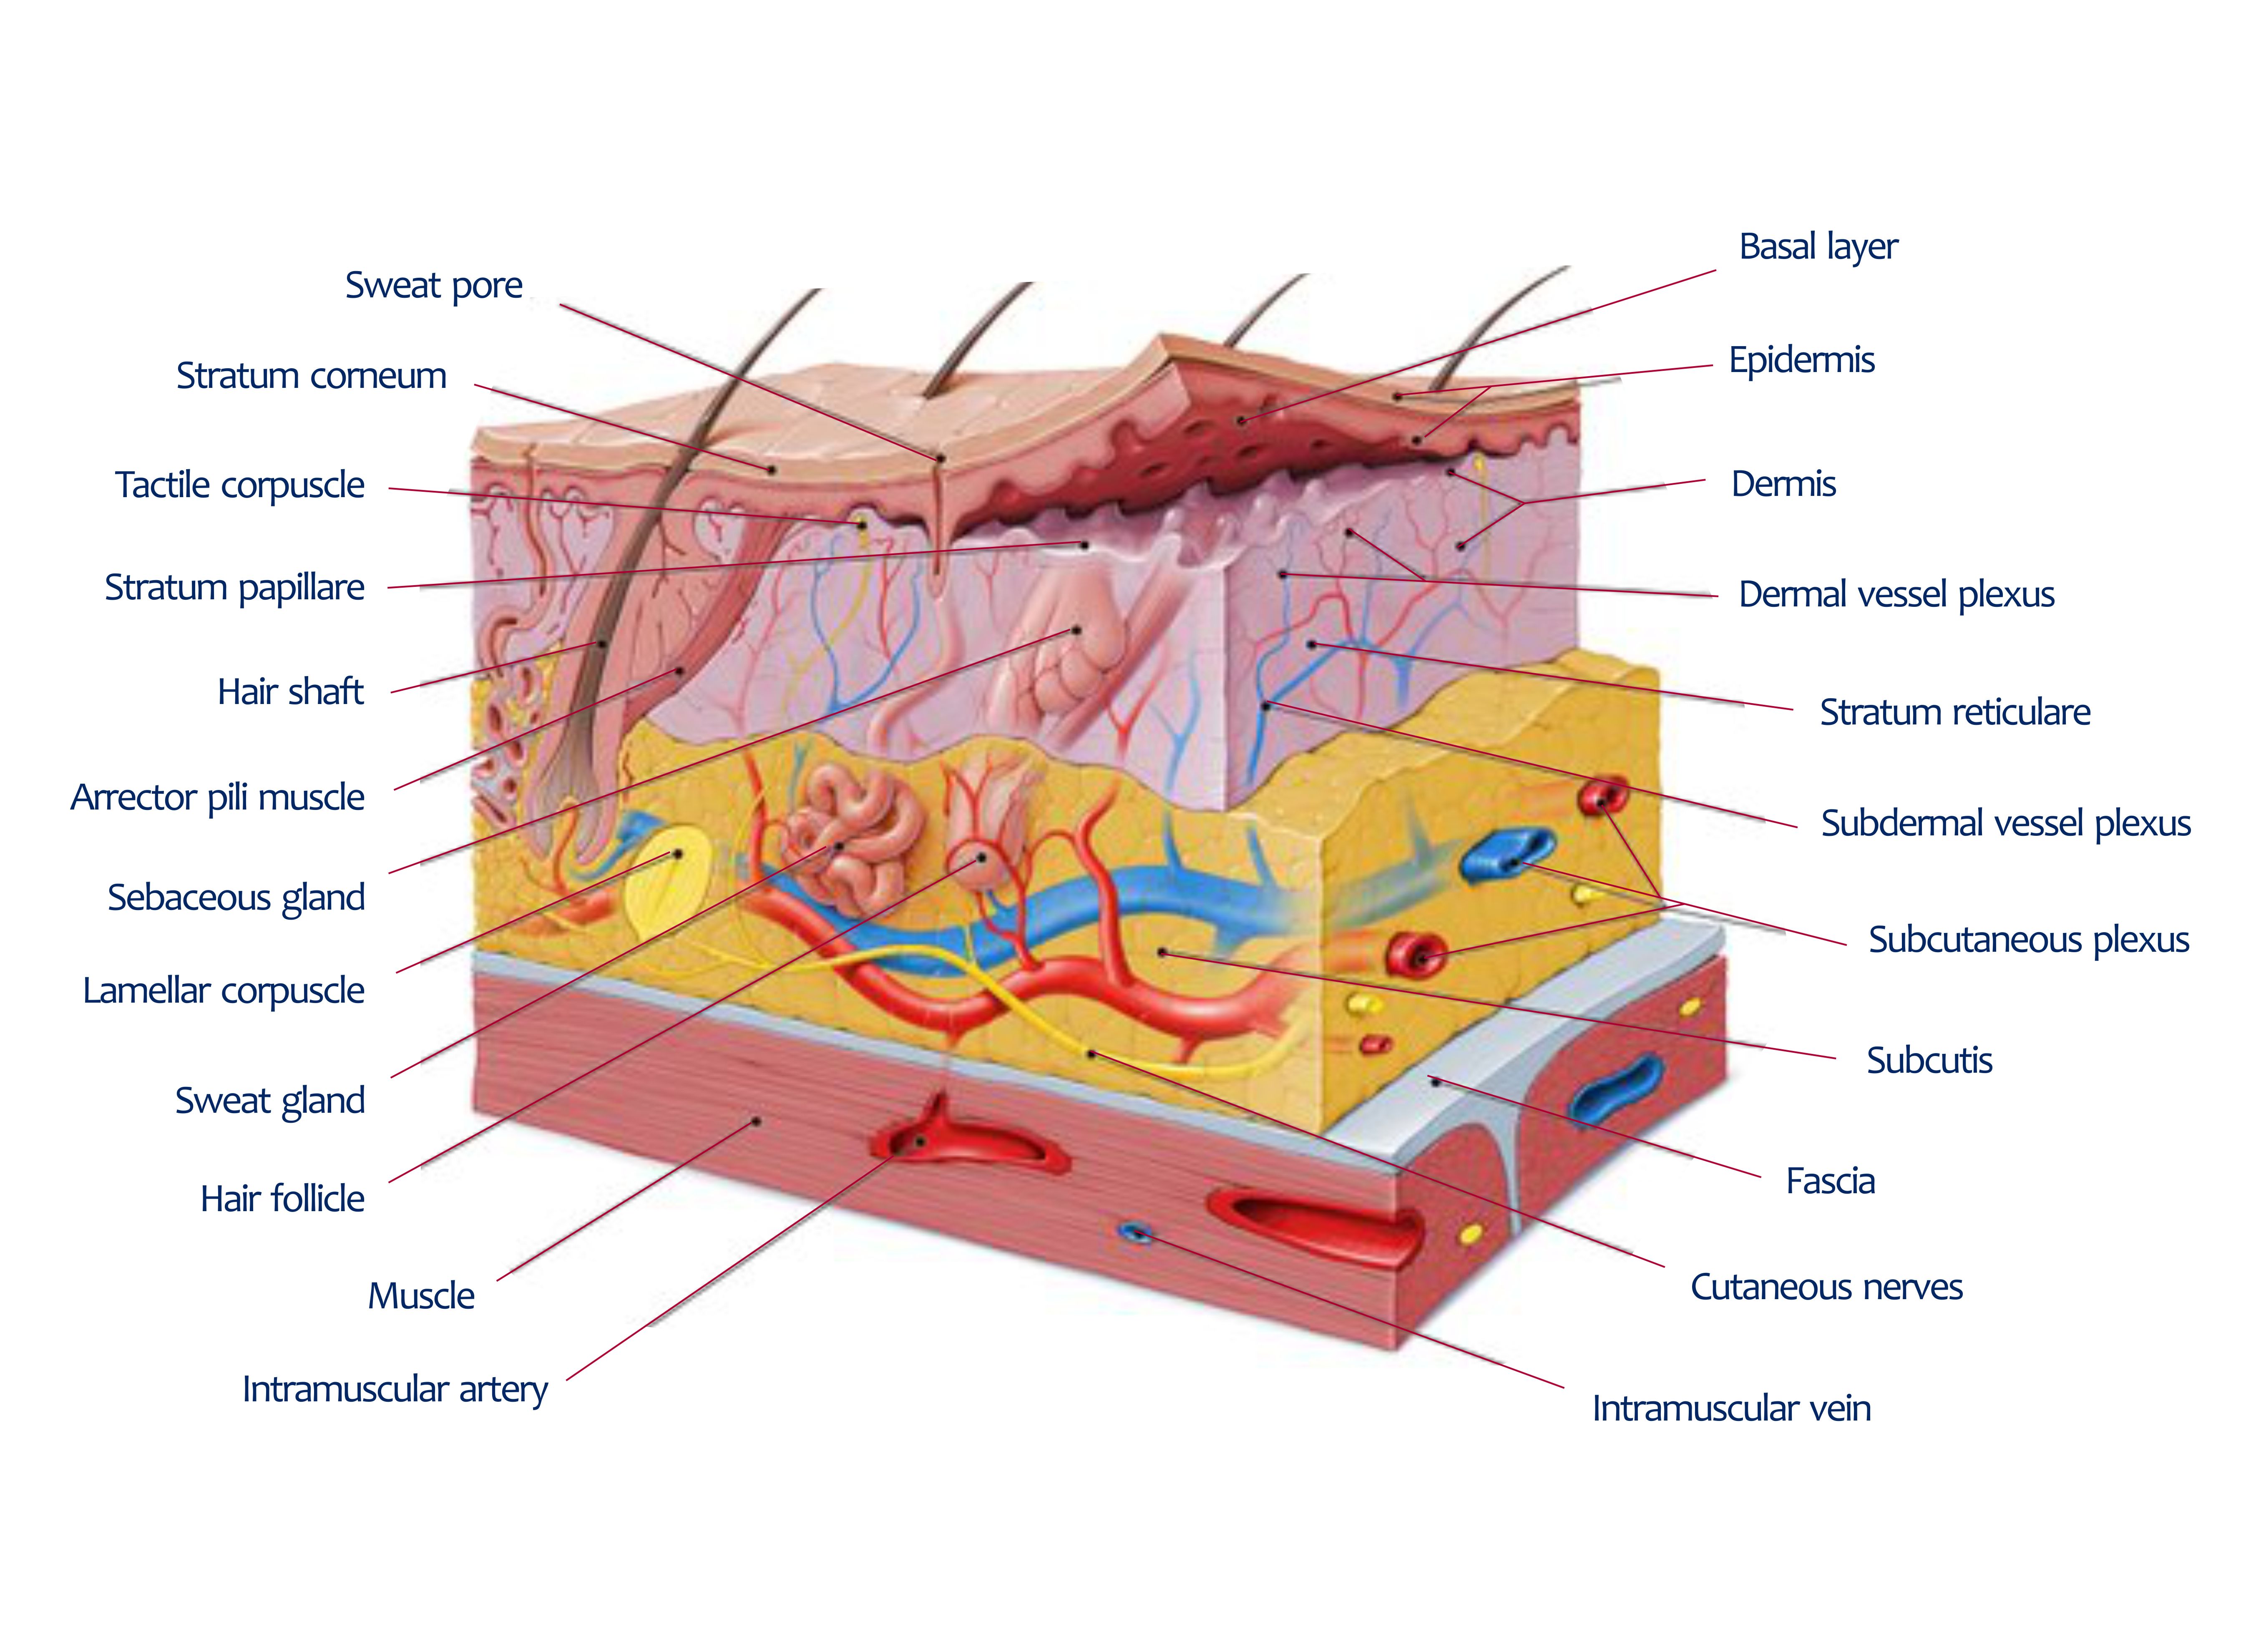
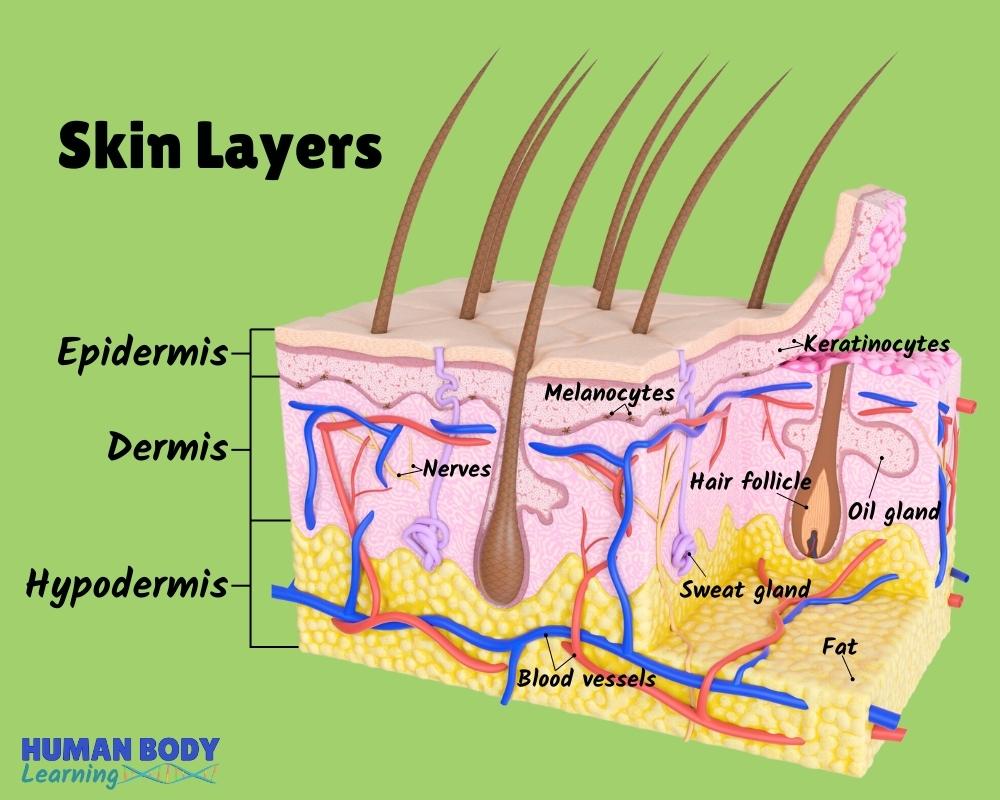
Superficial anatomy is the study of external landmarks and their relationship to deeper structures. It tells you where to place a needle, where a pulse lives under pressure, or why a certain swelling pattern means something specific. The field is not glamorous, but every physical exam depends on it. I have seen residents miss diagnoses because they relied entirely on imaging and skipped the surface landmarks that would have pointed them in the right direction within thirty seconds. The process starts with palpation. You learn to feel for bony prominences first, then trace the soft tissue relationships around them. The anterior superior iliac spine is one of those reliable anchors. Once you locate it, everything else in the lower abdomen and groin becomes easier to map. I use it constantly when I need to estimate landmark positions in patients with significant adipose tissue, where standard reference charts become unreliable. Here is something people rarely discuss openly. Superficial anatomy changes depending on body habitus, and most textbooks present idealized diagrams that assume a average frame. In practice, a patient with obesity shifts fascial planes. The same surface landmark can sit several centimeters away from where the chart says it should. I encountered this during a routine venipuncture attempt on a patient with a BMI over 35. The median cubital vein was not where it was supposed to be based on standard anatomical position. I adjusted by using the bicipital aponeurosis as a deeper tactile guide, pressing medially until I felt the fascial band, then angling the needle slightly lateral to that point. The vein was there. It saved the procedure from becoming a hematoma.
How To Actually Use Surface Landmarks In Clinical Practice
You do not need fancy equipment to practice this. A pen, a mirror, and another person to examine give you enough to start building tactile memory. Begin with your own body. Palpate your own clavicle, trace the sternoclavicular joint, then move down to the manubrium and body of the sternum. Feel the costal angles. Now repeat on someone else. The variation between bodies is where the real learning happens. When you move into procedural planning, the sequence matters. Identify the bony landmark first, then the muscle border, then the vascular or neural structure you are targeting. This order reduces your risk of hitting something you should not be hitting. I check the femoral pulse location by starting at the midpoint of the inguinal ligament, which I find by locating the anterior superior iliac spine and the pubic tubercle and drawing an imaginary line between them. Once I have the ligament, the artery sits just below and lateral to it. That method has worked consistently for me across different patient sizes. Another practical tip that does not get enough attention. Light, superficial palpation tells you about skin and subcutaneous tissue. Deeper pressure reveals muscular and fascial boundaries. Switching between the two during an exam gives you layered information quickly. I use this distinction when assessing abdominal masses. A mass that moves with the skin is likely subcutaneous. One that stays fixed when I lift the skin suggests a deeper origin. That single maneuver separates a lipoma from something requiring further imaging.
Where This Approach Breaks Down
Superficial anatomy has clear limitations. It cannot replace imaging when internal pathology is involved. A surface landmark tells you where a structure should be, not whether it has been displaced by a tumor, fluid collection, or surgical scar. I had a case where a patient presented with what appeared to be a straightforward lumbar puncture indication. The surface landmarks aligned perfectly with standard positioning, but an MRI taken afterward revealed a significantly elevated intracranial pressure with tonsillar herniation risk. Landmarks were correct. The clinical decision needed to be different. I wish we had gotten that imaging sooner. Body position also changes landmark reliability. Supine, standing, and seated positions shift fascial planes and muscle tension. A landmark that is clear in one position may disappear in another. I have found that having patients flex or extend a joint slightly can bring a subtle structure into better relief. For example, mild wrist extension makes the anatomical snuffbox more pronounced, which helps when you need to locate the radial artery for an arterial blood gas draw. The biggest practical bottleneck is time. Learning surface anatomy through palpation is slow. You might spend two or three weeks just becoming reasonably confident with thoracic landmarks before you feel comfortable using them under pressure. If you are rushing through clinical rotations, it is easy to skip this phase and fall back on memorized diagrams. That shortcut costs you later when you are on call and need to make a decision without a reference book.
Get the Full Details

If you want a faster alternative for certain procedures, ultrasound guidance bridges the gap between surface anatomy and internal visualization. It is not a replacement for knowing where things should be, but it does reduce the learning curve for needle placement. I use it selectively, usually when landmark reliability is low or when the patient has conditions that alter normal anatomy. Even then, I still rely on surface landmarks to position the transducer correctly. The two methods work together rather than one replacing the other. The skill of reading the body surface is foundational and often underestimated. It does not require expensive tools or complex training. It requires repeated hands-on practice and the willingness to notice what standard diagrams leave out. That noticing is what separates competent procedural work from guesswork.