Unlock The Future Of Healthcare Exploring Health Informatics Careers
Samantha
2026-03-08
Getting Into Health Informatics Is Easier Than You Think, But It Isn't The Job You Imagine
Most people hear "health informatics" and picture someone staring at lines of code or building fancy dashboards. The reality is messier. You spend half your time translating between clinicians who want things to look a certain way and IT teams who need specs that won't break the interface. The other half is spent fighting with data that doesn't exist where you expect it to.
I've worked in this space long enough to know the terrain. Here's what actually matters if you want to break in.
The Day-to-Day Nobody Talks About
Clinical informaticists don't sit around building algorithms. At least, not in most mid-sized hospitals and health systems. The bulk of the work involves workflow optimization, EHR configuration, and making sure the system actually supports how clinicians work instead of how administrators wish they worked.
You'll attend meetings about order sets. You'll get paged because a nurse can't find a button. You'll document every change for compliance purposes. It's technical enough to be interesting but repetitive enough to drain you if you go in expecting something else.
The pay is decent though. Entry-level roles in the US typically land between $55,000 and $75,000. Mid-career professionals with two to five years of experience pull $80,000 to $110,000. Senior roles and those with specialized skills in interoperability or data architecture can push past $130,000 depending on the market.
Unlock The Future Of Healthcare Exploring Health Informatics Careers
The career paths aren't as linear as computer science or nursing programs suggest. You don't need a dedicated informatics degree to get started. I've hired people coming out of nursing, pharmacy, health information management, and straight out of computer science. Each background brings something useful. Nurses understand clinical workflows. CS grads understand data structures. HIM people understand coding systems and compliance. The gaps are obvious but teachable.
Here's the part most career guides skip. You need to understand at least one major EHR platform intimately. Epic and Cerner dominate the market together holding roughly 70% of the hospital bed space in the United States. Being Epic-certified as an analyst in a specific module like Clarity or CPOE can fast-track you. The certification costs money and requires employer sponsorship in most cases, which is why some people get hired specifically to train up on it.
The Tools That Actually Matter
Your toolkit will include SQL at minimum. Not the fancy analytics stuff. Just basic queries to pull data, join tables, and verify that what the dashboard shows matches what's actually in the database. I once spent three weeks tracking down a discrepancy in a sepsis reporting metric that turned out to be a single field mapping error between a legacy system and an updated FHIR resource. The fix was adjusting the value set on one field. Three weeks for one field.
HL7 becomes important if you touch interfaces. Version 2.x is still the workhorse in most hospitals despite everyone agreeing it's a mess. FHIR is replacing it gradually, but you'll deal with both for years. Understanding the difference between an ADT message and a SIU message isn't trivia. It's what lets you troubleshoot why patient admissions aren't showing up in the destination system.
Excel is still king for quick analysis. Don't let anyone tell you otherwise. Power BI and Tableau matter for visualization roles, but the initial data wrangling almost always happens in spreadsheets.
A Real Problem I Handled Recently
A regional health system came to me last year with a problem they'd been struggling with for eight months. Their outpatient scheduling system wasn't syncing appointment data to the central patient registry fast enough. Clinicians were seeing outdated visit information during referrals. The vendor said it was a configuration issue. The IT team said it was a data flow issue. Both were partially right and completely unhelpful.
I traced the problem through the interface engine logs. The messages were being generated and sent successfully. They were also being acknowledged by the receiving system. But the target system was rejecting certain field combinations silently because of a validation rule that had been modified two years prior during an upgrade. The validation was failing on a specific diagnosis code pattern that only appeared in certain specialty clinics.
The workaround was straightforward once I found it. I updated the interface mapping to exclude the problematic field from that particular message type, then worked with the target system admin to relax the validation rule. Took me about four hours from starting the investigation to deploying the fix. The team had been circling it for eight months because nobody checked the interface acknowledgments closely enough to notice the silent rejections.
The Counter-Intuitive Stuff
Being technically proficient won't get you promoted in this field. Being the person who can explain to a surgeon why the order set can't work the way he wants it to will. Technical skills get you the interview. Communication skills keep the job. I've watched sharply technical informaticists stall out because they couldn't navigate the politics of changing how a department worked.
Another thing nobody mentions. Documentation is not optional. Every configuration change, every workflow modification, every exception you make needs to be documented. Not for the paperwork. For the next person who walks in when you're gone. I've inherited systems where the person who built everything had left years ago and left behind three sticky notes and a shared drive full of incomplete drafts. It slows you down enormously. Make the habit now.
Where This Field Falls Short
Health informatics isn't a clean career move. The burnout rate is higher than most people expect. You're caught between departments that have conflicting priorities and often lack the authority to enforce decisions. You'll have opinions about what should happen and very little control over whether they happen.
Small health systems, particularly rural ones, rarely have dedicated informatics roles. You'll wear too many hats. The big systems have the specialties you want but the bureaucracy to match. There's a middle ground in consulting firms and vendor companies, but those roles come with travel and client management demands that some people hate.
The certification landscape is fragmented. CAHIMS and CPHIMS through HIMSS are the standard names but they don't guarantee competence. They guarantee you passed a multiple-choice exam. Real competency comes from shipped projects and fired issues.
What Actually Gets You Hired
A bachelor's degree in anything related helps. Health informatics, nursing, biology, computer science. A master's is increasingly common for senior roles but not always required. I've seen people get hired with just experience and the right certifications bypassing the degree filter entirely in places that were desperate for bodies.
The resume hack most people miss. List specific systems and standards, not generic skills. "Epic Clarity" is worth more than "database experience." "HL7 V2.x interface troubleshooting" means something concrete to a hiring manager. "Data analysis" means nothing by itself.
Build a portfolio even if it's personal projects. A GitHub repo with SQL queries against a public dataset like MIMIC-IV shows you can work with real clinical data. MIMIC is freely available after completing a short ethics course. It's the most respected open clinical dataset and mentioning it on a resume immediately signals that you understand the domain.
The Practical Path
Start somewhere adjacent if you can. Medical scribe, clinical documentation specialist, EHR consultant, health information technician. These roles put you in front of the systems and the problems. Six to twelve months in any of them gives you more practical context than a semester of coursework.
Then pivot internally if possible. Most health systems have informatics positions and prefer promoting from within because you already understand their environment. External hires require more training on their specific workflows and configurations.
If you're coming from outside healthcare entirely, the steep part is learning the domain language. CPT codes, ICD-10, SNOMED CT, LOINC. You don't need to memorize them. You need to understand what they are, when they're used, and why getting them wrong causes billing or clinical problems. A couple of weekends with the official documentation and some practice quizzes covers the basics.
The job market for health informatics has been strong since 2020 and it's not slowing down. The Bureau of Labor Statistics projects about 20% growth through 2030, which is much faster than average. Every hospital is trying to do more with their data. Most of them are behind. That gap is where the jobs are.
Gallery Unlock The Future Of Healthcare Exploring Health Informatics Careers
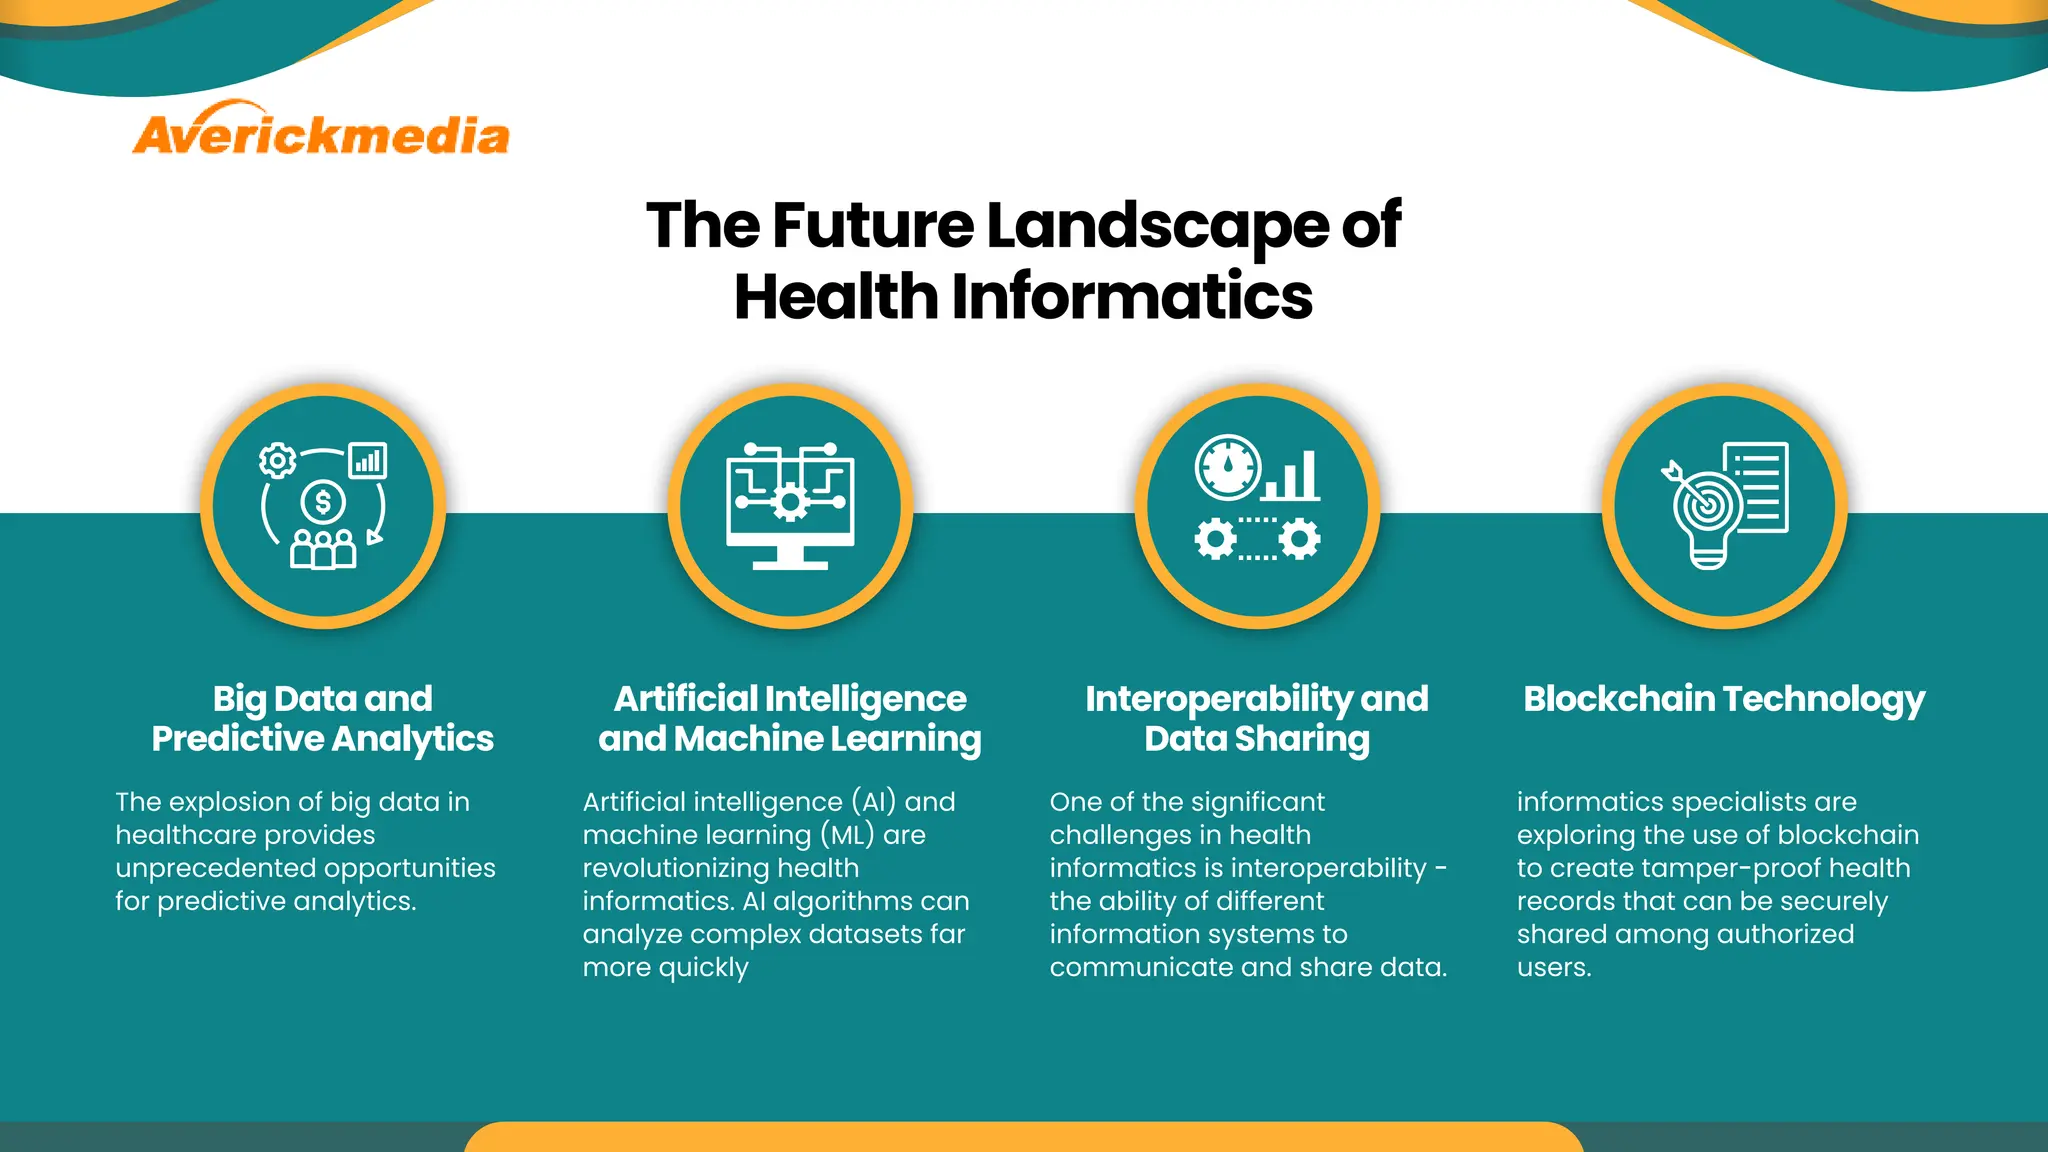
Future of Healthcare: The Impact of Health Informatics Specialists | PDF
How Is Health Informatics Changing The Future Of Healthcare - HealthPulls
Future of Healthcare: The Impact of Health Informatics Specialists | PDF
Melbourne Connect | AI and the Future of Healthcare Careers
Health Informatics Degree Key to Future for HIM Careers