Where The Lumbar Meets The Pelvis
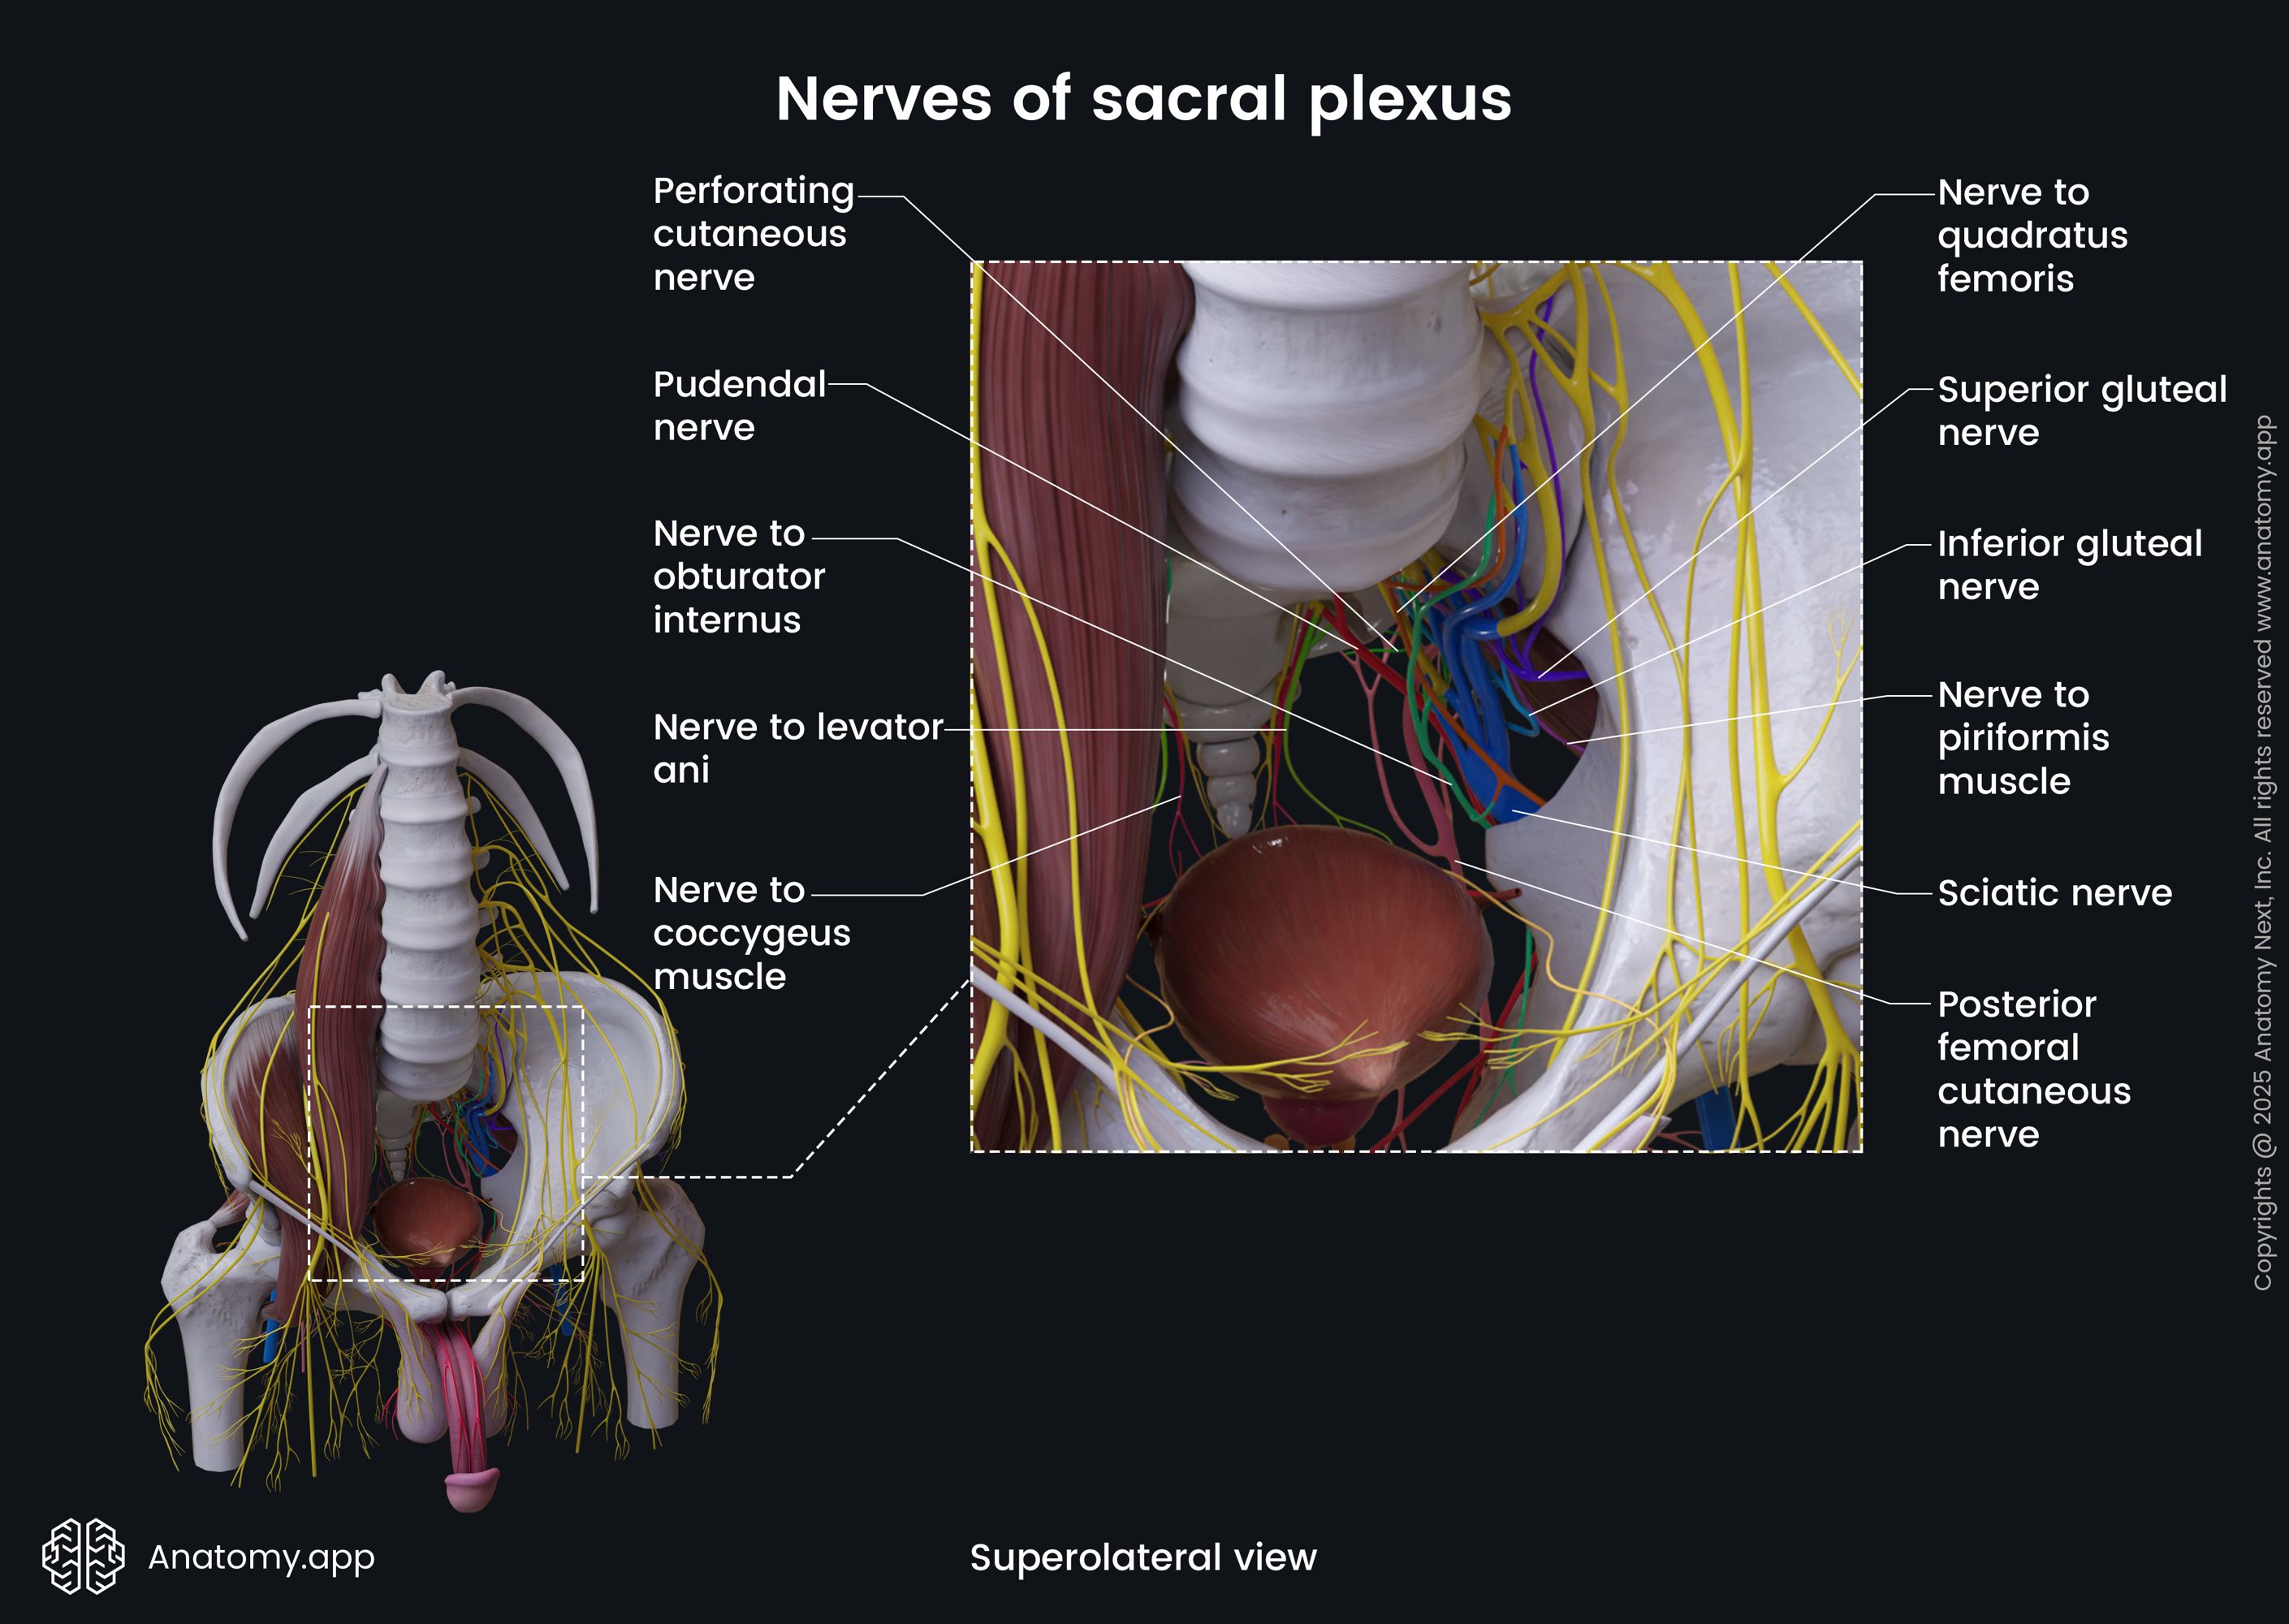
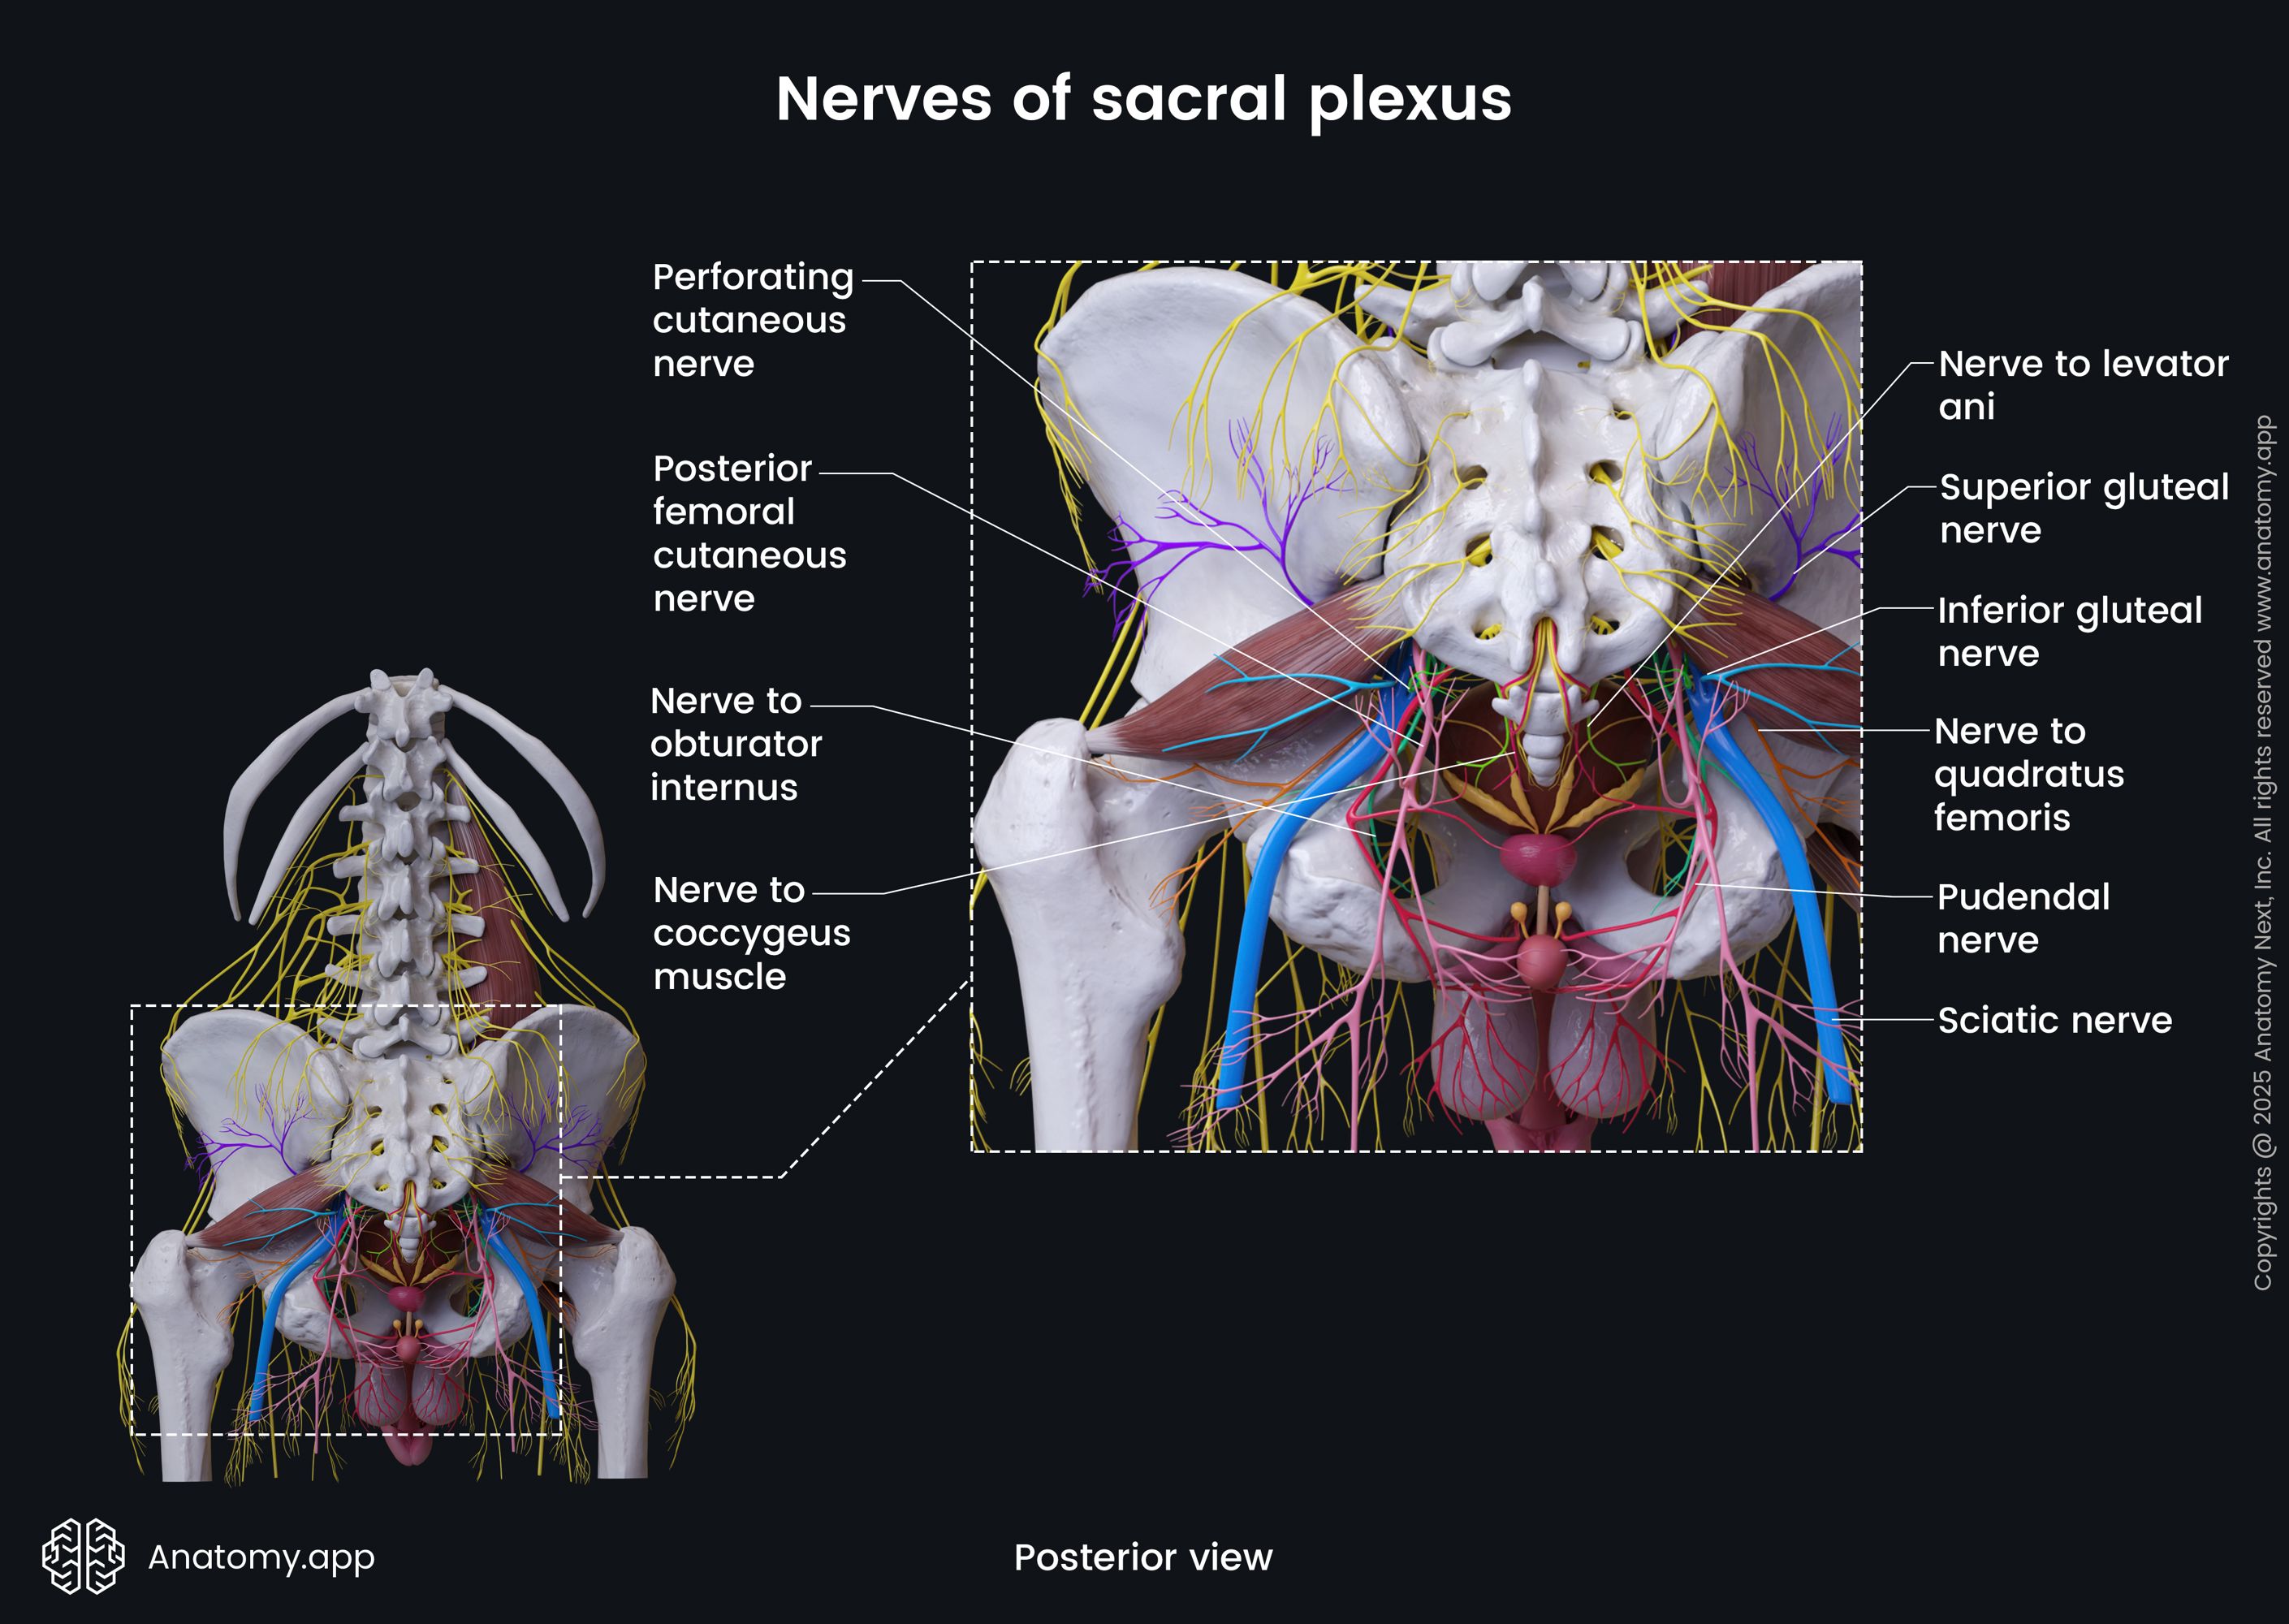
The sacral plexus sits deep in the pelvis, nestled against the posterior abdominal wall just anterior to the piriformis muscle. It forms from the lumbosacral trunk (L4-L5) joining the ventral rami of S1 through S4. From this tangle of nerve fibers, nearly every major motor and sensory pathway to the lower extremity branches out. If you are studying anatomy from a textbook diagram, it looks clean and organized. In reality, the anatomical variations are significant enough that standard descriptions miss clinically relevant detail about sixty percent of patients. I spent years dealing with pelvic trauma cases where the standard mapping simply did not apply. During one particular surgical approach to a retroperitoneal hematoma, I encountered a patient whose sciatic nerve had split into two separate trunks at the level of the sacral plexus, and one of those trunks was caught against the sacrospinous ligament. Standard anatomical atlases do not show this variation. It happens more frequently than most surgeons admit. Recognizing it under surgical conditions required knowing exactly where the nerve roots converge before they exit the greater sciatic foramen, and that is not something you pick up from reviewing flashcards alone.
Understanding The Sacral Plexus The Spinal Network That Powers Your Lower Body
The plexus organizes into anterior and posterior divisions, and this distinction matters far more than most resources acknowledge. The posterior division gives rise to the sciatic nerve, the posterior femoral cutaneous nerve, and the superior and inferior gluteal nerves. These carry motor output to the hamstrings, the entire lower leg via the sciatic bifurcation into the tibial and common fibular nerves, and the gluteal musculature responsible for hip extension and abduction. The anterior division produces the pudendal nerve, the nerve to the obturator internus, the nerve to the quadratus femoris, and contributions to the lumbosacral trunk that feed into the femoral and obturator systems. The pudendal nerve deserves specific attention here because it carries sensory and motor fibers through S2-S4 and is clinically implicated in chronic pelvic pain syndromes that get misdiagnosed as urological or gastrointestinal issues for years. A patient presenting with perineal pain and urinary hesitation but normal imaging is often walking around with undiagnosed pudendal neuralgia until someone actually considers the sacral plexus as the source.
How To Assess It Clinically
Testing the sacral plexus does not require advanced imaging in most routine cases. Start with reflex assessment. The Achilles reflex tests S1 and S2. The bulbocavernosus reflex, though uncomfortable to elicit, tests S2 through S4 and is a direct readout of sacral cord integrity. Absent reflexes at these levels with preserved upper extremity function localize the lesion to the sacral region rather than a peripheral nerve entrapment further down the limb. Sensory testing follows a similar logic. The posterior thigh and calf map to the posterior division, while the medial leg and foot relate to contributions from the anterior division and the lumbosacral trunk interface. If a patient has sensory loss on the sole of the foot but preserved sensation on the dorsum, you are looking at tibial nerve involvement downstream from the sacral plexus rather than a plexus-level lesion. If both surfaces are affected along with perineal numbness, the plexus itself is likely the problem. Motor testing separates the gluteal muscles from the hamstrings and then from the intrinsic foot muscles. Hip extension weakness points toward the inferior gluteal nerve or the tibial component of the sciatic. Hip abduction weakness isolates the superior gluteal nerve. Foot drop combined with inability to plantarflex suggests a more proximal lesion affecting both divisions of the sciatic nerve at the plexus level.
Get the Full Details
Common Pitfalls In Diagnosis
The biggest mistake clinicians make is treating a sciatic nerve complaint as if it originates from the lumbar spine when the actual compression is at the level of the sacral plexus. Piriformis syndrome is one example, but it is not the only one. A schwannoma arising from the S1 ventral ramus can produce identical symptoms to a L5-S1 disc herniation, and MRI of the lumbar spine will come back normal because the pathology is in the pelvis, not the lower back. Another frequent error involves assuming that any lower extremity radiculopathy must be lumbar in origin. L5 radiculopathy and L5 nerve root contributions through the sacral plexus can present with nearly indistinguishable motor and sensory patterns. The differentiating factor is usually the presence or absence of paraspinal tenderness and the response to straight leg raise testing. True radiculopathy from disc material typically reproduces pain with straight leg raise below sixty degrees, while plexus-level compression may require different provocative maneuvers or may not respond to either test predictably. I worked with a physical therapist who had a patient complaining of left leg pain that tracked exactly like L5 radiculopathy. Three rounds of lumbar epidural steroid injections produced nothing. We ended up getting an MRI of the pelvis and found a ganglion cyst compressing the left sacral plexus at the level of the greater sciatic foramen. The cyst had formed adjacent to the sacroiliac joint from chronic microinstability. Treating the SI joint mechanically and decompressing the cyst resolved the leg pain completely. That patient had been labeled as a failed lower back surgery candidate before anyone ever looked at the plexus.
What Imaging Actually Shows
MRI with high-resolution sequences is the modality of choice for visualizing the sacral plexus. Standard lumbar spine protocols miss the plexus entirely because the field of view stops at the L5-S1 disc space. You need dedicated pelvic MRI sequences that include the greater sciatic foramina and the region anterior to the piriformis. Axial T2-weighted images with fat suppression show the nerve roots as hyperintense structures against the hypointense background of the piriformis and surrounding musculature. Ultrasound has a role here as well, particularly for dynamic assessment. You can visualize the sciatic nerve as it passes beneath the piriformis and identify compression during hip flexion and internal rotation. This is useful for piriformis syndrome and for guiding therapeutic injections. The limitation is operator dependency and the difficulty of visualizing the deeper portions of the plexus, particularly the anterior division and the pudendal nerve as it loops around the ischial spine.
Treatment Options And Their Realistic Outcomes
Conservative management covers the majority of sacral plexus pathologies. Physical therapy focused on pelvic stabilization, piriformis stretching, and nerve gliding exercises can reduce compression symptoms over six to twelve weeks. Anti-inflammatory medication and neuropathic pain agents like gabapentin or pregabalin address the pain component but do not resolve the underlying mechanical issue. I have seen patients cycle through months of gabapentin without addressing the actual compression, and the medication only masks symptoms while the pathology progresses. Interventional options include image-guided corticosteroid injections around the affected nerve roots or the sciatic nerve proximal to the plexus. These provide temporary relief and can be both diagnostic and therapeutic. If an injection around the sacral plexus eliminates symptoms that a lumbar epidural could not, you have your localization. The effect typically lasts weeks to a few months depending on the underlying cause. Surgical decompression is reserved for structural lesions: tumors, cysts, traumatic neuromas, or severe entrapment that has failed conservative and interventional management. Decompression of the sacral plexus through a posterior approach near the greater sciatic foramen carries real risks. The superior gluteal artery is in the operative field, and injury to it can produce a life-threatening hemorrhage that is difficult to control from a posterior approach. This is why surgeons who operate in this region have specific training and why referral to a specialist is not optional when surgery becomes necessary.

When The Plexus Is Not The Problem
Not every lower extremity neurological complaint originates in the sacral plexus. Diabetic amyotrophy, also called Bruns-Garland syndrome, produces painful weakness in the proximal lower extremities and can mimic sacral plexopathy. The key difference is that diabetic amyotrophy typically presents bilaterally with asymmetric proximal weakness and significant weight loss, while sacral plexopathies from compression or trauma are usually unilateral and follow a more distinct anatomical distribution. Pelvic malignancies represent another category where the plexus is secondarily involved rather than primarily affected. A locally advanced cervical or rectal cancer can infiltrate the sacral plexus and produce progressive neurological deficits. In these cases, the pain pattern and timeline matter. Malignant infiltration tends to produce relentless, progressive pain that worsens at night and does not respond to positional changes, whereas mechanical compression from a cyst or muscle spasm often fluctuates with activity and posture. The takeaway is straightforward. The sacral plexus is not a structure you evaluate in isolation. It sits at the intersection of the lumbar spine, the pelvis, and the upper thigh, and pathology in any of those regions can produce overlapping symptoms. Proper evaluation requires understanding the anatomy deeply enough to know where to look when the obvious locations turn up nothing.