What actually happens when kidneys fail to clear toxins
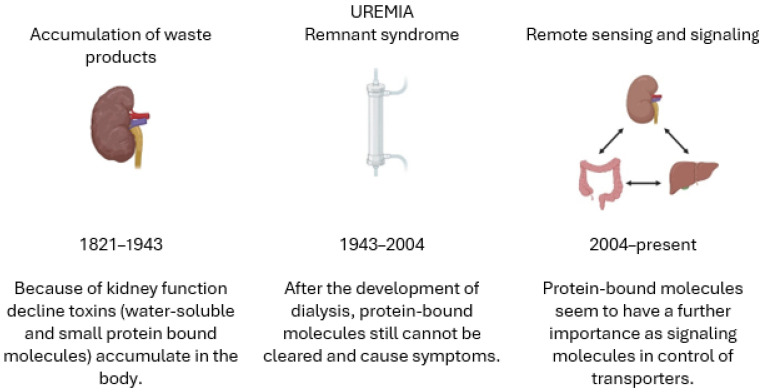
Uremia is not a single disease. It is the clinical syndrome that develops when glomerular filtration drops below a level sufficient to maintain internal homeostasis. In practice this means waste products accumulate, electrolyte balance breaks down, and hormonal dysregulation follows. The term itself comes from the Greek words for urine and blood, which is fairly literal. Uremia sits at the far end of chronic kidney disease progression, typically when the estimated glomerular filtration rate falls below 15 mL/min/1.73 m², though individual patients cross into symptomatic territory at different thresholds depending on their muscle mass, comorbidities, and rate of decline. I spent years managing dialysis patients, and the thing most people get wrong is treating uremia as one uniform condition. It is not. The risk profile changes dramatically depending on whether you are looking at an acute kidney injury patient who has been on a ventilator for three weeks with rising BUN, or a 72-year-old diabetic who has been sliding into stage 5 CKD over five years. The uremic milieu in those two people looks very different, and the complications you watch for are not identical. The risks are substantial and multi-system. Uremic pericarditis occurs in roughly 5 to 10 percent of patients who reach end-stage renal disease without adequate dialysis. It is not a minor finding. It carries a meaningful risk of hemorrhagic effusion and cardiac tamponade. I had a patient once who presented with pleuritic chest pain and was initially misdiagnosed with pneumonia because the pericardial friction rub was subtle and masked by tachypnea. An urgent bedside echocardiogram revealed a moderate effusion with early tamponade physiology. We started emergent hemodialysis and the effusion resolved over 48 hours. If we had waited another day the outcome would have been worse.
Bleeding diathesis is another major risk. Uremia impairs platelet function through multiple mechanisms including interference with von Willebrand factor binding and altered platelet adhesion. Standard coagulation panels like PT and PTT are typically normal, which is misleading. The bleeding time or PFA-100 closure time is what actually reflects the problem. Desmopressin gives a temporary improvement in platelet function for about six to eight hours, but it is not a long-term solution. Cryoprecipitate or conjugated estrogen therapy are options for refractory cases. I have seen patients with uremic bleeding present as GI hemorrhage or intracranial bleed before the platelet dysfunction was recognized, which is why routine assessment of bleeding risk matters more than checking a basic coagulation panel. Neurological complications range from subtle cognitive slowing to overt uremic encephalopathy with asterixis, myoclonus, and seizures. Peripheral neuropathy develops insidiously and is often the first sign in patients who are delaying dialysis initiation. Sleep disturbances are nearly universal and poorly treated. The restless leg syndrome connection to iron deficiency and uremic toxin accumulation is well established but frequently overlooked. Metabolic acidosis is a constant companion. The kidneys cannot excrete the daily acid load, and bicarbonate buffers get depleted. This accelerates muscle wasting and worsens bone disease through calcium leaching. Hypertension and volume overload follow predictable patterns when sodium and water excretion fail. Hyperkalemia is the most immediately lethal risk, particularly in patients who are still making some urine and think they are safe. I lost a patient to fatal hyperkalemia because he refused dietary potassium restriction and stopped checking his labs after feeling better on temporary dialysis. He was stable for two weeks and then collapsed at home. The potassium was 8.2.
Now the benefits side of this is unusual to discuss because uremia itself has no benefits. What people usually mean is the benefit of recognizing and treating uremia early. Timely dialysis initiation, kidney transplantation, and even conservative management strategies when dialysis is not appropriate all alter the risk trajectory significantly. Transplantation eliminates the uremic state entirely and reverses many of the complications within weeks. Dialysis replaces roughly 10 to 15 percent of normal kidney function, which is enough to prevent the worst outcomes but not enough to fully normalize the biochemistry. That gap between adequate dialysis and true renal function is where many complications persist. There is a counter-intuitive point that beginners miss. Lowering the BUN and creatinine quickly does not always improve outcomes. Rapid osmotic shifts during the first few dialysis sessions can cause dialysis disequilibrium syndrome, particularly in patients whose baseline BUN is very high. I have seen cerebral edema develop after an aggressive first hemodialysis run. The workaround is straightforward: start with short, gentle sessions at lower blood flow rates and use sodium profiling. Most centers now do this routinely, but it is worth noting when a new provider suggests starting with full 4-hour sessions on day one. Another nuance is that not all "uremic symptoms" are caused by uremia itself. Fatigue in end-stage renal disease patients is multifactorial. Anemia of chronic disease, iron deficiency, sleep apnea, depression, and residual kidney function all contribute. Assuming every tired patient needs earlier dialysis because their BUN is slightly elevated leads to premature initiation, which carries its own risks including vascular access complications, infections, and cardiovascular strain from dialysis itself. The timing of dialysis start is one of the most debated topics in nephrology, and the NIDICC and DIALYSIS trials showed no mortality benefit to early initiation versus waiting for clear clinical indications.
Get the Full Details
The benefits of adequate uremia management extend beyond survival. Quality of life improves substantially once pruritus is controlled, acidosis is corrected, and dialysis adequacy targets are met. Kt/V above 1.2 per session and urea reduction ratio above 65 percent are the standard adequacy benchmarks. Patients who consistently meet these targets have better nutritional status and fewer hospitalizations. The downside is that achieving and maintaining these numbers requires consistent treatment, reliable vascular access, and frequent lab monitoring, which is a lot to ask of patients dealing with comorbid diabetes, heart failure, and limited social support. Uremic gastritis and nausea affect nearly half of untreated stage 5 patients and significantly impact oral intake. Antiemetics help but do not address the underlying motility issue caused by autonomic neuropathy. Small frequent meals and early dietary protein restriction before dialysis begins can slow progression and reduce symptom burden, though protein intake must be carefully balanced against malnutrition risk once dialysis starts. The transition from conservative management to dialysis nutrition is where many patients lose weight rapidly, and that weight loss predicts worse survival independent of other factors. Phosphate control deserves more attention than it gets. Hyperphosphatemia drives secondary hyperparathyroidism and vascular calcification. The calcification process is not reversible with treatment. I have seen lumbar spine CT scans of dialysis patients where the aorta and coronary arteries looked like chalk pipes. This increases cardiovascular mortality independently of traditional risk factors. Sevelamer and lanthanum are non-calcium-based binders that do not contribute to calcification, but they are expensive and require taking multiple pills with every meal. Many patients struggle with adherence. Calcium-based binders are cheaper but carry the calcification risk, especially in patients with elevated PTH and phosphate who are already on vitamin D analogs.
Anemia management with ESA therapy and iron supplementation has improved survival but is not without risk. Stroke and thrombotic events increase at higher hemoglobin targets. The CHOIR and CREATE trials showed that targeting hemoglobin above 13 g/dL provided no benefit and may cause harm. Most clinicians now aim for 10 to 11.5 g/dL. Iron deficiency remains underrecognized in dialysis patients because ferritin is an acute phase reactant and can be falsely elevated during inflammation. TSAT below 20 percent is a more reliable indicator of functional iron deficiency, but even TSAT has limitations in the context of chronic inflammation. The bottom line is that uremia is a complex multisystem disorder and understanding the risks and benefits requires looking beyond laboratory values. The clinical picture matters more than any single number. Dialysis replaces some function but introduces its own risks. Transplantation is the closest thing to a cure but carries immunosuppression risks and organ scarcity limits access. Conservative management without dialysis is a valid path for selected patients and requires careful symptom management to be humane. The worst outcome is usually not the uremia itself but the complications that arise from delayed recognition or incomplete treatment. Monitoring should be regular, comprehensive, and adjusted to each patient's trajectory rather than applied as a rigid protocol.