What PTCA Actually Is, And Why It Matters When The Door Is Closing
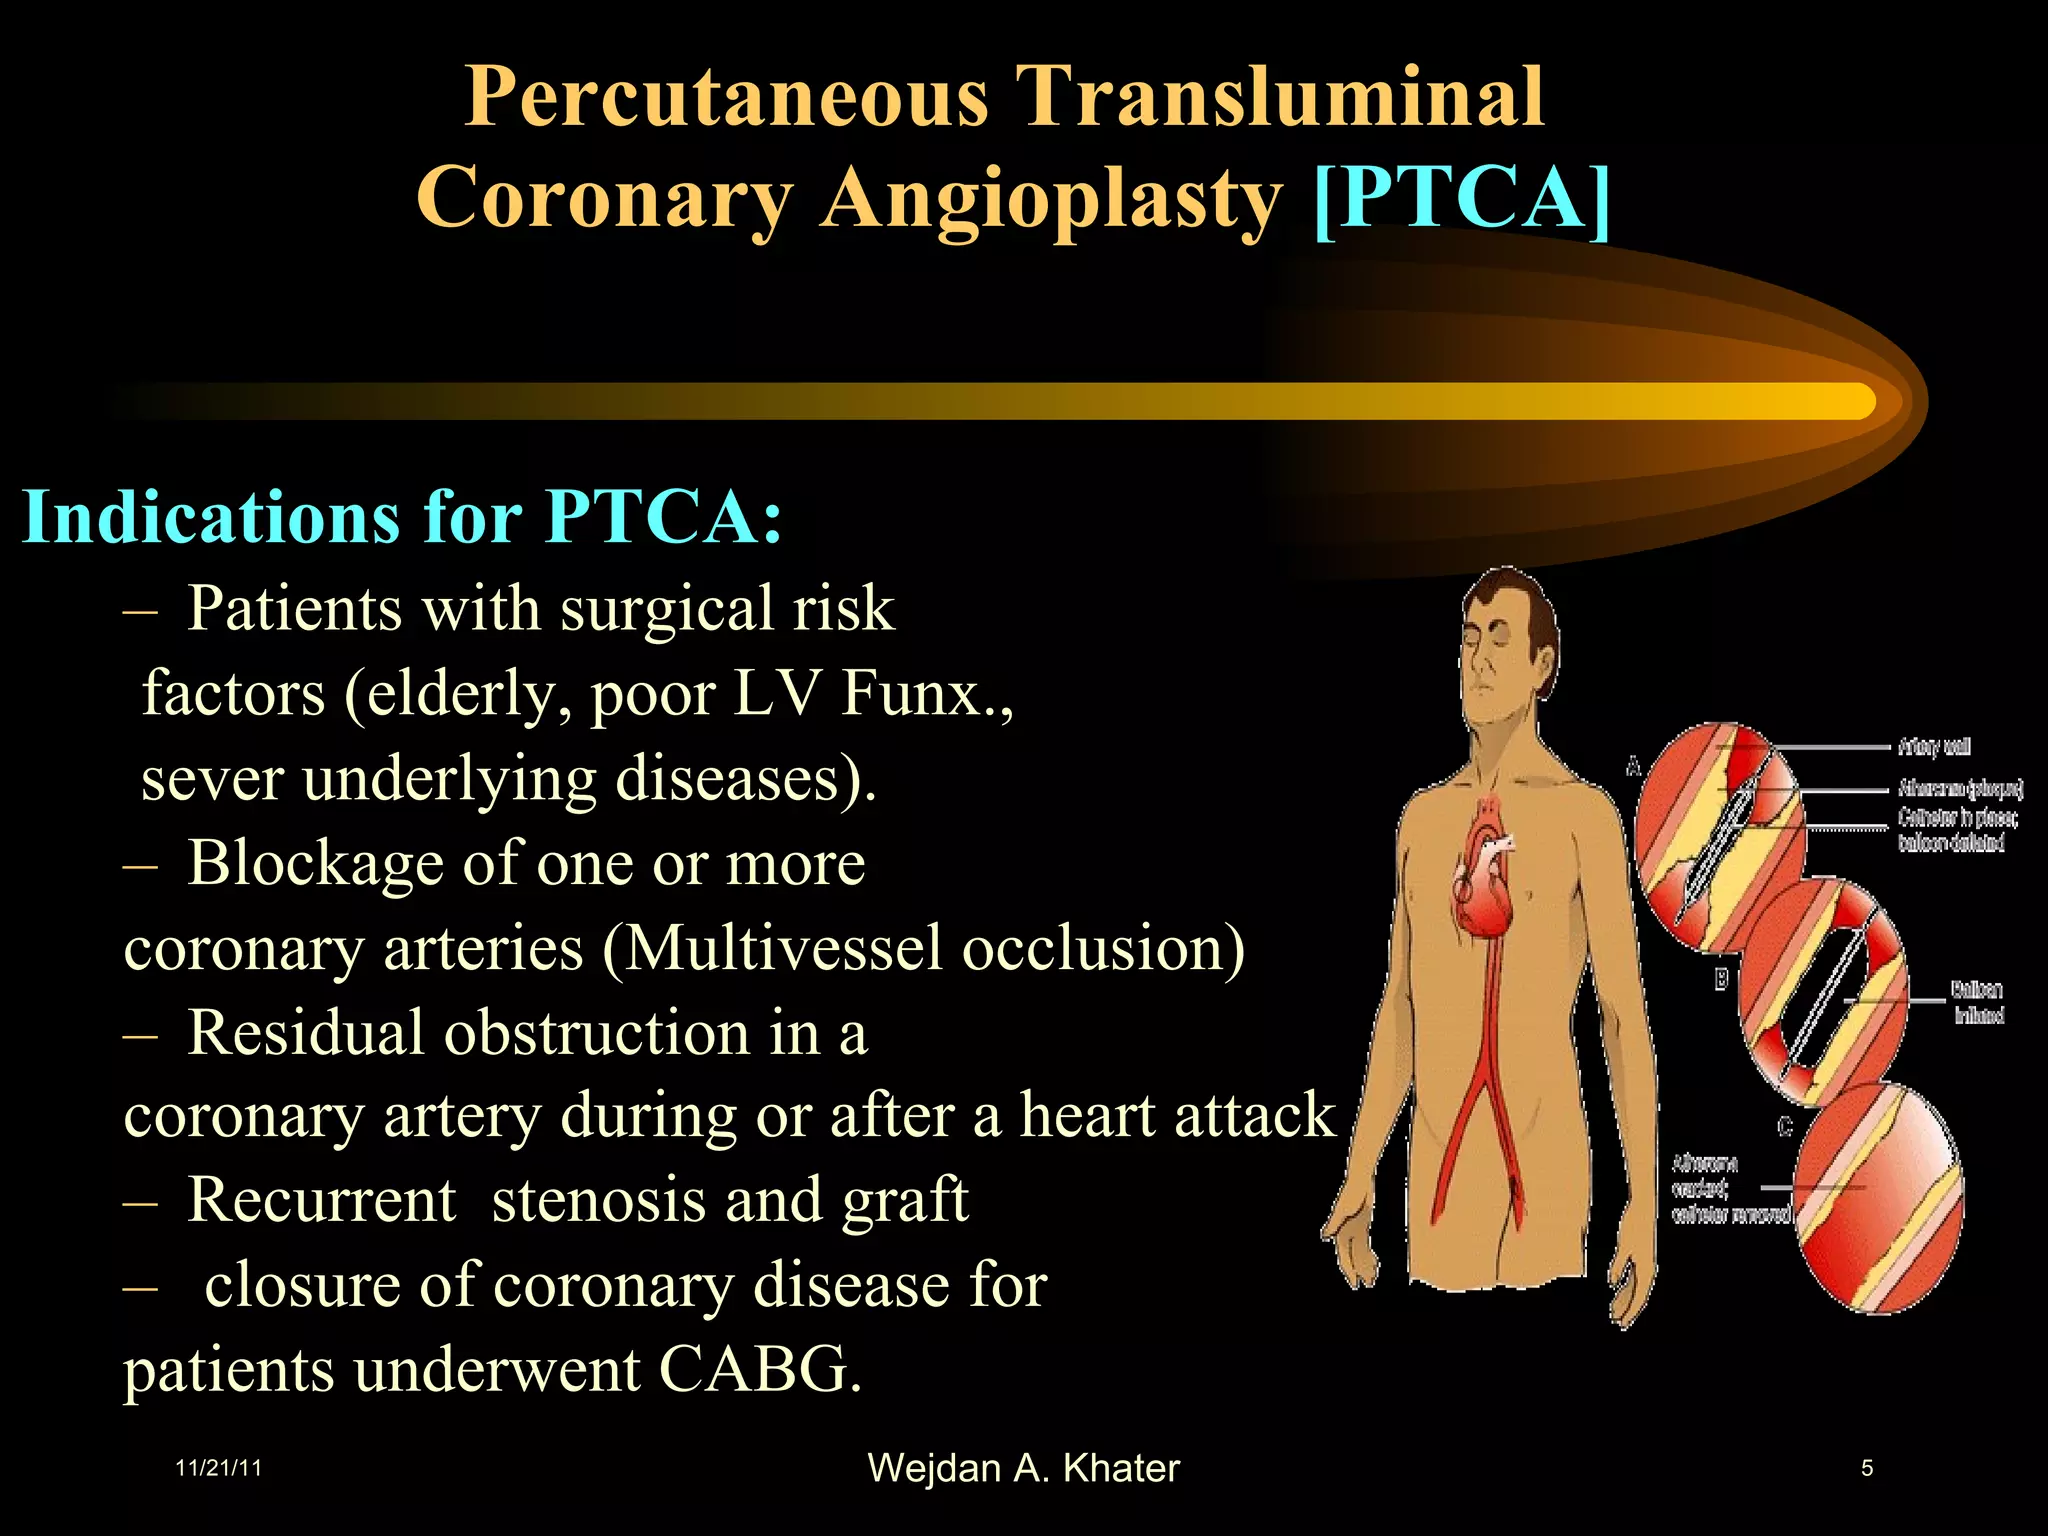
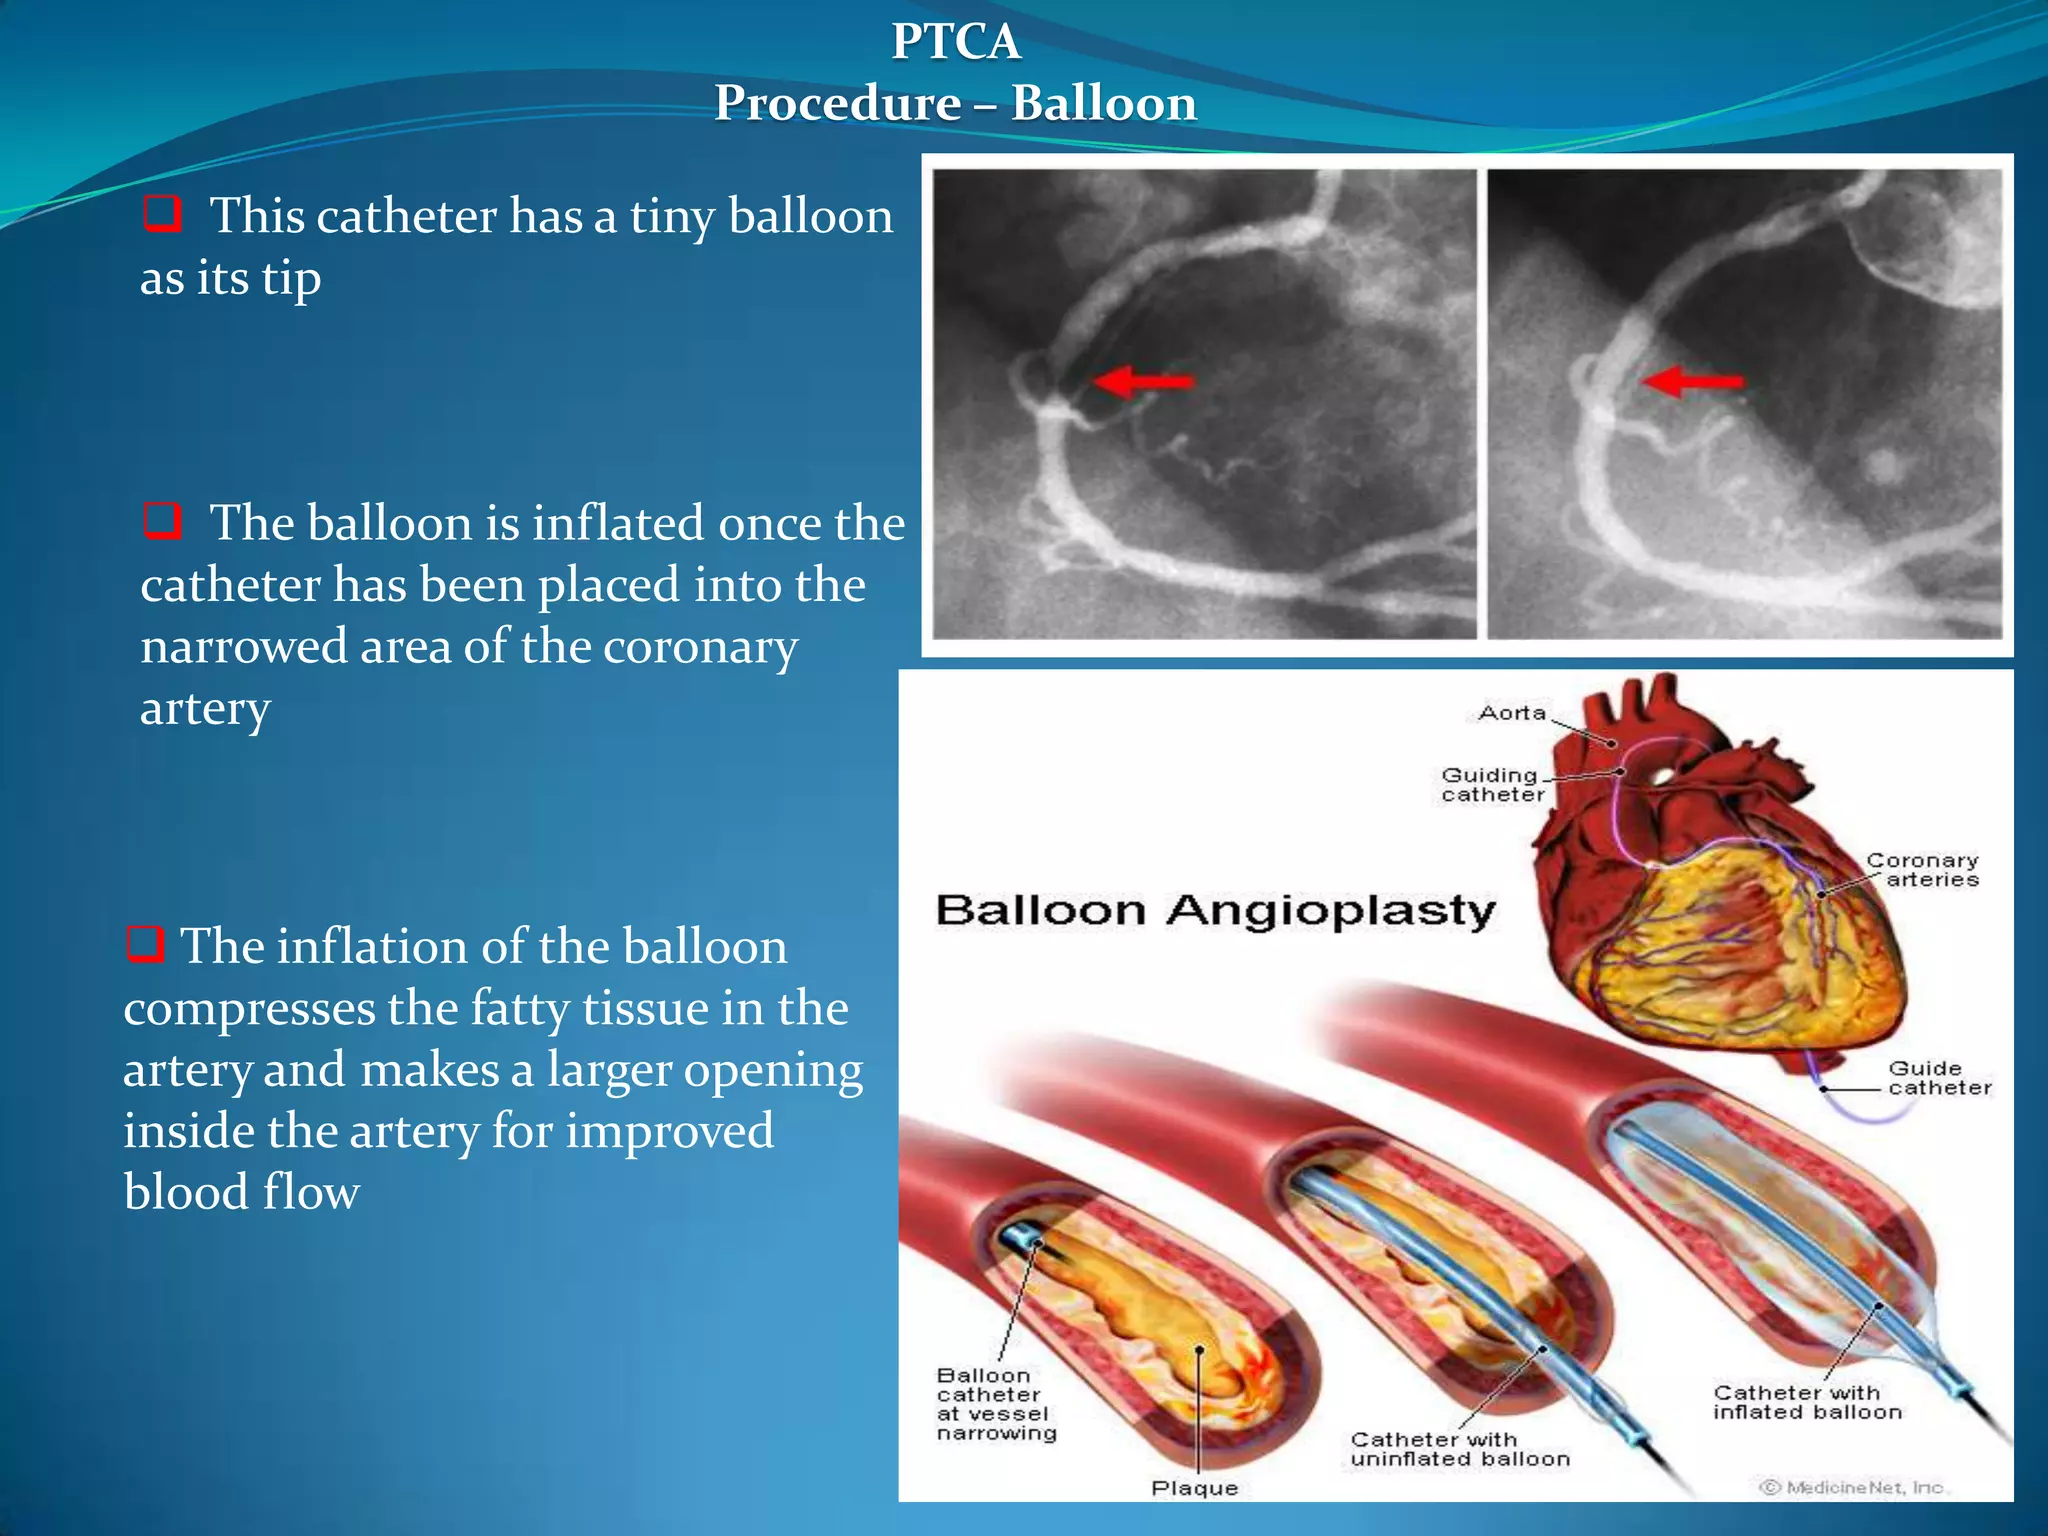
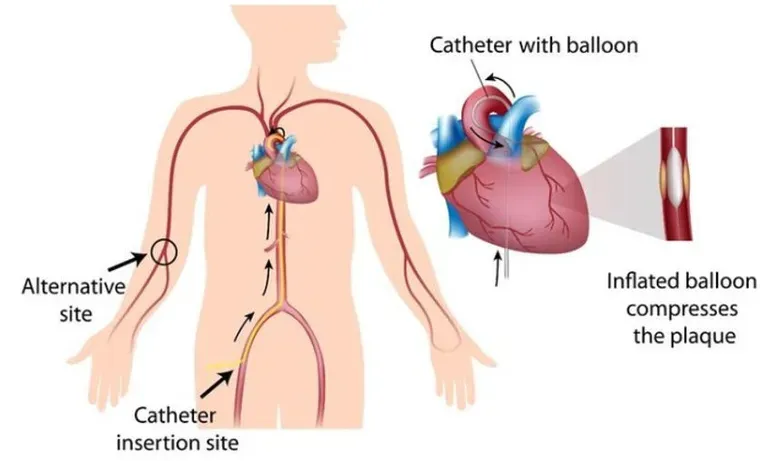
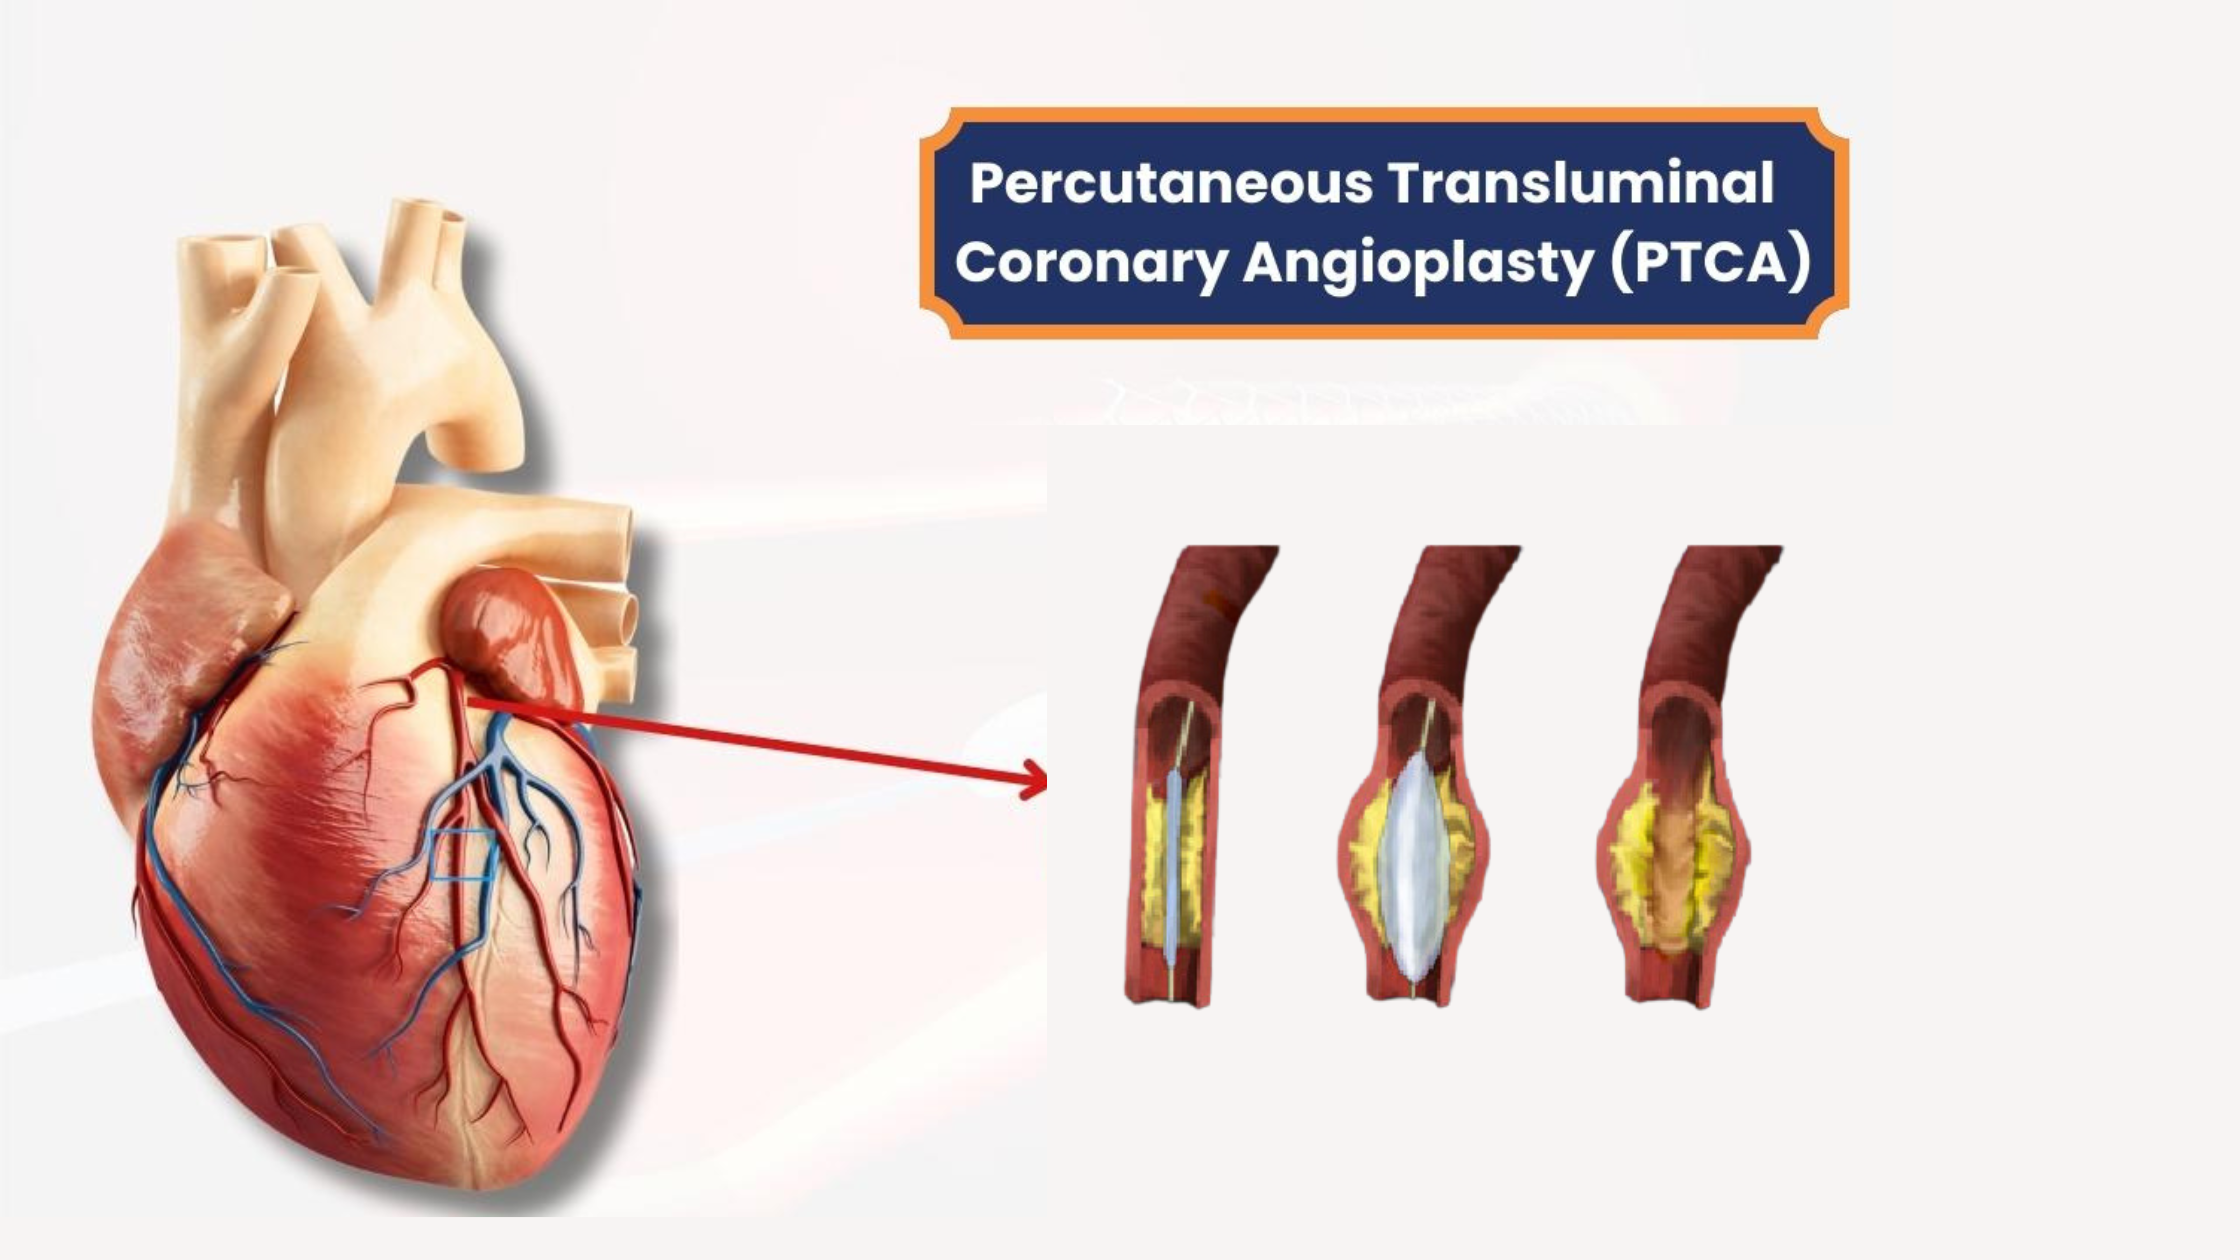
PTCA stands for Percutaneous Transluminal Coronary Angioplasty. It is a catheter-based procedure where a balloon-tipped wire is threaded through a blood vessel, usually the femoral or radial artery, and advanced to a blocked coronary artery. Once the lesion is located, the balloon is inflated to compress the plaque against the vessel wall, restoring blood flow. In most cases today, a stent is placed afterward to keep the artery open. The whole thing takes anywhere from 30 minutes to two hours depending on how many blocks need addressing and how calcified the arteries are. The importance comes down to one thing: time. In an ST-elevation myocardial infarction (STEMI), every minute of untreated occlusion costs roughly one percent of viable myocardium. The difference between a successful PTCA and a delayed transfer isn't abstract. I was on call at a community hospital where we had a patient with an inferior MI, and the nearest PCI-capable center was a 50-minute drive away. We did a primary PTCA with a drug-eluting stent in 45 minutes. The patient went home in three days with near-normal ejection fraction. The patient who waited for transfer that same week had a significantly larger infarct and required an IABP for a week post-op. That is not dramatic. That is just what the data and the chart show. For non-STEMI patients, PTCA is less of an emergency but still critical when there is a high-risk anatomy or persistent ischemia. It is not always the first step. Guidelines often recommend an ischemia-guided approach for stable patients, but when a patient has dynamic ECG changes, elevated troponins, and multivessel disease, waiting is a mistake.
How The Procedure Actually Works In Practice
Here is the sequence without the textbook polish: First, the access site is chosen. Radial access is now standard in most centers because it cuts bleeding complications dramatically and lets patients sit up sooner. If radial access fails, you switch to femoral without hesitation. Second, a sheath is placed and anticoagulation is started with heparin. Third, a guiding catheter is advanced over a wire to the coronary ostium. Fourth, a coronary angiogram is performed to map the blockage. Fifth, a crossing wire is advanced across the lesion. This is the step where things can go wrong if the lesion is heavily calcified or tortuous. You use a workhorse wire like a Fielder or Confianza and a supportive guide like an Amplatz or Cobra. Sixth, pre-dilation with a balloon is done if the lesion is tight or calcified. Seventh, a stent is deployed. Eighth, post-dilation with a non-compliant balloon ensures the stent is fully apposed to the wall. Ninth, the final angiogram confirms TIMI 3 flow. If you hit a chronic total occlusion (CTO), the steps change completely. CTO PCI can take three to four hours and requires different wires, microcatheters, and sometimes retrograde access. Do not attempt a CTO as your first case unless you are well trained.
Counter-Intuitive Things Beginners Miss
The first thing people get wrong is thinking that opening the artery is the hard part. It is not. The hard part is managing the complications and recognizing when you should not proceed. I have seen operators press on through a dissection because they did not want to admit defeat. That dissection turned into a pericardial tamponade. The patient needed pericardiocentesis and emergency CABG. The rule is simple: if you are not getting flow or you see a new dissection that threatens the vessel, stop and reassess. Bring in more help if you have it. The second thing is underestimating contrast-induced nephropathy. Patients with diabetes and baseline creatinine above 1.5 need aggressive hydration before and after. I use a conservative contrast limit of 3 mL/kg body weight and prefer iso-osmolar contrast like iodixanol. In one case, I had a patient with an ejection fraction of 25 percent who needed a complex two-vessel PCI. I stuck to under 80 mL of contrast, gave the patient a salt-free fluid protocol, and checked the creatinine the next morning. It barely moved. The patient who got 200 mL of contrast and no hydration had a bump to 3.2. That is the kind of detail that separates a safe procedure from a regrettable one.
Get the Full Details
When PTCA Is Not The Answer
PTCA fails in certain scenarios, and you need to recognize them early. Severe calcification that prevents balloon expansion or stent delivery is one. IVUS or OCT imaging can show you the calcium burden, and if it is heavy, you may need atherectomy or intravascular lithotripsy before stenting. Another scenario is left main disease with complex anatomy. In those cases, surgical revascularization with CABG has better long-term outcomes, especially in diabetic patients. The SYNTAX score helps guide that decision, but it is not perfect. A score of less than 22 favors PCI. Above 32 usually points toward surgery. In between, it is a discussion with the heart team. There is also the issue of small vessel disease. If the reference vessel diameter is less than 2.5 mm, stent outcomes drop and restenosis risk rises. In those cases, bare-metal stents or even balloon angioplasty alone might be considered, though drug-coated balloons are gaining traction. I had a case where a patient had diffuse disease in a 2.0 mm vessel. We placed a paclitaxel-coated balloon, avoided a stent, and the patient remained event-free at six months. Stenting that vessel would have been asking for trouble.
What Patients And Families Need To Understand
The procedure itself is not painful. You are awake but sedated. The area around the access site is numbed. Most people report pressure but not pain. Recovery is faster with radial access, and many patients are home the next day. The real concern is not the procedure but the underlying coronary disease. PTCA fixes one problem in one artery. It does not cure coronary artery disease. Dual antiplatelet therapy is mandatory after stent placement. I cannot stress this enough. Patients who stop their aspirin and P2Y12 inhibitor early because they feel fine are the ones who come back with stent thrombosis. That is a catastrophic event with high mortality. Make sure they understand the medication requirement before they leave. I once had a patient who stopped clopidogrel on day five because he thought it was causing bruising. He presented 11 days later with acute stent thrombosis and had to go back to the lab. We managed it, but it was entirely preventable. The education needs to happen before discharge. Not after.
A Note On Outcomes And Reality
Success rates for straightforward PTCA are high, often above 95 percent for single-vessel disease. Complication rates are low in experienced hands. But these numbers hide the reality of difficult anatomy, comorbid patients, and operator variability. Your outcomes depend on case selection, preparation, and knowing when to call for backup. There is no shortcut for that. It comes from doing the cases, reviewing the angiograms, and learning from the ones that went poorly. If you are looking to learn more about the clinical guidelines and published data, the American Heart Association and the European Society of Cardiology both have detailed documents on PCI and ACS management. Start with the 2021 AHA/ACC/SCAI Guideline for Coronary Artery Revascularization and the 2020 ESC Guidelines for the Management of Acute Coronary Syndromes. They are dense but necessary if you are working in this space.