Sepsis Is Not A Diagnosis You Get To Sit With
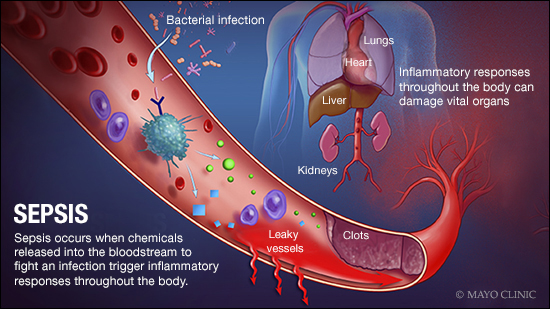
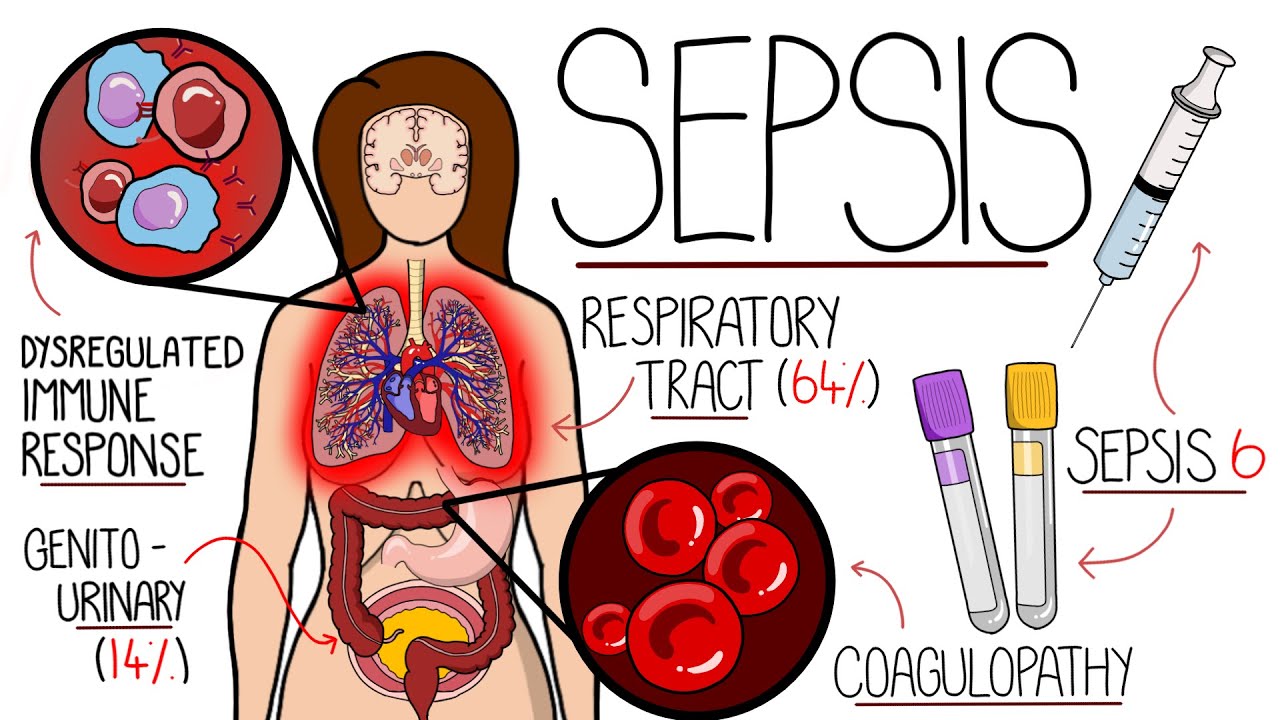
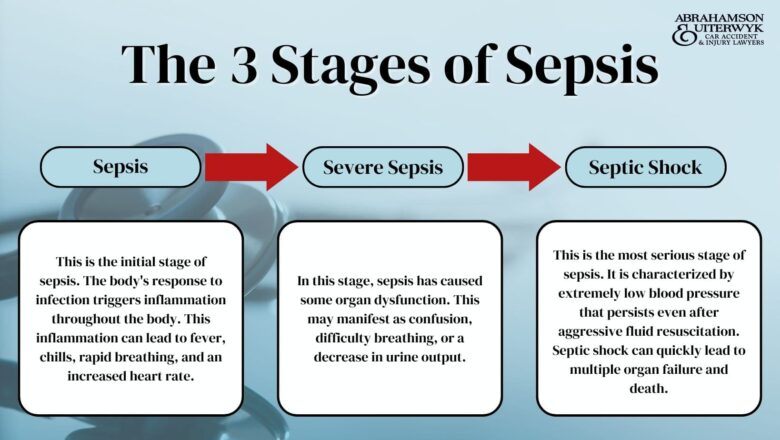
Sepsis is the body's systemic response to infection that spirals out of control. The immune system releases chemicals into the blood to fight the invading pathogen, but that triggering of the inflammatory cascade throws the whole circulatory system into chaos. Blood pressure drops. Organs start failing. You are looking at a medical emergency where every hour without treatment significantly increases mortality. The thing most people don't understand is that sepsis is not an infection itself. It is the body's response to one going wrong. Any infection can trigger sepsis. Bacterial infections are the most common culprits, particularly Gram-negative organisms like E. coli, Klebsiella, and Pseudomonas. Streptococcus and Staphylococcus aureus, including MRSA, are also frequent offenders. Fungal and viral infections can do it too, though they are less common in typical community-acquired cases. The infection source matters clinically. Pneumonia accounts for roughly thirty percent of sepsis cases. Urinary tract infections leading to pyelonephritis or urosepsis come in second. Intra-abdominal infections from perforated appendices or gallbladder issues are third. Skin and soft tissue infections round out the major categories. I spent time on a surgical floor dealing with post-operative patients who presented with subtle signs. A woman in her sixties had a hip replacement and came back with confusion and a low-grade fever that nobody connected to anything serious. Her white blood cell count was mildly elevated. The lactate was slightly high at two point three. We missed it for about eight hours because nobody was running the SIRS criteria properly. She went into septic shock by morning. The lesson there was that post-op patients often present atypically. Don't anchor on "expected recovery symptoms" and stop thinking.
How To Spot It Before It Gets Worse
The old SIRS criteria were standard for years. Two or more of the following: temperature above thirty-eight or below thirty-six degrees Celsius, heart rate over ninety beats per minute, respiratory rate over twelve or a PaCO2 below thirty-two, and white blood cell count above twelve thousand or below four thousand. The problem with SIRS is that it is too sensitive. Almost anyone with any inflammation will meet those criteria. It catches people but it also catches healthy immune responses that have nothing to do with sepsis. The modern clinical tool is SOFA, the Sequential Organ Failure Assessment. It scores six organ systems. Respiratory, coagulation, liver, cardiovascular, CNS, and renal. A change in SOFA score of two or more points in the context of a suspected infection is what defines sepsis according to the Sepsis-3 consensus. In practice, you are looking for something simpler at the bedside. qSOFA was introduced as a quick screen. Abnormal mental status, systolic blood pressure at or below one hundred millimeters of mercury, and respiratory rate of twenty-two or higher. Two or more points on qSOFA suggests a poorer outcome and should trigger a full sepsis workup immediately. The nuance nobody teaches enough is that lactate matters. A serum lactate above two millimoles per liter in a patient with suspected infection indicates septic shock risk even if blood pressure is currently normal. Lactate clearance is your trend parameter. If you treat and the lactate is not dropping, something is still wrong. I had a case where a patient's blood pressure normalized after fluids but the lactate stayed elevated at four point one. We assumed we had won. We were wrong. She had an undrained intra-abdominal abscess that required surgery forty-eight hours later. Normal blood pressure does not equal resolved sepsis.
The Treatments That Actually Save Lives
The Surviving Sepsis Campaign guidelines are the benchmark. Within the first hour of recognition, you need three things done. Blood cultures before antibiotics if you can get them without significant delay, but do not hold antibiotics for cultures. Broad-spectrum antibiotics. And fluid resuscitation with crystalloids, typically thirty milliliters per kilogram of ideal body weight. If the patient is hypotensive or the lactate is above four, you start vasopressors. Norepinephrine is first line. You are targeting a mean arterial pressure of at least sixty-five millimeters of mercury. The antibiotic timing window is real. Each hour of delay in appropriate antibiotic administration after presentation increases mortality by approximately seven to nine percent in bacteremic sepsis. That is not a theoretical number. It is measured. If you suspect sepsis and the patient is going to the ICU, do not wait for confirmatory cultures to start antibiotics. Draw the cultures first if it takes thirty seconds, but start the drugs. Source control is the part that gets overlooked. Antibiotics and fluids treat the systemic response. They do not fix the infected gallbladder, the perforated bowel, the abscess, or the necrotizing fasciitis. If there is a drainable collection, you need to drain it. If there is necrotic tissue, you need to debride it. If there is an infected device, you need to remove it. This is not optional. A patient can be perfectly resuscitated and still die if the source remains untreated. I saw this repeatedly with biliary sepsis. The antibiotics stabilized the patient temporarily but the obstruction was still there. Definitive drainage with ERCP or percutaneous cholecystostomy was what actually saved them.
Get the Full Details
Where The Guidelines Break Down
Fluid resuscitation is not a free intervention. The traditional approach of large volume crystalloid boluses has come under scrutiny. Excessive fluid administration, what some call a "fluid creep," is associated with worse outcomes in certain populations. Pulmonary edema, abdominal compartment syndrome, and prolonged mechanical ventilation are real risks. The current recommendation is more nuanced. Start with an initial bolus of twenty to thirty milliliters per kilogram, then reassess. Use dynamic measures like stroke volume variation or passive leg raise tests to determine fluid responsiveness rather than giving everyone the same fixed volume. If the patient does not respond to the initial bolus, do not just keep adding fluid. Start vasopressors early and investigate the source. Albumin as an adjunct to crystalloids shows some benefit in certain septic shock populations but it is expensive and the evidence is mixed. It is not standard first-line therapy. Stress-dose steroids are another area where practice varies widely. The ADRESS trial showed a mortality benefit with hydrocortisone in septic shock patients who required vasopressors, but only in the subgroup with relative adrenal insufficiency. Most clinicians I work with use a trial of hydrocortisone one hundred milligrams every eight hours in refractory septic shock, tapering over four to six days if there is a response. There is no universal agreement on who benefits. The one area where I would push back on standard protocol is routine corticosteroid use in non-shock sepsis. Some institutions have protocols for broad steroid use in any sepsis patient. The evidence does not support this. Steroids have immunosuppressive effects, they cause hyperglycemia, they predispose to secondary infections. Use them when there is clear indication, not as a blanket intervention.
Procalcitonin guidance for antibiotic de-escalation is another contested area. Some studies support using procalcitonin levels to shorten antibiotic duration, but the data is strongest in respiratory sources. For intra-abdominal or urinary sources, the evidence is weaker. I tend to use procalcitonin as one data point among many, not as a standalone decision tool. The organism and the clinical trajectory matter more. Sepsis kills through a combination of distributive shock, microvascular thrombosis, and mitochondrial dysfunction. It is not just low blood pressure. The cellular level dysfunction persists even after hemodynamics are corrected, which explains why some patients have prolonged recovery and delayed organ function improvement. Supportive care matters. Nutritional support, glycemic control, DVT prophylaxis, and early mobilization once stable are all part of management. The initial resuscitation gets all the attention but the subsequent care determines long-term outcomes. Sepsis-associated cognitive dysfunction is real and affects a significant minority of survivors, particularly older patients. It is easy to miss in the acute phase when you are focused on keeping the patient alive.