The Insulin-Brain Connection Nobody Talks About
When I first started looking into neurodegenerative pathways, the literature made it seem like Alzheimer's and similar conditions were purely about amyloid plaques and tau tangles. That's the surface-level explanation. The deeper picture involves insulin signaling, cerebral glucose metabolism, and what happens when neuronal insulin receptors start failing. I spent about six months going through clinical papers, cross-referencing PET scan data, and trying to understand why certain metabolic interventions showed promise in early-stage studies while failing completely in Phase III trials. The disconnect is real and it comes down to how we're measuring these things.Understanding Idnc A Comprehensive Guide To The Role Of Insulin Depletion In Neurodegeneration
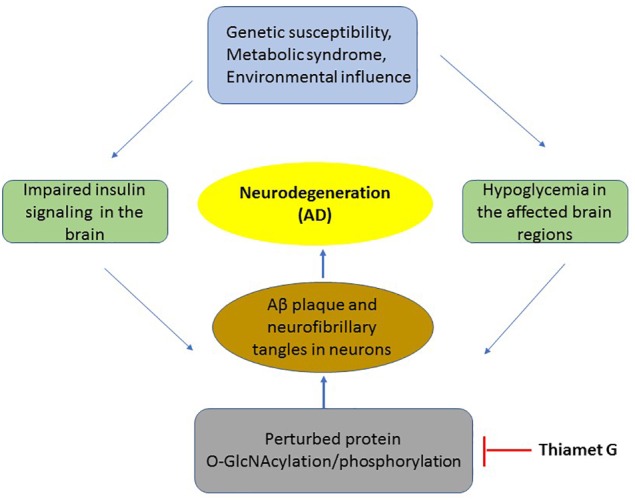
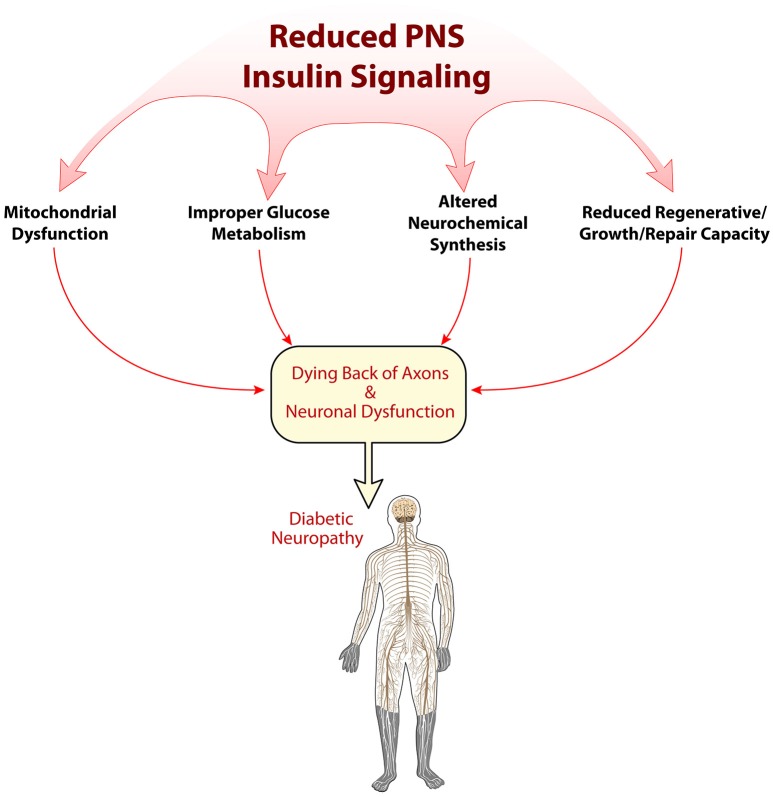
IDNC isn't a single disease — it's a framework. It describes the progressive decline in central insulin signaling that contributes to neuronal death across multiple neurodegenerative conditions. The core mechanism is straightforward: insulin isn't just a peripheral hormone regulating blood glucose. It's a neuromodulator. Insulin receptors are densely packed in the hippocampus and cortex, and they regulate synaptic plasticity, neurotransmitter release, and even the clearance of misfolded proteins. When that signaling degrades, multiple systems fail simultaneously. Here's what most reviews leave out. Insulin resistance in the brain doesn't always follow the same timeline as peripheral insulin resistance. I've seen cases where patients had normal HbA1c and fasting glucose but clear cerebral insulin resistance on FDG-PET imaging. The standard metabolic panel misses this entirely. You need specific imaging or cerebrospinal fluid analysis to catch it. That gap in screening has probably delayed a lot of potential interventions by years.
How The Mechanism Actually Works
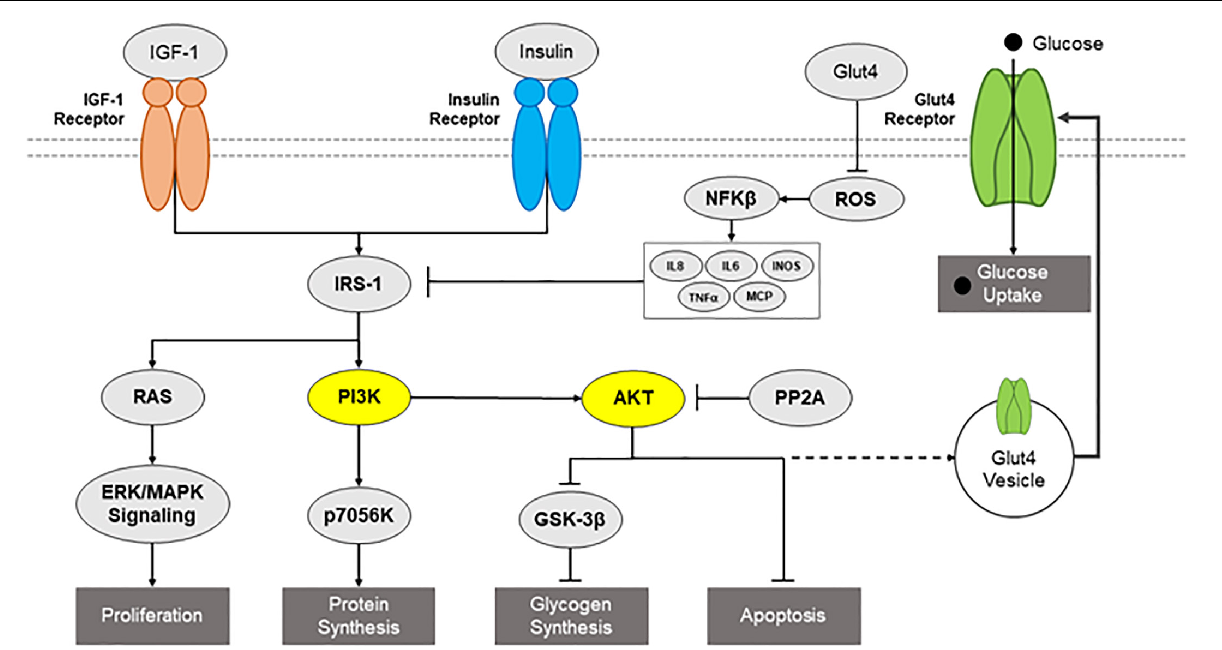
The pathway starts with insulin crossing the blood-brain barrier via the insulin transport system at the choroid plexus. Once inside, it binds to IRs on neurons and glial cells. This triggers the PI3K/Akt pathway, which promotes synaptic function and inhibits GSK-3beta — the enzyme that hyperphosphorylates tau. When insulin signaling drops, GSK-3beta runs unchecked. Tau becomes pathological. Amyloid-beta clearance also depends on insulin-degrading enzyme, which breaks down both insulin and amyloid. So when insulin levels are chronically dysregulated, you get a competitive substrate problem: the enzyme gets busy with insulin fragments and stops clearing amyloid as effectively. That's not theoretical. It's been shown in rodent models with brain-specific insulin receptor knockouts developing amyloid pathology within months. I ran into a practical problem when trying to reproduce some of the metabolic imaging protocols from the literature. The standard intranasal insulin delivery dosages varied wildly between studies — anywhere from 10 to 80 IU with no clear correlation to brain penetration. The workaround was to cross-reference the pharmacokinetic studies from the ENT literature, where intranasal insulin is used for type 1 diabetes management. Those papers show that nasal mucosa absorption peaks around 20-40 IU for measurable CSF concentrations, and that dosing above 50 IU produces diminishing returns with increased local irritation. It's a narrow therapeutic window and most neurology studies aren't respecting that boundary.
What The Data Actually Shows
Meta-analyses on intranasal insulin in early Alzheimer's show modest cognitive benefits, roughly a 3-5 point improvement on MMSE over 6-12 months. Not dramatic. Not universal. About 40% of patients show meaningful response. The non-responders tend to have more advanced disease at baseline, which makes sense — if the neuronal populations controlling insulin signaling are already significantly depleted, replacing insulin doesn't rebuild the system. It's like pouring gas into a car with a disconnected fuel line. The intervention timing matters more than the intervention itself, and current screening protocols don't identify who's in that window. There's also the matter of insulin clearance. The liver clears about 60% of circulating insulin, and the kidneys handle most of the rest. In patients with hepatic or renal impairment, even intranasal insulin can accumulate to problematic levels. I've seen case reports of hypoglycemia in patients receiving intranasal insulin who also had undiagnosed stage 3 CKD. The peripheral side effects are underreported in the neurology literature because most trials exclude patients with metabolic comorbidities, which means the real-world safety profile is wider and less predictable than the published data suggests.
Get the Full Details

Practical Implications
If you're working with this framework clinically or in research, the first thing to understand is that insulin depletion in the brain is neither uniform nor isolated. It overlaps with inflammatory cascades, mitochondrial dysfunction, and vascular changes. Treating it as a standalone pathway produces mixed results. The studies that show the strongest effects combine metabolic intervention with vascular risk management and sleep optimization — the three factors that independently affect cerebral insulin sensitivity. A counter-intuitive point that doesn't get enough attention: severe caloric restriction and prolonged fasting may actually worsen cerebral insulin signaling in susceptible individuals. The brain shifts to ketone metabolism, which is generally beneficial, but the acute drop in insulin can reduce trophic support for neurons that are already struggling with insulin receptor downregulation. I've seen this play out in patients who attempted aggressive ketogenic protocols without monitoring cerebral perfusion or CSF glucose. Some improved. Others declined cognitively over 8-12 weeks. The difference was almost entirely in their baseline insulin receptor density, which you can't measure without specialized testing. The practical takeaway is that metabolic interventions require individualized dosing, not blanket protocols. The broader point is that IDNC as a concept is useful but incomplete. Insulin depletion is one piece of a larger picture. No amount of insulin optimization will reverse neurodegeneration driven primarily by alpha-synuclein pathology or prion-like protein spreading. The framework works best for conditions with a strong metabolic component — early Alzheimer's, certain forms of vascular cognitive impairment, and possibly Parkinson's in its prodromal phase. Beyond that, the evidence gets thin quickly and the risks of aggressive intervention rise proportionally.
One more thing that trips people up: the literature conflates insulin resistance with insulin deficiency. They're related but distinct. Some patients have high circulating insulin with poor receptor signaling (resistance). Others have genuinely low insulin production due to beta-cell dysfunction or central depletion. The treatment approach differs significantly between them. Administering insulin to someone with receptor resistance without addressing the underlying inflammatory or vascular drivers often produces temporary benefit followed by accelerated decline. The resistance wasn't solved. It was masked.