
What Hypervigilance Actually Feels Like
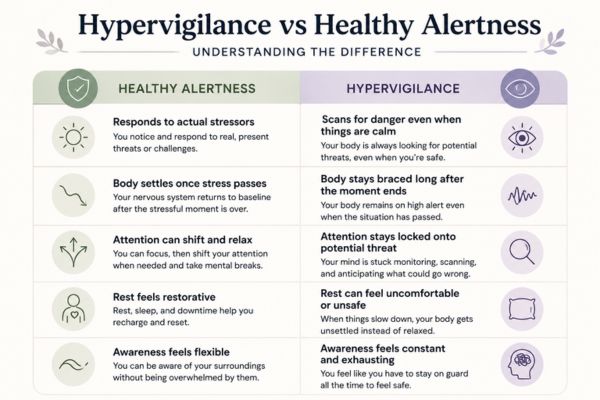
Most people think hypervigilance is just being alert or paranoid. It isn't. It's a nervous system stuck in a feedback loop where the body's threat detection circuitry fires constantly, even when nothing is wrong. Your amygdala is sending danger signals at baseline, and your prefrontal cortex can't quite override it because the signal has become automatic rather than intentional. I spent about three years working with trauma survivors who had this condition, and the most consistent complaint was that they couldn't turn it off. Not that they were anxious, but that their body was reading every room, every tone of voice, every pause in conversation as a potential threat. Sleep was nearly impossible because the moment they drifted toward sleep, their muscles would twitch and their mind would snap back to scanning. This isn't a character flaw. It's a physiological state that takes time to unlearn.
Understanding Hypervigilance Meaning Psychology And How To Cope
In clinical terms, hypervigilance is a symptom, not a diagnosis. It appears in PTSD, generalized anxiety disorder, CPTSD, and sometimes as a residual effect of chronic stress even when no formal disorder is present. The DSM-5 lists it under the hyperarousal criteria for PTSD, which means it's one of five possible symptoms needed for that diagnosis. That's important because it tells you something: treating hypervigilance in isolation without addressing the underlying condition often fails. The symptom comes back. The core mechanism involves the sympathetic nervous system becoming hypersensitive to sensory input. Light touches, sudden movements, ambient noise—these register at a higher intensity than they should. Research on the startle reflex shows that people with hypervigilance have a significantly lowered threshold for their acoustic startle response, and this response can remain elevated for months or years after the original trauma, even when the person feels calm on the surface. Here's the part most guides skip: hypervigilance isn't just mental. It's embodied. The body maintains its own memory of threat through muscle tension patterns, breath holding, and postural guarding. You can talk yourself into feeling safe all day, but if your diaphragm has been chronically restricted for two years, your nervous system still reads that as danger. This is why breathing exercises alone rarely fix it.
Why Standard Advice Doesn't Work
The usual suggestions are grounding techniques, deep breathing, meditation, and avoiding triggers. These help some people and do almost nothing for others. The problem is that most of these strategies treat hypervigilance as a cognitive issue when it's primarily a physiological one. Telling someone to breathe slowly when their autonomic nervous system is stuck in overdrive is like tapping the check engine light to turn it off. I saw this repeatedly in practice. A patient would come in saying they'd done ten minutes of box breathing and still felt on edge. The breathing was correct. The technique wasn't the problem. The problem was that their interoceptive awareness—their ability to sense internal body states—was so dysregulated that slow breathing actually felt like suffocation to them. For some people with severe hypervigilance, focusing inward makes things worse before it gets better. That's a counter-intuitive point that almost nobody mentions. Another common failure point is trigger avoidance. Yes, avoiding loud noises or crowded spaces reduces acute distress in the short term. But long-term avoidance reinforces the brain's threat assessment. Every time you avoid something and feel relief, your nervous system learns: that thing was dangerous and I survived by escaping. The neural pathway gets stronger. This is why exposure therapy, when done correctly, is more effective than avoidance, even though avoidance feels better day to day.
Get the Full Details
What Actually Helps
Somatic experiencing and sensorimotor psychotherapy are two approaches that target the body-first nature of hypervigilance. The idea is to help the nervous system complete defensive responses that were interrupted during the original trauma. When someone is threatened, the body has a sequence: freeze, fight, flee, fawn. If that sequence gets stuck mid-cycle, the energy stays trapped in the nervous system. Somatic work helps discharge that trapped energy gradually. A specific technique that has real evidence behind it is neurogenic tremoring. These are involuntary shaking movements that the body produces when releasing stored stress. They're not the same as a seizure or a medical tremor. They tend to happen in the legs and hands, are rhythmic, and usually stop on their own. I've had clients do this for maybe ten minutes and report a noticeable shift in their baseline anxiety level. It sounds strange, but the mechanism is straightforward: the shaking activates the parasympathetic nervous system through a process called auto-regulation of the nervous system. Vagus nerve stimulation is another evidence-backed approach. This can be done through humming, cold exposure on the face, or specifically targeted breathing patterns. The vagus nerve is the main component of the parasympathetic system, and stimulating it signals to the brain that the threat has passed. One practical method is the physiological sigh: two quick inhales through the nose followed by a long exhale through the mouth. Studies show this pattern reduces arousal faster than standard deep breathing because it fully deflates the lungs and triggers a stronger parasympathetic response.
Working With a Professional
Therapy works best when it's trauma-informed and targets the nervous system directly, not just the thoughts. EMDR, somatic experiencing, and parts work (IFS) are the most commonly recommended modalities. Medication can help in some cases—SSRIs and low-dose beta blockers are sometimes prescribed—but medication alone doesn't retrain the nervous system. It lowers the volume, but the song stays the same until the underlying pattern is addressed. The timeline matters. Most people see meaningful improvement within eight to sixteen weeks of consistent therapy, but that depends heavily on the severity and duration of the hypervigilance. Someone who has been hypervigilant for twenty years won't resolve it in two months. That's not a criticism of the treatment or the person. It's just the reality of neuroplasticity. Neural pathways that have been reinforced for decades require sustained, repeated new experiences to rewire. I'll be direct about what doesn't work. Apps and self-help books alone are insufficient for moderate to severe hypervigilance. They can supplement therapy, but they can't replace the interpersonal regulation that happens in a therapeutic relationship. Another thing to watch for: therapists who push too hard too fast with exposure or grounding can actually worsen hypervigilance by triggering a fight-or-flight response. Go slow. The nervous system needs to learn that safety is real, and that learning takes repetition, not intensity.
Day-to-Day Management
Beyond therapy, there are practical steps that help. Sleep hygiene is the foundation because sleep deprivation amplifies amygdala reactivity by up to 60 percent according to some studies. Even one night of poor sleep can push a mildly hypervigilant person into full hyperarousal. Regular exercise, especially rhythmic activities like walking, swimming, or cycling, helps regulate the nervous system over time. These aren't vague wellness tips—they directly affect cortisol levels and neurotransmitter balance. Caffeine and alcohol are worth monitoring closely. Caffeine mimics adrenaline in the body, which makes hypervigilance worse. Alcohol disrupts sleep architecture and can increase anxiety the next day, creating a cycle. I once had a client who couldn't figure out why her hypervigilance was suddenly worse after months of being stable. She'd started drinking wine every night to sleep. The wine was fragmenting her REM sleep, and her nervous system was compensating by staying more alert throughout the night. Two weeks off alcohol and her baseline improved noticeably. Sensory reduction helps too. Noise-canceling headphones, dimming lights, reducing screen time before bed—these aren't luxuries for hypervigilant people. They're necessary adjustments because your threat detection system is already running at maximum capacity. Adding more sensory input is like asking a computer with full CPU usage to run another program. It will lag.

The hardest part is patience. Progress isn't linear. Some days will feel like you're back at square one, and that's normal. The nervous system consolidates changes during rest, not during active effort. Consistency beats intensity every time. Ten minutes of regulated breathing daily is more effective than an hour of trying to force calm once a week.



