What You Need To Know About The Lingual Vestibule Before You Start Working In That Space
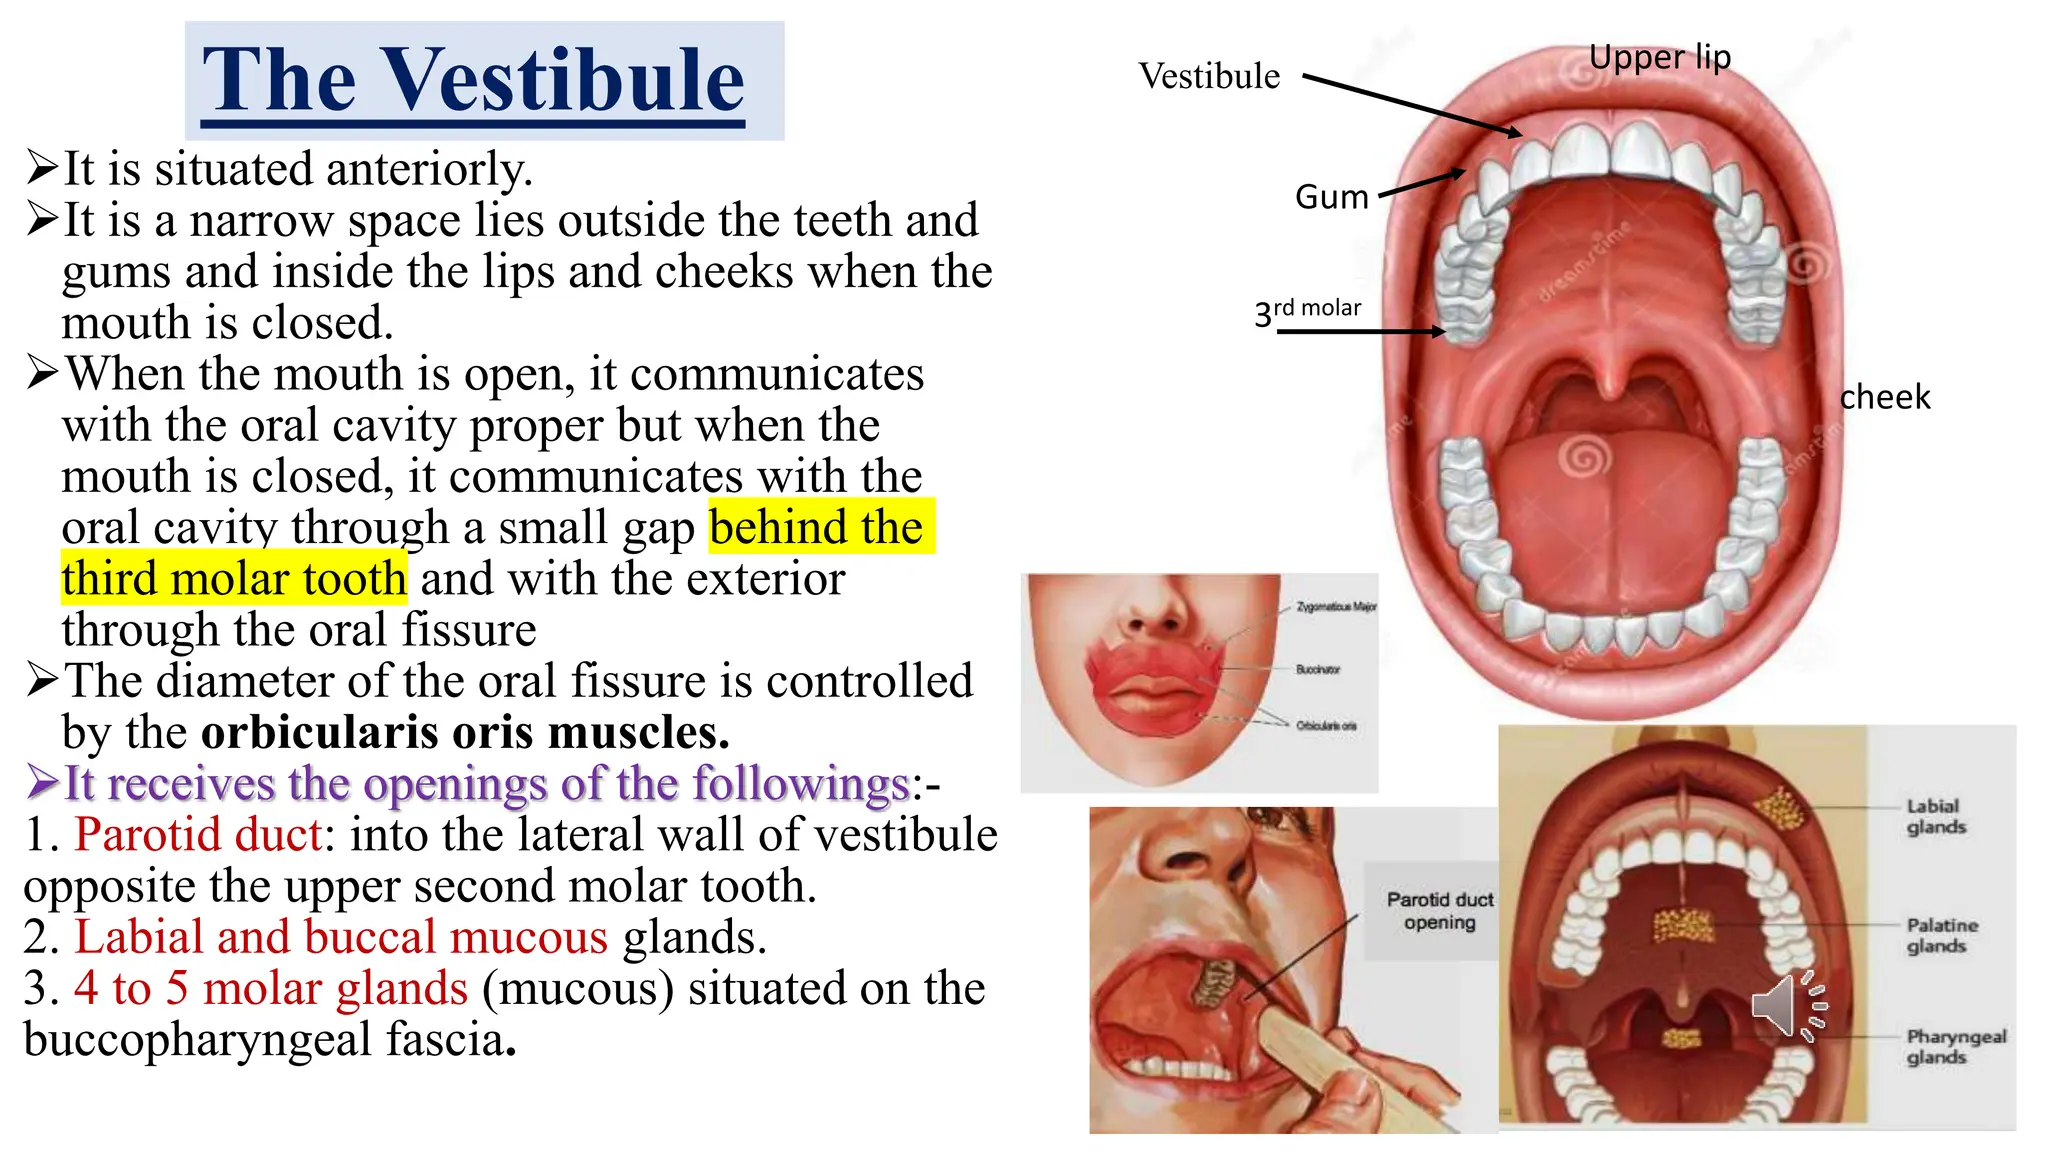
The lingual vestibule is the shallow pocket of tissue that sits between your lower tongue and the inner surface of your mandibular teeth and alveolar ridge. It is not some hidden anatomical mystery. It is a real, measurable space that every dentist, hygienist, and oral surgeon navigates regularly, usually without thinking about it much until something goes wrong. When I first started doing lower dentures, I underestimated how much the shape of that vestibule could throw off an impression. A patient's frenum attachment, the thickness of the mucosa, and even the degree of ridge resorption all changed how deep I needed to go with my tray. Getting that wrong meant either losing retention or causing the patient enough irritation that they refused to keep the denture in. If you are looking at this from a clinical perspective, here is how the space actually works. The buccal vestibule on the upper and lower arches serves as the peripheral seal area for complete dentures. On the mandibular side, the lingual vestibule is especially critical because the floor of the mouth and the mylohyoid muscle attach directly into that region. The depth of the vestibule varies enormously between patients. Some people have a fairly deep sulcus that is easy to record. Others have what we call a shallow vestibule, often due to fibrous tissue attachment or advanced resorption, and you have to work differently in those cases. I ran into a case last year where a patient had a severely resorbed mandibular ridge with a mylohyoid attachment running almost to the crest of the ridge. There was virtually no vestibular depth on the lingual side. A standard stock tray simply would not seat. I ended up using a custom tray made from a preliminary impression, trimming it back about 2mm from the vestibular depth so I could load border molding compound and capture the functional movement of the mylohyoid. Without that step, the denture would have been dislodged every time the patient spoke or ate. That is the kind of detail most textbooks gloss over.
How to properly assess and record the lingual vestibule during an impression procedure: Start with a preliminary impression using light-body silicone or polyether. I prefer polyether for the first pass because it is stiff enough to hold detail and does not flow into the vestibule the way some alginates do. Once you have a master cast, fabricate a custom tray that extends into the vestibule about 2 to 3mm beyond the resting sulcus depth. Use a wax rim or border molding material to trace the functional depth. Ask the patient to perform specific movements: press their tongue against the roof of their mouth, move the tongue from side to side, and say "ee-oh-oo" to engage the mylohyoid and geniohyoid muscles. These movements define the functional depth of the lingual vestibule, and that is what your final tray needs to capture. The common mistake I see all the time is taking the impression with the patient's mouth open and their tongue relaxed. That gives you a static depth that disappears the moment the tongue moves. The recorded border will be too shallow, and the denture will lift off the tissue during function. You end up with a denture that looks fine in the mirror but falls out the first time the patient tries to eat soup. I spent three weeks troubleshooting a case like that before I realized the border mold was static instead of dynamic. Now I always ask the patient to move their tongue through the full range of motion while the border material is still soft and setting.
For implant-supported overdentures, the lingual vestibule takes on a different set of challenges. When you place two implants in the anterior mandible, the bar or attachments sit close to the mylohyoid line. If the vestibule is shallow, the prosthesis can impinge on the functional movement of the tongue and floor of the mouth. I had a patient who complained constantly about the denture feeling like something was stuck under her tongue. Turns out the bar was positioned too close to the crest, and every time she tried to speak, the bar was pressing against her tongue base. We had to redesign the prosthesis with a lower profile bar and slightly recontour the vestibular tissue. It was a painful lesson in why you need to evaluate vestibular depth before you even plan the implant positions. If you are working with a patient who has significant vestibular depth and healthy mucosa, the standard impression techniques work fine. The issue is always the edge cases. Shallow vestibules, high frenum attachments, thick fibrous tissue, and active mylohyoid movement are the scenarios where things fall apart. In those situations, a custom tray with functional border molding is not optional. It is the only way to get a reliable record. Silicone putty-wash techniques can work here too, but you still need to manage the functional movements separately from the static impression. The bottom line is that the lingual vestibule is not something you can ignore. It determines retention, stability, and comfort more than most clinicians realize. Spend the extra fifteen minutes on functional border molding and you will save yourself hours of adjustments later.
Get the Full Details