How I Measure What Actually Matters When Checking Arterial Blood Pressure
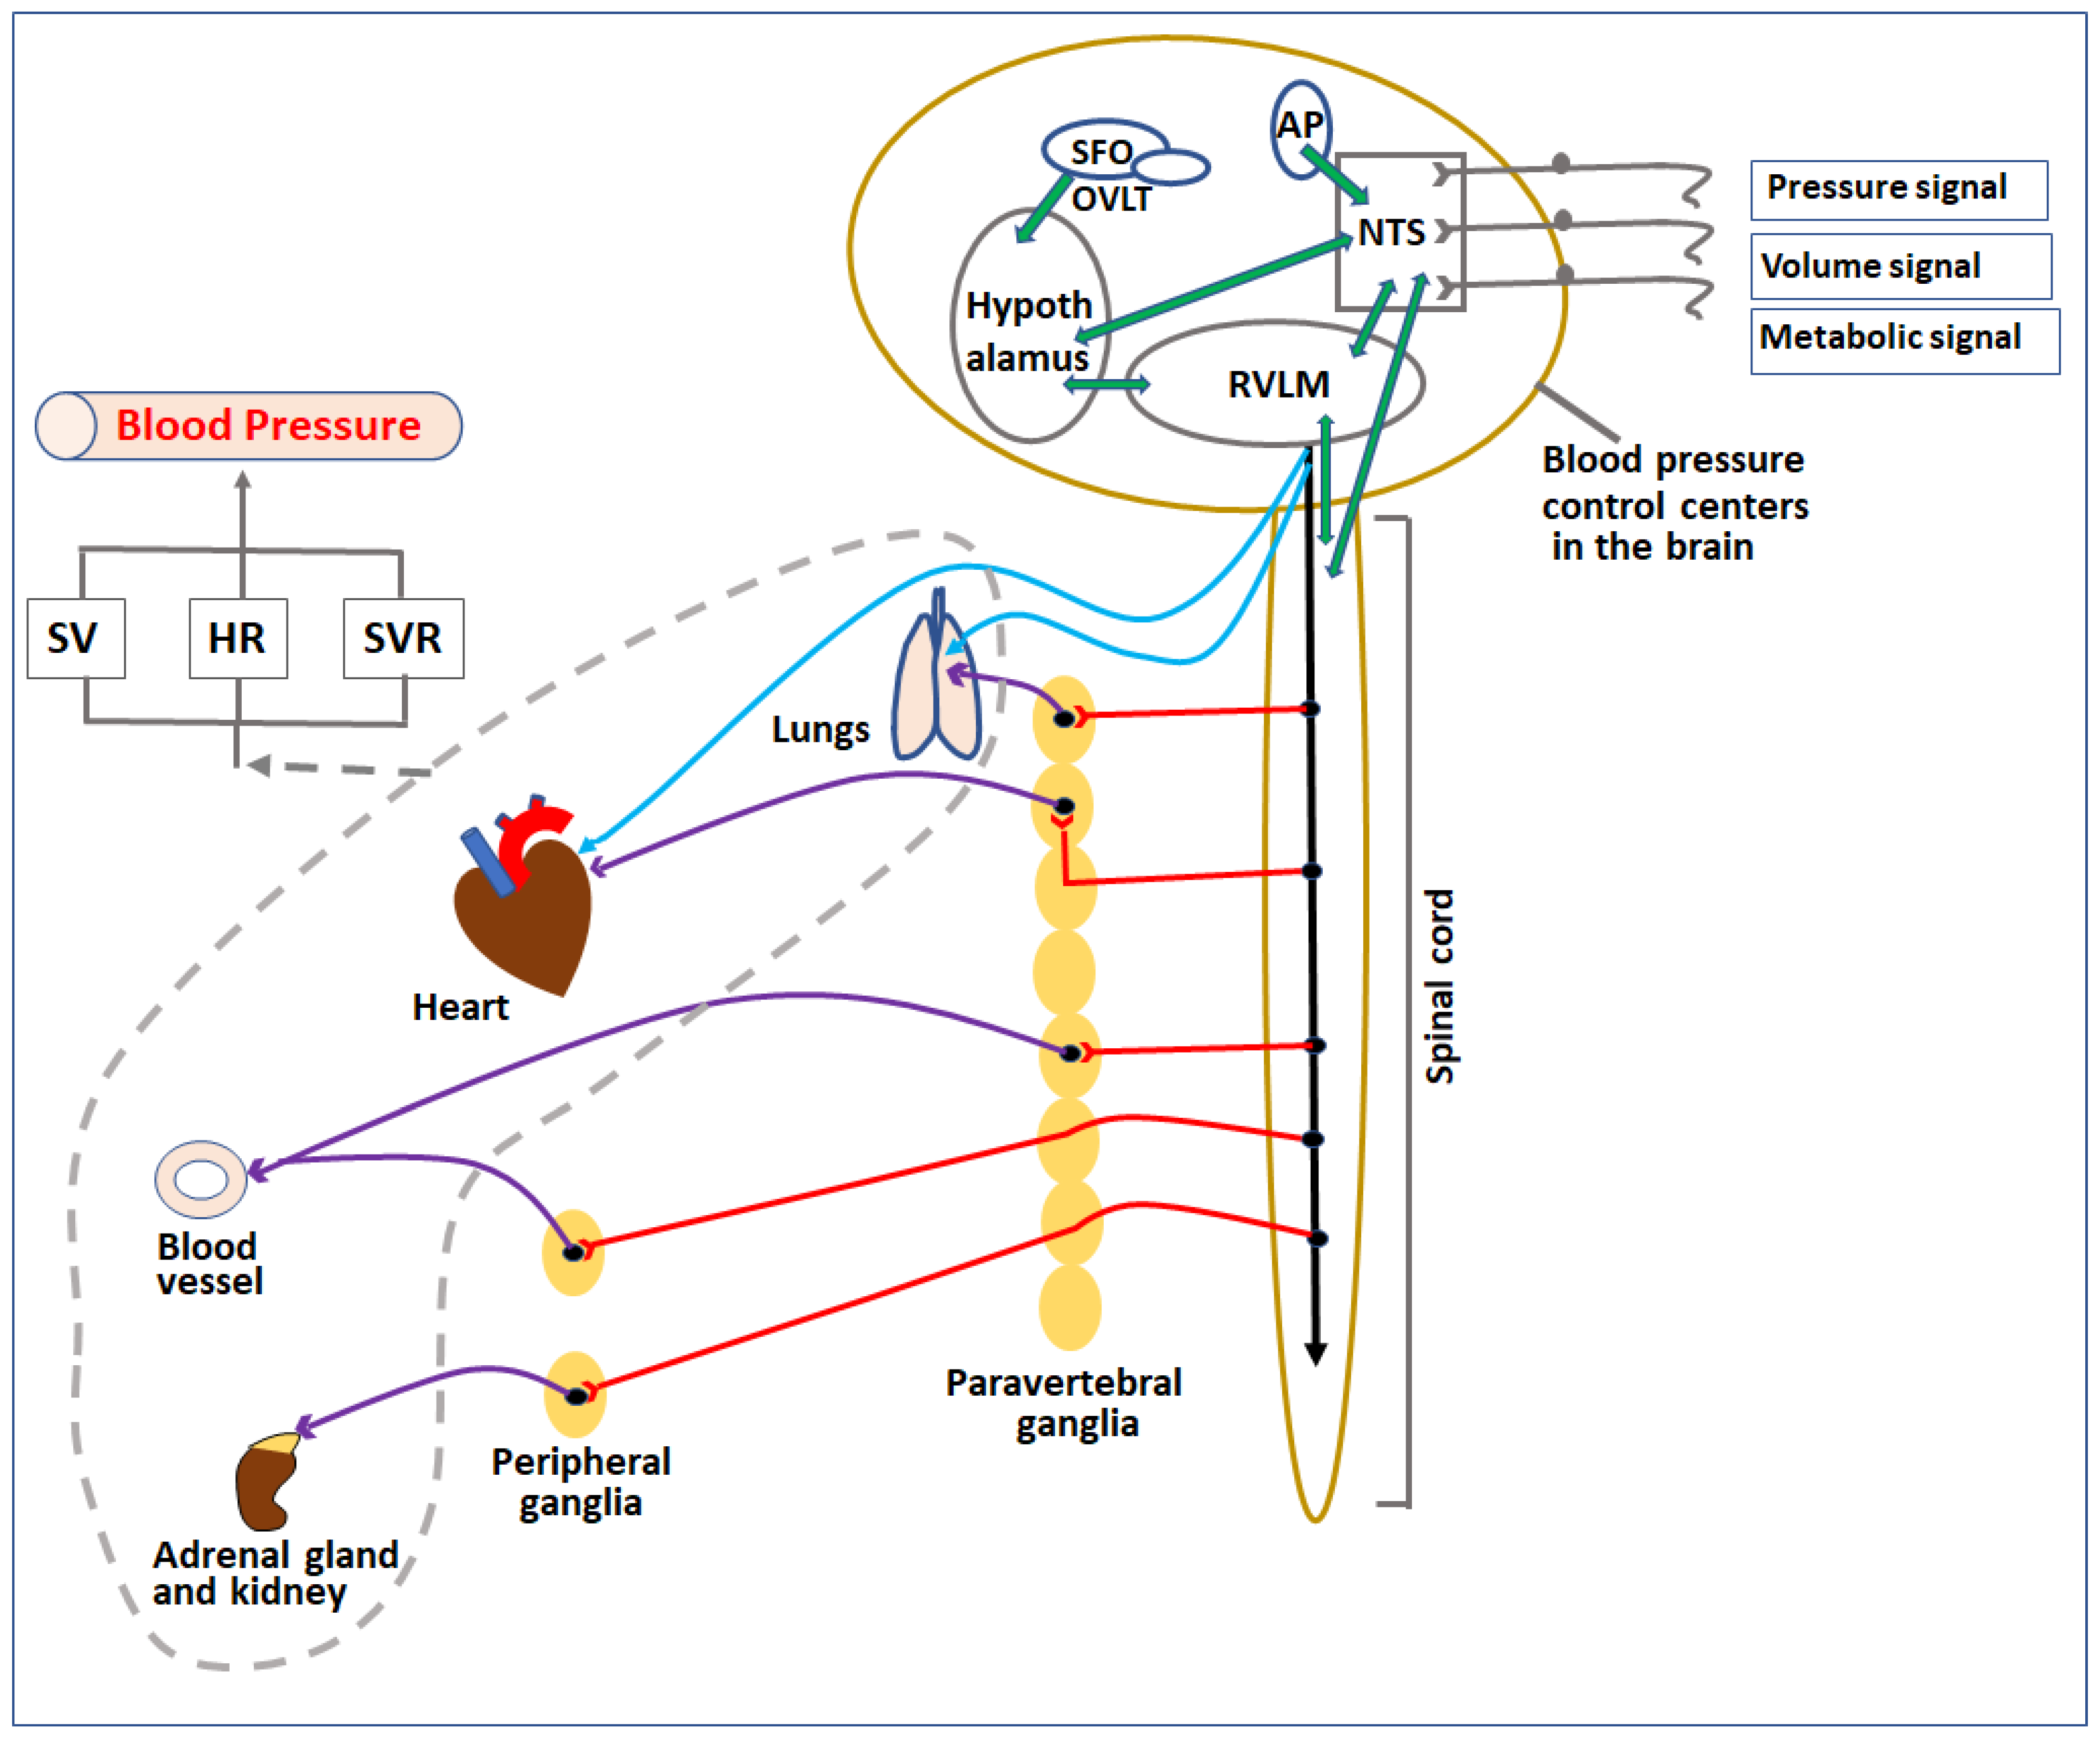
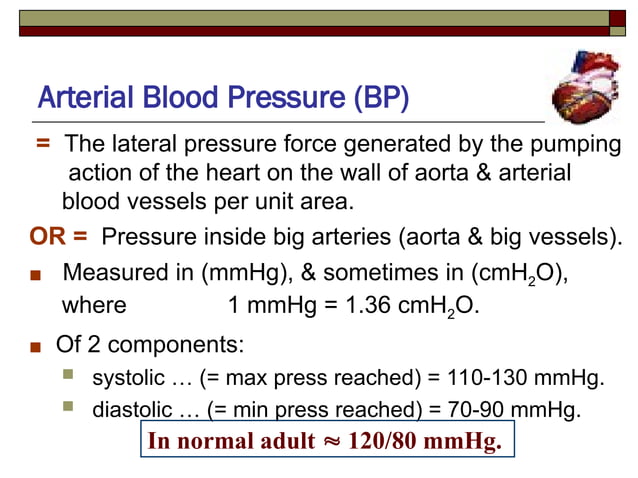
I spent years dealing with patients who had perfectly "controlled" readings in the clinic but were quietly developing end-organ damage anyway. The standard office number does not tell you the whole story. Most people chasing vascular health stop at a single brachial reading and call it a day. That approach misses more than it catches. I learned this the hard way after a patient came in with consistent 128 over 78 readings for two years and then presented with silent renal impairment. His numbers looked fine on paper. His arteries were not happy. The real work starts with understanding that arterial pressure is not a static value. It is a dynamic wave system shaped by stroke volume, arterial stiffness, peripheral resistance, and the timing of wave reflections. If you want proper insight into vascular health, you need to look at more than the average number.
Uncovering The Secrets Of Control Of Arterial Blood Pressure Understanding The Golden Standard Of Vascular Health
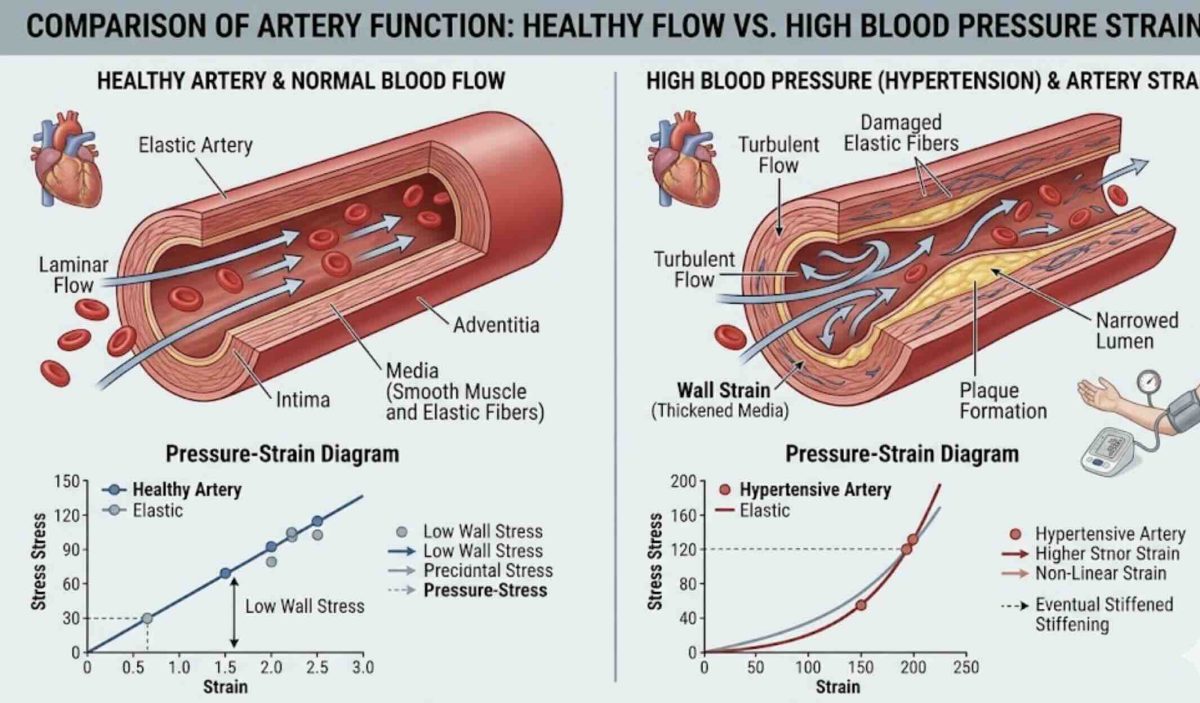
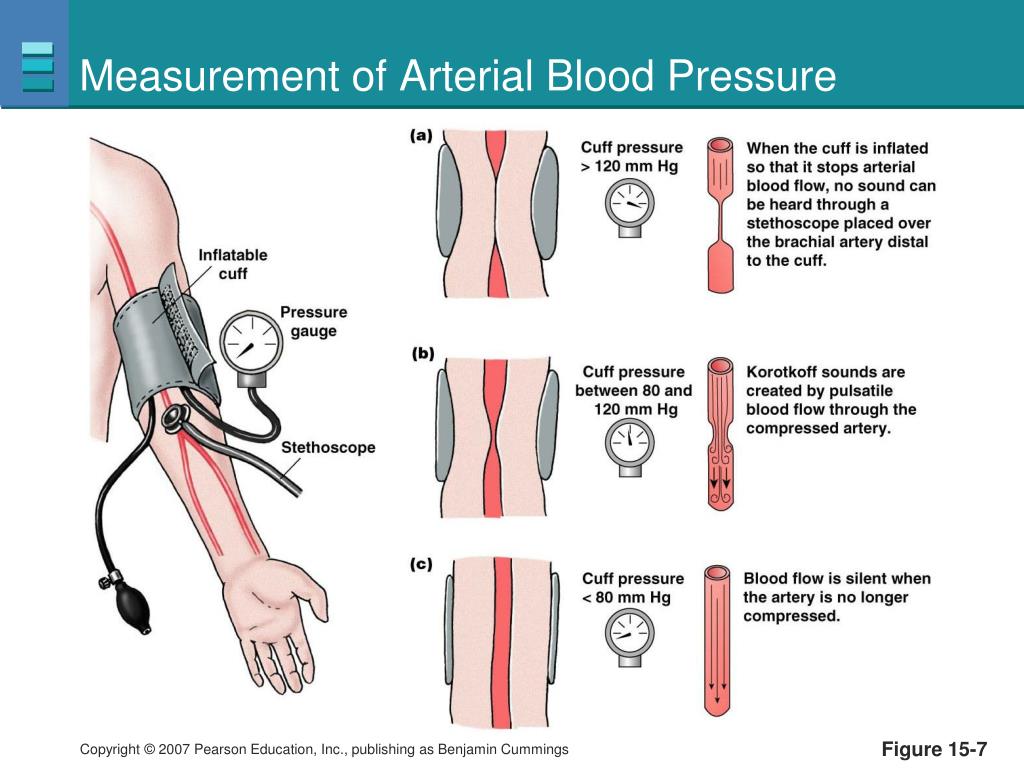
Here is the practical method I use. You begin with properly calibrated equipment. Not the cheap wrist monitors. Wrist devices are unreliable unless the arm is held exactly at heart level every single time, which almost nobody manages. A validated upper-arm oscillometric device with an appropriately sized cuff is the bare minimum. Cuff size matters more than people realize. A standard adult cuff on a muscular or larger arm will overestimate systolic pressure by ten to twenty millimeters of mercury. That is enough to mask actual hypertension completely. From there, you move into ambulatory monitoring. Twenty-four hour ABPM is the clinical golden standard for a reason. It captures daytime activity, nighttime dipping, morning surges, and white coat or masked hypertension that office visits completely miss. I have seen normotensive office readings hide a non-dipping pattern that signaled early autonomic dysfunction. The workaround for this is straightforward: order the ambulatory monitor, but insist on proper settings. Minimum of sixty second intervals during the day and one hundred twenty second intervals at night. Anything less produces sparse data that looks clean but tells you nothing useful. Once you have the ambulatory data, you look at specific metrics. Mean arterial pressure is basic. Pulse pressure variation across the day matters more for assessing arterial stiffness. A systolic-diastolic split that consistently exceeds sixty millimeters of mercury in a middle-aged patient is a red flag for reduced compliance. The augmentation index derived from applanation tonometry adds another layer. It measures how much the reflected wave amplifies the central systolic pressure. High augmentation means your arteries are stiff and your heart is working harder than the brachial reading suggests. Central aortic pressure can be five to ten millimeters higher than what your arm cuff shows, especially in older patients with stiffened vasculature.
I ran into a particularly stubborn case last year involving a sixty-two-year-old male with type two diabetes. His brachial readings were controlled on medication, his HbA1c was reasonable, and every standard marker looked acceptable. Yet his augmentation index was forty-two percent, well above the normal range. The brachial numbers were lying. We adjusted his medication to target morning surge reduction instead of just lowering the average number, and over six months his pulse wave velocity improved measurably. The key insight most clinicians overlook is that treating the average hides the peaks. Those peaks are what damage the endothelium over time. There are limitations to all of this. Ambulatory monitoring is expensive and compliance is mediocre outside of clinical settings. Home monitoring helps but introduces user error at nearly every step. Pulse wave analysis requires specialized equipment and trained operators, which means access is uneven. The augmentation index varies with heart rate, so you must account for that or the numbers are meaningless. No single metric gives you the full picture. The best approach combines at least two of these methods over a sustained period rather than relying on any one snapshot. If you are working through this yourself, start with proper home measurement technique. Sit quietly for five minutes before taking a reading. Support your arm at heart level. Take two measurements thirty seconds apart and record both. Do this morning and evening for at least one week before drawing any conclusions. Then take that data to someone who can interpret it in context. The numbers alone are just noise without the clinical framework behind them.
Get the Full Details