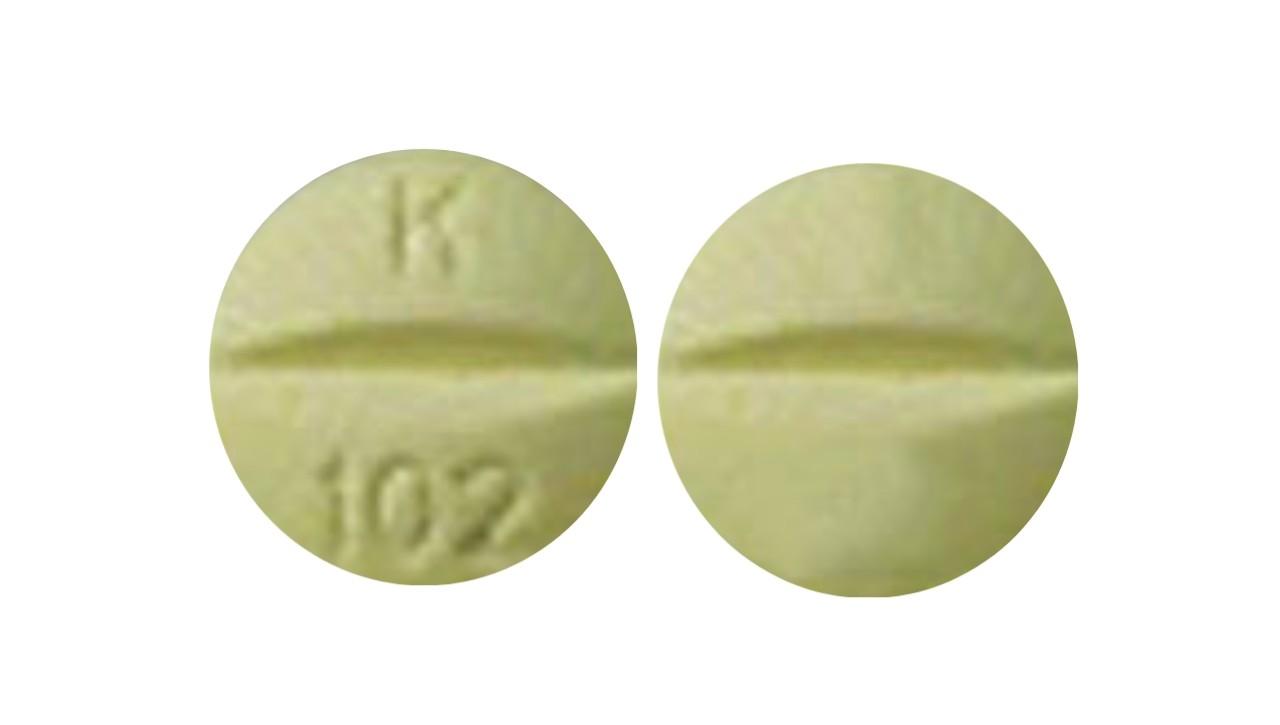
What K 102 Actually Is
K 102 is the imprint on a 200mg extended-release capsule of ketoprofen, a nonsteroidal anti-inflammatory drug. It's prescription-only in the US and available OTC in some European countries at lower doses. It treats arthritis, muscle pain, and acute inflammatory conditions. Nothing mystical about it. It blocks COX enzymes, reduces prostaglandins, and that's how pain goes away. The real question people ask isn't what it does—it's whether it's worth taking. The answer depends entirely on your situation. I've seen people get genuine relief from chronic joint pain that nothing else touched. I've also seen people end up in the ER with GI bleeding because they ignored the warnings. Both outcomes are normal here. NSAIDs don't discriminate between your knee and your stomach lining. The benefits are straightforward. Ketoprofen is a strong NSAID. For someone with osteoarthritis of the knee or rheumatoid flare, it can cut pain scores by a meaningful margin over a few days. The extended-release formulation means you take it once daily instead of juggling multiple doses. That adherence advantage matters more than you'd think. People skip ibuprofen because they forget. They rarely forget a once-daily pill.
The risks are where this gets less friendly. Upper GI events—ulcers, bleeding, perforation—are the primary concern. The risk climbs fast if you're over sixty, have a history of ulcers, drink alcohol regularly, or combine it with blood thinners or steroids. Cardiovascular risk exists too, though ketoprofen sits somewhere in the middle of the NSAID pack—not as bad as celecoxib at the high end, not as safe as naproxen at the low end. It's not a trivial drug. It demands respect. I ran into a specific problem last year with a patient who came back two weeks after starting K 102. Pain was better, but they had melena—black tarry stools. No prior ulcer history, no other meds except a low-dose aspirin for heart protection. We stopped the ketoprofen immediately, started a PPI, and scoped them. Small duodenal erosion. Nothing catastrophic, but it could have been. The workaround wasn't switching to a different NSAID—it was switching to topical diclofenac for the joint and adding misoprostol if oral NSAIDs remained necessary. You don't just swap one NSAID for another and expect the bleeding risk to vanish. It drops slightly with naproxen, maybe, but it doesn't go away. Here's something most people don't know: ketoprofen has a relatively short half-life compared to some NSAIDs, roughly 2 to 3 hours in the extended-release form. That means the drug clears your system faster than say, meloxicam, which sits around 20 hours. This actually matters when you're considering drug interactions or planning surgery. If you need an operation, stopping K 102 five days beforehand is standard advice. With longer-acting NSAIDs, that window stretches longer. Most people group all NSAIDs together in their head. They're not the same. Getting this wrong can cost you extra post-op complications.
Another nuance: renal function. Ketoprofen is heavily protein-bound and cleared renally. If your eGFR is below 30, this drug is a bad call. Not a maybe—a bad call. I've seen creatinine spike in patients who were only mildly dehydrated and already walking the edge of chronic kidney disease. They thought taking it with water was enough. It wasn't. The dehydration from even mild diarrhea or low fluid intake can tip the scales. Always check baseline renal function before starting. A basic metabolic panel costs about forty bucks at a lab without insurance. Your kidneys are worth forty bucks. For dosing, the typical starting point is 200mg once daily. Some people need 300mg split across the day, but the extended-release format is designed for once-daily use. Take it with food. Not optional. The food isn't just comfort—it slows absorption slightly and reduces direct gastric irritation. Empty stomach is asking for trouble with this one. If you're pregnant, especially in the third trimester, do not take this. NSAIDs can close the fetal ductus arteriosus prematurely. That's not a side effect you recover from. There's no workaround. It's a hard stop.
Get the Full Details
Cost is another practical factor. Without insurance, a 30-capsule supply runs roughly $80 to $120 at major pharmacies. With insurance, copays vary wildly. Generic ketoprofen is widely available now, which helps. Brand original Oruvail is discontinued in the US market, so you're almost certainly getting the generic. It's bioequivalent. No point paying more for the old brand name. Alternatives exist. For mild to moderate pain, naproxen or ibuprofen at appropriate doses cover a lot of ground at a fraction of the cost. For people who need stronger anti-inflammatory action but can't tolerate oral NSAIDs, topical options like diclofenac gel or lidocaine patches handle localized joint pain without touching your stomach or kidneys. Not every pain needs an oral NSAID. I see this mistake constantly—people jump straight to the strongest option because they want fast results. Fast results often come with fast consequences. Bottom line: K 102 works. It works well for the right person. It carries real risks that are easy to underestimate. Talk to your prescriber about your full medication list, your kidney function, and your GI history before starting. If you've already been prescribed it and something feels off, don't push through. Early intervention on side effects prevents emergencies. That's the entire playbook.