Spina Bifida Is A Real Thing That Happens During Pregnancy
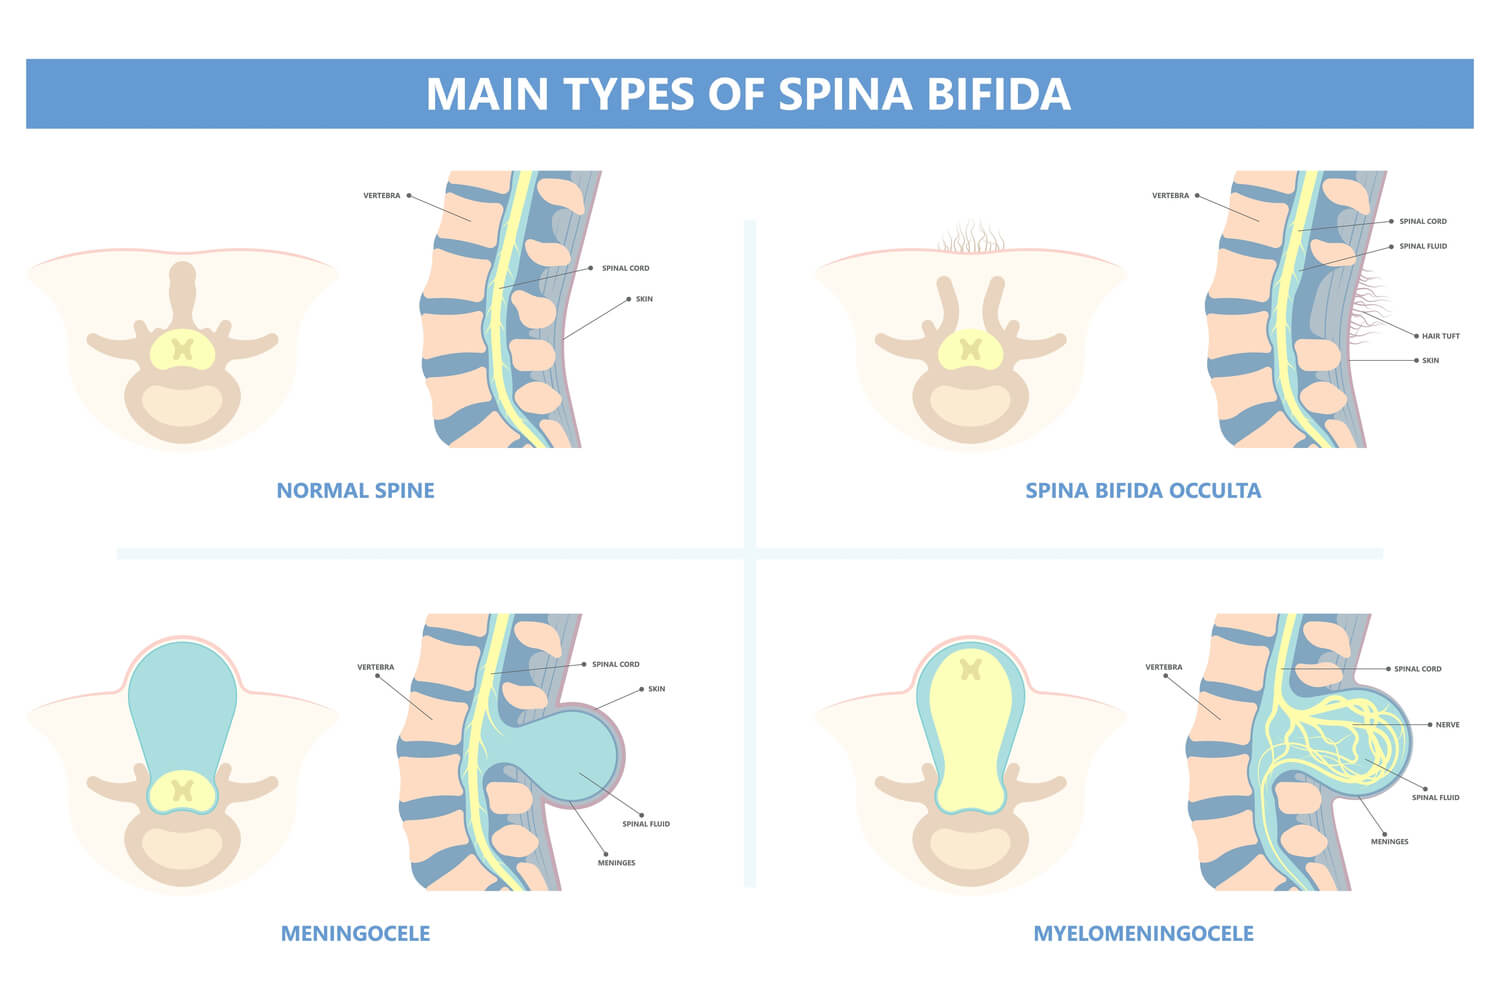
It is one of the most common birth defects in the United States, affecting roughly 3,000 pregnancies each year. The spine does not close properly during early fetal development, and that opens a range of complications that vary wildly from person to person. I spent years working with pediatric neurology cases and saw enough of these to know that every presentation is different. Some kids walk without assistance. Others need wheelchairs, catheters, and constant monitoring. The medical community understands a lot more now than even ten years ago. The causes are still not fully mapped out, but the consensus points to a combination of genetics and environmental factors. Folate deficiency before and during early pregnancy is the strongest known risk factor. That is why folic acid supplementation is standard advice for anyone trying to conceive. Beyond that, certain medications like valproic acid increase risk. Family history plays a role too, though most children with spina bifida are born to parents who have never had it. Symptoms depend entirely on where along the spine the defect occurs and how severe the opening is. There are three main types. Myelomeningocele is the most serious form. The spinal canal stays open near the lower back, and the membranes and spinal cord push through as a sac. This causes moderate to severe disability. Meningocele is less severe. The sac contains only fluid and membranes, no spinal cord tissue. People with this type often have normal intelligence and only mild physical issues. Occult spinal dysraphism is the mildest form. There is a gap in the spine but no sac, and sometimes people go undiagnosed until adulthood.
I will tell you something most patient guides leave out. Not every case shows up on a standard ultrasound. In my experience, the neural tube defects are usually visible around 18 to 20 weeks, but milder forms can be missed. We caught one case late because the mother had a higher BMI, which reduced image clarity. The baby had a smaller defect that only became obvious after birth when we noticed a dimple and a small tuft of hair on the lower back. That was a lesson in not relying solely on prenatal imaging for ruling out the milder presentations.
Treatment Exists But It Is Not A Cure
Surgery is the primary treatment, and timing matters. For myelomeningocele, surgeons can operate either before or after birth. The MOMS trial changed how we think about this. Prenatal surgery, done around 25 to 26 weeks, showed better outcomes for motor function and reduced the need for shunts compared to postnatal surgery. But prenatal surgery carries its own risks. The mother faces a higher chance of preterm delivery and uterine scar issues in future pregnancies. That decision is not simple and it should never be rushed. After birth, if surgery was not done prenatally, repair typically happens within the first few days of life. The goal is to close the opening and prevent infection. Hydrocephalus, fluid buildup in the brain, is a frequent complication. About 70 to 80 percent of children with myelomeningocele develop it and require a ventriculoperitoneal shunt. Those shunts often need revisions as the child grows. I saw a boy who went through four shunt revisions by age twelve. It is a reality that families need to understand going in. Beyond surgery, treatment is multidisciplinary. Neurology manages seizures and nerve complications. Orthopedics handles clubfoot, hip dislocations, and spinal curvature. Urology is critical because bladder and bowel dysfunction is nearly universal with myelomeningocele. Many patients need clean intermittent catheterization. This is not optional. Untreated bladder issues lead to kidney damage, which is a real long-term threat.
Get the Full Details
Long-Term Management Is Where The Work Really Happens
The acute phase ends quickly. What follows is years of therapy, equipment, and adaptive strategies. Physical therapy helps maintain mobility and prevent contractures. Braces and walkers are common. Some individuals use wheelchairs full-time. Occupational therapy focuses on daily living skills and independence. I remember a family struggling with school accommodations. The child had good cognitive function but could not manage writing tasks due to limited hand strength and mobility. The IEP process is complicated, and many parents feel unprepared for it. The workaround was pushing hard for a 504 plan that covered keyboard access, extra time, and a personal aide. It took months of meetings, but the accommodation list is what kept that kid from falling behind academically. Pain management is another area that gets short shrift in mainstream discussions. As these patients age into adulthood, chronic pain becomes a major issue. Nerve damage, spinal deformities, and overuse injuries from altered biomechanics all contribute. Opioids are rarely the right answer long-term. We tend to combine medications like gabapentin with physical strategies and sometimes surgical interventions for structural problems.
What Actually Helps And What Does Not
Folic acid before conception reduces risk significantly. This is the single most actionable thing for prospective parents. The CDC recommends 400 micrograms daily starting at least one month before pregnancy. Higher doses are recommended for women with a prior affected pregnancy or those on certain medications. Prenatal screening with maternal serum alpha-fetoprotein testing and detailed ultrasounds helps detect the condition early. If spina bifida is diagnosed prenatally, referral to a maternal-fetal medicine specialist and a pediatric neurosurgery team should happen immediately. Having a coordinated care plan before birth improves outcomes measurably. There is no cure. No supplement, diet, or alternative therapy will fix the underlying defect once it has occurred. Be very wary of anyone claiming otherwise. The evidence base is clear on what works and what does not. Steroids, stem cell treatments, and experimental therapies have not shown meaningful benefit for spina bifida in rigorous clinical trials.
Support networks matter enormously. Organizations like the Spina Bifida Association provide resources, but so do local parent groups. The emotional burden on families is real and ongoing. Adults with spina bifida who report the best quality of life tend to have strong social support and access to comprehensive medical care throughout their lives.



