What Actually Happens to Your Eyes After 40
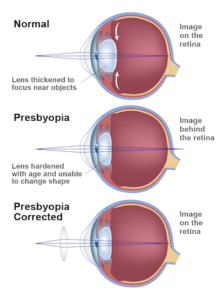
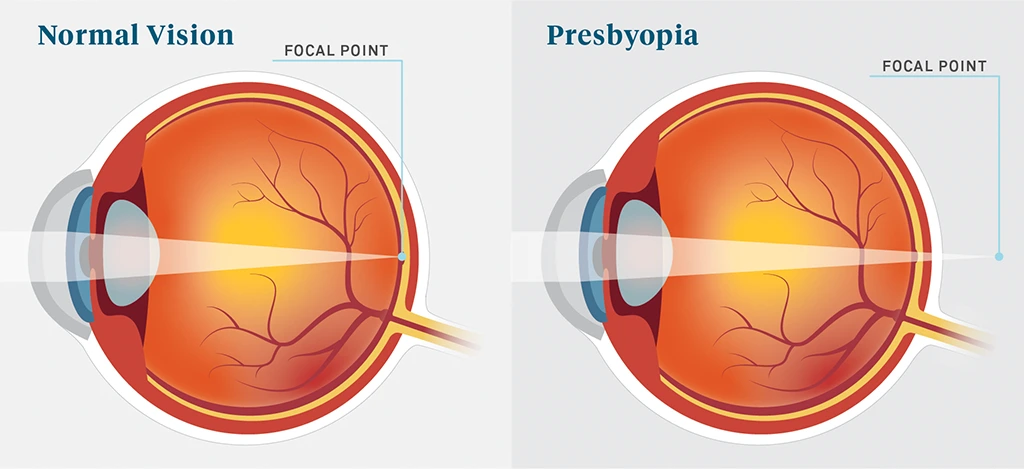
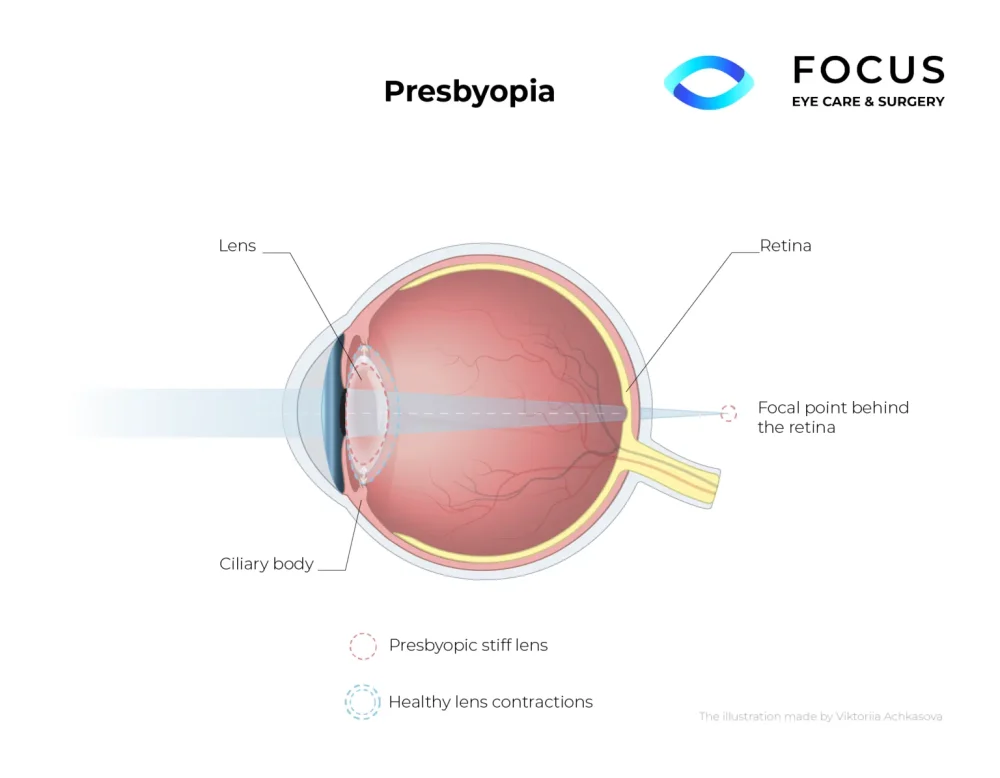
You pick up your phone to check a text message and suddenly you can't read it unless you hold it at arm's length. You frown. You squint. You move it closer, then farther away, and nothing helps. This isn't dramatic. It's not some rare condition. It's just your lens losing the ability to change shape the way it used to, and it happens to almost everyone if they live long enough. Presbyopia is the age-related loss of near focusing ability. The medical term describes exactly what's happening: the crystalline lens inside your eye becomes progressively less elastic, and the ciliary muscle that controls it simply can't bend it into the steeper curvature needed for close work. This isn't theory. This is mechanical failure of a biological component that was never designed to last beyond reproduction age, honestly speaking. The onset typically begins around age 40 to 45, though the exact timing varies based on genetics, occupational demands, and whether you were nearsighted or farsighted to start with. My own transition happened at 43. I was reading a wiring diagram on a service manual at my kitchen table and realized I had to put on my computer glasses just to see the tiny font. I didn't have computer glasses. I had reading glasses from a pharmacy that turned everything into a blurry mess because they were optimized for 16 inches, not the 24 inches my screen sat at. That mismatch alone wasted me about 40 minutes of frustrated troubleshooting before I figured out what was wrong.
Here's what most guides don't tell you about presbyopia: it doesn't progress linearly. The first decade—roughly ages 40 to 50—is where changes are fastest, maybe 0.25 to 0.50 diopters per year. After 50, the rate slows considerably. By 60, most people have stabilized at around +2.50 to +3.00 diopters of add power. Understanding this timeline matters because it changes how you approach correction. Getting glasses at 42 is different from getting them at 58. There's a common misconception that presbyopia affects distance vision. It doesn't. Your distance vision stays exactly the same. What changes is your ability to accommodate for near objects. This distinction matters enormously for treatment decisions. If someone tells you that progressive lenses will fix your distance vision too, they're wrong. If you're nearsighted and develop presbyopia, you'll still need correction for distance. Reading glasses alone won't solve the problem because they optimize for one working distance, and life doesn't work at one fixed distance.
How Correction Actually Works in Practice
The simplest approach is single-vision reading glasses. You buy them, you wear them for near tasks, you take them off for distance. This works fine for people who spend most of their time either far away or close up but not switching between the two frequently. It fails dramatically for people like me who go from looking at a computer monitor to reading a document on my desk to glancing at a whiteboard across the room every three minutes. Constantly putting glasses on and taking them off gets old within about a week. Bifocals were the standard for decades. The visible line on the lens separates distance correction from near correction. They work adequately but create a noticeable jump in your field of view whenever your eyes cross that line. You look down through the wrong part of the lens for a split second and the world snaps to a slightly different magnification. It's disorienting, and the adaptation period ranges from a few days to several weeks depending on how sensitive you are to optical artifacts. Progressive addition lenses, or varifocals, eliminate the visible line by smoothly blending distance, intermediate, and near prescriptions across the surface of the lens. The trade-off is peripheral distortion. The sides of progressive lenses aren't optically correct for anything you'd actually want to look through. Most people adapt to this within two weeks without realizing there was a problem. The real issue with progressives is the intermediate zone. If you're using a computer monitor at desk distance, the corridor between distance and near vision on a standard progressive lens is often too narrow and positioned wrong for your setup. I had to get a custom occupational progressive with an extended intermediate zone, which cost about 40 percent more than a standard pair but eliminated the head-bobbing I did every time I shifted from screen to papers on my desk.
Get the Full Details

Contact lens options exist but they introduce their own complications. Monovision contacts correct one eye for distance and the other for near. Your brain learns to favor the appropriate eye depending on what you're looking at. About 70 to 80 percent of people can adapt to monovision, but the ones who can't experience persistent depth perception issues that make activities like pouring liquid or judging stairs genuinely difficult. Multifocal contacts are another option, using concentric rings of different powers, but they reduce overall contrast sensitivity and aren't suitable for anyone with significant dry eye, which becomes more common with age anyway.
Emerging Options and What They Actually Deliver
Surgical approaches have improved substantially over the last decade. Corneal inlays, small devices implanted into the cornea of one eye to increase its focusing power, were promising but fell out of favor because results were inconsistent and complications like glare and halos were more common than initially reported. The FDA withdrew approval for the KAMRA inlay in 2020 after long-term data showed disappointing outcomes. Multipresbyopic intraocular lenses are the more reliable surgical option today. These are artificial lenses implanted during cataract surgery—or refractive lens exchange in people who haven't developed cataracts yet—that provide multiple focal points. The real question isn't whether they work but whether you're a good candidate. People with macular degeneration, glaucoma, or significant corneal irregularities tend to have poor outcomes with multifocal IOLs because those conditions interfere with the optical quality these lenses require. I worked with a client who had early-stage macular changes and expected excellent vision after multifocal IOL surgery. She ended up with decent distance vision but unacceptable near vision and significant photophobia. She needed a monofocal IOL in one eye and glasses for everything else, which was a much more modest result than she'd been sold. LASIK and PRK for presbyopia, often marketed as monovision LASIK, is another option worth discussing honestly. It reshapes the cornea so one eye is corrected for distance and the other for near. The advantage over contacts is that it's permanent. The disadvantage is that it's irreversible and the success rate for comfortable adaptation is lower than with contact lens trial first. If you've never tried monovision with contacts, don't get monovision LASIK. Try contacts for at least two weeks. If you can't adapt to them, surgery won't help you either.
What You Should Actually Do About It
Get a comprehensive eye exam. Not a quick screening at a pharmacy or a mall kiosk. A proper dilated exam with a licensed optometrist or ophthalmologist. Presbyopia can mask other conditions, and the first time you notice difficulty reading might also be the first time certain eye diseases become apparent. Glaucoma, cataracts, and macular issues often coexist with presbyopia, and treating one without checking for the others is negligent. Track your symptoms for about two weeks before your appointment. Note what distances are problematic, how long it takes to refocus when switching between near and far, whether you experience headaches or eye strain, and what time of day things get worse. This information saves time during the exam and helps your provider recommend the right correction strategy rather than just the cheapest one. Don't delay correction because you think you're too young or too old. People in their late 30s notice early signs, and people in their 70s who've never corrected presbyopia often have accumulated tension headaches and postural problems from squinting and holding reading material at awkward distances. The correction method matters less than getting some form of correction at all.
If you're over 50 and considering surgical options, understand that you'll likely need reading glasses afterward regardless of what procedure you choose. No surgical method completely eliminates the need for near vision correction in all situations. The goal is reduction, not elimination. Anyone who tells you otherwise is selling something. Presbyopia is inevitable. It's not a disease. It's not a malfunction. It's the normal wearing down of a tissue that regenerates poorly and has been under mechanical stress for decades. The people who handle it best are the ones who accept it quickly, get properly corrected, and stop treating it like a personal failing.