Understanding DIC in Medicine
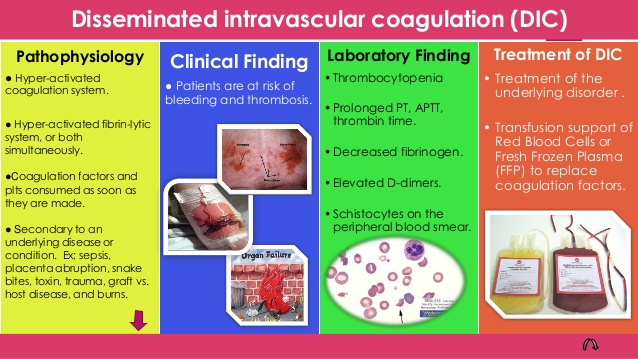
DIC is Disseminated Intravascular Coagulation. That is the full form. It sounds like a mouthful, and honestly, that is fair. The condition itself is not straightforward either. It is a systemic disorder where the blood clotting mechanism goes haywire, causing both widespread clotting and uncontrolled bleeding at the same time. People tend to think it is one or the other, but it is usually both, which is part of why it catches clinicians off guard.I remember handling a postpartum patient who presented with heavy vaginal bleeding. The initial plan was standard—uterotonics, fluids, the works. But the platelet count kept dropping, the INR was elevated, and fibrinogen was nearly undetectable. It took about two hours of back-and-forth lab results before we landed on DIC secondary to placental abruption. That is the thing about this condition. It rarely presents on its own. It almost always comes as a complication of something else. DIC is not a primary disease. It is a secondary process triggered by an underlying condition. Common triggers include severe infections like sepsis, trauma with extensive tissue damage, obstetric complications such as amniotic fluid embolism or abruptio placentae, malignancies especially acute promyelocytic leukemia, and venomous snake bites. When any of these hit the system, they activate the coagulation cascade inappropriately, leading to microvascular thrombosis throughout the body. That consumes clotting factors and platelets, which then creates a paradoxical state where the patient is simultaneously forming clots and bleeding uncontrollably. The diagnosis relies on a combination of clinical context and laboratory findings. You look for thrombocytopenia, prolonged PT and aPTT, elevated D-dimer, low fibrinogen, and the presence of schistocytes on a peripheral smear. The ISTH scoring system is commonly used to formalize this. A score of five or higher generally confirms overt DIC. It is not perfect, but it is about as good as it gets without specialized testing.
One thing beginners often miss is that DIC can be subacute or even chronic in certain patients, particularly those with solid tumors. In those cases, the laboratory abnormalities are milder, and the presentation is subtler. I had a patient with metastatic pancreatic cancer who had borderline low platelets and slightly elevated D-dimers for months. We dismissed it as chemotherapy effect until he suddenly developed diffuse bleeding from his IV sites. Looking back, that was chronic DIC that had been quietly progressing. The lesson here is that if a patient has a known trigger and you see any unexplained coagulopathy, consider DIC even when the labs do not scream it. Treatment is fundamentally about addressing the underlying cause. There is no specific drug that fixes DIC because the disorder is driven by whatever initiated it. If it is sepsis, you need antibiotics and source control. If it is an obstetric emergency, delivery is usually the decisive intervention. Supportive care involves replacing consumed clotting factors and platelets, but this is a balancing act. You do not want to fuel further thrombosis by over-replacing, but you also cannot let the patient bleed out. Fresh frozen plasma, cryoprecipitate, and platelet transfusions are used selectively based on active bleeding and lab values, not on a fixed schedule. A common pitfall is assuming that anticoagulation with heparin is the answer. In acute DIC with significant bleeding, heparin is generally contraindicated because it will make the bleeding worse. Anticoagulation has a role in chronic DIC, particularly in malignancy-associated cases, but that decision requires careful risk assessment and is not a first-line move. I have seen residents reach for heparin too quickly in acute settings, and it does not end well.
The mortality rate for DIC remains high, largely because the underlying condition is often already critical. Sepsis-induced DIC alone carries a mortality of roughly thirty to fifty percent depending on the population. Early recognition matters, but so does realistic expectations. Once DIC is established, even with aggressive management, the outcomes are heavily dependent on whether you can control the trigger quickly enough. If you want a reliable reference for the diagnostic criteria and management algorithms, the ISTH guidelines are the standard resource, and the UpToDate entry on DIC is reasonably comprehensive for quick clinical review. Beyond that, the literature is fairly consistent on the approach because there is limited alternative evidence given how sick these patients are and how hard randomized trials are to conduct in this population.
Get the Full Details