Aspirin Isn't Just a Headache Pill. It's a Pharmacological Swiss Army Knife With Serious Limitations.
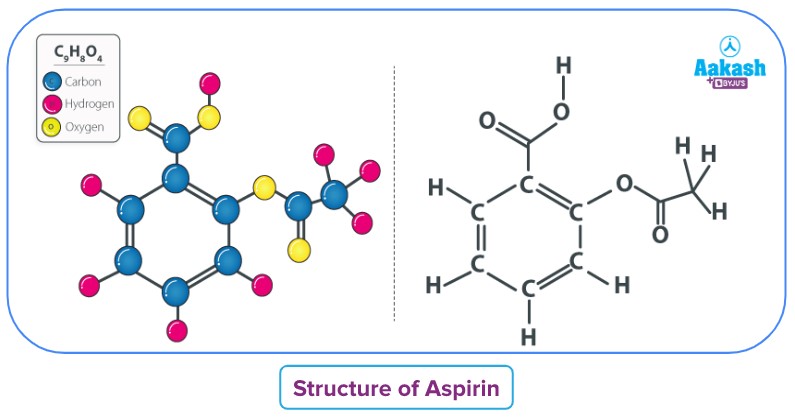
I've spent years watching people treat aspirin like it's either a miracle drug or completely harmless candy, and both attitudes are wrong. The classification alone tells you more than most primary care physicians will bother explaining. Acetylsalicylic acid is a non-steroidal anti-inflammatory drug, yes, but that label barely scratches it. It's also a salicylate, a COX-1 and COX-2 inhibitor, and at low doses an irreversible platelet aggregation blocker. That last property is what makes it useful for cardiovascular prevention and what makes it dangerous if you're about to have surgery. Start with the mechanism because everything else flows from there. Aspirin acetylates the serine residue in the active site of cyclooxygenase enzymes. COX-1 gets knocked out permanently in platelets, which have no nucleus to synthesize new enzyme. That's why a single low dose has a prolonged antiplatelet effect lasting the 7 to 10 day lifespan of the platelet. COX-2 inhibition is reversible and shorter-lived, which is why you don't get sustained anti-inflammatory effects from a 81 mg baby aspirin. The math matters here. A 325 mg tablet hits both pathways significantly. A 81 mg tablet does very little for pain or inflammation but effectively disables platelets. I ran into this distinction head-on about three years ago when a patient came in with what they thought was a stubborn tension headache. They'd been taking two 325 mg tablets every four hours for five days because their pharmacy had run out of ibuprofen. By day three they'd developed epistaxis that wouldn't stop. By day five they had coffee-ground emesis. The platelet dysfunction from the repeated dosing schedule. We stopped the aspirin, gave them sucralfate and a PPI, and monitored their hemoglobin for 48 hours. It was a textbook case of someone who didn't understand that aspirin's classification as an NSAID doesn't mean it behaves like one in terms of gastrointestinal toxicity. It's actually worse for the gastric mucosa than most alternatives because the topical irritant effect plus systemic COX-1 inhibition of protective prostaglandins creates a compound problem. Ibuprofen reversibly blocks COX-1, so platelet function recovers within hours. Aspirin doesn't give that back until new platelets are made.
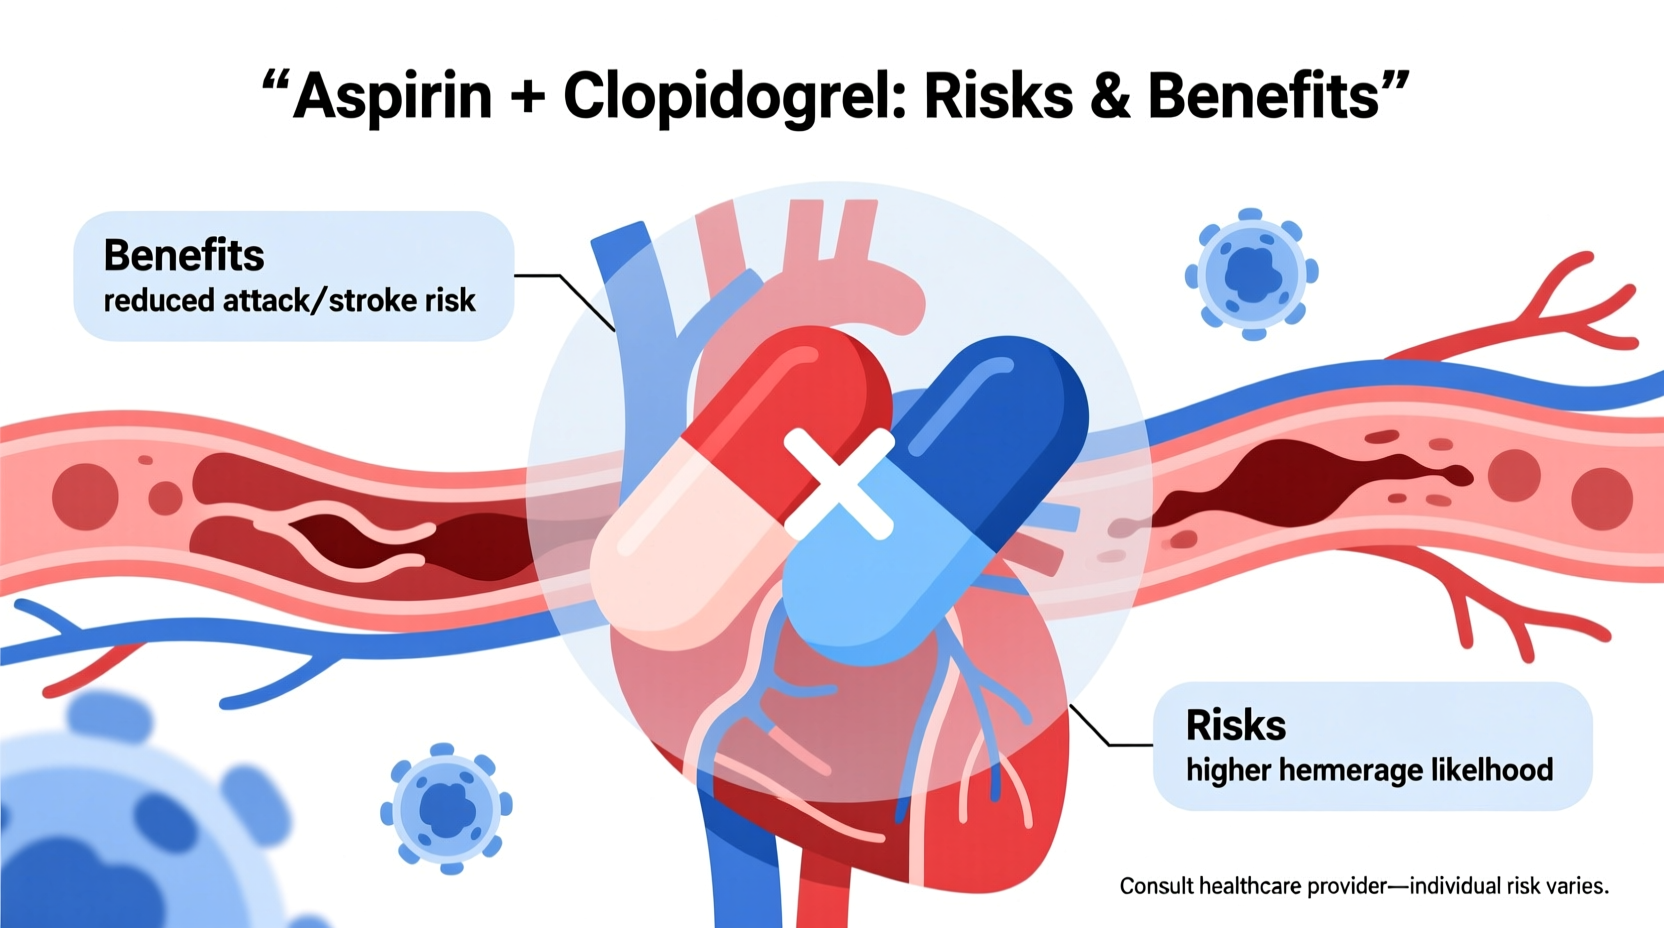
The cardiovascular indications are where aspirin earns its reputation. Secondary prevention of myocardial infarction and ischemic stroke is well-established. The absolute risk reduction is small but real. If you've already had an event, adding low-dose aspirin cuts the relative risk of a recurrent event by about 20 to 25 percent over five years. That translates to roughly one prevented event per 200 patients treated over five years. For primary prevention, the picture is messier. The 2022 USPSTF guidelines narrowed the recommendation substantially. Adults aged 40 to 59 with a 10 percent or greater 10-year cardiovascular risk might consider it, but for anyone over 60 starting primary prevention, the bleeding risk now outweighs the benefit in most cases. The ARRIVE and ASPREE trials changed the conversation by showing that in older or lower-risk populations, major bleeding events roughly offset any cardiovascular benefit. There are a few things beginners consistently miss about aspirin's dosing strategy. One is that enteric coating doesn't actually reduce GI bleeding risk. It delays absorption and may reduce direct gastric irritation, but the systemic COX-1 inhibition happens regardless. Another is that taking aspirin with food doesn't meaningfully change absorption kinetics. It might help with stomach comfort, but the antiplatelet effect is the same whether you take it before or after a meal. The more important variable is timing relative to other medications. Clopidogrel and aspirin together increase bleeding risk substantially, which is why dual antiplatelet therapy protocols exist and why the duration is carefully calibrated rather than open-ended. The preeclampsia prevention indication is another area where the classification leads to useful applications that most people don't know about. Low-dose aspirin started between 12 and 28 weeks gestation in high-risk patients reduces the incidence of preeclampsia by roughly 15 to 20 percent. The mechanism here isn't antiplatelet activity, it's likely related to the prostaglandin modulation effects on placental development. This is a prescription-level use that requires obstetric supervision and proper risk stratification. You wouldn't find it in any patient handout from your pharmacy.
Here's what most sources won't tell you about the cancer prevention data. The CAPP2 trial showed a roughly 30 percent reduction in colorectal cancer incidence after 10 or more years of daily aspirin use in Lynch syndrome patients. The effect takes a decade to appear. That's not something you start taking today and expect results from next year. For the general population, the evidence is suggestive but not conclusive enough to recommend routine use. The CRCSP trial and others have shown signals, but the benefit-to-harm ratio remains unclear outside of specific genetic populations. Drug interactions deserve a section of their own because aspirin plays badly with several common medications. Warfarin and DOACs obviously increase bleeding risk, but even therapeutic doses of NSAIDs like naproxen or diclofenac create competing GI toxicity. The interaction with corticosteroids is often overlooked. Both aspirin and steroids damage the gastric mucosa through different mechanisms, and together they're roughly multiplicative rather than additive in risk. Methotrexate is another one. Aspirin reduces renal clearance of methotrexate, and at higher doses this can push methotrexate into toxic territory. I've seen this happen with patients on low-dose weekly methotrexate for rheumatoid arthritis who started taking 650 mg aspirin three times daily for joint pain without realizing the interaction. The Reye's syndrome warning isn't theoretical. It's why aspirin is contraindicated in children and teenagers with viral infections. The association with acute encephalopathy and hepatic failure in this population is well-documented, and while the absolute incidence is low, the mortality rate is significant enough that no pediatrician will touch aspirin for fever management. Use acetaminophen or ibuprofen instead. The distinction matters because aspirin is still available over the counter and parents see it as the most familiar pain reliever.
Get the Full Details
What aspirin cannot do is prevent hemorrhagic stroke. In fact, it slightly increases the risk. The reduced risk of ischemic stroke from antiplatelet activity doesn't extend to bleeding events in the brain, and for patients with uncontrolled hypertension the risk-benefit calculation shifts further against routine use. Blood pressure management before initiating aspirin for any indication is something that gets insufficiently emphasized in clinical practice. For anyone considering long-term low-dose aspirin, the conversation with a physician should cover baseline cardiovascular risk using a tool like the ASCVD calculator, recent GI history including H. pylori status if there's any suggestion of chronic dyspepsia, renal function since aspirin affects prostaglandin-mediated renal blood flow at higher doses, and current medication list for interactions. The decision is individualized and time-dependent. Starting at age 70 with no prior events is almost certainly the wrong move. Starting at 55 with a prior stent placement is standard of care. The gap between those two scenarios is where most confusion lives.