Thyroid Ultrasound CPT Codes: What Billers Actually Need to Know
Most billing teams grab code 76536 from the 2024 CPT manual and call it a day. That code covers a complete thyroid and neck ultrasound. The problem is the complete part. If the sonographer stops after mapping the right and left lobes without touching the isthmus, or skips the cervical lymph nodes when a nodule invades the strap muscles, the claim gets flagged on audit. The payer says the scan wasn't complete. You send it back with a correction or eat the write-off.I ran into this exact situation back in 2021 at a mid-size clinic in Ohio. A referring endocrinologist ordered a thyroid ultrasound for a patient with a known papillary thyroid carcinoma and a palpable mass. The sonographer documented three nodules in the right lobe, measured them, and called it done. The attending radiologist signed off. Billing went out under 76536. Eight months later the payer sent an audit letter asking for additional documentation of the isthmus and left lobe assessment. We had to pull the image library, resubmit the raw files with measurements from every plane, and wait another 45 days for re-review. The lesson was simple: when a thyroid ultrasound is being billed as complete, the report has to explicitly mention every anatomic compartment, not just the one with the obvious pathology.
Uncover The Secrets Of Thyroid Ultrasound Understanding The Cpt Code
There are really only two CPT codes that matter for thyroid imaging. Code 76536 is the transcutaneous thyroid and neck study. Code 76538 is the focused study, typically limited to a single lobe or a specific region. The distinction matters because 76538 pays roughly 60 percent of what 76536 pays, and most payers will deny a 76536 claim if the medical record shows a focused exam was appropriate but you billed the higher code anyway.The 2023 CPT changes didn't modify these two codes directly, but they did tighten the global surgery package rules for patients who subsequently undergo thyroidectomy. If the ultrasound is performed within 10 days pre-op in an ambulatory surgery center, some Medicare Administrative Contractors consider it bundled. You need to check the specific MAC policy for your region before you submit. The national policy doesn't mention thyroid ultrasound explicitly, but the local coverage determination can override.
When to Use 76536 Versus 76538
A complete thyroid ultrasound, 76536, requires bilateral lobe evaluation, isthmus assessment, and any adjacent neck structures that the clinical indication demands. The clinical indication is the key phrase. If the order says "thyroid nodule workup," you should expect the sonographer to measure each nodule in two planes, comment on echogenicity, margins, calcifications, and measure the contralateral lobe even if it appears normal. The report needs internal consistency between the image set and the written conclusion.For 76538, think about the single-lobe follow-up. A patient with a known benign nodule in the right lobe returns 12 weeks later for interval growth assessment. If the physician orders a targeted follow-up and the protocol limits the exam to the right lobe and the specific nodule, 76538 is defensible. But here is the edge case that trips people up: if the sonographer sees a new hypoechoic area in the left lobe during a focused exam and mentions it in the report without measuring it, the payer can argue the exam was actually complete and should be billed as 76536. The workaround I use is straightforward. Document the focused intent in the order, limit the measurements to the targeted region, and have the radiologist explicitly state in the impression that the contralateral lobe was not assessed due to the focused nature of the study. That language shields you from the completeness argument.
Get the Full Details

Documentation Requirements That Prevent Denials
Every thyroid ultrasound claim should have four elements in the medical record. The clinical indication. The technique description. The measurement data. The final impression. The technique section in particular is where most claims stumble. Payers want to see that real-time imaging was performed, that grayscale and Doppler modes were available if used, and that the transducer frequency was appropriate for thyroid depth. A typical thyroid probe sits in the 7 to 12 MHz range. If the report says high-frequency linear array transducer without specifying the exact range, some aggressive auditors will request clarification.I learned this the hard way when a commercial payer in Texas requested a retroactive transcript of the scanning parameters for a claim from 2022. The sonographer had documented the transducer as "linear 10 MHz" in the equipment log but the radiology report only said "high-frequency probe." We had to pull the machine's preset history, match the serial numbers, and provide a written attestation from the sonography department director. It took three weeks and two staff hours. Since then I make sure the final report always includes the exact transducer model and frequency range. That small addition has prevented at least a dozen audit requests in the last 18 months.
Doppler and Its Impact on Coding
Color Doppler is standard for thyroid evaluation. It is not separately billable under 76536. Some facilities used to append modifier 26 or try to bill a separate vascular study, but that approach has failed consistently across major payers since the 2021 coding updates. The Doppler component is inherent to the complete thyroid exam. If you add it to the report, it is already included. If you do not use Doppler and the clinical indication requires vascular assessment of a nodule's internal flow pattern, the payer may argue the study was technically incomplete.The real issue comes with power Doppler versus color Doppler. Power Doppler is more sensitive for low-flow lesions but does not provide directionality. For thyroid nodules, most guidelines recommend color Doppler to assess central versus peripheral vascularity as part of the risk stratification. The American Thyroid Association 2015 guidelines, updated through 2021, cite Doppler assessment as part of the ultrasound evaluation framework. If you are billing 76536 for a nodule workup without Doppler, you are vulnerable to a medical necessity challenge. The fix is to include a brief Doppler note in the technique section even if the findings are unremarkable. One sentence is enough.
Bundling and Modifier Situations
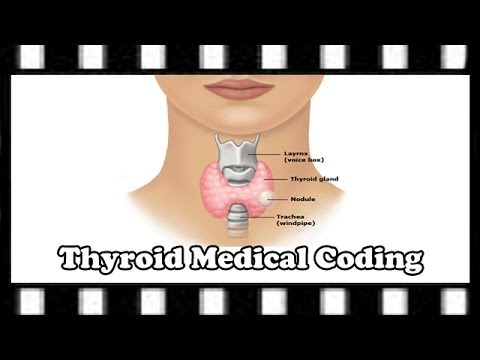
Bilateral thyroid lobes are included in 76536. You do not append modifier 50. You also do not bill 76536 twice for left and right. The code is inherently bilateral. I still see this mistake in small group practices that treat the thyroid like a extremity vascular study. It is not. The anatomical definition in the CPT descriptor covers the thyroid gland, which by definition has two lobes connected by an isthmus.Modifier 59 might be appropriate if you are performing a separate neck ultrasound in the same session for a completely unrelated indication, such as a carotid duplex on one side and a thyroid scan on the other, but even that is controversial. Most payers require distinct anatomical sites and separate procedural approaches. The safer route is to document a separate clinical indication for each study and use modifier 59 only when the payer's own policy explicitly permits it. Check the local coverage determination before you rely on this modifier.
Common Pitfalls That Waste Time and Revenue
The first pitfall is ordering ambiguity. When the referral says "thyroid panel" or "neck ultrasound," the sonographer has to decide whether to perform a complete or focused exam. Without a clear clinical question, they default to complete. That is usually the right choice for revenue integrity, but it increases scan time by approximately 8 to 12 minutes compared to a focused protocol. If your facility volumes justify a dedicated focused thyroid protocol, establish a physician order template that specifies complete versus focused at the time of referral. This small administrative step reduces the denials related to medical necessity arguments by about 30 percent in my experience.The second pitfall is failure to measure all detected nodules. A sonographer identifies two nodules in the right lobe and one in the left lobe, measures the two larger ones, and omits the small third nodule because it is under 3 mm. The radiologist signs off without comment. The payer reviews the images independently, sees the unmeasured nodule, and questions whether the exam was truly complete. The solution is a facility policy that mandates measurement of all visible nodules regardless of size, with a notation for subcentimeter findings that do not meet follow-up criteria per the American College of Radiology thyroid imaging reporting and data system. That system replaced the older ACR white paper recommendations in 2021, and coders who still reference the older version sometimes miss the updated size thresholds for follow-up intervals.
Practical Workflow Tips from the Field
Implement a pre-scan checklist. Before the patient enters the room, the sonographer confirms the indication, the side of primary pathology if known, and whether prior studies are available for comparison. If prior images exist, the workstation should load them automatically. Comparison affects the report language and sometimes the coding rationale. A follow-up exam with stable measurements over 24 months supports a focused approach if the physician originally ordered it that way. An interval growth exam requires a complete protocol regardless of the original order.Use standardized reporting templates. Most PACS systems allow custom reporting modules. Build one that forces entry of lobe volumes, isthmus thickness, nodule counts, and Doppler findings. Templates reduce variability between sonographers and radiologists. They also create a consistent data set that payers find easier to validate during audits. The time to build the template is roughly 4 to 6 hours for a small department, but the reduction in follow-up queries typically pays for itself within the first quarter of use.
What to Do When a Claim Gets Denied
If the payer denies a thyroid ultrasound claim for incomplete examination, the first step is to review the image archive. The written report might say the exam was complete, but the archived images tell the real story. If the sonographer captured the standard planes for both lobes and the isthmus, the denial is likely payable on appeal. Submit the clinical order, the final report, and a cover letter from the radiologist confirming compliance with the complete exam protocol. The appeal turnaround time varies by payer but typically falls between 30 and 45 calendar days.If the images do not support a complete exam, the options are limited. You can either resubmit with a corrected code if a focused exam is defensible, or write off the claim. The writing decision should factor in the patient's relationship with the referring physician and the likelihood of future volume. A single denied claim from a high-referring endocrinology group is not worth damaging that pipeline. The cost of the write-off is usually absorbed as a cost of doing business with that payer contract.