What Uhealth Chart Actually Does
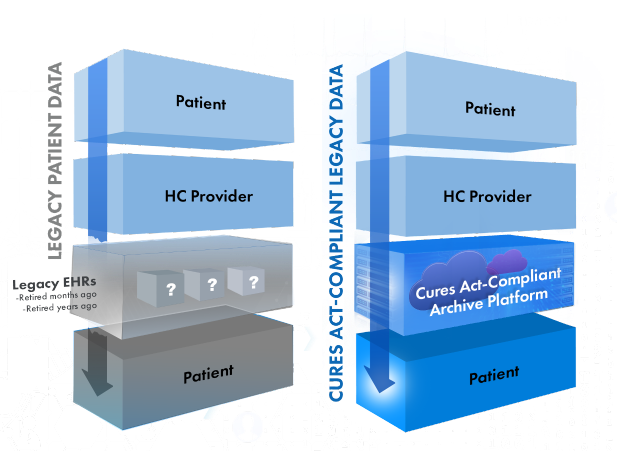
Most hospitals run on at least three separate systems that do not talk to each other properly. A patient sees a specialist, gets admitted to inpatient, then gets discharged and follows up at a clinic — and every single touchpoint lives in a different database with different field structures. Uhealth Chart is a data management platform that sits above those fragmented systems and creates a unified longitudinal patient record. It pulls data from EHRs, lab systems, imaging archives, and billing modules into a single view with standardized identifiers. I worked through an implementation with a regional health network last year. We had roughly 240,000 patient records spread across two legacy EHR platforms, one standalone lab system, and a pharmacy database that predated HL7 FHIR standards. Uhealth Chart mapped those systems through their interoperability layer — primarily FHIR R4 resources and C-CDA document exchange — and rebuilt patient identities using a probabilistic matching algorithm with deterministic anchors like SSN fragments and date of birth. The deduplication pass alone found and merged 18,000 phantom duplicates that were causing duplicate encounters and conflicting medication lists.
Uhealth Chart The Silent Revolution In Patient Data Management And Healthcare Efficiency
The value proposition here is not flashy. It is mostly boring, which is why it matters. You get a complete patient timeline with encounter dates, lab values normalized to common codes, medication histories reconciled across prescribers, and imaging reports linked to the correct study. That is what health systems buy it for. The workflow works like this. You start by configuring your data sources through the Uhealth Connector module. Each EHR or legacy system gets its own adapter with field mapping rules. Then you run the identity resolution engine, which produces a match score between potential duplicates. Records scoring above your threshold get flagged for manual review. After that, you activate the clinical data repository, which stores everything in a FHIR-compliant format, and finally point your downstream applications — dashboards, analytics tools, quality reporting — at the unified data layer. Setting up the connectors usually takes about two weeks per source system if your IT team already has EHR API access. The identity resolution phase is the part that eats time. On a medium-sized health system, initial deduplication runs can take three to five days depending on record volume and data quality. I found that running the matcher in batches of 50,000 patients and reviewing the overlap zone between clusters prevented batch boundary errors where patients near the end of one group would miss matches against the start of the next.
Common Pitfalls People Miss
The biggest problem is not the software. It is your source data quality. If your legacy EHR has free-text fields populated with inconsistent abbreviations — and almost all of them do — the normalization layer will produce garbage output regardless of how well Uhealth Chart is configured. I once spent three weeks fixing a medication mapping issue that traced back to a single outpatient clinic that used brand names and trade names interchangeably without any standardization. The fix was writing custom codebooks for that facility and backfilling two years of records. Another thing nobody warns you about is the cost of continuous data reconciliation. Uhealth Chart will merge your historical data beautifully, but every new patient record created in any connected system generates a sync event. Your data quality drifts over time unless you allocate staff to monitor match failures and run periodic reconciliation jobs. We set up a daily job that exports failed merge attempts and routes them to a small team of clinical data analysts. Budget for that staffing before you launch, not after. There is also the compliance layer that quietly slows everything down. If you are handling PHI, Uhealth Chart stores everything encrypted at rest with AES-256 and in transit with TLS 1.3. That is standard, but your organization still needs to configure RBAC properly and maintain audit logs. I have seen teams skip the audit log configuration step during initial rollout because they assumed the platform handled it automatically. It does not. The audit trail requires explicit enablement and proper log retention policy setup. Without it, you are not HIPAA compliant on the data governance side, regardless of what the vendor brochure says.
Get the Full Details
When Uhealth Chart Does Not Work Well
The platform assumes your source systems have at least basic interoperability capabilities. Small practices running entirely on paper charts or very old EHR versions without API support will not get much value out of it. There is a manual data import path, but it is slow and error-prone. You are better off using a document scanning and OCR pipeline to digitize paper records before attempting import. Another limitation: Uhealth Chart is not a clinical decision support tool. It manages and presents data. It does not generate alerts, suggest diagnoses, or flag drug interactions on its own. If your organization expects CDS features out of the box, you need to integrate a separate engine like those from Epic's Cogito orcern's DSDM. I learned this the hard way when our quality team expected the platform to auto-flag HbA1c gaps during diabetic care reporting. It does not. We had to connect a separate rules engine to the Uhealth data layer and build our own query logic. Cost is another factor that does not show up in initial demos. licensing scales with patient count and data volume. A mid-size hospital with 150,000 active patients and five connected data sources typically pays in the six-figure annual range when you factor in implementation services, ongoing support, and infrastructure. Smaller networks sometimes find ROI only after twelve to eighteen months, which is a tough sell to finance teams that want quarter-one results.
Practical Implementation Notes
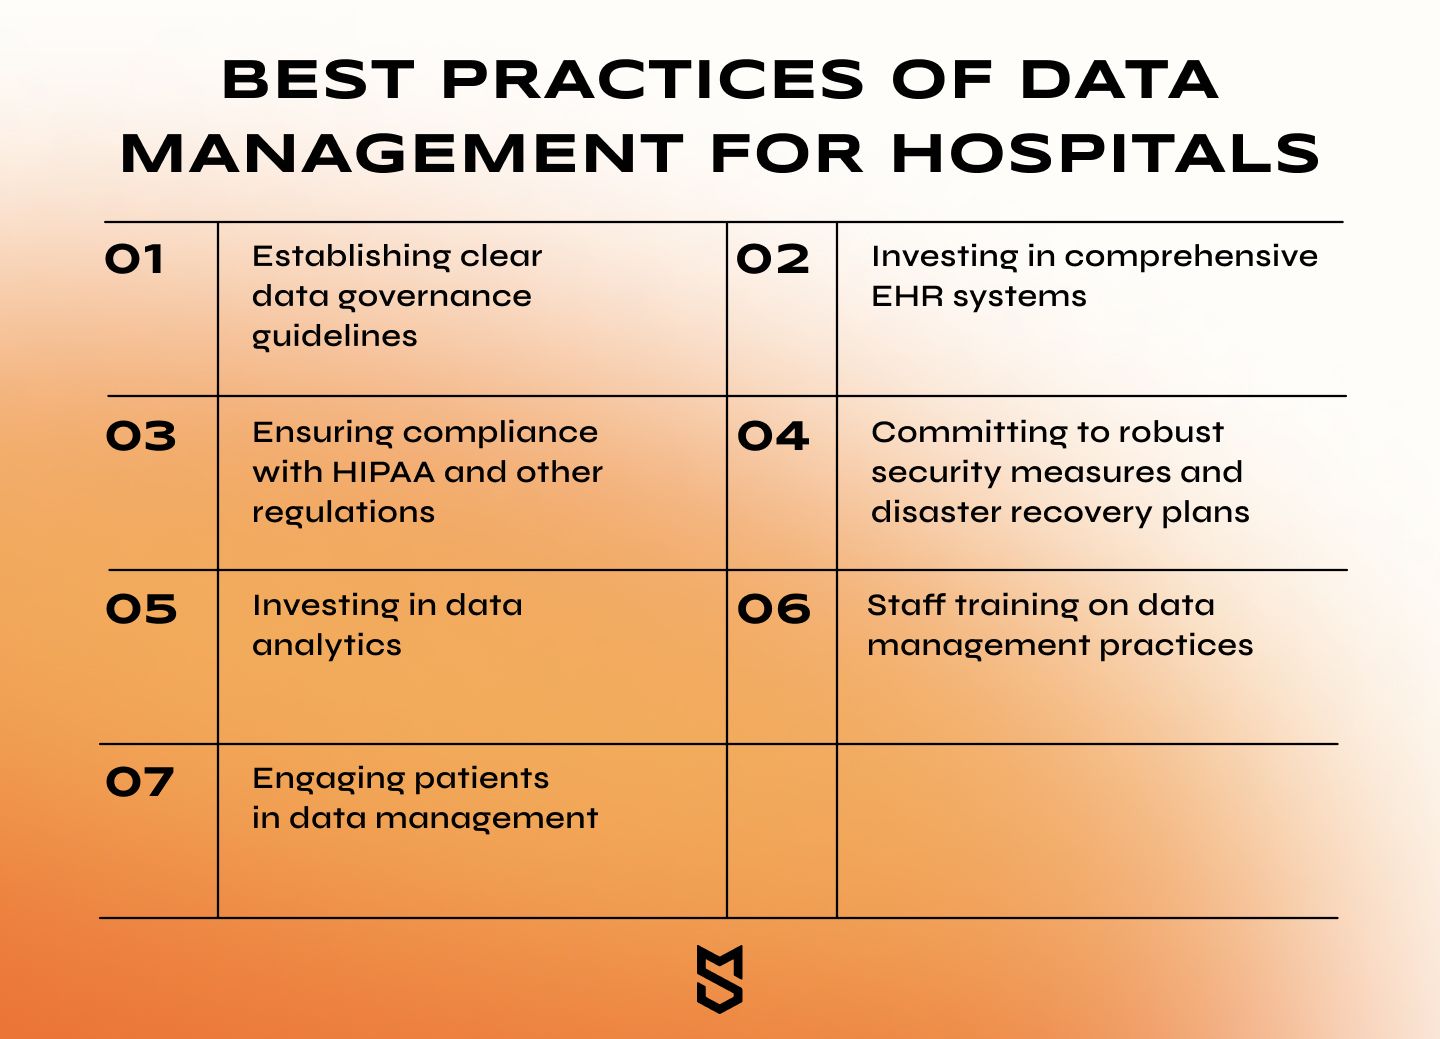
If you are planning a rollout, start with a single data source and one clinical department. Do not attempt a simultaneous migration across all systems. I have seen two implementations fail because the project team tried to connect four EHRs, a lab system, and a pharmacy network in the same month. Data quality issues in one source cascade into the identity resolution process and corrupt matches across the board. Get your data governance committee involved before configuration begins. Who owns the master patient index? Who approves manual merge decisions? What is the escalation path when the automated matcher flags a suspicious duplicate? These decisions should be made by people who understand the clinical and legal implications, not by the IT team that is just trying to get the platform online. The committee took us about three weeks to stand up, but it saved us at least two months of rework later when questions about data ownership came up from compliance auditors. Training matters more than most organizations expect. Clinicians are not going to use a unified patient record if it adds clicks to their workflow. We embedded the new dashboard into the existing EHR login flow using SSO and reduced the number of clicks to access a full patient summary from seven to three. Adoption jumped from 34 percent in the first month to 71 percent by month four after that change. The platform itself did not change. Only the access path did.
The documentation is adequate but not comprehensive. The vendor provides a knowledge base with setup guides and API references, but edge cases like partial record merges, orphaned encounter linking, and bulk patient de-duplication after system retirement are only covered in troubleshooting threads or paid support interactions. I recommend budgeting for at least one professional services engagement during implementation to handle scenarios that are not documented. It costs extra upfront but prevents three months of internal trial and error.