Setting Up and Navigating UHC's Provider Network for Digital Care Delivery
The provider network is massive, which means it's also full of contradictions. You'll pull up a directory listing that says a specialist accepts your payer, then submit a claim and watch it bounce back with a "not in-network" denial. This happens constantly. The Uhc Provider The Healthcare Network Redefining Digital Care Delivery system sounds like a unified concept when you read the marketing copy, but in practice it's three or four different backend systems that occasionally fail to sync, and you learn to work around the gaps rather than expecting the tool to resolve them. UnitedHealthcare maintains one of the largest provider directories in the country, roughly 1.4 million providers across their various plans. The "digital care delivery" component is the newer layer built on top of that existing network infrastructure, covering telehealth authorization, store-and-forward image routing, and remote patient monitoring reimbursement. These are not separate systems — they sit inside the same provider enrollment and credentialing framework, which is why a provider's eligibility for in-person services doesn't automatically guarantee their eligibility for digital modalities. The directory splits into distinct tiers. Tier 1 providers are fully contracted with broad service authorization. Tier 2 includes providers who are in-network for select plan products but may have restrictions on telehealth or out-of-state practice. Tier 3 is the reference-only category, meaning the provider accepts UHC at fee-for-service rates but isn't in the primary contracted network. The portal doesn't always label these tiers clearly, so you have to infer them from plan-level eligibility flags and historical claims data.
I ran into a concrete problem last year when a client was setting up a telehealth program for behavioral health providers across three states. The directory showed every provider as "in-network" for their respective markets. We filed five referrals through the digital platform and got three denials. The issue wasn't the provider network status — it was that two of those providers had been credentialed only for in-person mental health services under their specific plan product. Their telehealth authorization codes existed in the system but were marked as inactive because the practice had never submitted a digital care addendum during renewal. The workaround was pulling the enrollment printout for each provider, locating the Telehealth Services Indicator field in Section 4, and re-submitting the addendum through the provider portal. It took seven business days per provider and required calling the network operations desk to escalate because the automated system kept returning a generic "credentials not found" error. Knowing that field exists and where to find it saved me about two weeks of back-and-forth.
How the Digital Care Platform Actually Works
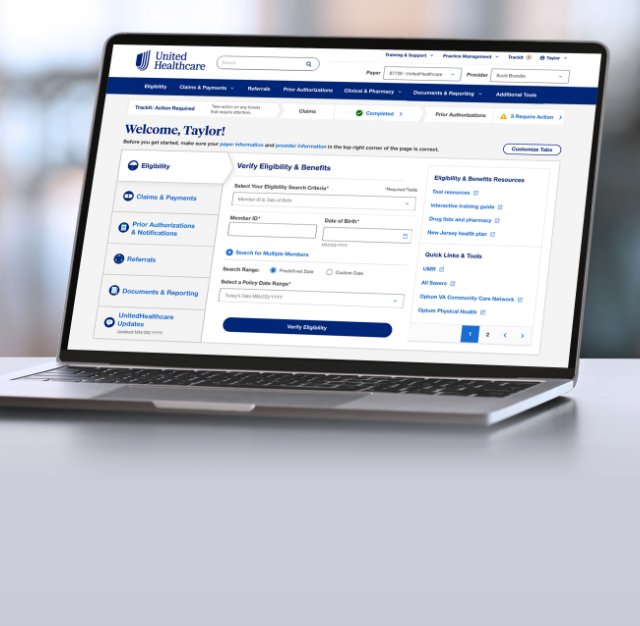
Providers enroll through the UHC Provider Center, which is the primary portal for applications, credentialing status checks, and directory updates. The platform also hosts a separate digital health module that handles telehealth authorization requests, Virtual Care participation agreements, and remote monitoring code validation. These two sections aren't always linked cleanly — you might submit a digital care request in one area and never receive a confirmation email because the transaction was logged in the other. The credentialing timeline runs 90 to 120 days for new applications. Expedited processing is available for providers completing facility transitions or merging practices, but it requires a written request with documentation of the organizational change. Most providers fall into the standard queue, so if you're evaluating network inclusion for a new practice location, start the process at least four months before your anticipated launch date. Directory verification is where most people get burned. The online directory search tool pulls from a database that refreshes on a rolling 30-day cycle. A provider who updated their profile last week may still show an expired address or outdated specialty listing until the next batch sync completes. I learned to verify directory status through two channels simultaneously: the live directory search for current listings, and the downloadable monthly provider file for the baseline data. Cross-referencing those two sources catches discrepancies that neither view reveals on its own. The downloadable file is accessible from the Provider Center under the "Reports and Downloads" tab, but it requires an active provider agreement number to access, which some smaller practices don't have until their first claim adjudicates successfully.
Get the Full Details

Common Pitfalls and What Beginners Miss
One counter-intuitive detail that trips people up: a provider can appear in-network for UHC Marketplace plans but out-of-network for UHC Commercial plans, even within the same state. The contracting happens separately for each plan type, and the directory search defaults to showing all UHC products unless you specifically filter by plan category. I've seen referral coordinators send patients to specialists based on a general "UHC accepted" result, only for the patient to show up and discover their particular plan doesn't cover that provider's specialty at all. Another issue that almost nobody mentions upfront is the telehealth parity law interaction. After the public health emergency declarations, many states enacted permanent telehealth parity requirements, but UHC's implementation of those requirements varies by state and by plan product. A behavioral health visit coded as a telehealth service in one state may carry a different reimbursement rate or require a specific modifier in another, and the provider directory doesn't display these nuances. The only reliable way to confirm is checking the plan-specific benefit summary and, when in doubt, calling the provider services line with the exact CPT code and state in question. The hold times range from 15 to 45 minutes depending on the regional call center, so you'll want to have the provider's NPI and enrollment ID ready before you call. The remote patient monitoring space has its own set of quirks. UHC covers RPM for specific chronic conditions — primarily diabetes, hypertension, and COPD — but only when the device used is on their approved technology list. The list changes roughly twice a year, and the current version is buried in a clinical policy bulletin rather than the main provider portal. I keep a local copy of the bulletin and flag it when new devices get added or old ones are removed. A clinic I worked with recently switched to a new continuous glucose monitor vendor and assumed it was covered because the manufacturer marketed it as UHC-compatible. It wasn't on the approved list until the next policy update, so three months of claims went out with denials that took another six months to reverse.
Practical Steps to Get Your Practice Set Up
Start by confirming your NPI Type 1 designation is active and matches the TIN on file. Any mismatch between your individual NPI and your practice's group NPI will cause the directory to list you under the wrong entity, which cascades into claim rejections and patient confusion. You can verify this through the NPPES lookup tool, then cross-reference with the UHC Provider Center directory entry. Next, complete the provider application through the portal. Gather your malpractice insurance certificates, DEA registration if applicable, and board certification documents before you start. The application has about 40 fields, and having the supporting documents open in another window cuts the submission time from roughly 45 minutes to about 12. Missing a single field — usually the second phone number or the fax number for the primary practice location — triggers an automatic hold that adds 10 to 14 days to the timeline. Once your application is submitted, monitor the status weekly through the Provider Center. The dashboard shows four possible states: received, under review, completed, or additional information requested. The "under review" stage is where most delays happen, and there's no way to accelerate it unless you request expedited processing with proper documentation. I set a calendar reminder for day 45 after submission to check in, because that's typically when the system moves a standard application from review to either completion or a request for more information.
After credentialing completes, immediately verify your directory listing by searching your name and NPI in the public directory. Confirm your address, phone number, specialty classifications, and plan acceptances are all correct. If anything is wrong, submit a profile update through the portal. Directory corrections take 15 to 20 business days to propagate, so don't wait until a patient call or a claims denial forces you to fix it. For digital care specifically, once your base credentialing is active, navigate to the telehealth authorization section and submit the Virtual Care Services Agreement. This step is optional for some plan products but mandatory if you want to bill telehealth visits under UHC's digital care reimbursement policies. The agreement requires you to confirm compliance with state telehealth laws, consent procedures, and technology standards. Processing takes about 10 business days, and you'll receive a confirmation letter via mail and an update to your provider record in the system.
Where This System Falls Short
The directory search interface is clunky and produces inconsistent results. Sometimes a search by specialty returns providers who don't actually practice that specialty within UHC's network parameters. Sometimes a geographic radius search omits providers who are actually in-network for your plan. I spend about 20 minutes per provider verification call going through a manual checklist: confirm NPI, confirm plan product, confirm telehealth authorization, and confirm active status. No amount of portal automation replaces that verification step. Credentialing turnaround times have gotten longer, not shorter. The advertised 90-day window assumes a straightforward application with no gaps in employment history and no need for primary source verification delays. If you've practiced in multiple states, changed practices in the last five years, or have a gap in malpractice coverage, expect the process to stretch to 150 days or more. The portal gives you no real-time estimate of where you stand in the queue, so there's no way to plan around it. The digital care platform's notification system is unreliable. Status changes, document requests, and approval confirmations sometimes arrive as emails and sometimes don't. I recommend enabling text notifications in the portal settings and checking the Provider Center dashboard daily during active applications rather than relying on email alerts.
If your practice is small or newly established, UHC's process may feel disproportionately complex compared to other payers. Some regional plans and ACO-aligned networks offer faster onboarding with simpler digital integration tools. Depending on your location and patient population, evaluating alternatives like Aetna's provider portal or Cigna's network tools might save you several weeks of administrative overhead, though those systems have their own directory accuracy issues in different markets. The trade-off is usually between speed and network size, not quality.
Bottom Line on Navigation
The UHC provider network is comprehensive but internally fragmented. The digital care delivery layer works well for established practices with clean credentialing histories, but it requires manual verification at multiple touchpoints. Budget two to three hours per provider for initial setup and directory verification, and another hour per month for ongoing maintenance if you're adding or removing providers. The system will handle routine tasks without intervention, but the edge cases — plan-specific telehealth restrictions, directory sync delays, and approval status inconsistencies — are where you'll lose time if you're not tracking them proactively.