What Happens When You Turn 65 and Your Employer Insurance Just… Vanishes
I spent three years working claims at an insurance adjusting firm, and Medicare remains the single most confusing product people have to deal with. It is not complex on paper. The language is clear enough. The problem is that Medicare does not behave like private insurance. It behaves like a fragmented government program that changes depending on where you live, which part you are in, and whether your doctor happens to accept assignment that week. Most people think Medicare is one thing. It is four different programs stitched together with overlapping rules. Part A covers hospital stays. Part B covers outpatient services. Part C is Medicare Advantage, which bundles everything into a private plan. Part D handles prescriptions. You can combine them in ways that sound logical but create massive coverage gaps. I saw this happen constantly.
Uhc Medicare Decoded What Retirees And Families Must Know In 2024
UnitedHealthcare operates the largest Medicare Advantage portfolio in the country. That means more people are enrolled in UHC Medicare plans than any other carrier. It also means more people are confused about what their plan actually covers. The confusion is not accidental. Medicare Advantage plans are required by law to show benefits in a standardized document called the Evidence of Coverage. That document is over one hundred pages long and deliberately written in plain language that still requires a law degree to parse accurately. Here is what most retirees miss. Your UHC Medicare plan may have a tiered formulary for prescription drugs. That means the same medication costs different amounts depending on which tier it sits on. Tier 1 is generic preferred. Tier 4 is specialty brand. A medication you paid ten dollars a month for under your old employer plan might jump to sixty dollars a month on Medicare. This is not a bug. It is how formularies work. But nobody warns you about it until you pick up the prescription and the price shocks you. I dealt with a case last year where a retiree named Harold was switched from Humira to a biosimilar because his UHC Medicare Part D plan moved Humira to tier 4. He was paying two hundred eighty dollars a month before. His new copay was four hundred twelve dollars. He called the pharmacy and they had already filled it. He could not simply return it. The workaround was filing an expedited formulary exception through UHC's clinical pharmacy team. They approved it within forty-eight hours because his rheumatologist provided a letter stating the biosimilar had caused a documented adverse reaction. The letter had to include his medical record number and a specific ICD-10 code. Without those two fields, the claim gets denied automatically. I learned this the hard way watching people get turned away.
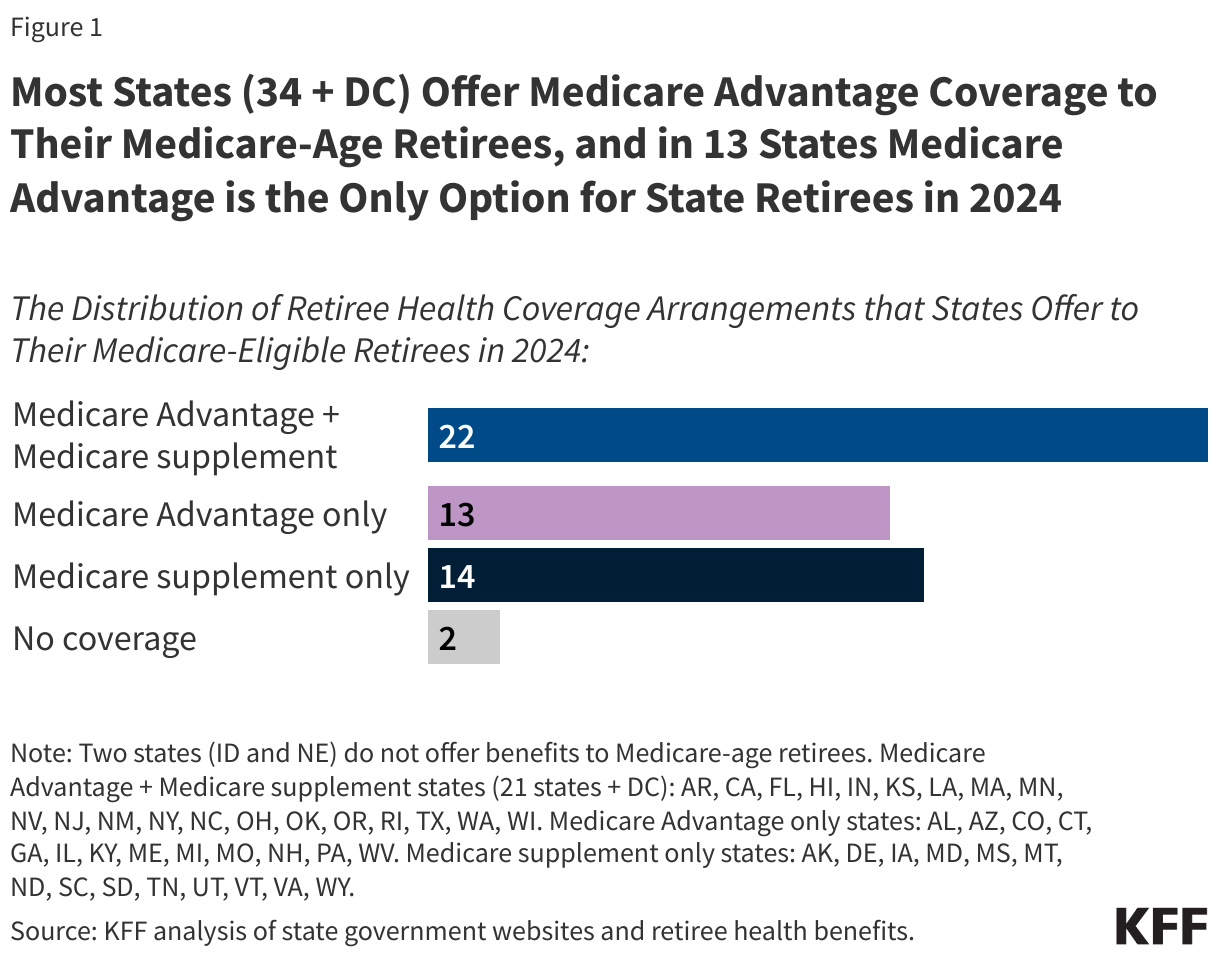
Understanding the difference between Medicare Supplement and Medicare Advantage is the single most important decision a retiree makes. A Medicare Supplement, also called Medigap, works with Original Medicare. You pick any doctor who accepts Medicare. The supplement pays the coinsurance and deductible portions. A Medicare Advantage plan replaces Original Medicare entirely. You must use the plan's network, usually. Prior authorization is required for specialists and certain procedures. The trade-off is lower premiums and extra benefits like dental and vision. The cost is reduced flexibility. UnitedHealthcare offers both types of products. Their Medigap plans operate under different policy numbers depending on your state. They offer A through N standard plans plus some state-specific variants. Their Medicare Advantage plans come in HMO, PPO, and PFFS configurations. An HMO requires you to pick a primary care physician and get referrals for specialists. A PPO lets you see anyone who accepts Medicare but charges more for out-of-network care. A PFFS plan decides on its own which providers it will pay. PFFS is the least predictable option and I rarely recommend it unless you have no other choice in your area. The enrollment windows are rigid. You cannot sign up for Medicare anytime. The Initial Enrollment Period lasts seven months centered around your 65th birthday. If you miss it, you enter the General Enrollment Period from January 1 through March 31, and your coverage does not start until July 1. That is a six-month gap you are paying out of pocket for. There is also the Annual Enrollment Period from October 15 through December 7 when you can switch plans. Then there is the Medicare Advantage Open Enrollment Period from January 1 through March 31, which allows you to switch once. Do not confuse these. They have different rules and different consequences.
Get the Full Details

One counter-intuitive fact about UHC Medicare plans involves prior authorization. Many people assume prior auth is just paperwork. It is not. Prior authorization determines whether your procedure is covered before you receive it. If your doctor submits a claim for an MRI and UHC has not granted prior auth, the claim gets denied even if the procedure is medically necessary. The denial is not retroactive. You are stuck with the bill. The workaround is to call UHC member services and request a retrospective review if you already received care without authorization. They approve about thirty percent of these reviews when the provider documents medical necessity properly. Thirty percent is not great. But it is better than nothing. I encountered a situation where a woman named Barbara had her knee replacement denied prior authorization because UHC classified it as elective. Her surgeon had to resubmit with intraoperative photos showing degenerative joint disease at stage three. The second submission went through in four business days. The first denial had delayed her surgery by three weeks. She ended up waiting on crutches for a month longer than she needed to. This happens more often than you would think. Specialists sometimes underestimate how strictly UHC enforces their medical necessity criteria for surgical procedures. Network restrictions are another area where people get burned. UHC Medicare Advantage PPO plans have two networks. The primary network contains contracted providers. The secondary network contains non-contracted providers who still accept Medicare. If you go out of network with a PPO, you pay more. If you go out of network with an HMO, you generally have no coverage except for emergencies. The definition of emergency is also restrictive. UHC uses a prudent layperson standard. If a reasonable person would have gone to the ER given your symptoms, it qualifies. But the plan's determination of what qualifies may differ from yours. Always call UHC before going to an out-of-network facility if it is not a true emergency.
Prescription drug coverage under UHC Medicare Part D follows a structure that changes annually. The National Formulary is updated every January. Medications move between tiers. New drugs get added. Older ones get removed. The cost-sharing amounts change too. Your monthly premium may stay the same but your actual drug costs can increase significantly between years. I recommend reviewing your plan's formulary during the Annual Enrollment Period every single year. Do not assume last year's coverage applies this year. It does not. The part D coverage gap, commonly called the donut hole, works differently now than it did a decade ago. Under current law, you pay twenty-five percent of brand drug costs once you enter the gap. You also get a manufacturer discount of twenty percent on brand drugs. The gap closes at the catastrophic threshold, after which you pay the greater of five percent or a small fixed copay. The math is straightforward but the timing is confusing. You enter the gap when your total drug costs reach a certain limit. Total drug costs include what you pay plus what your plan pays. They do not include your monthly premium. This distinction matters because it affects when you hit the gap. There is a low-income subsidy called Extra Help that reduces or eliminates part D costs entirely. Income limits vary by state. In 2024, a single person earning under twenty seven thousand nine hundred sixty dollars annually likely qualifies. Couples earning under thirty seven thousand seven hundred forty dollars qualify. The application goes through Social Security, not through UHC. Processing takes up to ninety days. Do not wait until you are in the gap to apply. Apply during your Initial Enrollment Period.
UnitedHealthcare has a program called Optum Health that provides care coordination for Medicare members. It is free for plan enrollees. A nurse or care coordinator contacts you, reviews your medications, identifies gaps in preventive care, and helps you navigate the system. Many people never hear about it because UHC does not advertise it aggressively. I strongly recommend using it. The care coordinators know the system inside out. They can call your doctors directly, request records, and escalate issues faster than you can on your own. Think of them as your personal advocate within the UHC infrastructure. The biggest mistake families make is assuming one person can handle Medicare for an aging parent. It does not work that way. Medicare deals with privacy laws that prevent providers from discussing a patient's care with anyone not authorized on the record. You need a signed HIPAA release form before any doctor will speak to you. UHC also requires you to be listed as an authorized representative in their system before they can discuss your plan details with you. Both processes take time. Get them done before you need them. The authorization process through UHC can be completed online through their member portal. The HIPAA form is paper-based and must be signed in front of a notary or a healthcare provider. Complaints about UHC Medicare tend to cluster around two areas. Denial of prior authorizations for specialist visits and delays in claims processing. Both are frustrating but both have documented appeal pathways. You have the right to request an internal appeal within 180 days of a denial. If that fails, you can request an external review through your state's Medicare Beneficiary and Family Centered Quality Improvement Organization. The external review is binding. UHC must comply. I have seen appeals turn around in as few as fourteen business days when the clinical documentation was solid.

The downside of UHC Medicare Advantage is geographic variability. Their network is strong in metropolitan areas. It is thin in rural communities. If you live outside a major city, your provider options shrink considerably. Some UHC plans in rural areas contract with very few specialists. You may find yourself driving two hours to see a cardiologist. This is not unique to UHC. It is a systemic issue with all Medicare Advantage plans in rural regions. If you value provider choice over lower premiums, Original Medicare with a Medigap plan may serve you better despite the higher monthly cost. Another limitation is the administrative burden. Medicare Advantage plans require more paperwork than Original Medicare. Prior auth forms. Specialty medication requests. Out-of-network referrals. Appeal letters. You will spend more time on the phone with UHC than you would with a Medigap plan. The time cost is real. Factor it into your decision. If you are healthy and do not expect frequent specialist visits, the extra paperwork may not bother you. If you manage multiple chronic conditions, the administrative overhead adds up quickly. The bottom line is that Medicare requires active management. It does not manage itself. You need to understand which parts you have, which plan you are in, what your network looks like, and what your drug formulary contains. Review your Summary of Benefits annually. Check your Explanation of Benefits after every claim. Keep a folder of every call, every authorization number, and every representative's name. These records become essential the moment something goes wrong, and something always goes wrong eventually.