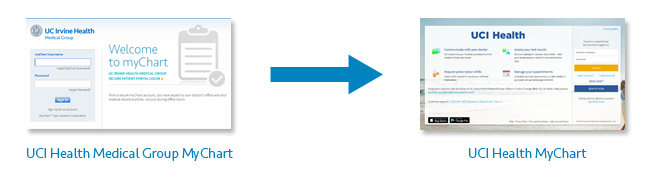
Getting Into the UC Health System Without Losing Your Mind
I spent three years as a clinical research coordinator at UC Irvine before moving into health IT consulting, which means I dealt with MyChart more than I care to admit. The UC system uses Epic's MyChart platform across all its campuses. It is functionally identical from San Francisco to San Diego with minor UI tweaks. The underlying architecture, authentication methods, and data routing are all the same Epic engine. That consistency is both the best and worst thing about it. The setup process is straightforward if you know what to expect. You get a link from your UC clinic, usually via email or a printed card at checkout. The link takes you to a registration page where you verify your identity using your date of birth and a portion of your phone number on file. After that, you create a password and set up two-factor authentication through either the Epic app or an SMS code. The whole process takes about twelve minutes if your information is clean. Half the people I helped get through this hit a snag on the second attempt because their insurance info didn't match what the system had. One thing nobody tells you upfront is that MyChart does not automatically sync all record types. Lab results typically appear within twenty-four hours of the lab signing them off. Medication lists update in real time as pharmacists process them. But imaging reports? Those can sit in a pending state for three to five business days after the radiologist dictation. I learned this the hard way when I was trying to pull a recent MRI report for a second opinion. It showed as "available" in my chart but the actual text wasn't there. I called the UC Davis radiology department directly and they told me the report was still in transcription review. Waiting forty-eight hours solved it. There is no notification for report status changes inside MyChart unless the ordering provider adds a note.
The messaging feature is where most people either find it invaluable or walk away completely frustrated. You can send messages to your care team through the portal and they respond within a couple of business days on a good day. I once sent a medication question to my endocrinologist at UCI Health and got a reply in six hours. Two weeks later I sent a similar question to a specialist at UCSF and waited eleven days before a nurse wrote back saying to call the office. Response times depend entirely on the practice group's staffing, not the platform itself. Epic does not distinguish between urgent and non-urgent messages in a way that actually prioritizes them. The system flags them as "new" but there is no triage layer built in. If you need something answered quickly, do not rely on the message center. Call the office. Use the portal for routine refill requests and non-urgent questions. That distinction will save you hours over a year. The prescription renewal flow works like this: you navigate to the medications tab, click on the active script, and select "request refill." The request routes to the pharmacy on file and then to the prescriber's office for approval. Most routine refills go through within one to two business days. The bottleneck is usually the medical assistant reviewing the request rather than the doctor. If your refill is taking longer than three days, call the office. Do not submit multiple requests through the portal. It creates duplicate tickets and pushes your actual request further back in the queue.
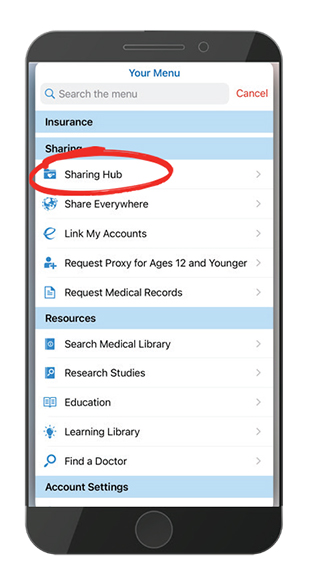
Scheduling appointments through MyChart is another area with a hidden layer most users never see. When you book through the portal, you are actually accessing the practice's scheduling module within Epic. Some UC clinics have opened their scheduling fully to patients. Others only allow appointment requests that a staff member confirms. At UCI Health, primary care lets you pick a time slot directly. Specialties like dermatology and cardiology typically show "request appointment" buttons instead. The difference comes down to whether the practice has enabled self-scheduling in their Epic configuration. There is no indicator in the interface that tells you which mode your clinic is using. You find out by clicking through and seeing what happens. The billing and insurance section is where the system shows its most glaring weaknesses. You can view claims and explanation of benefits documents, but the data is not always complete. I have seen claims where the CPT codes were correct but the adjustment amounts did not match the negotiated rates. Denial reasons sometimes appear as generic codes instead of plain language. When this happens, you need to pull the actual Explanation of Benefits document from your insurer's website, not the one in MyChart. The portal's financial data is a summary layer that can lag behind your insurance company's records by several billing cycles. One workaround that actually works: export your health summary as a PDF before every major visit. MyChart has a "Share Record" feature under the settings menu that generates a comprehensive PDF including your problem list, current medications, allergies, and recent lab trends. I used this document consistently during my research years when transferring patients betweenUC sites. It cut down on duplicate testing and prevented medication errors that would have happened from relying solely on verbal handoffs. The export takes about twenty seconds to generate. Print two copies and bring them to the appointment.
Get the Full Details
There are also practical limitations worth noting. The mobile app version of MyChart is documents reviewing lab The accessibility options in MyChart are better than most patient portals I have worked with. You can adjust font sizes, enable high contrast mode, and use screen reader compatibility. For users with vision impairments or motor disabilities, these settings make a real difference. However, the screen reader support is not perfect. Some of the newer UI components in Epic do not have proper ARIA labels, which means a blind user navigating with JAWS or NVDA will hit dead ends at certain pages. The lab results page is particularly problematic. It loads dynamically and screen readers often cannot parse the updated content without a full page refresh. If you are managing records for someone else, like an elderly parent or a dependent, you can set up proxy access through the portal. The process requires both parties to complete an authorization form, which can be filled out digitally or printed and signed. Proxy access gives you the ability to message providers on behalf of the patient, view their records, and manage their appointments. The catch is that some UC clinics restrict proxy permissions at the practice level. A parent may not be able to access their adult child's records even with proper authorization if the clinic has not enabled that level of proxy access in their Epic instance. If you run into this, the only solution is to request that the clinic adjust their proxy settings. That usually requires a phone call to the clinic's health information management department.
Data portability is another area where MyChart falls short of what patients might expect. You can request a copy of your medical records through the portal, but the format and delivery method depend on the UC campus. Some campuses provide documents in PDF via secure email within five business days. Others require a written request submitted by mail and will only deliver paper copies. The fastest route is calling the medical records department at the specific UC facility where you received care and asking them directly about their process. The answer will vary from campus to campus even though they all use the same Epic system. One edge case that caught me off guard: if you received care at multiple UC hospitals during a single treatment course, your records may be fragmented across different Epic instances. UCI Health, UCLAE, and UCSF each run separate Epic environments that are not fully integrated for patient-facing data. A lab drawn at UCI Medical Center may not appear in your UCLAE MyChart portal. I discovered this when I was tracking clinical trial enrollment criteria and needed a complete medication history across two UC sites. The data was split between two separate MyChart accounts. The workaround was to request a cross-campus record transfer through UC's centralized health information exchange, which took about ten business days and required filling out a release of information form for each campus separately. The vaccination record feature is one of the more useful tools and it actually works reliably. If you receive shots at any UC student health center or primary care clinic, they should appear in your immunization section within forty-eight hours. You can export this section specifically for school or workplace requirements. Some UC schools accept the MyChart immunization export as proof of compliance. Others still require a stamped paper record from the clinic. Check with the institution before relying on the digital export.
Bottom Line on What Actually Works Here
MyChart at UC is a solid patient portal that does the core functions adequately. It will not replace having an advocate or making phone calls when things get complicated. The messaging response times, the fragmented data across campuses, the unreliable mobile uploads, and the inconsistent proxy settings are real limitations. But if you learn the workarounds early, it saves significant time compared to the alternative of managing everything through phone tag and fax machines. Start with the health summary export before your next appointment. Use the portal for non-urgent requests only. And do not assume data you see is complete without verifying it against your insurance statements. The system is good enough that you will want to use it regularly. It is also flawed enough that you need to know exactly where it breaks before you rely on it for anything important.