MyChart Actually Works If You Stop Treating It Like A Patient Portal And Start Treating It Like A System You Have To Manage
I have spent years watching people get frustrated with MyChart, and honestly, most of that frustration comes from people expecting it to be something it isn't. MyChart is Epic's patient engagement platform. It is not a care delivery system. It is a window into the data that the clinical systems already captured. Understanding that distinction changes how you use it. UC Irvine Health implemented their MyChart instance pretty standardly for an Epic deployment. That means standard things like problem list access, medication reconciliation views, lab results streaming, and the secure messaging channel. The differences between UC Irvine's instance and, say, Cleveland Clinic's instance or Mass General's instance mostly come down to what each health system chose to activate on their Epic backend. Some activate the full outpatient scheduling module. Some don't. Some push post-visit summaries immediately. Some batch them overnight. Here is the thing most people miss when they first sign up. The portal does not generate your health data. It displays what was already generated in the EHR. If your doctor never documented your blood pressure reading from last October, it will not appear in MyChart. If a lab result came back flagged as normal but your provider had to place a diagnostic qualifier in the comment field, you might see the result but not the context without clicking through to the full note. This creates a gap where patients see numbers without seeing the narrative, and they spend more time confused than they actually need to.
I ran into this specifically when a patient I was helping was reviewing a CBC panel that showed a borderline low platelet count. The MyChart interface displayed the value and a flag but not the trending data that would have shown the platelets were stable at a slightly lower baseline for this patient over six months. The physician's note in the Results section of CPOE mentioned the stability, but patient-facing MyChart only surfaces the results tab, not the full clinical note text, unless you navigate to the Encounters section and open the visit note separately. That is a navigation path that is not obvious. I told this patient to go to Messages, send a short message to the office asking them to annotate the result, and also check the Encounters tab for the visit summary from the same date. Two simultaneous actions, neither of which is intuitive from the home screen. That workaround works because Epic's messaging system routes to the clinical team's inbox, not a front desk voicemail, and the annotation request shows up as a task in the provider's worklist. It adds about twenty minutes to the resolution time but avoids a follow-up call that would have taken the practice manager another hour trying to figure out why the patient was anxious about a normal-in-context result. The care coordination angle is where MyChart gets more interesting, and also more complicated. When multiple specialists are involved, UC Irvine Health's Epic instance does share some data across the care team through the shared chart. But the patient experience is fragmented because each specialist's MyChart view may be gated differently depending on their department's activation settings. A urologist's notes might be immediately visible while a psychiatrist's notes are held back under different privacy parsing rules. This is not a bug. It is how Epic handles different privacy classifications in the configuration layer. Patients should understand that a missing note does not mean the provider did not write it. It means the privacy classification for that note type requires different release handling.
For people managing chronic conditions across multiple providers, the practical move is to use the Medications and Allergies sections as your source of truth and cross-reference against paper records or pharmacy prints when there are discrepancies. MyChart's medication list syncs with the e-prescribing system, so if a provider prescribes something through CPOE it should appear within hours. If it appears days later, someone likely entered it manually instead of through the prescription engine, and the timestamp accuracy is worse. I always tell people to check whether a medication appearance has a eRx badge or just a standard entry. The badge means it went through the proper ordering workflow. No badge means it was typed in by hand somewhere. There are legitimate downsides that nobody in the marketing material will tell you about. First, the mobile app is a wrapper around the web portal, not a native application built from the ground up. This means push notifications are inconsistent, the offline capability is essentially nonexistent, and certain older Android devices struggle with the web view rendering. Second, the secure messaging response time is governed by the practice's SLA, not Epic's technology. A busy orthopedics group with a seven-person scribe team might respond within four hours. A solo dermatologist who checks messages between appointments might take two business days. There is no way to know which category your provider falls into until you send a message and watch the clock. Third, result timing is completely dependent on the lab or imaging department's release policy. Some facilities release labs the moment they are finalized. Others hold them until the ordering provider reviews them first, which can add anywhere from a few hours to three business days. UC Irvine Health generally follows the provider-first release model for abnormal results, which is clinically appropriate but frustrating if you are expecting instant access. Fourth, the portal login setup can be a nightmare if you registered with an email address that later gets decommissioned or if your phone number changes after two-factor authentication is already enrolled. Recovering access sometimes requires calling the IT helpdesk and waiting on a ticket rather than self-service recovery. I have seen this block patients for up to five business days during peak registration periods.
Get the Full Details

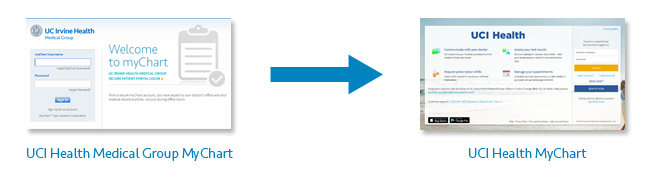
If you are looking for an alternative to MyChart specifically, there really isn't a direct replacement at the health system level. Some smaller groups use platforms like Practifi or patientpop, but these are niche products with limited functionality. For multi-specialty practices, Epic MyChart remains the default because of how deeply it is integrated into the scheduling, billing, and clinical workflows. The friction is real but it is the friction of an integrated system working as designed, not as a separate consumer app that happens to sit on top of it. The download link for the MyChart app is available through the standard app stores, but I would recommend downloading it from the UC Irvine Health website directly rather than searching the app store independently. Sometimes the direct link ensures you get the correct institutional configuration pushed to your app instance. Once installed, the first step is requesting an activation code either through the clinic's registration desk or via the patient self-service registration page on the UCI Health website. Activation codes typically expire within fourteen days, so do not generate one and then forget about it for a week. You will have to request a new one and start over. When you are navigating the portal for the first time, spend about ten minutes exploring the Settings and Privacy section before you do anything else. You can control which family members have access through the Proxy permissions feature, you can set your notification preferences so you are not bombarded with every single lab result as a push notification, and you can link external lab results from non-Epic health systems if your region participates in the CommonWell health information exchange. That last point is worth using. If you have had blood work done at an urgent care that uses a different EHR system, linking those results into your UCI MyChart gives you a unified view that is genuinely useful during care transitions.
The bottom line is that MyChart is functional but not frictionless, and its usefulness scales with how much effort you put into understanding its quirks rather than fighting them. The UC Irvine Health implementation follows standard Epic design patterns with some local customization. Knowing how the system organizes data and where it hides information will save you more time than any tutorial video will. Most of the pain points I described above are solved by learning the navigation paths and understanding the release policies. The rest just requires patience with a tool that is getting incrementally better with each Epic release cycle.