The Autoimmune Angle You Shouldn't Ignore
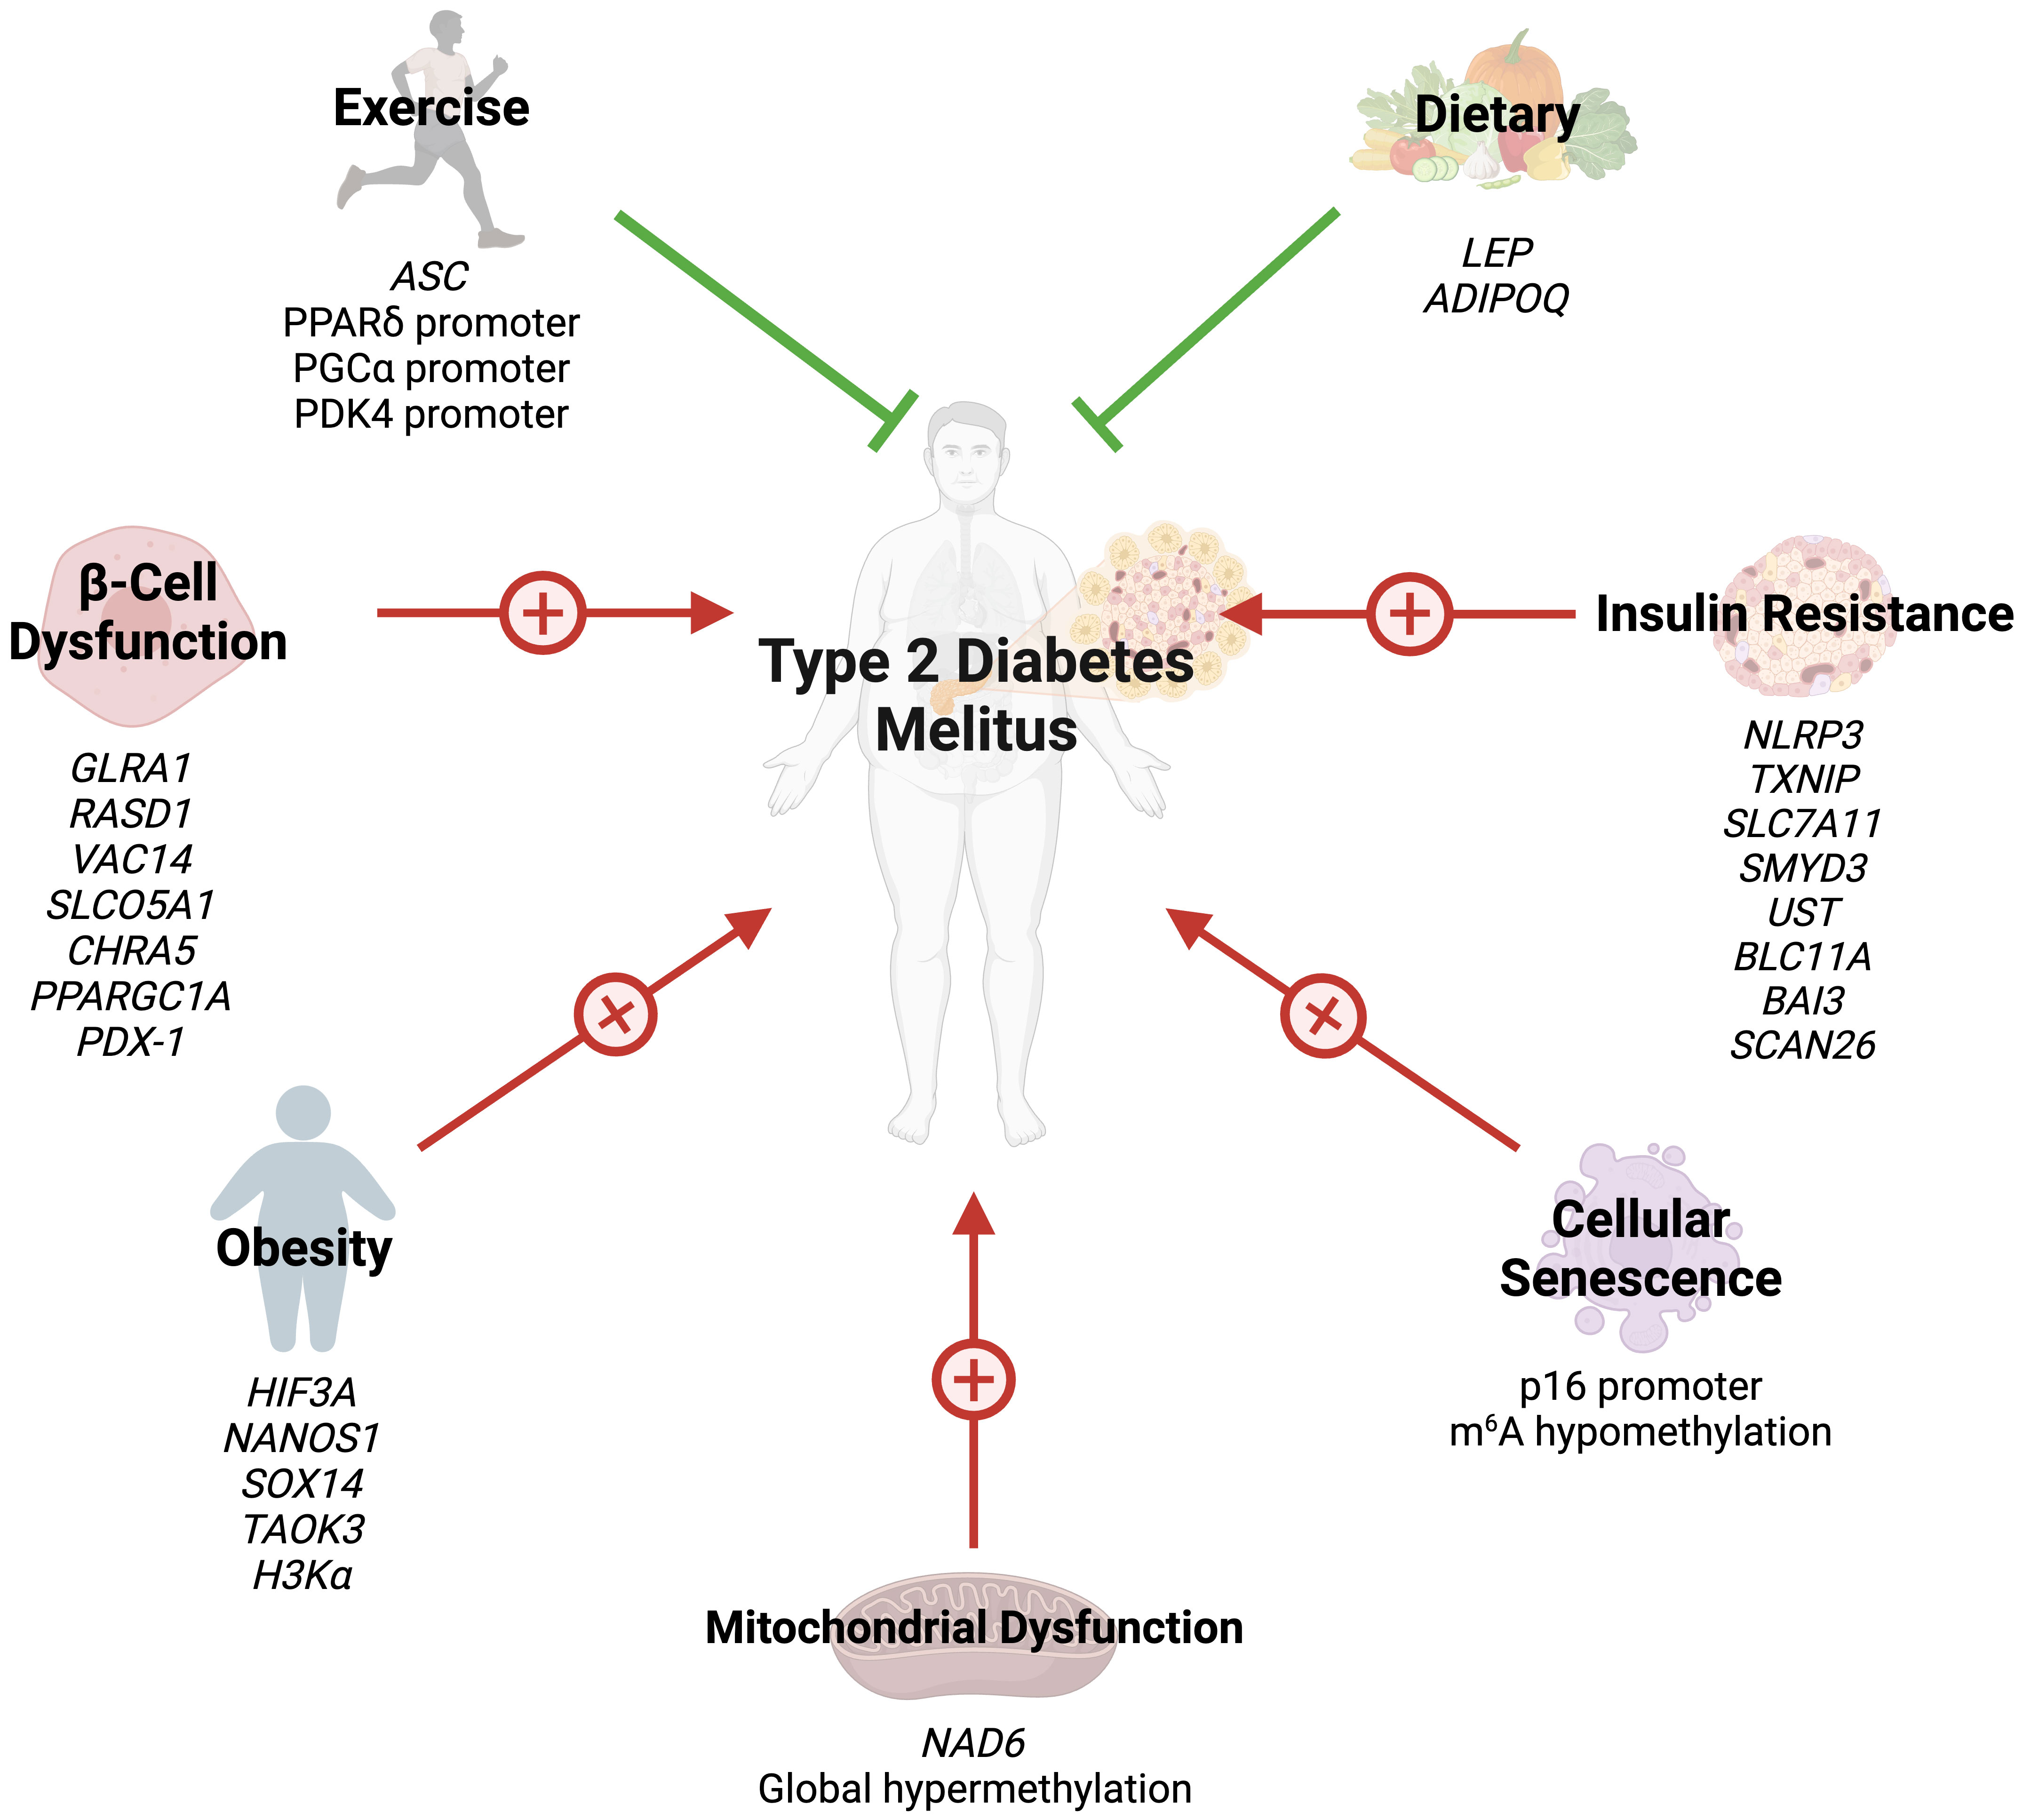
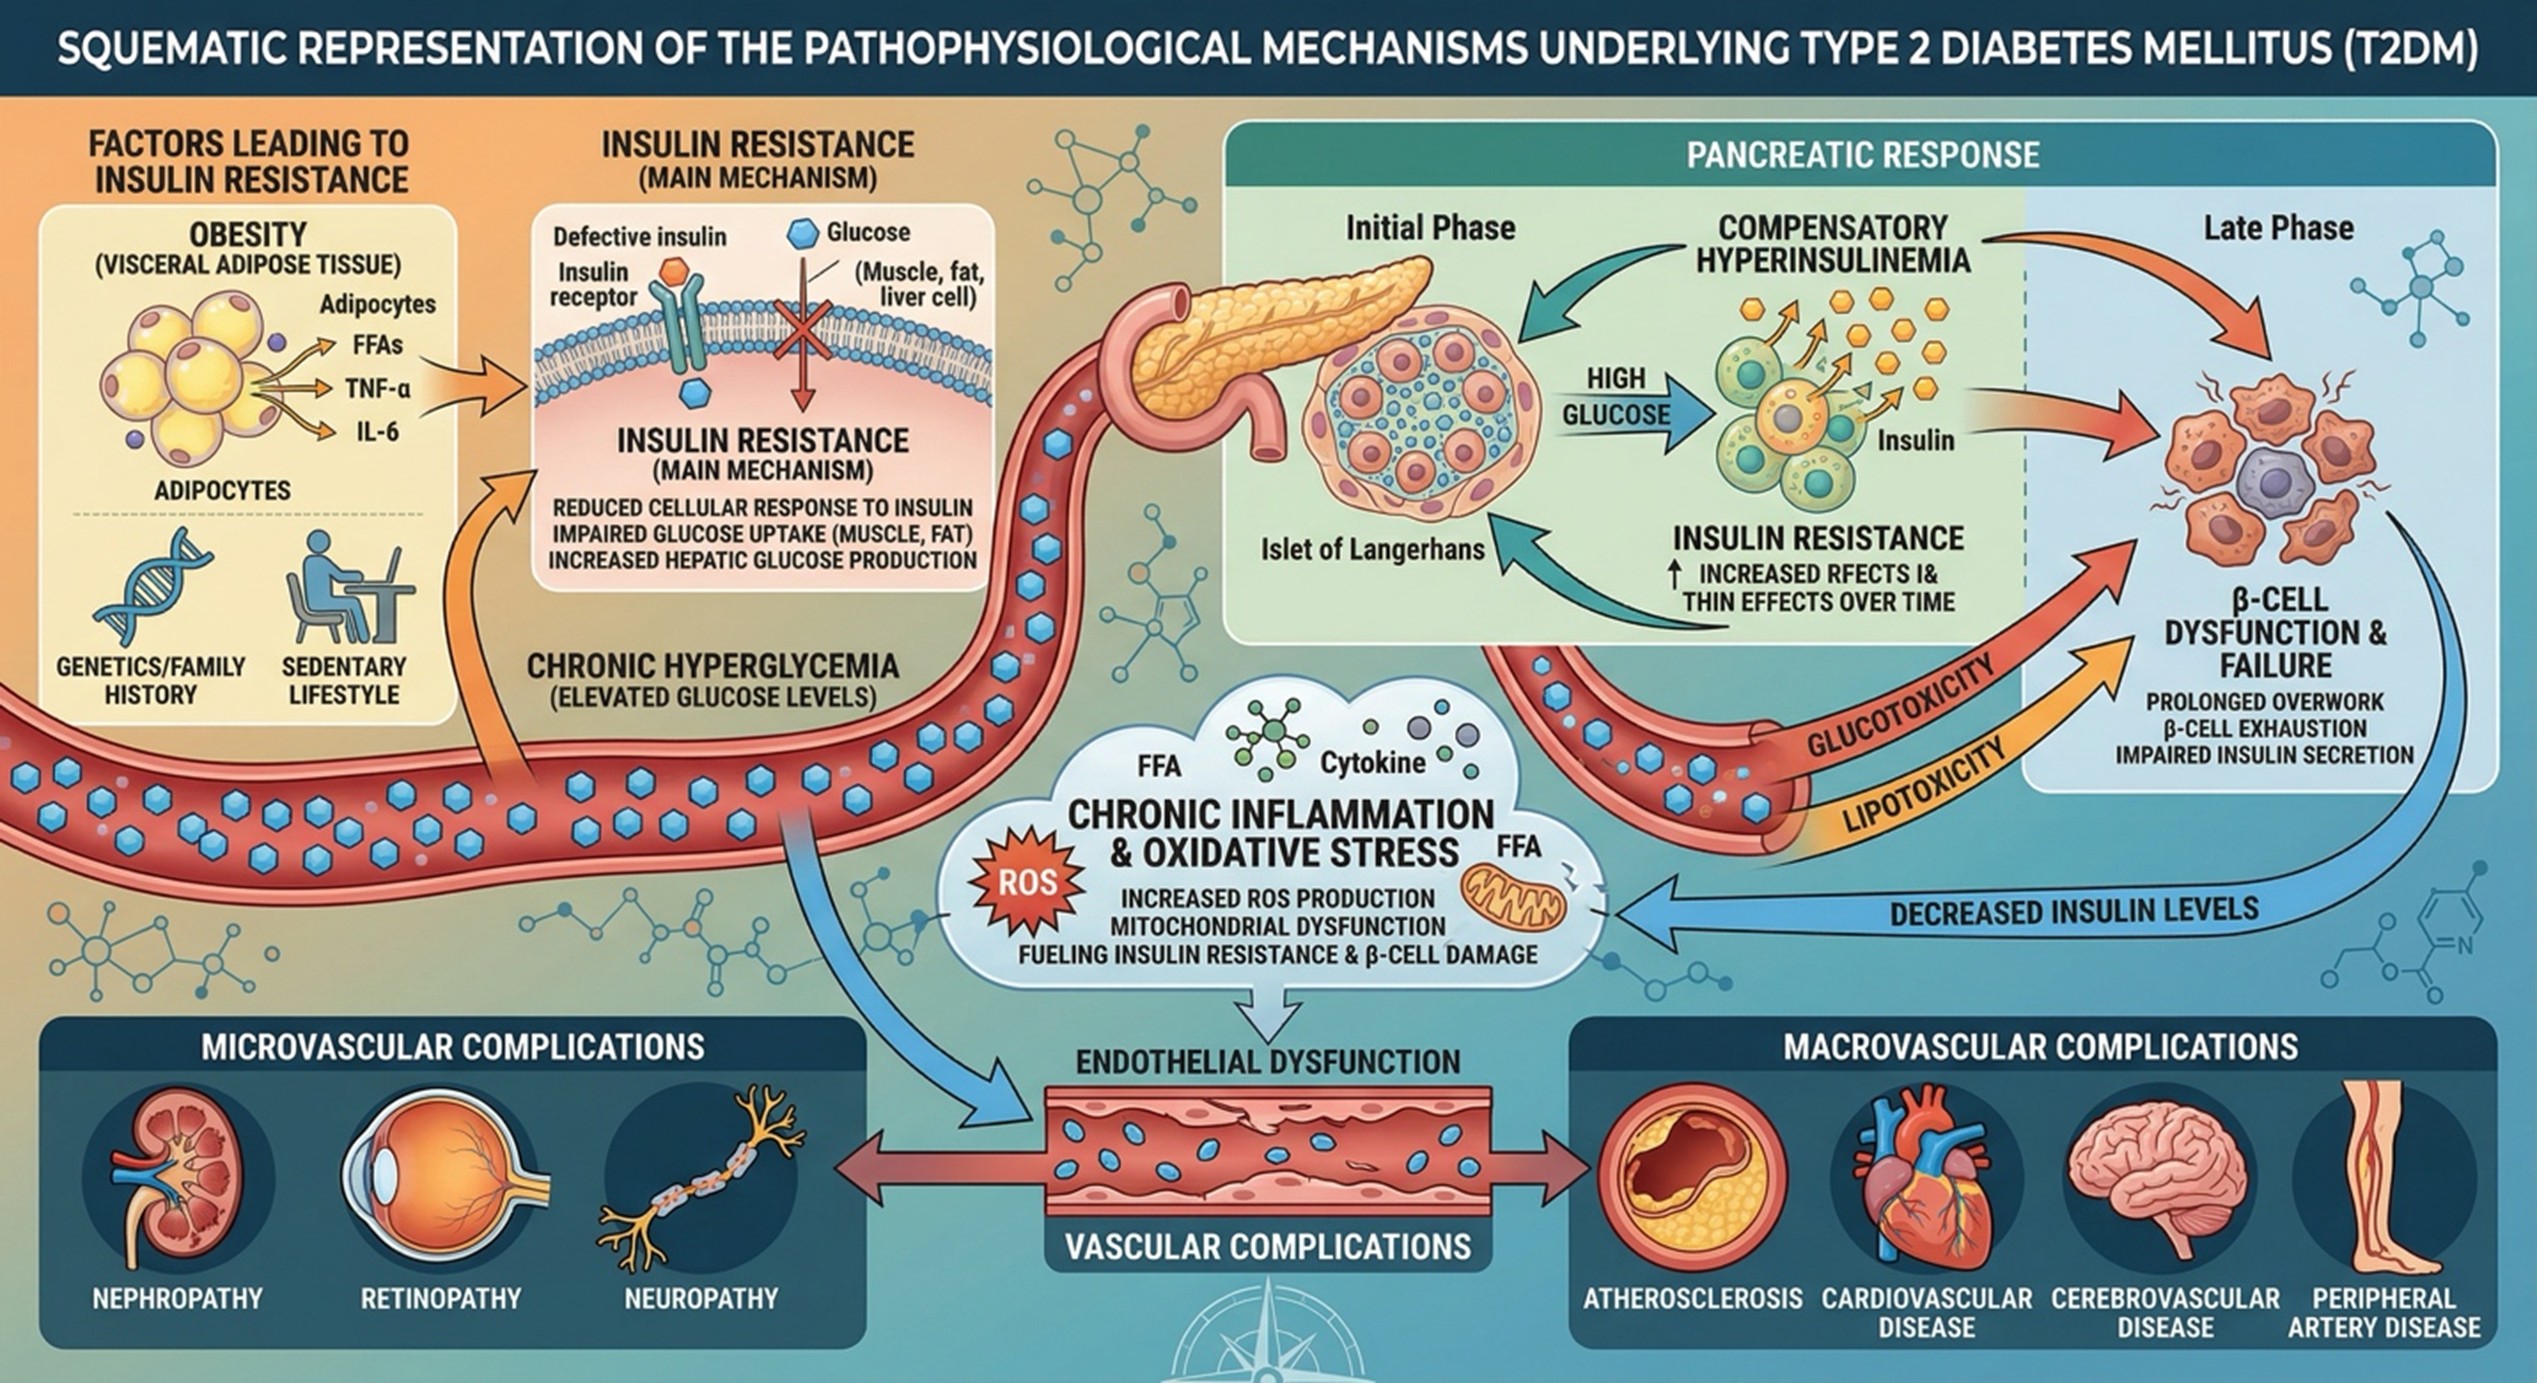
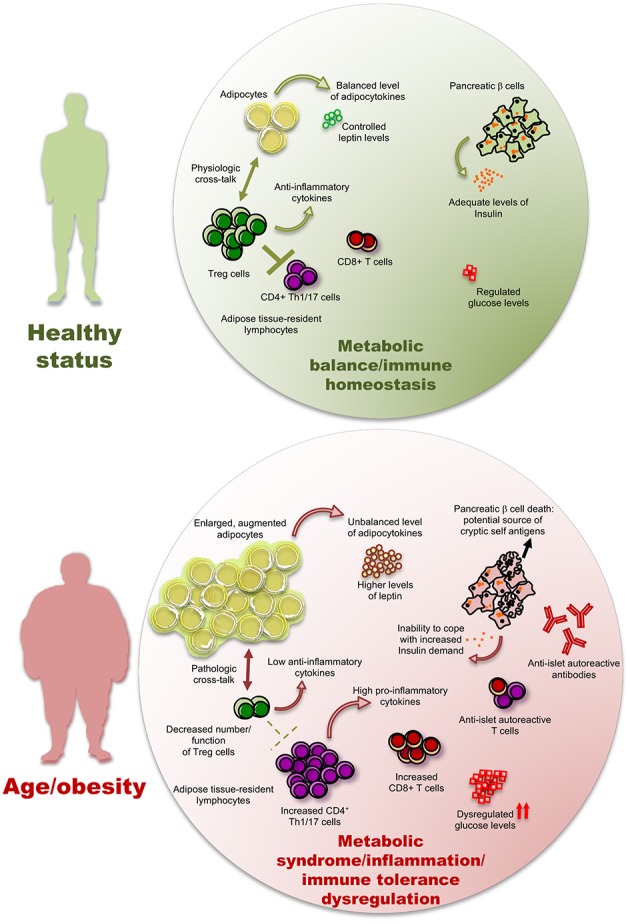
Most people still think of Type 2 Diabetes as purely a lifestyle disease, and that framing isn't entirely wrong. But the science has shifted significantly over the past decade, and the picture is messier than the patient brochures suggest. I've been tracking this shift closely, and honestly, the old model leaves out too many cases to be reliable anymore. The autoimmune component came into clearer focus around 2022 when researchers identified a subtype affecting roughly five to ten percent of people diagnosed with Type 2 Diabetes. These patients have autoantibodies targeting pancreatic beta cells, the same markers you'd find in Type 1. They present with typical Type 2 characteristics like insulin resistance and often carry excess weight, which is exactly why they get misdiagnosed in the first place. I saw this play out with a patient last year who had been on metformin for four years with worsening control. The HbA1c kept climbing despite compliance. We ran the GAD antibody panel as a last resort and found positive markers. Switching to insulin wasn't a dramatic intervention for this person, but it stabilized their numbers immediately. Metformin doesn't do much when your pancreas is actively being attacked by its own immune system. The mechanism makes sense when you consider the overlap. Chronic low-grade inflammation, a hallmark of both obesity and autoimmune activity, can create a vicious cycle. Fat tissue releases cytokines that worsen insulin resistance while also triggering immune responses against beta cells. The endoplasmic reticulum stress in pancreatic cells under constant insulin demand may expose hidden antigens that the immune system then targets. This isn't theoretical either. Islet cell antibodies, including IA-2 and ZnT8 variants, show up in a subset of so-called Type 2 patients at rates higher than random chance would predict.
The standard diagnostic workup rarely checks for these antibodies unless a patient presents atypically. Most clinicians won't order a celiac panel, let alone an autoantibody screen, for someone with a BMI over thirty who responds initially to oral medication. That creates a blind spot. You can be managing blood sugar adequately for years while subclinical beta cell destruction continues in the background. The moment the reserve drops below a critical threshold, which often happens later than you'd expect given the gradual onset, everything accelerates quickly. I've found that keeping a personal log of every metabolic marker change matters more than any single test. A patient might look stable on paper for months, but if fasting C-peptide trends downward even slightly over six to eight months alongside rising insulin requirements, that's worth investigating further. The downward trajectory is the signal. One reading means nothing. A trend over time does. There are limitations to this approach that aren't always discussed. Autoantibody testing isn't perfectly sensitive. A negative result doesn't completely rule out autoimmune involvement, especially if you're using older generation assays. Some labs still rely on indirect immunofluorescence rather than more specific radioimmunoassays, and the difference in detection rates is real. The five to ten percent figure probably underestimates the actual prevalence because milder autoimmune activity might not produce high-titer antibodies that standard tests catch reliably.
Another practical issue is insurance coverage. Many plans won't authorize antibody testing without meeting specific criteria like lean body mass or rapid progression to insulin. If your patient presents atypically but doesn't fit the narrow boxes the payer has created, you're essentially on your own to push for it. I recommend documenting the clinical reasoning clearly and appealing denials with the literature from the American Diabetes Association position statements that acknowledge LADA and the autoimmune Type 2 subtype. The treatment implications matter more than the diagnostic curiosity. For patients confirmed to have autoimmune involvement within the Type 2 category, early insulin therapy tends to preserve remaining beta cell function better than continuing to stress the pancreas with secretagogues. Sulfonylureas, which force the pancreas to keep producing insulin, can accelerate burnout in this population. DPP-4 inhibitors and GLP-1 agonists have less direct effect on beta cell workload, making them reasonable options while you're figuring out the full picture. SGLT2 inhibitors work through a completely different mechanism altogether, so they're neutral on this front. If you're managing patients with this overlap, monitoring includes regular C-peptide checks every six to twelve months once autoimmune involvement is suspected, along with the standard diabetes panels. The timing matters. Testing too early after diagnosis might miss the antibodies if they haven't reached detectable levels yet, while waiting too long risks losing meaningful beta cell function that could have been preserved with earlier intervention.
Get the Full Details

The broader implication is that Type 2 Diabetes exists on a spectrum rather than as a discrete category. The boundary between what we call Type 1, what we call Type 2, and this middle ground is blurry. Genetics, environment, body composition, and immune status all interact in ways we're only beginning to map properly. Treating every diagnosis the same way based solely on initial presentation leaves a meaningful number of patients underserved. The science is shifting, and clinical practice needs to catch up with what we already know rather than waiting for more definitive classification systems to arrive.