Understanding Turner Syndrome: Visual Signs, Diagnosis, and Long-Term Management
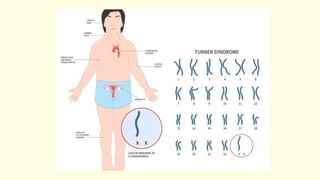
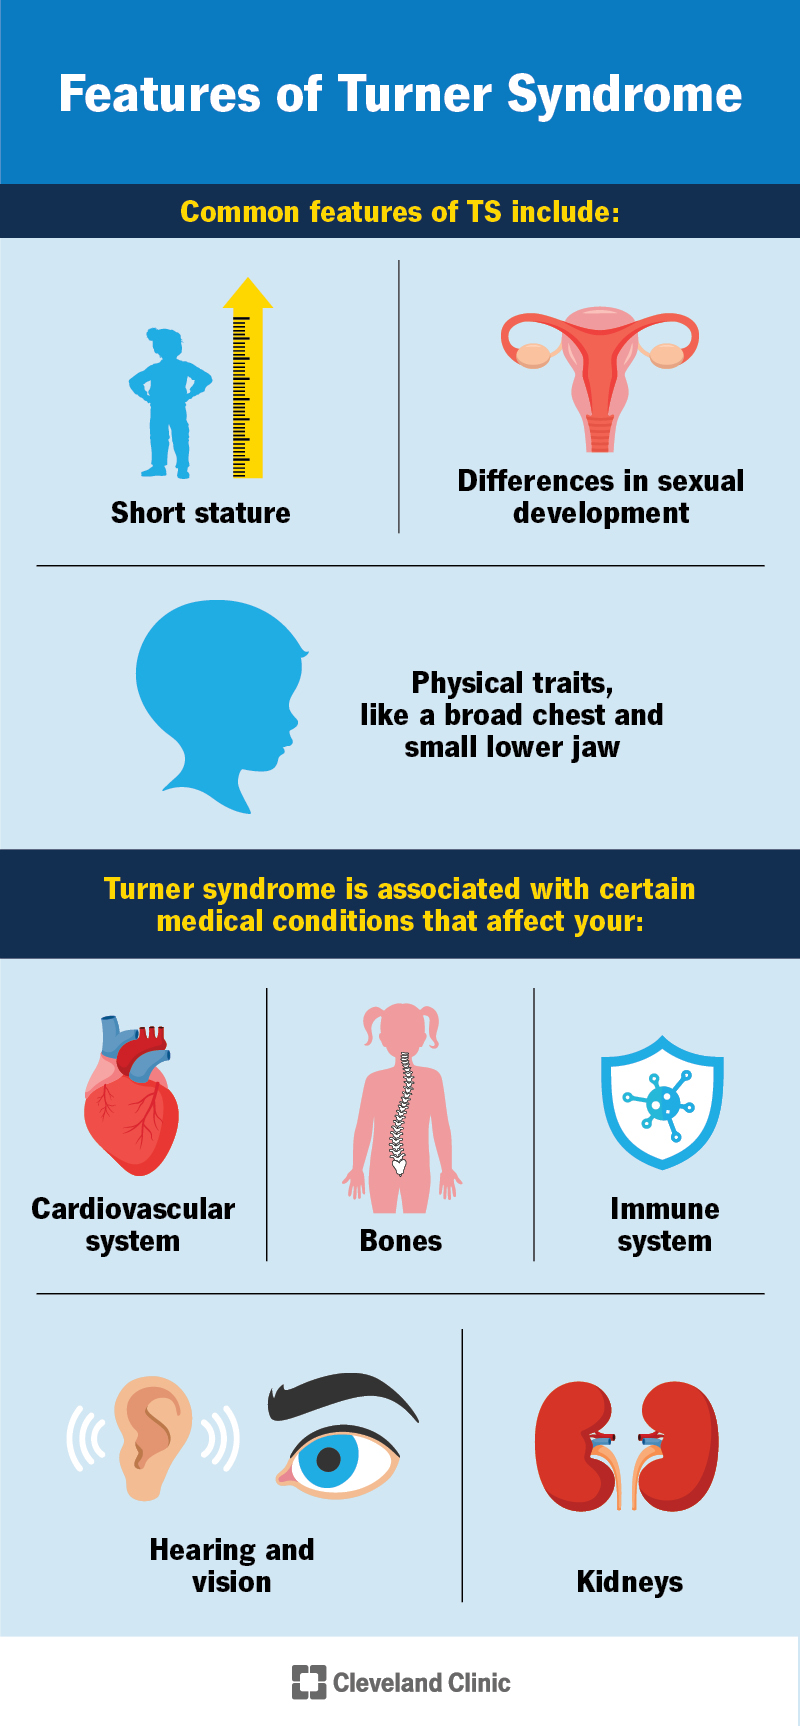
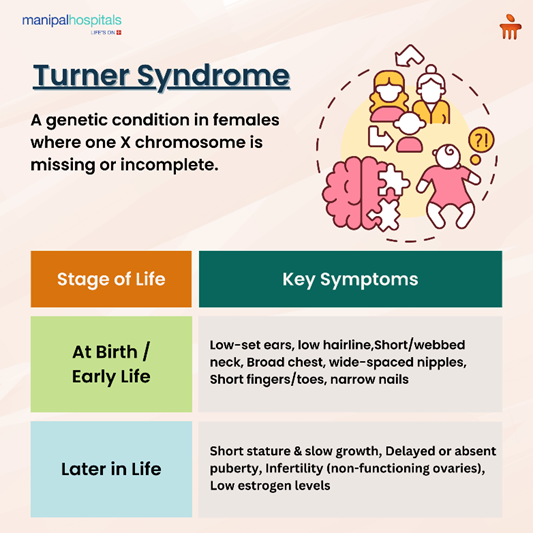
Turner syndrome affects roughly 1 in 2,500 live female births, and most people encountering it for the first time are struck by how subtle or overt the physical features can be depending on who you're looking at. Some individuals present with clearly noticeable signs, while others carry only one or two minor traits that wouldn't register without a clinical eye. That variability is the first thing you learn when you start dealing with this condition regularly. The visual features associated with Turner syndrome are what typically prompt the initial suspicion. A webbed neck, a broad chest with widely spaced nipples, short stature, and swollen hands or feet in infancy are among the classic markers clinicians look for. But here's the thing most patient handouts don't emphasize enough: not every person with Turner syndrome has all of these features, and not everyone with some of these features has Turner syndrome. I once had a case where a teenager was referred for possible Turner syndrome purely because she was short, had a low hairline, and mild cubitus valgus. Her karyotype came back 46,XX with a balanced translocation unrelated to Turner. The physical features overlapped with other conditions, and the referral was based on pattern recognition rather than a specific indicator. That's why visual assessment alone is never enough. Photographic documentation does play a role in clinical practice, though not in the way you might think. It's less about creating a visual checklist and more about tracking progression or documenting atypical presentations over time. A pediatric endocrinologist might photograph a child's hand to monitor lymphedema resolution, or record facial features at different ages to note changes. Those photos become part of the clinical record, not a public reference library. There isn't really a standardized set of "Turner syndrome photos" that clinicians use as a diagnostic tool. The diagnosis comes from genetic testing, not from matching a face to a picture.
How Diagnosis Actually Works
Karyotyping is the gold standard. You take a blood sample, culture the cells, arrest them in metaphase, stain them, and look at the chromosomes under a microscope. The classic finding is 45,X — one X chromosome instead of two. But mosaicism complicates everything. A significant portion of Turner syndrome cases are mosaic, meaning some cells have 45,X and others have a normal 46,XX complement. When I was working in a clinical genetics lab, we saw cases where the abnormal cell line was only present in blood at low levels but more prominent in skin fibroblasts. A standard peripheral blood karyotype can miss mosaic Turner syndrome, especially if the 45,X line is under 10 percent. The workaround was to run FISH analysis on interphase nuclei as a screening tool before committing to full karyotyping, which caught cases that would otherwise have slid through. Prenatal diagnosis adds another layer. Cell-free fetal DNA screening can sometimes pick up sex chromosome abnormalities, but it's not definitive. If a non-invasive prenatal test flags a potential X chromosome issue, the next step is always diagnostic testing — either chorionic villus sampling or amniocentesis. I've seen situations where a screen-positive result turned out to be confined placental mosaicism, meaning the pregnancy was actually unaffected. That's a stressful period for families, and it's worth noting that visual features of Turner syndrome aren't reliably detectable on routine mid-trimester ultrasounds. Some soft markers exist — increased nuchal translucency, cystic hygroma, cardiac defects — but none of them are specific to Turner syndrome.
Features Beyond the Physical
Here's where most general overviews fall short. Turner syndrome isn't just a collection of visible traits. It's a multisystem condition. Congenital heart defects occur in about 50 percent of cases, most commonly bicuspid aortic valve and coarctation of the aorta. Renal anomalies like horseshoe kidney are found in roughly 30 to 40 percent. Autoimmune thyroiditis and celiac disease are more prevalent. Hearing loss, often conductive in origin due to recurrent otitis media, affects a large proportion of individuals. Bone health is another major concern — osteoporosis risk is elevated even in young adults with Turner syndrome, largely due to estrogen deficiency and possibly inherent bone density issues beyond just hormonal factors. The cognitive profile is also frequently misunderstood. Intelligence is generally in the normal range, but there's a documented increase in specific learning disabilities, particularly in visuospatial reasoning and mathematics. Social cognition can be affected too. Parents and educators should know that a child with Turner syndrome might struggle with certain types of problem-solving without any overall intellectual impairment. It's easy to miss that nuance, and easy to either underestimate or overestimate what the child is capable of.
Get the Full Details

Management and Treatment
Growth hormone therapy is standard. Starting treatment in early childhood can add several centimeters to adult height, though results vary depending on when therapy begins and the individual's response. Most patients also require estrogen replacement therapy, typically initiated around the age of 11 to 12 to induce puberty. The timing matters because delaying estrogen can affect bone mineralization and psychological well-being, while starting too early can compromise final height by advancing bone age too quickly. The balance is tricky and requires regular monitoring of bone age X-rays alongside growth velocity. Cardiac screening should be lifelong. Even if a congenital heart defect is repaired in childhood, adults with Turner syndrome are at risk for aortic root dilation and dissection. Annual echocardiography and blood pressure monitoring are recommended. I worked with a patient in her late twenties who presented with a sudden severe headache and was found to have an aortic dissection. She'd had a bicuspid aortic valve diagnosed at age eight and had been followed regularly, but the aortic root measurement had been subtly increasing over the years and hadn't crossed the threshold that would have triggered surgical intervention. This is exactly why consistent follow-up matters — the guidelines give thresholds, but each patient's trajectory is individual. Fertility is another critical area. Most individuals with Turner syndrome are infertile due to accelerated ovarian follicle depletion, which often begins in utero. Spontaneous puberty and menstruation do occur in a small minority, particularly those with mosaic karyotypes, and a very small number have gone on to carry pregnancies, usually with significant maternal and fetal risks. For most, egg donation remains the only option for biological parenthood. Reproductive counseling should happen early, ideally before any gonadotropin treatment or other interventions that might further impact ovarian function.
What the Literature Gets Wrong
One persistent issue is the tendency to present Turner syndrome as a straightforward diagnosis with a predictable feature set. In practice, the phenotypic expression is remarkably heterogeneous. Two siblings with the same 45,X karyotype can look very different. The same gene dosage effects play out differently depending onModifier genes, environmental factors, and random developmental variation. Another problem is the chronic care gap. Many patients transition from pediatric to adult care and fall through the cracks. The multidisciplinary team that managed them in childhood — endocrinology, cardiology, audiology, nephrology — doesn't automatically transfer. Adults with Turner syndrome often navigate their care alone until something serious happens. That's a systemic failure, not a medical one, but it's the kind of thing that shows up repeatedly in clinical practice. If you're looking at this from the perspective of someone newly diagnosed or supporting someone who is, the most practical advice is straightforward: get a complete baseline workup, establish care with a clinician familiar with Turner syndrome, and commit to long-term follow-up. The visual features are interesting but secondary. The real work is in the cardiac imaging, bone density scans, thyroid panels, and hearing tests that happen year after year. There's no shortcut around that, and no amount of looking at pictures changes the management plan.