The Reality Of Treating Traumatic Injuries
Traumatology isn't what you see in movies. There's no dramatic music when you're reducing a compound fracture in a resource-limited setting. You just work. The science of healing after severe trauma involves understanding how the body responds to catastrophic stress and how to support that response without making things worse. When someone sustains major trauma, their body enters a hypermetabolic state that can last weeks. Catecholamine surge, cortisol elevation, and systemic inflammation create a perfect storm that your job is to manage, not reverse directly. You support what the body is already trying to do. The initial phase requires damage control surgery within the golden hour for hemorrhage control. This means packing, temporary vascular shunts, and permissive hypotension rather than aggressive fluid resuscitation. Getting MAP to 60-70 mmHg instead of normalizing blood pressure preserves clot stability while maintaining organ perfusion. I learned this the hard way dealing with a penetrating abdominal injury where aggressive crystalloid administration caused the coagulopathy that nearly killed the patient. Switching to balanced blood product transfusion at 1:1:1 ratios changed the trajectory entirely.
Understanding The Inflammatory Cascade
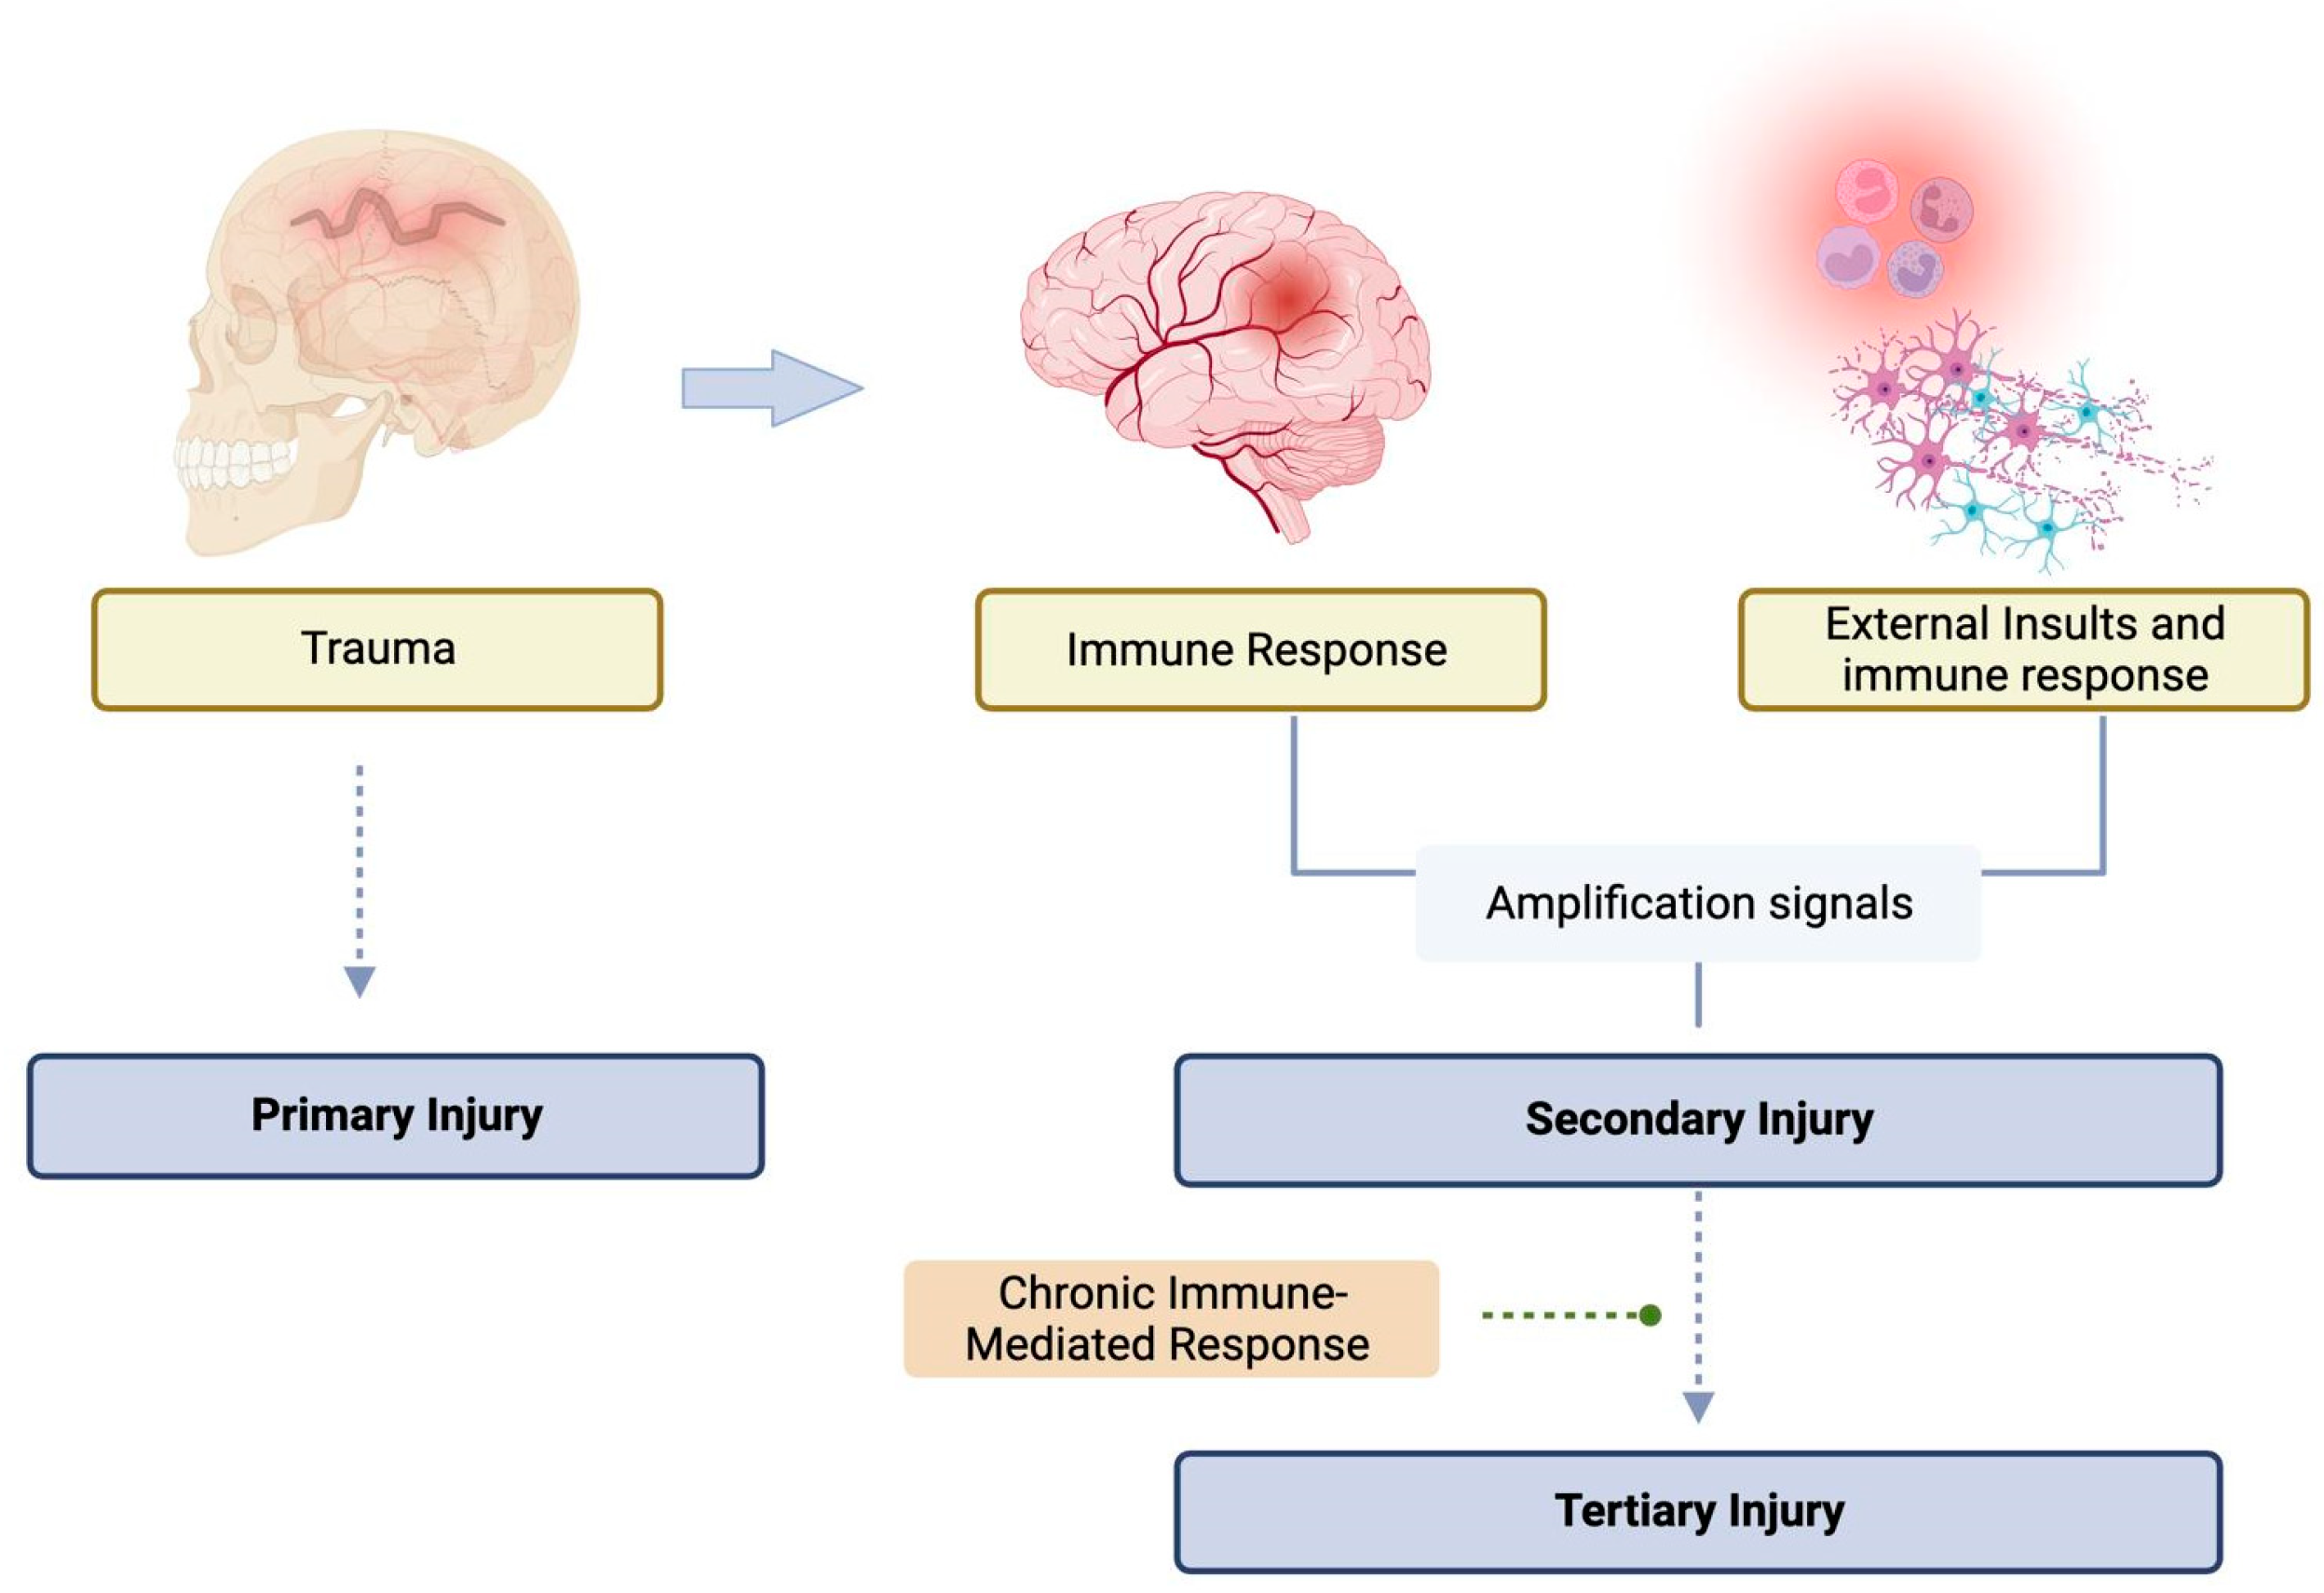
After the immediate life-threatening issues are controlled, the inflammatory cascade becomes the primary concern. Without intervention, this can progress to multiple organ dysfunction syndrome. The key mediators involve TNF-alpha, IL-1, IL-6, and the complement system. These aren't abstract concepts, they're measurable markers that dictate treatment decisions. Early enteral nutrition within 24-48 hours of injury significantly reduces bacterial translocation from the gut. This is one of those interventions that seems simple but gets overlooked constantly. I've seen ICU stays extend by an average of 8 days in patients who missed that window because feeding tubes weren't placed promptly enough. The timing of wound closure matters enormously. Delayed primary closure for contaminated wounds reduces infection rates from approximately 15-20% down to under 5%. Opening the wound on day 3 or 4 for secondary intention isn't failure, it's protocol. Surgeons who insist on closing everything immediately often regret it within 72 hours.
Practical Approaches To Healing Optimization
Glycemic control in the range of 140-180 mg/dL improves outcomes significantly compared to tight control strategies. Hypoglycemia in trauma patients carries worse mortality than mild hyperglycemia. This counter-intuitive finding caught many clinicians off guard when the NICE-SUGAR study results came out, but the data held up across multiple centers. Deep vein thrombosis prophylaxis timing depends on injury pattern and imaging stability. For solid organ injuries, I typically hold pharmacologic prophylaxis for 24-72 hours post-injury with sequential compression devices as bridge therapy. After that window, LMWH or unfractionated heparin becomes appropriate if repeat imaging shows no expansion. Pain management directly affects healing through stress hormone modulation. Adequate analgesia reduces catecholamine-driven catabolism. Combined neuraxial and peripheral nerve blocks for extremity trauma can eliminate opioid requirements entirely in the first 48 hours. I've used continuous femoral nerve catheters for distal femur fractures with excellent results, reducing opioid-related complications while improving patient comfort scores.
Get the Full Details

When Conventional Approaches Fall Short
The damage control paradigm has limitations, particularly in patients with pre-existing coagulopathies or those who develop abdominal compartment syndrome. Intra-abdominal pressures exceeding 20 mmHg with organ dysfunction require decompressive laparotomy. I managed a case where repeated closed-abdomen management led to renal failure and respiratory compromise that only resolved after fascial laxification with mesh bridging. Temporary abdominal closure systems like negative pressure wound therapy remain standard, but they don't solve every problem. Pharmacologic interventions targeting the inflammatory response have largely failed in clinical trials. Despite promising animal data, agents like IL-1 receptor antagonists and anti-TNF antibodies haven't demonstrated meaningful benefit in human trauma populations. The complexity of the cascade makes single-molecule targeting ineffective. Supportive care remains the most evidence-based approach. Rehabilitation timing varies significantly by injury pattern. Early mobilization within 48-72 hours for stable orthopedic injuries reduces pulmonary complications and muscle atrophy. The specific protocols depend on fixation stability and patient comorbidities. I've seen accelerated protocols work well for pelvic ring fractures treated with percutaneous fixation, while more complex cases require extended protected weight-bearing periods.
Nutritional assessment using tools like NRS-2002 or ESPEN criteria helps identify patients who will benefit from supplemental immune-modulating formulas containing arginine, omega-3 fatty acids, and nucleotides. The evidence for these formulations is stronger in elective surgical populations but shows promise in trauma patients with prolonged ICU stays.