
What a Tooth Filling Actually Is and What It Shouldn't Be
A tooth filling is a restorative procedure used to repair damage caused by tooth decay. The dentist removes the decayed portion of the tooth and fills the resulting cavity with a biocompatible material. The process is routine, but the outcomes vary significantly depending on material choice, cavity location, and the skill of the operator. Most people hear "filling" and think of a quick fix. It is not always that simple. The two most common filling materials in general practice today are composite resin and dental amalgam. Composite is tooth-colored and bonds directly to the tooth structure. Amalgam is a silver-colored alloy made primarily of mercury, silver, tin, and copper. It does not bond chemically to the tooth; it holds in place through mechanical retention and the precision of the cavity preparation. Each has distinct advantages and well-documented limitations.
Tooth Filling In Spanish Lo Esencial Para La Salud Dental
If you are reading Spanish-language dental resources or looking for the right terminology to use with a Spanish-speaking dentist, the key phrase here is obturacion dental. That is the standard term for a dental filling. "Empaste" is also used colloquially in some regions, though it is less clinical. Understanding these terms matters because translations from English health materials into Spanish are sometimes imprecise, and "health essentials" lists found online often skip over the technical details entirely. You need to know what the procedure actually involves rather than relying on a translated keyword list. The filling process follows a predictable sequence, but the time required depends heavily on cavity size and depth. For a small to moderate single-surface filling using composite resin, the entire procedure typically takes between 20 and 45 minutes per tooth. A large multi-surface restoration can run 60 to 90 minutes. Here is what happens during that window. Step one is anesthesia. The dentist applies a topical numbing gel and then injects a local anesthetic, usually lidocaine with epinephrine or articaine. The injection itself takes about ten seconds. Numbing takes two to five minutes to set in fully. If the decay is shallow and has not reached the dentin, some dentists will skip anesthesia entirely, though this is uncommon for anything beyond a superficial enamel lesion.
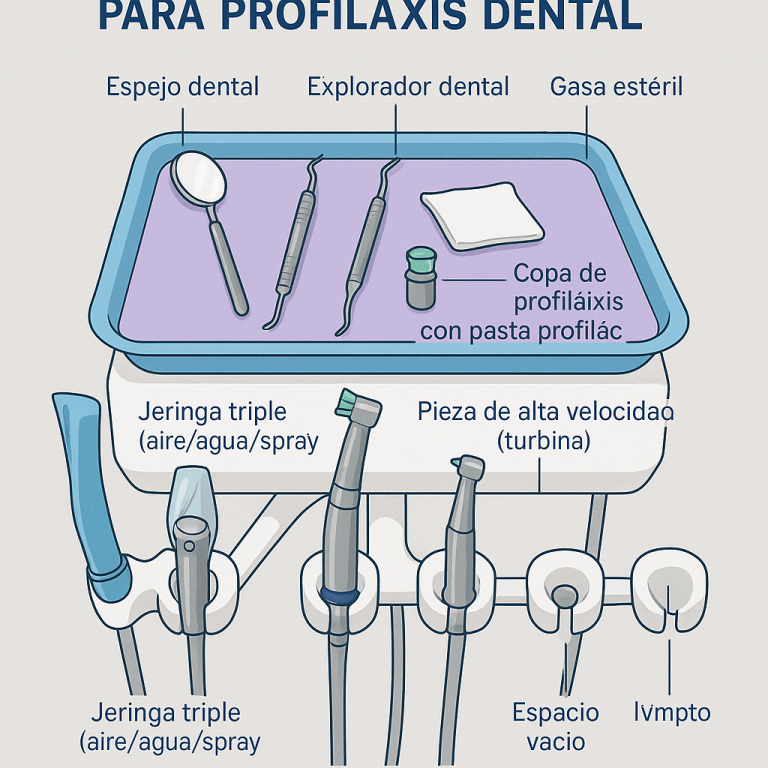
Step two is decay removal. This is done with a high-speed dental handpiece (the drill) or a slow-speed handpiece with a bur. The dentist removes infected dentin while preserving as much healthy tooth structure as possible. Air abrasion and laser techniques exist but are not widely used for standard fillings due to cost and limited indication range. During this phase, the dentist will encounter a texture change: decayed dentin is softer and leathery, while healthy dentin is hard and smooth. This tactile feedback is one of the most important skills in restorative dentistry. Step three is isolation. A rubber dam or cotton rolls and suction are used to keep the area dry. Moisture contamination is the number one cause of composite filling failure. Saliva or blood seeping into the prepared cavity before the bonding agent is applied will create a weak interface. The filling may look fine when you leave the chair, but within months it can develop microleakage, recurrent decay, or a frank fracture at the margin. Step four is bonding and placement. For composite fillings, the dentist etches the enamel and dentin with phosphoric acid gel, rinses it off, applies a primer and bonding agent, and then places the composite material in incremental layers. Each layer is cured with a blue-light polymerization lamp for about 20 to 40 seconds per layer. Layer thickness should not exceed 2 millimeters per increment to ensure adequate curing depth. Skipping this rule leads to a soft, under-cured layer at the bottom of the restoration that will fail prematurely.
Get the Full Details
Step five is shaping and polishing. Once the final layer is cured, the dentist checks your bite with articulating paper, adjusts any high spots, and polishes the surface. A properly polished composite filling feels smooth like natural enamel. A rough or overhanging margin collects plaque and irritates the gums.
Material Choices and Their Trade-offs
Composite resin fillings are the standard for front teeth and increasingly for back teeth as well. They look natural, bond to the tooth, and require less removal of healthy structure than amalgam. The downsides are technique sensitivity and cost. Composites absorb water over time, which causes minimal expansion and eventual wear. They also shrink slightly during polymerization, which can create gaps at the margins if the bonding protocol is not followed precisely. Amalgam fillings are stronger in terms of compressive strength and last longer in high-stress areas like large posterior surfaces. They are less technique-sensitive and cheaper. The downsides are aesthetics, the need for more tooth reduction, and the environmental and health concerns around mercury. Major dental organizations including the FDA and ADA consider amalgam safe for most patients, but it remains controversial in certain populations. Pregnant women and people with kidney impairment are often advised to avoid amalgam placement as a precaution. Glass ionomer is a third option used mostly for non-permanent fillings, pediatric cases, or as a liner beneath another material. It releases fluoride, which can help prevent recurrent decay, but it is weaker and wears faster than both composite and amalgam.
A Problem I Ran Into and How I Handled It
During a restoration on a molar with a cavity that extended near the pulp, I noticed the patient's bite felt slightly high immediately after the composite was finished. Standard adjustment should have resolved it, but the occlusion kept shifting every time the patient closed. The issue turned out to be the curing light. The lamp was underpowered, and the bottom layer of composite had not fully polymerized. The material was soft enough that biting pressure deformed it before the bond had achieved full strength. The fix was straightforward: remove the restoration entirely, replace it with a fresh batch of composite, and use a properly calibrated curing light with a radiometer to verify output before starting. It added roughly 20 minutes to the appointment and required re-isolating the tooth. Skipping that step would have resulted in a filling that fractured or leaked within a year. I now check curing light intensity at the start of every procedure, and I replace the fiber-optic tips every few months since they degrade with repeated autoclaving.

Common Pitfalls That Beginners Miss
One widely misunderstood point is that a filling cures completely right away. Composite resin reaches initial hardness within seconds of light exposure, but full polymerization continues for several hours afterward. This is why dentists advise against chewing hard or sticky foods on the treated side for a few hours after the appointment. Another overlooked factor is the transverse diameter of the cavity. Narrow, deep cavities present a significant challenge for moisture control and light penetration. The curing light cannot reach the bottom of a deep, narrow preparation effectively, which is why dentists use incremental layering and sometimes place a dentin desensitizer or base material first. A second counter-intuitive insight is that smaller is not always better. A very small, pinpoint cavity prep that is overly conservative can create a weak isthmus of remaining tooth structure that fractures under normal chewing forces. The ideal preparation balances preservation of healthy tooth with enough bulk of restorative material to withstand occlusal loads. This judgment call is where experience matters more than any textbook guideline.
Aftercare and Longevity
A well-placed composite filling lasts between five and ten years on average. Amalgam fillings can last ten to fifteen years or longer in low-moisture, low-bite-force situations. Glass ionomer typically lasts two to five years. Longevity depends on oral hygiene, diet, bite force, and the original quality of the placement. Grinding your teeth at night will destroy any filling faster, regardless of material. A nightguard is a practical investment if you have bruxism. When a filling fails, it usually fails at the margin. Recurrent decay develops under a compromised seal, and the dentist will need to remove the old restoration and place a new one. Each successive restoration removes more natural tooth structure, which is why prevention through fluoride use, flossing, and regular checkups is always the better path.
What the Spanish-Language Resources Get Wrong
Many Spanish-language dental health articles promote "lo esencial para la salud dental" with lists that include things like oil pulling, activated charcoal, and miracle herbal remedies. These are not substitutes for evidence-based care. Brushing twice daily with fluoride toothpaste, flossing once a day, and seeing a dentist for cleanings and exams every six months is what is actually essential. Anything else is supplementary at best and potentially harmful at worst. Charcoal abrasive paste can wear away enamel. Oil pulling does not remove established plaque or reverse decay. If a Spanish source presents these as replacements for professional dental care, disregard it. For someone who needs a filling, the relevant Spanish terms are: obturación (filling), resina compuesta (composite resin), amalgama (amalgam), dentina (dentin), pulpa dental (dental pulp), and caries (cavity or decay). Knowing these will help you ask the right questions and understand the dentist's explanation of what needs to be done and why.


