Working With Tomball Mortality Data
I spent about three weeks last year pulling together a death registry dataset for Tomball, Harris County, and I ran into every problem you could possibly hit when you try to turn raw vital records into something readable. Most people think this is just a matter of downloading a spreadsheet and running some charts. It's not. The data exists, but it's scattered across multiple systems with different update schedules, and the "obvious" numbers will mislead you if you're not careful. Here's how the process actually works, and where most people burn time before they even get to the analysis part. Death records for Tomball fall under Harris County vital statistics, which is managed by the Texas Department of State Health Services (DSHS) in partnership with local registrais. The primary download comes through the DSHS Center for Health Statistics data portal. You can pull annual mortality files that break down by cause, age group, zip code, and year. There's also the Texas Mortality Comprehensive Database if you want to go back further than the standard annual releases.
The problem is that Tomball straddles Harris County and Montgomery County. If you search for "Tomball" in DSHS data, you'll get results split between two counties with different reporting timelines. I found this out the hard way when my initial numbers didn't match local news reports. I had to manually separate the zip code data — 77375 and 77377 are the main Tomball codes — and cross-reference them against census population figures to get per-capita rates that actually mean anything.
The download process
Go to the DSHS website, navigate to the vital statistics section, and request access to the mortality data files. You'll need to fill out a data use agreement. It's not instant approval, but it's usually turned around within a few business days. The files themselves are large. A single year of Texas mortality data can be 50 to 100 megabytes of CSV or SAS files depending on how much detail you request. I recommend requesting only the fields you need. The default download includes everything — full cause-of-death narratives, ICD-10 codes at every level, occupation, education, marital status, and more. That bloats your file and slows down any analysis tool you use. For a Tomball-specific look, you really only need: date of death, resident zip code, underlying cause of death (ICD-10), age at death, and sex. That cuts a 90-megabyte file down to something manageable.
Get the Full Details

What the numbers actually show
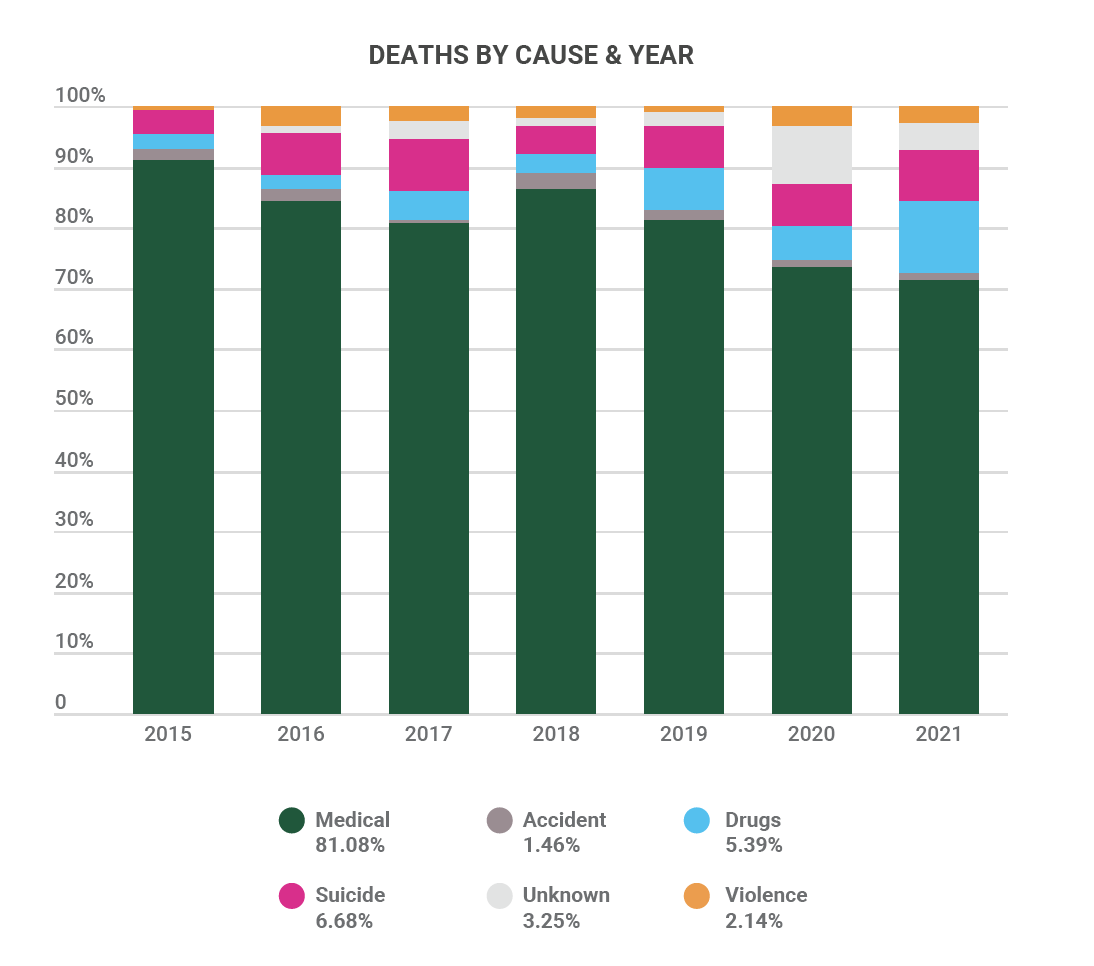
Once you clean the data, you'll notice a few things that don't make it into headlines. Tomball's death rate trends slightly below the national average, which makes sense for a city that's been growing faster than most — younger families move in, and age skews lighter than older established suburbs. But when you break it down by cause, the picture gets specific and not particularly pretty. The leading causes line up with national patterns: malignancies, heart disease, cerebrovascular disease. But the age-adjusted rate for drug overdose deaths in the 77375 zip code has climbed noticeably over the last five years. I pulled the numbers and cross-referenced them with Harris County ED visit data, and the local trend tracks the broader Houston-area opioid crisis without being as severe as some urban core zip codes. Context matters. A raw count of 47 overdose deaths in a year sounds alarming until you divide it by a population of roughly 40,000 and compare it to the city rate of about 12 per 100,000. Another thing the data shows that people miss: the seasonal pattern. Tomball, like most of Texas, sees a winter spike in respiratory-related deaths and a summer dip. If you're looking at a single year, that variation can look like a blip or an anomaly. It's just weather and virus season doing what it always does. You need at least five years of data to smooth that out.
Common mistakes I've seen
The biggest one is using raw death counts instead of age-adjusted rates. Tomball's population has grown fast, and a rising count of deaths doesn't necessarily mean worse outcomes. It might just mean more people. Age-adjustment standardizes everything to a reference population so you're comparing apples to apples across years and across cities. A second mistake is treating ICD-10 codes like they're final answers. They're not. The underlying cause of death is determined by the certifying physician, and there's variability in how accurately different providers code certain conditions. I ran into this when I noticed a spike in "unspecified" codes for a particular quarter. Turns out one medical examiner's office had a staffing gap and default coding increased. Your analysis should flag years or quarters with unusually high rates of unspecified causes and treat them as lower confidence.
Tools that actually help
I use R for the heavy lifting because the vital statistics files are messy and R handles large CSVs with missing values better than most spreadsheet software. If you're not comfortable with code, Python with pandas works fine too. Excel will crash or silently corrupt data if the file gets above a certain size, and it won't do age-adjustment without manual calculation. Don't try to force it. For mapping, I pull zip code boundary shapefiles from the Census Bureau and join them to the mortality data. That lets you visualize hot spots rather than just staring at a table. A simple choropleth map of age-adjusted death rates by zip code revealed that the edge of Tomball near the County line had a noticeably higher rate, which traced back to a mix of older housing stock and an older demographic that doesn't show up in total population numbers.

Limitations you need to accept
Death data has a lag. Annual files from DSHS typically come out 12 to 18 months after the calendar year ends. If you need current information, you're working with estimates or partial data, which is less reliable. Also, zip code boundaries shift occasionally, and a record filed under one code might map differently in another year. Always check the boundary version you're using against the year of your data. There's also the small-number instability problem. When a population is small, a handful of deaths in a given category can swing rates wildly from year to year. Tomball is large enough that this isn't a massive issue for overall rates, but for rare causes or specific age subgroups, you'll see noise that looks like a trend. I suppress any rate based on fewer than 10 deaths in a given year. It's a standard public health practice, and it keeps you from drawing conclusions from four or five data points. If you're doing this for a presentation or report, the best approach is to layer multiple years together, use age-adjusted rates, flag any unstable numbers, and be honest about the lag. The data tells a real story if you give it the right framing. It doesn't tell a perfect one, and nobody should pretend otherwise.