Understanding the Midback Spine: A Working Guide to the Thoracic Region
The thoracic spine sits between the cervical and lumbar regions, and it is the part most people notice only when it stops working correctly. There are twelve vertebrae, numbered T1 through T12. They are not just a sequence of bones. Each one has a specific role, and their arrangement explains a lot about why certain movements feel restricted or painful. I have spent years looking at imaging and working with people who have midback issues, and the anatomy is often more relevant than most guides admit. This is a functional overview of the thoracic region, with labeled structures explained in practical terms rather than textbook definitions alone.
Thoracic Vertebrae Labeled The Complete Atlas And Functional Guide To Your Midback Spine
Basic Anatomical Structure
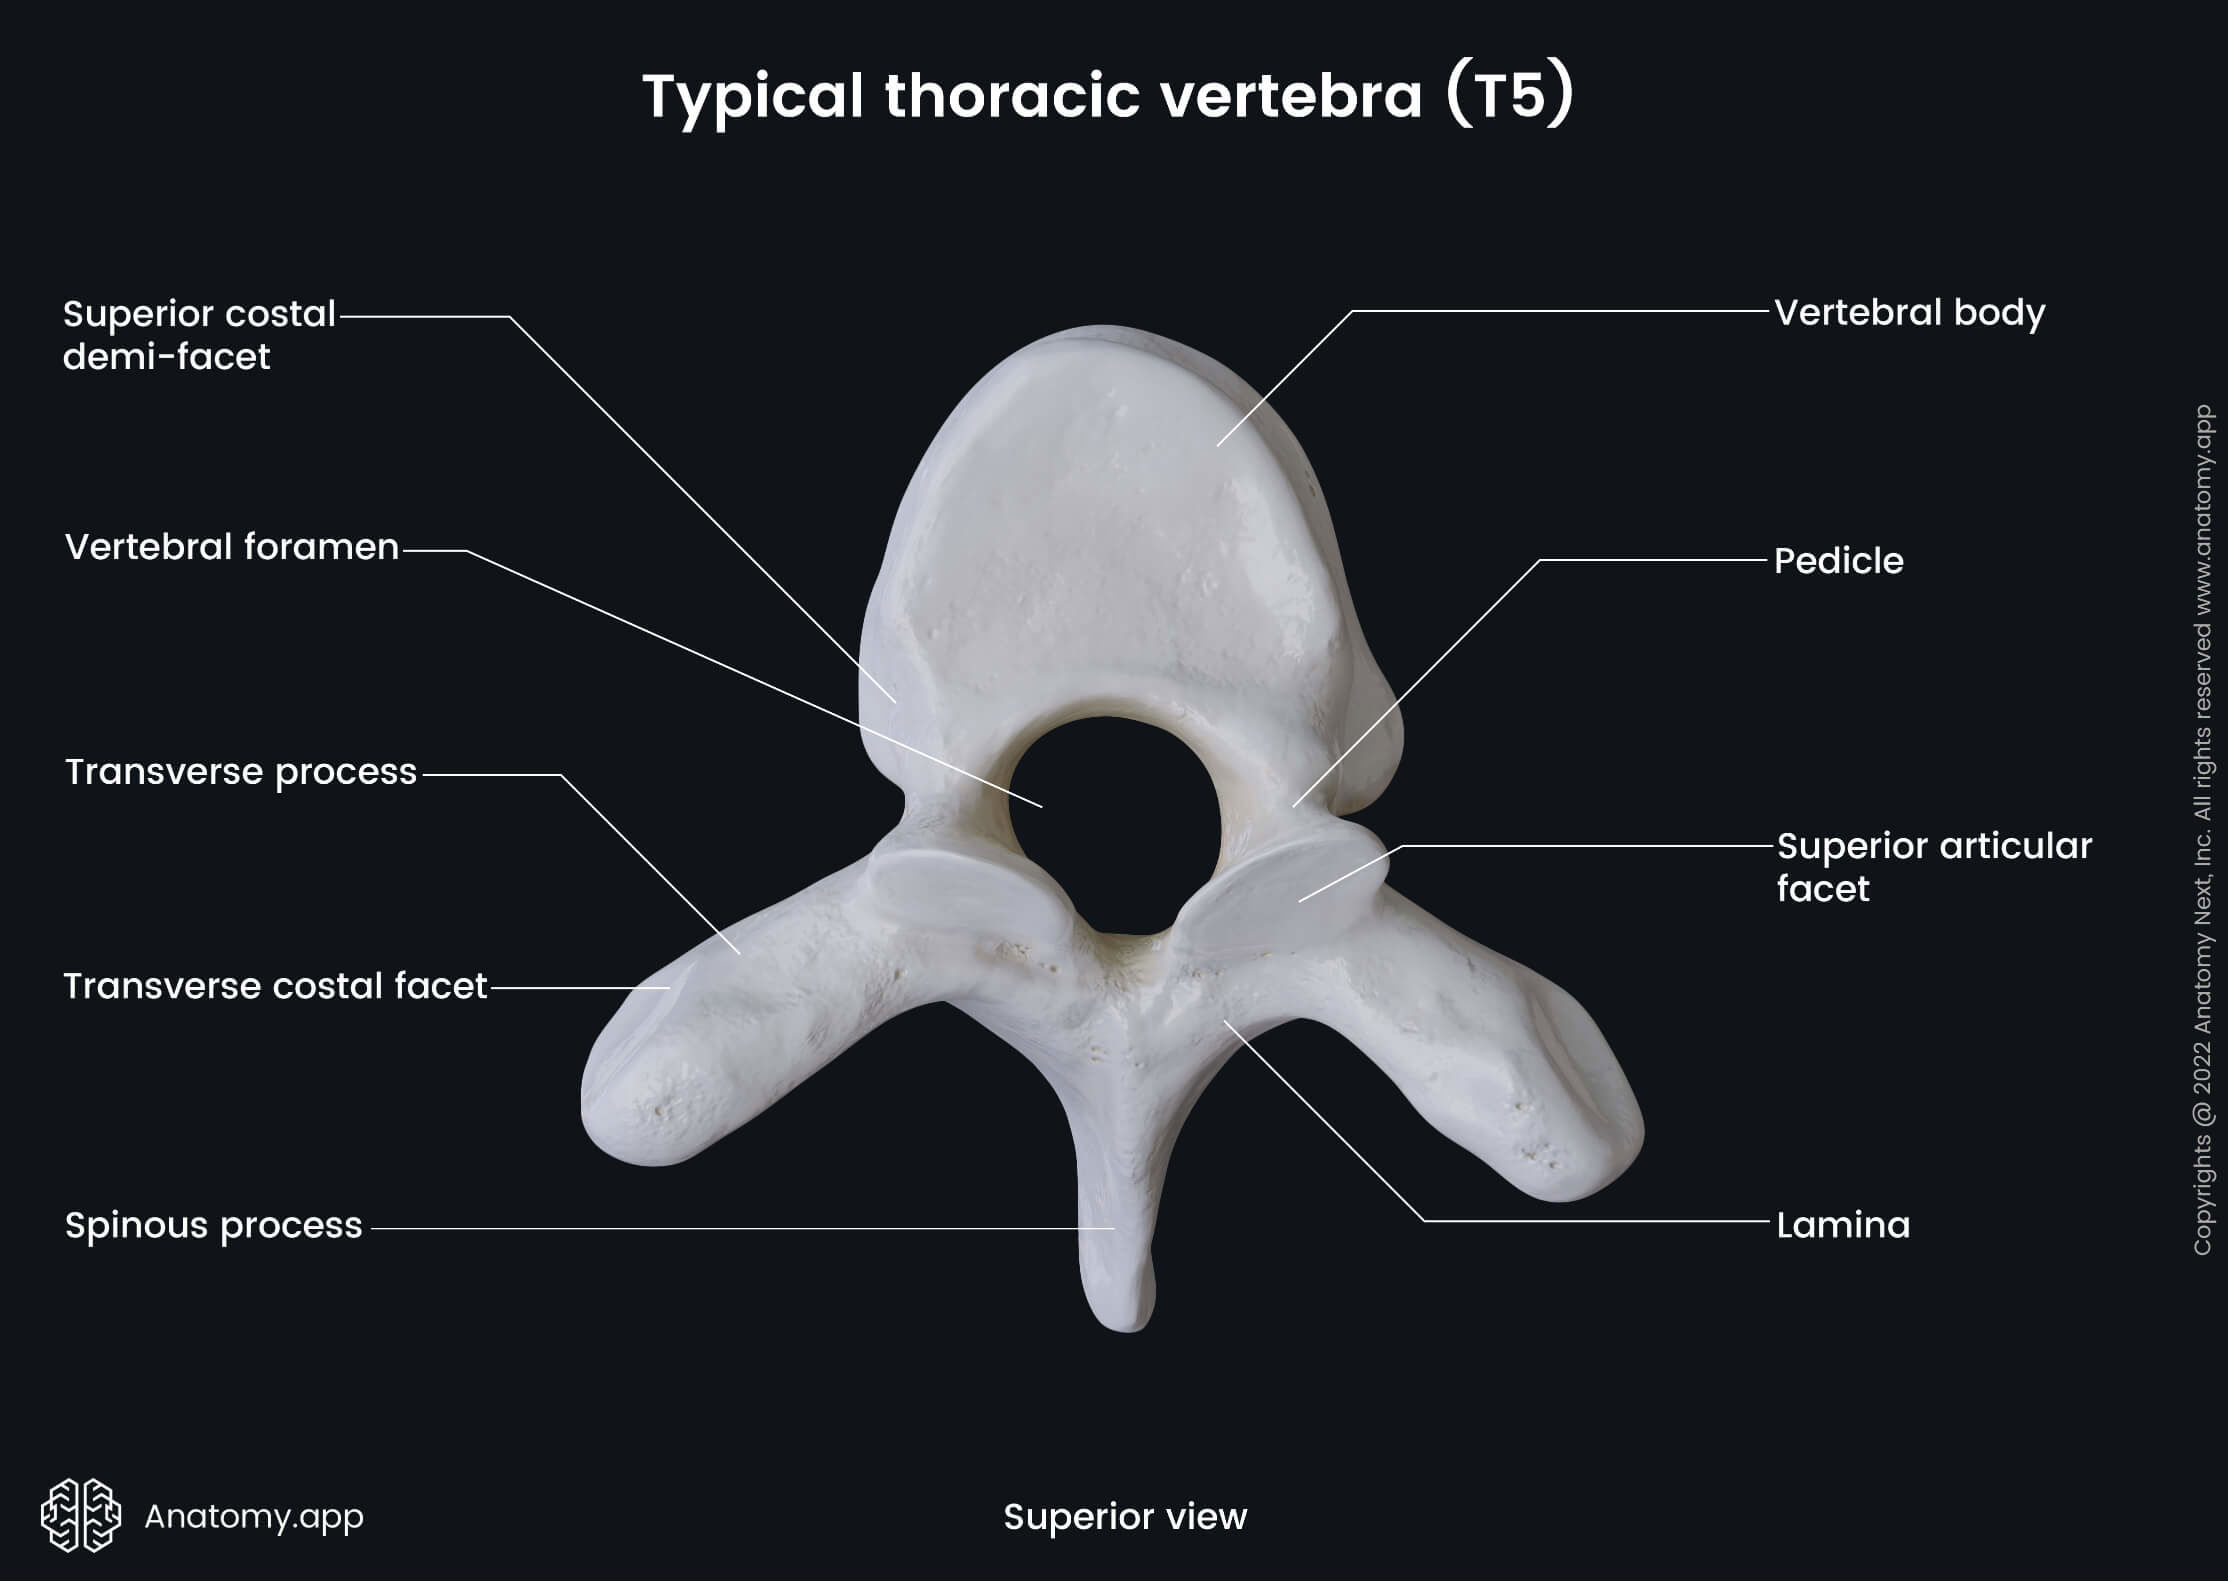
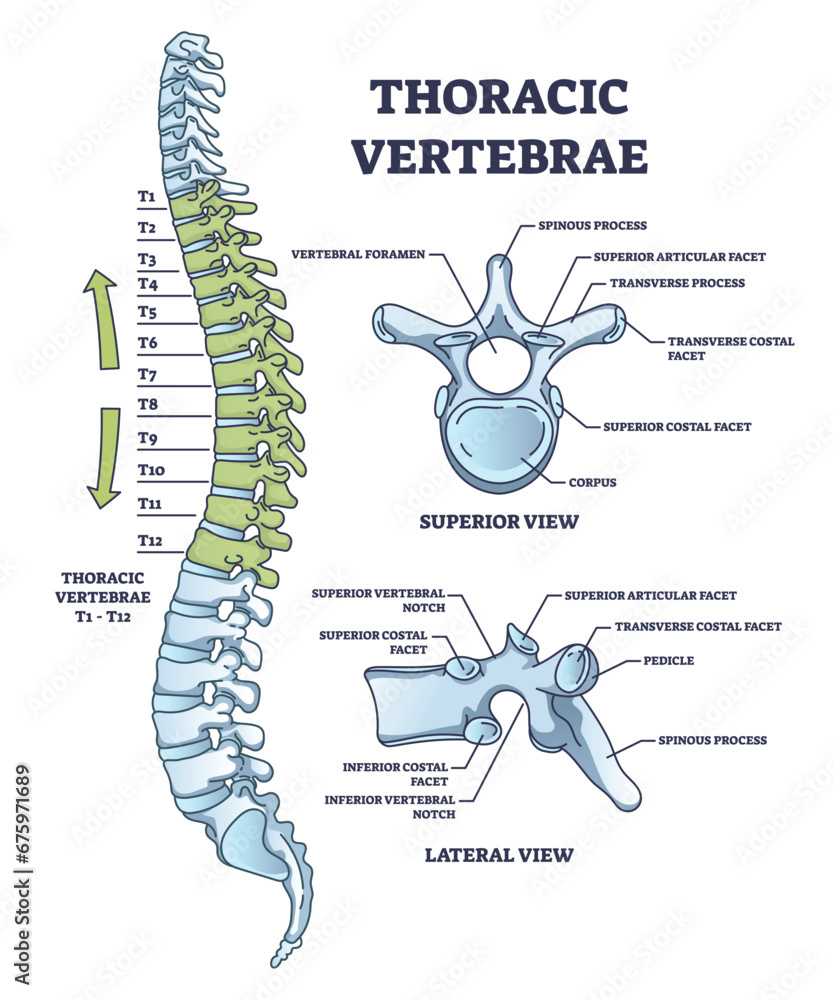
Each thoracic vertebra has a heart-shaped body. The bodies increase in size from T1 down to T12, which mirrors the increasing load they support. The vertebral foramen is smaller than in the cervical or lumbar regions, which means the spinal canal here has less room for movement. The spinal cord occupies more of the canal space in the thoracic region compared to other areas. The transverse processes project laterally and have facets on their anterior surface called costal facets. These articulate with the tubercles of the ribs. The superior articular processes face posteriorly and slightly laterally, while the inferior articular processes face anteriorly and medially. This orientation restricts rotation to some degree, but it does not prevent it entirely. The spinous processes are long and slope downward sharply. In the mid-thoracic region they often overlap like shingles on a roof. This overlapping design limits flexion and extension but provides attachment points for ligaments and muscles that control posture.
Vertebral Variations by Region
The thoracic spine is not uniform. T1 has a partial facet on its body for the first rib and a full facet for the second rib on its transverse process. T2 through T9 are typical thoracic vertebrae with complete costal facets on the body and transverse processes. T10 may lack costal facets on the transverse process entirely. T11 and T12 are atypical. They have whole body facets but no transverse costal facets, and their spinous processes are shorter and less angled. I encountered a case recently where a patient presented with right-sided midback pain that radiated around to the front. Imaging showed T4-T5 had a congenital hemivertebra on the right side. The patient had adapted to it over decades without knowing what it was. Standard treatment approaches would not have addressed the root cause because the structural variation was not obvious on a cursory review. We adjusted the movement analysis to account for the asymmetry, and the treatment plan changed significantly.
Get the Full Details

Rib Articulations and Their Impact
The thoracic vertebrae connect to the ribs, and this connection determines a lot about how the midback moves. True ribs (one through seven) attach directly to the sternum via costal cartilage. False ribs (eight through ten) attach indirectly or not at all to the sternum. Floating ribs (eleven and twelve) have no anterior attachment. This rib cage creates a stabilizing barrel around the thoracic spine. It limits lateral flexion and rotation compared to the lumbar region, but it allows a controlled amount of both. When the rib articulations are stiff or inflamed, thoracic mobility drops quickly. I have seen patients with frozen thoracic motion from chronic costovertebral joint irritation that resolved after targeted mobilization of those specific joints rather than generic stretching.
Movement Patterns and Functional Implications
The thoracic spine flexes, extends, laterally flexes, and rotates. Flexion and extension range is relatively limited, averaging about five to ten degrees per segment. Lateral flexion is similarly restricted. Rotation is the primary movement, and it is distributed across all twelve segments. A common mistake in rehabilitation is treating thoracic stiffness as a single issue. It is not. Upper thoracic restrictions (T1-T4) affect neck and shoulder mechanics. Lower thoracic restrictions (T8-T12) affect lumbar mechanics because the lumbar spine compensates for lack of upper spine mobility. I had a patient with recurrent lower back pain who improved only after we addressed T9-T10 stiffness. The low back was never the primary problem.
Common Pathologies and Clinical Considerations
Thoracic disc herniations are rare, accounting for roughly one percent of all disc herniations. The rib cage and ligamentous support provide significant stability. When they do occur, they often present with radicular pain following a dermatomal pattern rather than axial back pain. Osteoporotic compression fractures are more common in the thoracic region, particularly at the thoracolumbar junction (T12-L1). This is a high-stress transition zone where the rigid thoracic cage meets the more mobile lumbar spine. Vertebral body fractures here can reduce height anteriorly, creating kyphotic deformity. Scoliosis frequently involves the thoracic spine. Right convex thoracic curves are the most common pattern in idiopathic scoliosis. The rotation component of scoliosis causes rib humping on the convex side due to vertebral rotation pulling the attached ribs with it. This is not just a curvature issue. It is a three-dimensional deformity.
Palpation and Surface Landmarks
The spinous process of T7 is the most prominent landmark in the midback. It is often called the vertebra prominens, though that term technically applies to C7. T7 can be located by finding the inferior angle of the scapula, which rests approximately at that level when the arms are at the sides. Palpating the transverse processes requires careful technique because the ribs overlie them. The costotransverse joints are accessible just lateral to the spinous processes at each level. Joint dysfunction here is a frequent source of localized midback pain and referred pain patterns.
Practical Assessment Approach
Assessing thoracic mobility requires segmental evaluation rather than global movement observation. Have the patient sit or stand with hands behind the head. Observe flexion, extension, lateral flexion, and rotation at each level. Note where restriction begins and whether it is unilateral or bilateral. Rib assessment should include posterior palpation of the costovertebral and costotransverse joints through the full range of passive motion. Asymmetry in joint play is often more informative than range of motion measurements alone. I typically find that patients with chronic midback pain have multiple levels with restricted joint play rather than one obviously damaged segment.
References and Resources
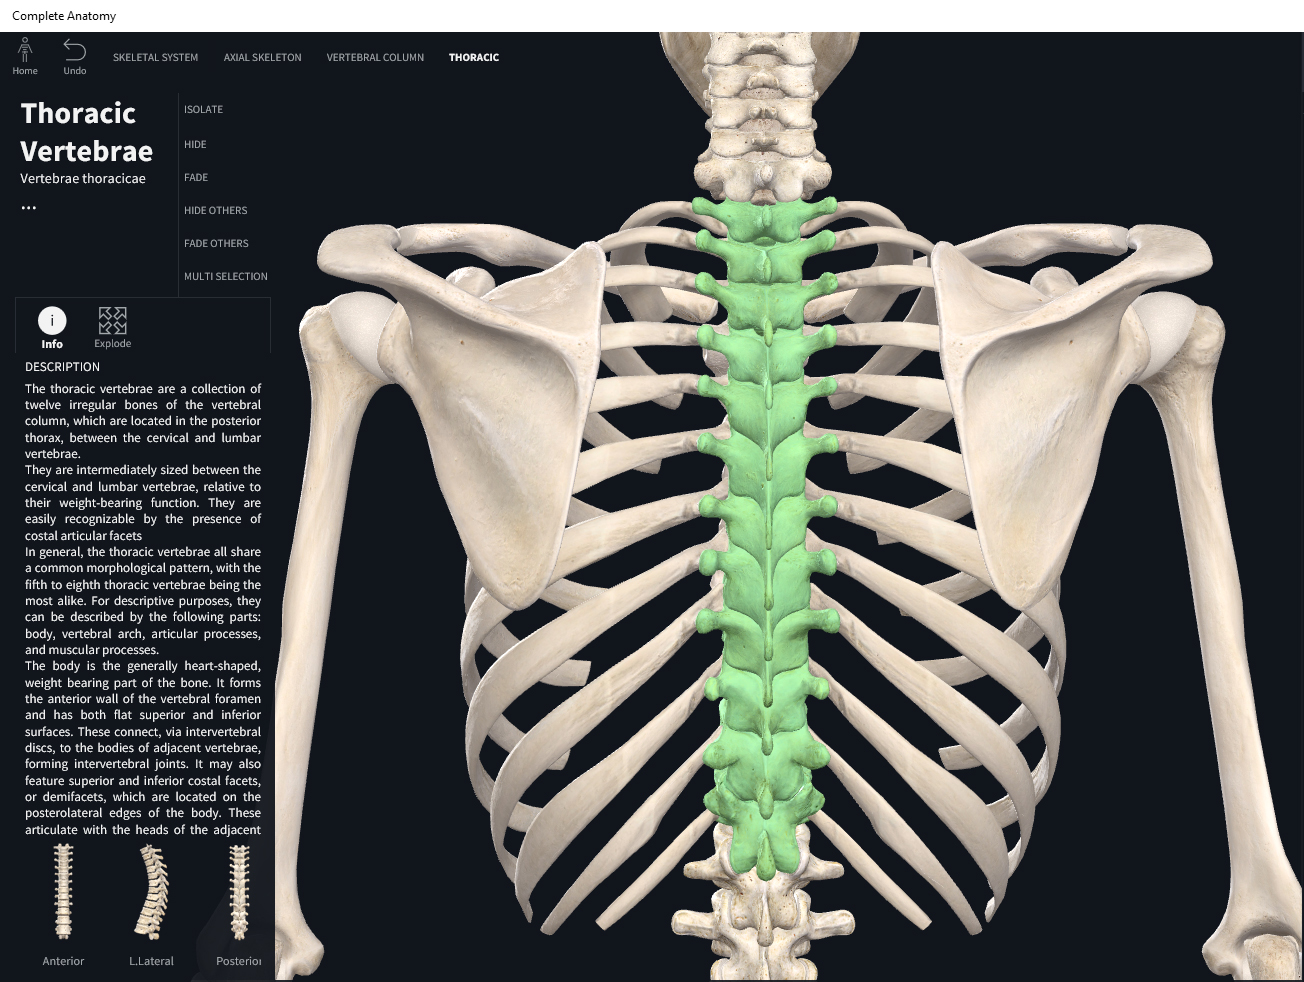
For detailed anatomical reference, standard texts such as Gray's Anatomy and Netter's Atlas of Human Anatomy provide comprehensive labeled illustrations of thoracic vertebrae. Clinical guides like Magee's Orthopedic Physical Assessment cover the functional assessment principles discussed here. Imaging atlases and anatomy software can supplement this information with three-dimensional views of the thoracic spine and rib articulations. These tools are useful for visualizing the spatial relationships that plain text descriptions cannot fully convey.