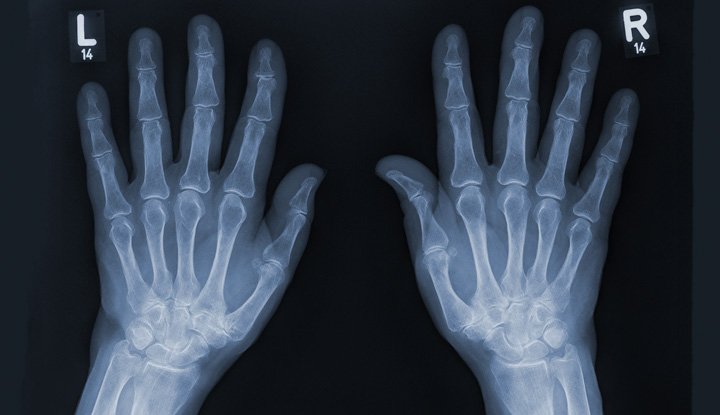
How Hand X-ray Imaging Actually Works
Most people think hand X-ray is straightforward. You put your hand on a plate, push a button, and get an image. The reality is a lot more fiddly than that. I've spent years working with hand radiography across clinical and forensic settings, and the difference between a diagnostic-quality image and a waste of film usually comes down to things nobody tells you about in the textbooks.The Xray Vision Of The Hand Unveiling The Secrets Of Hand Xray
Let me explain how the physics works first because that determines everything else about your setup. A standard hand X-ray uses low-kVp, typically between 50 and 60 kilovolts peak. This is deliberately lower than what you'd use for a chest or abdomen. The reason is simple: bone absorbs X-ray photons much more readily than soft tissue at these energy levels, and you want maximum contrast between the cortical bone and the surrounding structures. If you crank up the kVp to get a quicker exposure, you lose that contrast and the image becomes flat and useless for detecting subtle fractures. The milliamperage is equally important. You're looking at around 2 to 5 milliampere-seconds for an adult hand. That sounds small, but it matters. Too low and you get quantum mottle, which makes the image grainy and unreadable. Too high and you're irradiating the patient unnecessarily while risking saturation of the detector. I learned this the hard way during my second year when I was reading orthopedic films at a smaller clinic. We had a case involving a suspected scaphoid fracture on a 34-year-old male mechanic. The initial PA view looked clean. Standard protocol would have been to immobilize and repeat in 10 days, but something about the patient's mechanism of injury felt off to me. I took an additional lateral view with a slightly different angle, tilted the tube about 15 degrees caudally. There it was. A nondisplaced scaphoid waist fracture that the standard views had completely missed. The trick was recognizing that the scaphoid sits at an angle in the wrist. When you shoot it head-on, the proximal and distal poles overlap perfectly, hiding any fracture line running through the narrow waist. Tilt the beam and you separate those two segments enough to see the disruption. This is one of those things that doesn't come up in most training programs because it requires actually thinking about the anatomy rather than just following a checklist.Positioning protocols vary by clinical question. A routine hand series includes three views: posteroanterior, lateral, and oblique. The PA view goes with the hand flat on the detector, fingers spread slightly, X-ray beam perpendicular to the metacarpals. The lateral is trickier than it sounds. You have to rotate the hand 90 degrees so the thumb is up, but here's where people go wrong. They flex or extend the wrist, which superimposes the carpal bones in a way that obscures important detail. The wrist needs to be neutral, and the humerus should be parallel to the image receptor. If the lateral is done right, you should be able to trace the radius, lunate, and capitate in a smooth continuous arc. If that arc breaks, the position is wrong and you'll need to redo it. The oblique view has the hand rotated about 45 degrees from the PA position. This spreads out the metacarpal bases and the intermetacarpal spaces. It's essential for seeing injuries that the PA and lateral views compress together. I've seen metacarpal base fractures on the oblique that were completely invisible on the other two views combined. The fifth metacarpal base in particular, the one involved in boxer's fractures, shows up much better here because the rotation pulls it away from the rest of the carpal structure.
I work with a digital CR system now instead of film, and the workflow has changed significantly. With computed radiography, you use a phosphor plate that gets scanned by a laser after exposure. The dynamic range is wider than film, which means you can overexpose or underexpose somewhat and still recover the image during processing. That sounds like a benefit, and it is, but it also creates a dangerous complacency. Technicians who learned on film had a stronger incentive to get the exposure parameters right the first time because film doesn't forgive mistakes. Digital plates forgive a lot, and I've seen images that were clearly underexposed that still passed quality review because the processing software boosted the brightness enough to make everything visible. The tradeoff is increased noise in those recovered areas. There's also a problem with digital systems that nobody warns you about. When you boost a dark image during post-processing, you're not actually revealing more information. You're amplifying the signal that was already there along with the noise. A radiologist reading that image is working with the same diagnostic information they would have gotten from a properly exposed film, but now there's more visual clutter. This is why I still check the histogram on every single image before signing off. If the pixel values are bunched at the low end, I flag it and retake it. Takes thirty seconds and prevents diagnostic errors downstream.Pediatric hand X-rays require a completely different approach. The bones are still developing, which means you're looking at growth plates, ossification centers, and epiphyseal nuclei rather than fully formed bone. A normal child's hand looks nothing like an adult hand on X-ray, and misinterpreting normal anatomy as pathology is one of the most common errors in musculoskeletal imaging. The distal radius has multiple ossification centers that appear at different ages. The capitate and lunate appear around ages one and four respectively. If you don't know the normal sequence, you'll report a nonunion or delayed ossification that doesn't exist. For pediatric patients, exposure parameters drop significantly. A 5-year-old might need only 1 to 2 mAs compared to 3 to 5 for an adult. Children absorb radiation differently too, and their radiosensitivity is higher per unit of tissue mass. I've worked with facilities that had no pediatric protocols and were using adult hand settings on kids, which is both an unnecessary radiation risk and often produces overpenetrated images where the fine trabecular detail disappears into the background.
I've also encountered edge cases involving foreign bodies. Metal fragments, wood, glass. Standard X-ray picks up metal without question. Wood is nearly invisible unless it's large and you're lucky with the angle. Glass depends entirely on the type. Silica glass is radiolucent. Lead crystal shows up clearly. This came up with a 28-year-old woman who came in with a puncture wound to her palm from a vase. The initial X-ray showed nothing. She insisted she could feel something. I switched to a higher resolution technique with a smaller focal spot and increased magnification by placing the hand closer to the detector and the tube farther away. At that magnification, I could see a cluster of tiny radiopaque fragments embedded in the soft tissue, maybe 2 millimeters each. Too small for the standard view to resolve. She needed surgery to remove them. If I'd stuck with the routine protocol, those would have been missed.One thing worth understanding is how soft tissue evaluation works. A hand X-ray isn't just about bones. The soft tissue planes carry diagnostic information. Prevertebral soft tissue swelling on a lateral neck X-ray is a classic example, and the same principle applies to the hand. Swelling in the thenar eminence might suggest an infection tracking along the flexor tendon sheath. A loose body in the joint space shows up as a rounded density within the articulation. Subcutaneous emphysema appears as streaks of air in the soft tissues, usually from trauma or infection. The limitations are real though. X-ray is a 2D representation of a 3D structure. Overlapping bones create ambiguity. The scaphoid is the textbook example of this problem. So are the carpal bones in general. When you need to resolve what's happening in three dimensions, CT is the next step. A CT scan of the hand with 3D reconstruction can show fracture displacement, articular involvement, and carpal alignment in ways that plain film simply cannot. I use CT when the X-ray findings don't match the clinical picture or when pre-surgical planning requires precise anatomical detail.
Get the Full Details