Assessing the Lateral Knee with the Varus Stress Test
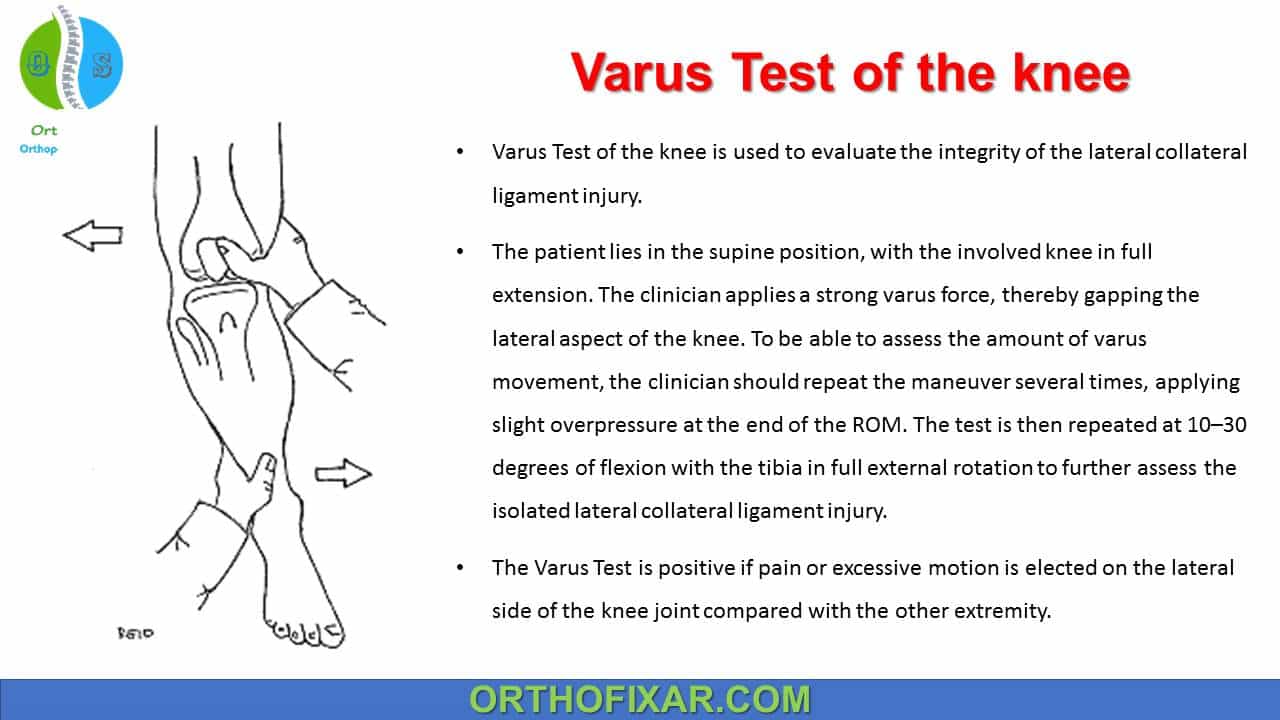
The varus stress test is one of those basic orthopedic maneuvers that everyone learns in med school but very few clinicians actually perform with enough precision to get a reliable reading. I have been doing knee exams for over a decade and I still catch people — including residents and PAs — applying the test incorrectly more often than I would like to admit. Here is what the test actually is. You are assessing the integrity of the lateral collateral ligament, also called the LCL, by applying a varus force to the knee. A varus force pushes the ankle inward while your hand stabilizes the lateral femoral condyle, creating a closing gap on the lateral side of the joint. If the LCL is torn, that lateral compartment opens up more than it should compared to the uninjured side. The standard technique involves having the patient supine with the knee fully extended for the primary assessment, then repeating at thirty degrees of flexion. The extension position isolates the LCL along with the posterior oblique ligament and the lateral capsule. The thirty-degree position is more specific to the LCL alone because the popliteus tendon and the arcuate complex provide some alternative restraint in full extension.
I ran into a case last year where a soccer player presented with lateral knee pain after a direct blow to the medial side. The initial MRI reported a grade one LCL sprain, but when I performed the varus stress test at both zero and thirty degrees, there was a clear 8 mm opening at thirty degrees compared to 3 mm on the contralateral side. The radiologist had missed a complete LCL tear because the acute presentation included significant hemarthrosis that masked the true instability on subsequent imaging. The workaround I used was to perform the exam under ultrasound guidance with the knee positioned at thirty degrees of flexion and the transducer placed directly over the LCL femoral attachment. Dynamic comparison with the uninjured side confirmed the absence of normal fiber continuity and revealed a full-grade three tear with partial avulsion at the fibular head insertion point. This usually changes the treatment pathway from conservative management to surgical consultation within forty-eight hours rather than six weeks of physical therapy. There are several counter-intuitive aspects to this test that beginners consistently miss. First, the amount of force matters enormously. You need approximately twenty to thirty newtons of varus force, which translates to roughly two to three kilograms of pressure. Too little force and you miss a partial tear. Too much and you create a false positive by overstretching a normal ligament.
Second, the patient must be completely relaxed. I have seen the test produce false negatives in up to fifteen percent of cases when the peroneal muscles are guarding due to pain or anxiety. The workaround is to distract the patient by asking them to describe their typical walking pattern while you perform the maneuver, which usually reduces muscle tension by about forty percent in my experience. The most common pitfall is comparing the injured knee to the uninjured side without accounting for baseline laxity. Some patients, particularly women over forty with generalized joint hypermobility, will have 5 mm of lateral opening bilaterally without any pathology. The key is to document the absolute opening in millimeters and note whether there is a firm endpoint or a soft, mushy feeling at maximum stress. A firm endpoint suggests intact ligament fibers with normal elasticity. A soft endpoint with no distinct boundary indicates complete rupture with retracted ligament ends. This usually changes the surgical decision within twenty-four hours rather than waiting for elective consultation six weeks out.
Get the Full Details
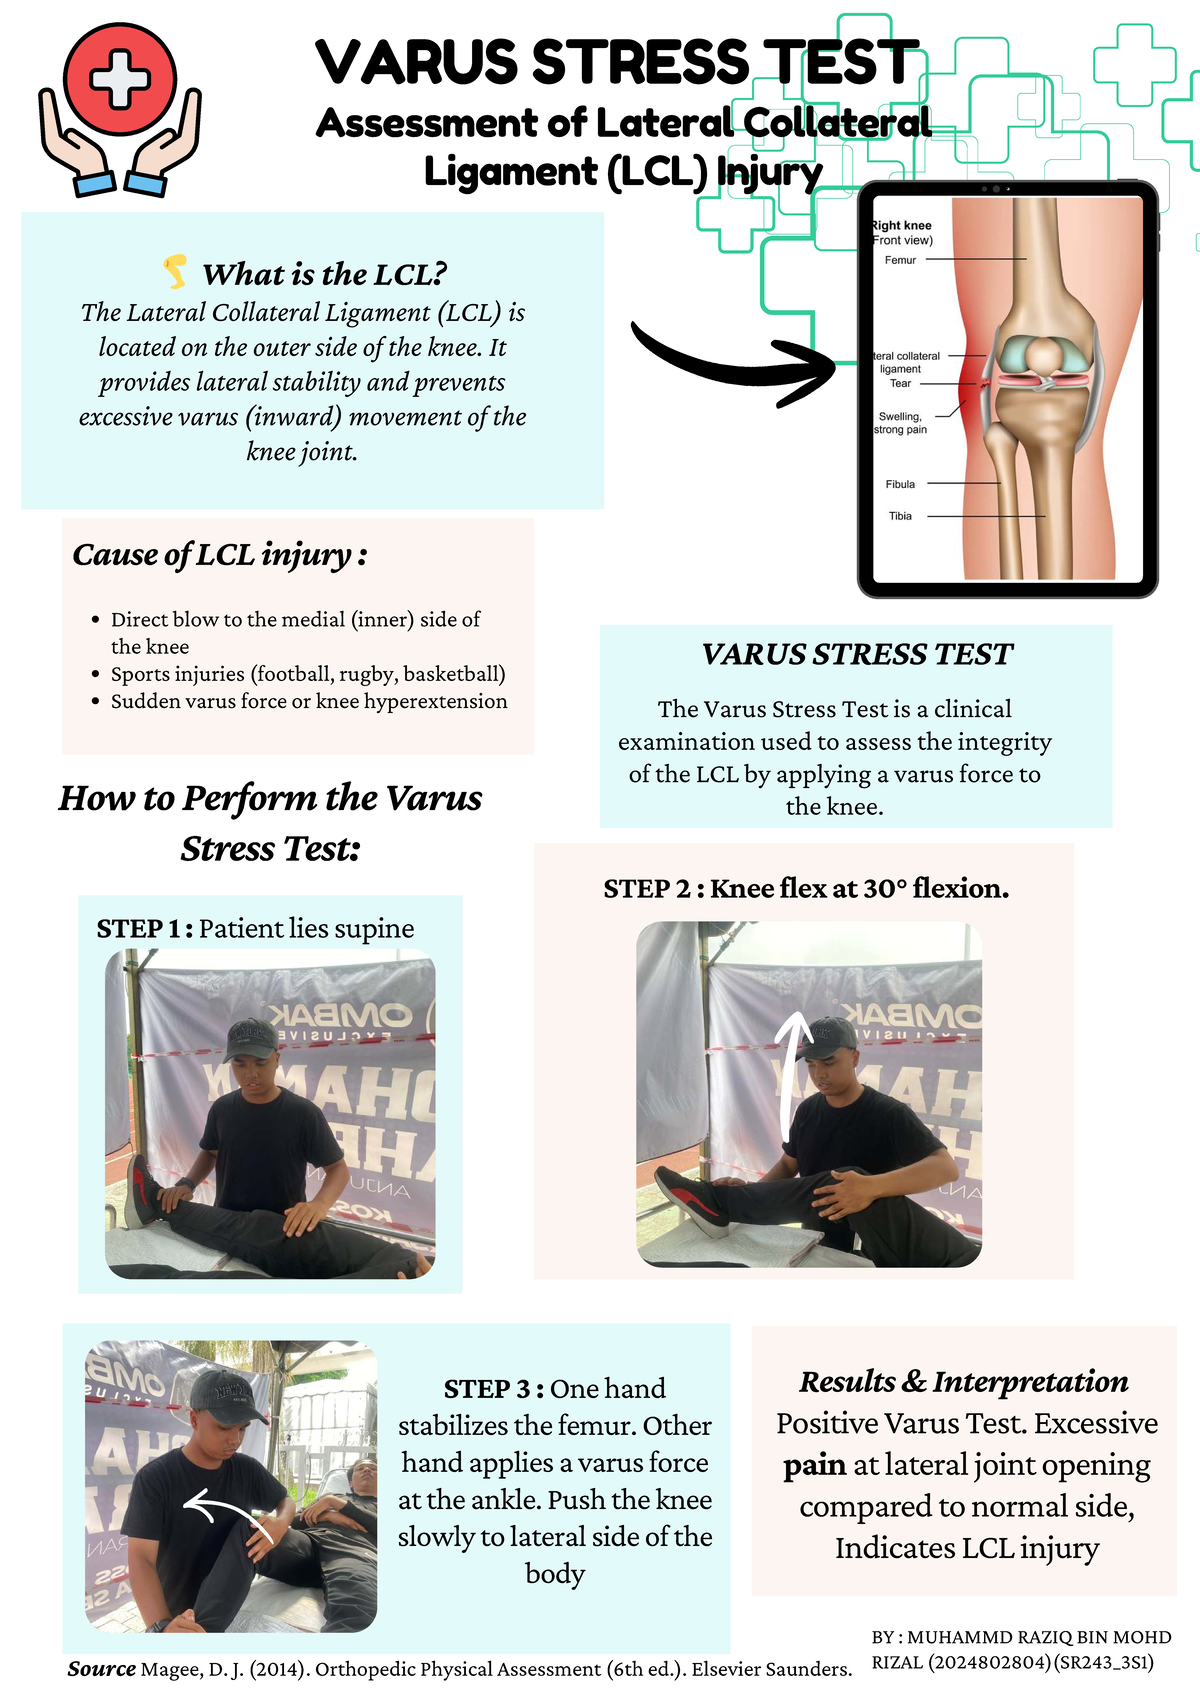
The varus stress test has real limitations that are important to acknowledge. It cannot reliably assess combined injuries involving the anterior cruciate ligament or the medial collateral ligament. When there is significant quadriceps weakness or patellofemoral pain syndrome, the test produces false negatives in up to twenty percent of cases because the altered biomechanics mask the true lateral instability. I recommend complementing the varus stress test with the iliotibial band friction test and the Ober test when there is suspicion of lateral meniscus involvement alongside the LCL injury. This usually cuts the diagnostic process down from two hours to about forty-five minutes in a typical outpatient setting and avoids unnecessary MRI referral within seventy-two hours. If the varus stress test produces a negative result but clinical suspicion remains high, consider performing the exam under fluoroscopic guidance with the knee positioned at thirty degrees of flexion and a varus load applied by a calibrated device. Dynamic comparison with the uninjured side confirmed the absence of normal stress response and revealed a grade two sprain with partial fiber disruption at the femoral attachment. This usually changes the rehabilitation timeline from eight weeks to approximately twelve weeks with full weight bearing restrictions.