Reading a Normal Hand X-Ray: A Practical Walkthrough
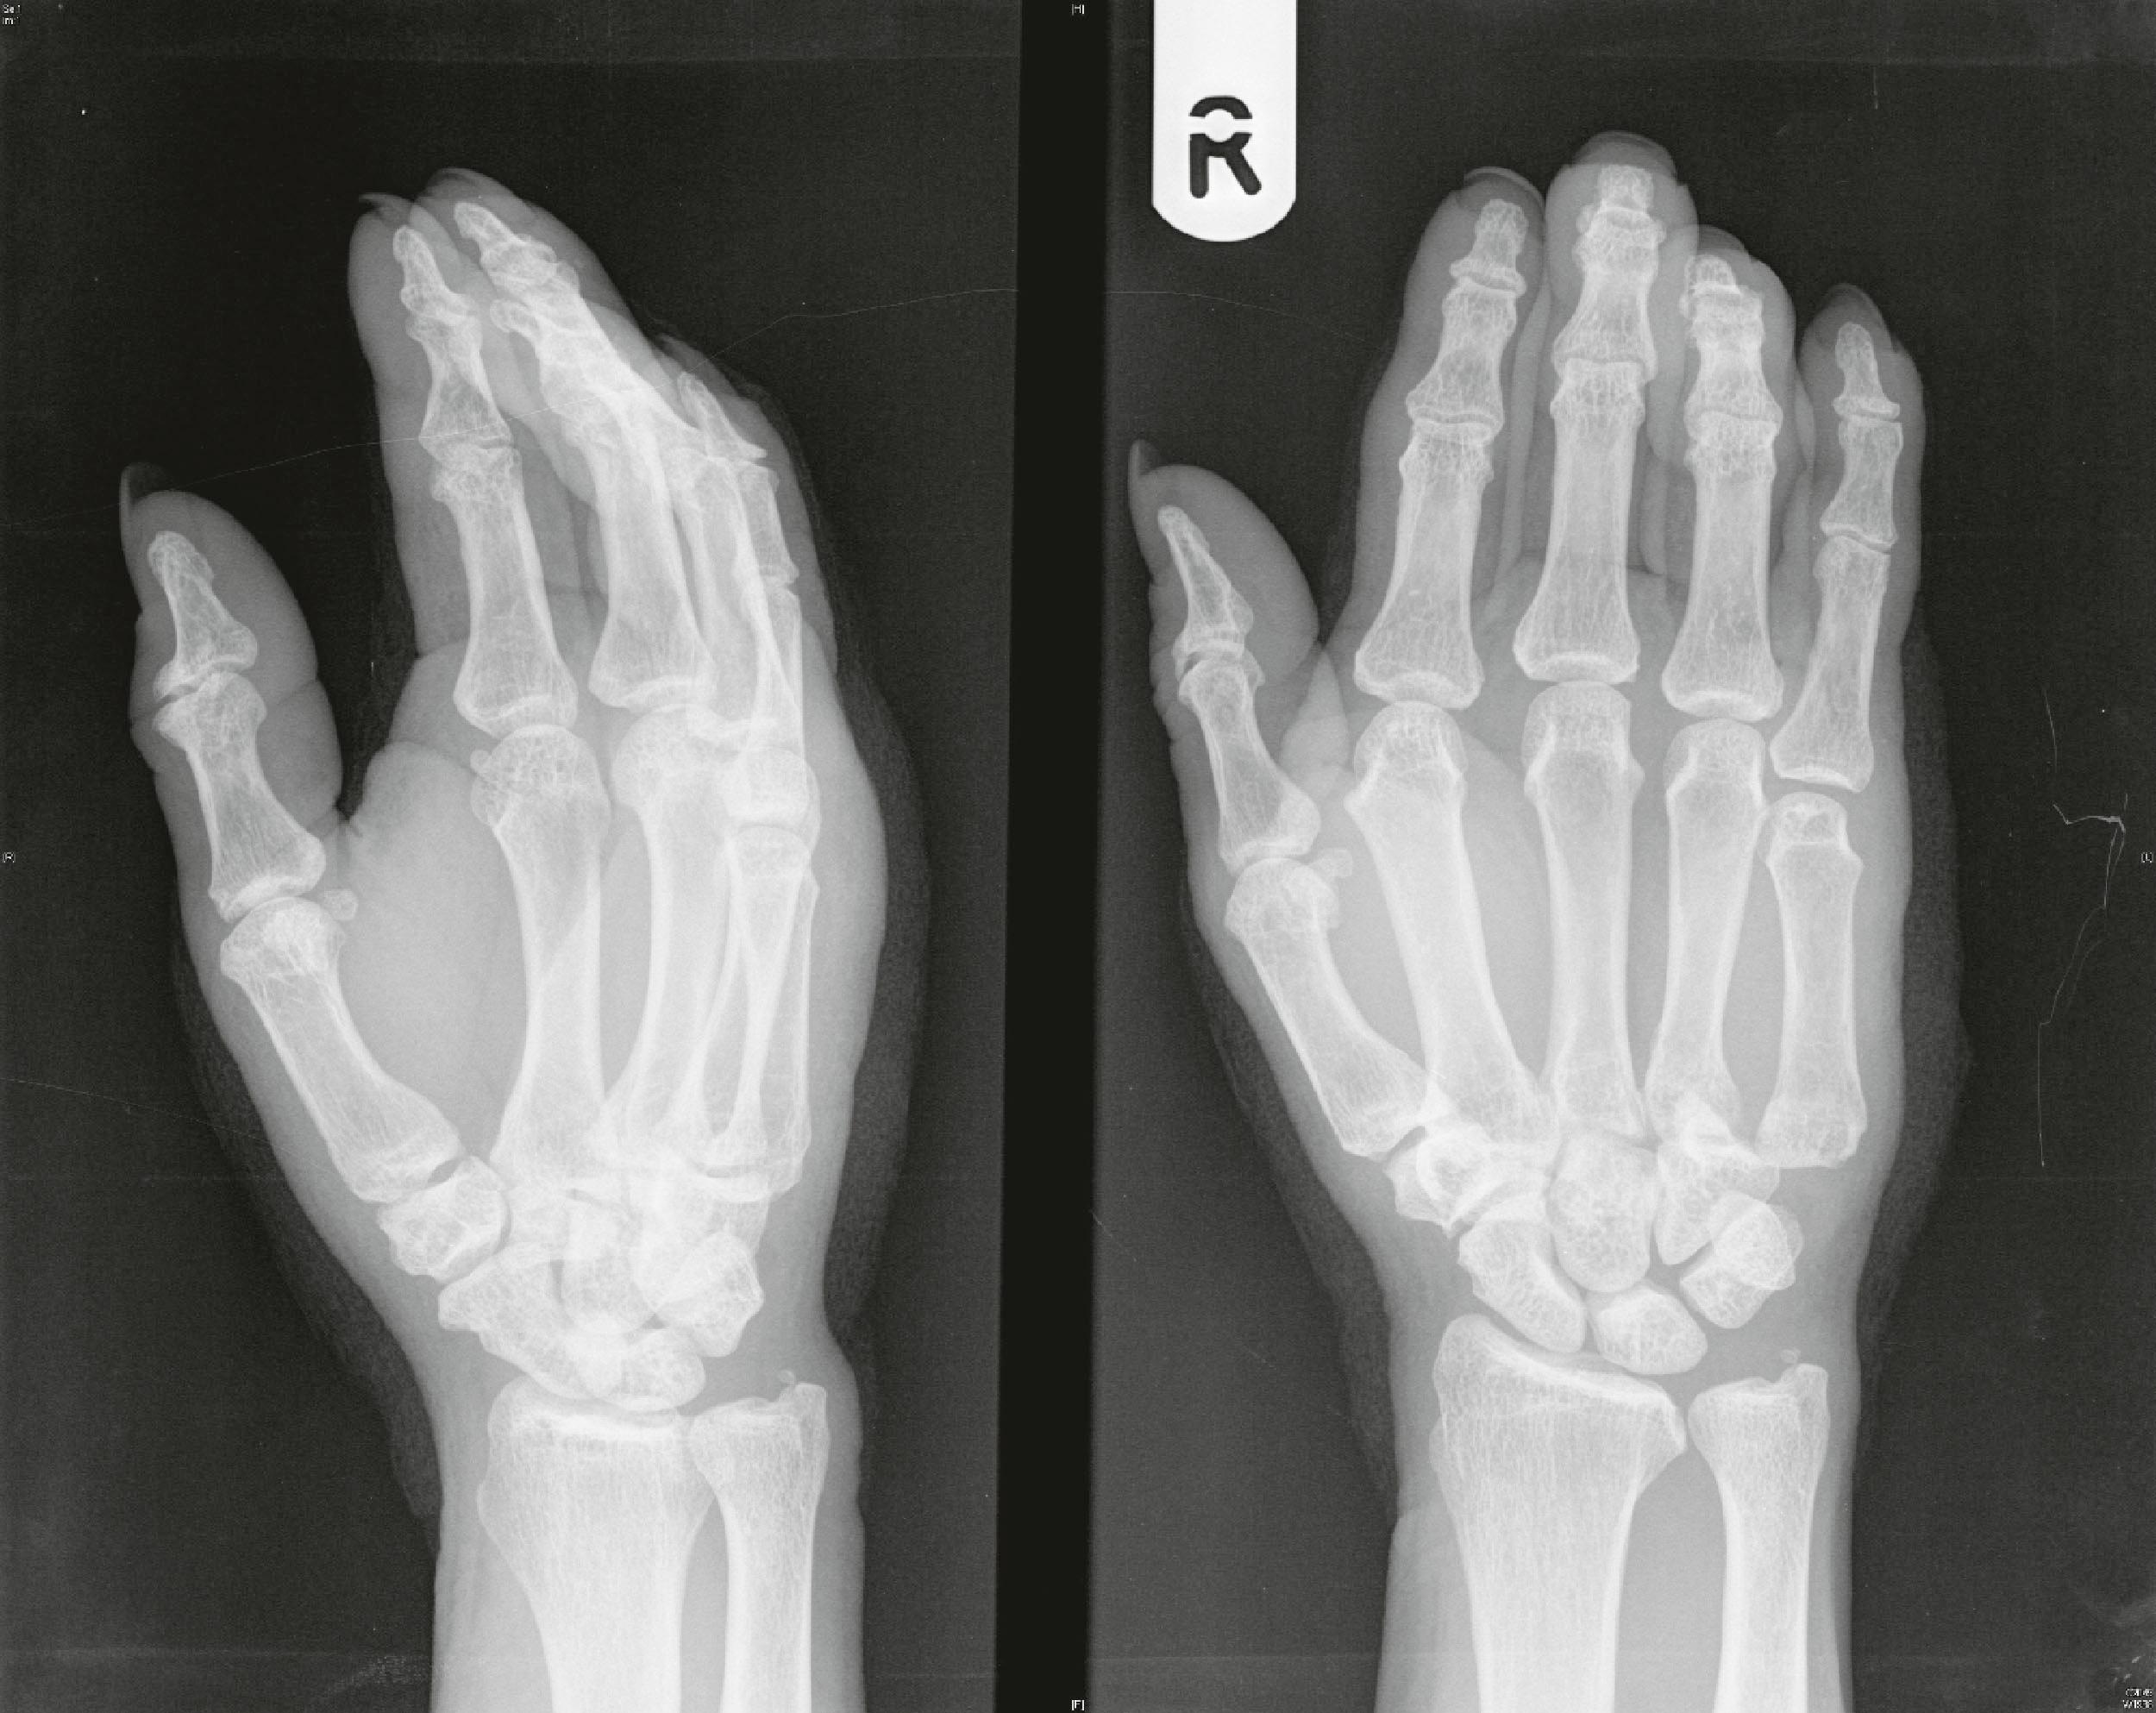
The hand is one of the most commonly imaged body parts in emergency departments and outpatient clinics. You'll see dozens of them in a shift. Most come back normal, which means your job is to confirm that quickly and not miss the one fracture hiding in plain sight. I've spent years reading these, and the hardest part isn't spotting the obvious break. It's staying systematic enough that you don't gloss over a subtle scaphoid fracture because you were already three scans deep. A standard hand series has three views: posteroanterior (PA), lateral, and oblique. That's it. Everything you need is in those three projections. I know some places add a dedicated scaphoid view or a CPA (carpal tunnel) view, but if you're in a busy department and those three are all you've got, you can still do this right. Start with the PA view. Look at the bones first, then the joints, then the soft tissues. That order matters more than people admit. When you scan randomly, your brain starts filling in gaps. I learned that the hard way early on when I missed a nondisplaced distal radius fracture because I was looking at the soft tissue swelling before tracing the cortical margins.
On the PA, check each phalanx, each metacarpal, and the carpal bones in order. There's a mnemonic most people learn: "Some Lovers Try Positions That They Can't Handle." Scaphoid, Lunate, Triquetrum, Pisiform, Trapezium, Trapezoid, Capitate, Hamate. Work through them left to right or right to left, just stay consistent. Miss one carpal bone and you're rolling the dice. The joints deserve their own pass. Look at the DIP joints, PIP joints, MCP joints, the CMC joints of the thumb, and the radiocarpal and midcarpal spaces. Joint space narrowing, erosions, or widening can all be significant. A widened joint space between the scaphoid and lunate on aPA view is a red flag for a ligamentous injury, even if the bones look fine. I once had a patient with persistent wrist pain and a normal-looking X-ray until I measured that scapholunate gap. It was 6mm on the affected side versus 2mm on the other. Perilunate instability, missed on the initial read by two other radiologists. The PA alone didn't scream pathology, but the measurement told the story. Move to the lateral view. This one is where alignment becomes critical. You should see the radius, lunate, and capitate stacked in a neat column. If that line of alignment is disrupted, something is wrong, usually a ligament tear or a fracture-dislocation. I've seen subtle dorsal intercalated segment instability (DISI) patterns that were easy to overlook if you weren't specifically checking the radiolunate angle. Normal is roughly 0 to 30 degrees of extension. Beyond that and you're looking at a scaphoid fracture or a ligament injury, even if you can't see the actual fracture line.
The oblique view is your safety net. It opens up the interosseous spaces and lets you see around the metacarpals and carpal bones without overlap. This is where you'll catch things like a Bennett's fracture at the base of the first metacarpal or a Rollander fracture. Both are intracapsular thumb fractures, and both are famously easy to miss if you're only looking at the PA and lateral. Soft tissues are not optional. Swelling in the anatomical snuffbox? That's your scaphoid warning sign. Soft tissue swelling over a joint without an obvious fracture could mean a ligament sprain or a septic joint. I had a case where the bones looked completely normal across all three views, but there was diffuse soft tissue swelling around the PIP joint of the third finger. The patient had a fever and couldn't move it. Turned out to be septic arthritis. The X-ray didn't show the infection, but it showed the downstream effect. Early on, that's all you get. One thing people don't tell you about normal hand X-rays: osteopenia changes everything. In a patient with significant demineralization, normal trabecular patterns disappear and fractures become nearly invisible on plain film. I dealt with a postmenopausal woman who fell on her outstretched hand and had a normal initial X-ray. Pain persisted. We did an MRI three weeks later and found a occult scaphoid fracture with early avascular changes. If you're reading hand X-rays in an osteopenic population, keep a low threshold for advanced imaging. Plain films have limits, and those limits are wider in weakened bone.
Get the Full Details

Another practical detail: position the hand correctly. PA views require the hand flat with fingers slightly spread and the wrist in slight extension. If the hand is rotated, the metacarpal heads won't overlay properly and you'll waste time wondering if a perceived abnormality is real or just a positioning artifact. I've spent extra minutes second-guessing a "widened" MCP joint only to realize the hand was internally rotated. Repositioned and it was normal. Don't skip quality control on the positioning. It saves headaches later. When you're confident the hand is normal, document it that way. "No acute fracture or dislocation. Normal alignment. No soft tissue abnormality." Clear and specific. Vague reports like "no acute osseous abnormality" without mentioning alignment or soft tissues leave too much room for interpretation. Clinicians reading your report want to know you actually looked at everything. The biggest pitfall I see, even among experienced readers, is pattern fatigue. After reading fifty normal hands in a row, your brain starts treating the fifty-first as normal by default. I combat this by deliberately varying my reading sequence. Some days I start with the soft tissues. Other days I trace the cortices bone by bone from proximal to distal. It's a small habit but it keeps your attention engaged. Automation is the enemy of accuracy here.
If you're learning to read hand X-rays, start with cases where the answer is known. Look at textbook atlases and case collections, then try reading them blind before checking the report. Compare your findings side by side. The gap between what you saw and what was reported is where you learn fastest. I still do this occasionally with complex trauma cases just to recalibrate my eye. Hand X-rays are straightforward in theory and deceptively difficult in practice. The anatomy is familiar, the views are standard, and most studies are normal. But the ones that aren't normal tend to be the subtle ones, the ones that hide behind overlapping bone or mild swelling that could be anything. Stay systematic, respect the positioning, and don't let volume make you complacent. That's really all there is to it.