What They Don't Tell You About Navigating CAMHS
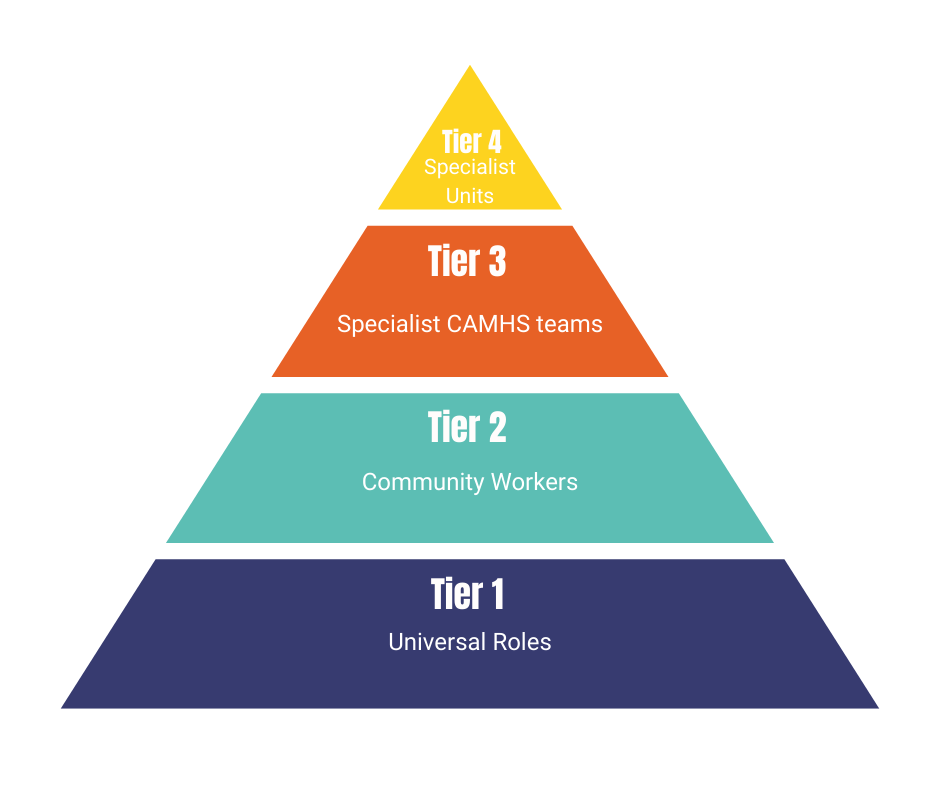
CAMHS referrals take an average of 6 to 12 weeks from initial contact to first assessment. Most parents and young people don't understand that the waiting period is often longer for higher-need cases because triage prioritizes acute risk over complexity. The system is structured around crisis management, not early intervention. I've spent over a decade working alongside these services, dealing with referrals, assessments, and the gaps that fall between them. The referral process itself is one of the most misunderstood parts. GPs send referrals, but they rarely explain what happens after that. The triage team decides which band you go into. Band 1 gets advice and signposting. Band 2 gets early intervention. Band 3 gets specialist care. Band 4 is for highly specialized or multi-agency cases. Most people land in Band 2 or 3 and wait. They don't realize that being in a lower band doesn't necessarily mean your case is less serious. It means it's being managed differently.
The Unspoken Truth What The Camhs System Fails To Teach
The biggest gap in everything CAMHS teaches families and even some frontline professionals is about documentation and self-advocacy. The system assumes a level of healthcare literacy that most people simply don't have. When you're referred, you should be receiving written confirmation within 72 hours. You should know your triage band, your estimated wait time, and who your point of contact is. Too often, people never get this information. I had a family come to me last year who had been waiting 14 months for a neurodevelopmental assessment. Their GP had sent the referral but never followed up. CAMHS hadn't contacted them once during that entire period. The workaround was straightforward: I helped them write a formal enquiry letter referencing the National Institute for Health and Care Excellence guidelines on waiting times, cited their specific referral date and GP practice, and sent it to the local clinical commissioning group's patient experience team. That triggered a response within five working days, and their assessment was rescheduled for three weeks later. Another thing nobody explains clearly is how CAMHS interfaces with other services. Schools, social care, adult mental health teams, pediatricians. These services operate in silos. Information sharing is theoretically governed by GDPR and local safeguarding protocols, but in practice it's inconsistent. I've seen cases where a child's risk assessment from social care was never passed to CAMHS, meaning therapists were making decisions without knowing the full picture. Conversely, I've seen CAMHS assessments sit in a school's file for months because no one knew who was responsible for transferring it when the child aged out. The transition process is perhaps the single most poorly handled part of the entire system. At 18, or sometimes 16 for certain cases, young people are moved from CAMHS to adult mental health services. This isn't a handover. It's often a cliff edge. Adult services have different criteria, different waiting lists, and different therapeutic approaches. Many young people who were stable in CAMHS deteriorate rapidly after transfer because nothing was planned beforehand. The rule is supposed to be that transition planning starts at age 14, but in reality, most transition letters arrive when the young person is already 17 or 18 and the CAMHS team is preparing to discharge them.
If you're dealing with CAMHS, here's what I'd suggest based on experience. Keep a personal timeline. Write down every phone call, every email, every name you speak to, and every date. This sounds tedious, but it becomes essential when you need to escalate something or prove that a service failed its duties. Request written communication whenever possible. If someone gives you information over the phone, send them an email afterward summarizing what was said and asking for confirmation. This creates a paper trail. Understand that CAMHS is not designed to be a comprehensive mental health service for young people. It's a specialist service for moderate to severe conditions. If someone has mild anxiety or low-grade depression, they'll likely be directed to talking therapies or left to manage it through primary care. That's not necessarily a bad outcome, but people often interpret it as dismissal when it's actually the system doing exactly what it's designed to do. If the concern is legitimate but below CAMHS threshold, ask your GP about IAPT services, school counseling provisions, or local youth mental health charities that may offer support while you navigate the formal system. The criteria for acceptance vary significantly between ICBs. One area might accept a 14-year-old with moderate depression for therapy within eight weeks, while a neighboring area might wait six months for the same presentation. There's no national standard that's consistently enforced. This means where you live matters enormously. If you're in an area with long waits and the situation is urgent, discuss with your GP whether a referral to a different integrated care board might be appropriate, though this is rarely straightforward and usually requires strong clinical justification.
Get the Full Details

Data accuracy within CAMHS is another quiet problem. I've encountered cases where a young person's diagnosis had been coded incorrectly in the system, which then affected their eligibility for certain interventions or educational adjustments. A miscode of a few letters could mean the difference between getting an education health and care plan or being told to speak to the local authority's general SEND team. Always check that the documentation held by your GP, the school, and CAMHS matches. If there's a discrepancy, request a records review in writing. Perhaps the most useful thing to understand is that CAMHS teams are often operating under capacity constraints that have nothing to do with the quality of care they provide. Staffing shortages, particularly in child psychiatry and psychological therapy roles, are widespread. This means even when your referral is accepted, the actual delivery of treatment may be fragmented. You might see one therapist for assessments, another for ongoing sessions, and a different person entirely if you need to be seen urgently. Consistency of caregiver is one of the most evidence-backed factors in positive outcomes for young people, and the system struggles to provide it. If you're supporting someone through this, the most practical thing you can do is help them prepare for appointments. Young people often freeze in clinical settings, especially when discussing difficult experiences. Having a written list of questions and key points beforehand, shared with the therapist in advance, makes a real difference. Some teams will accept a brief summary from a parent or advocate before the first session. It's worth asking.