Why Your Feet Are Breaking Down Everything Else
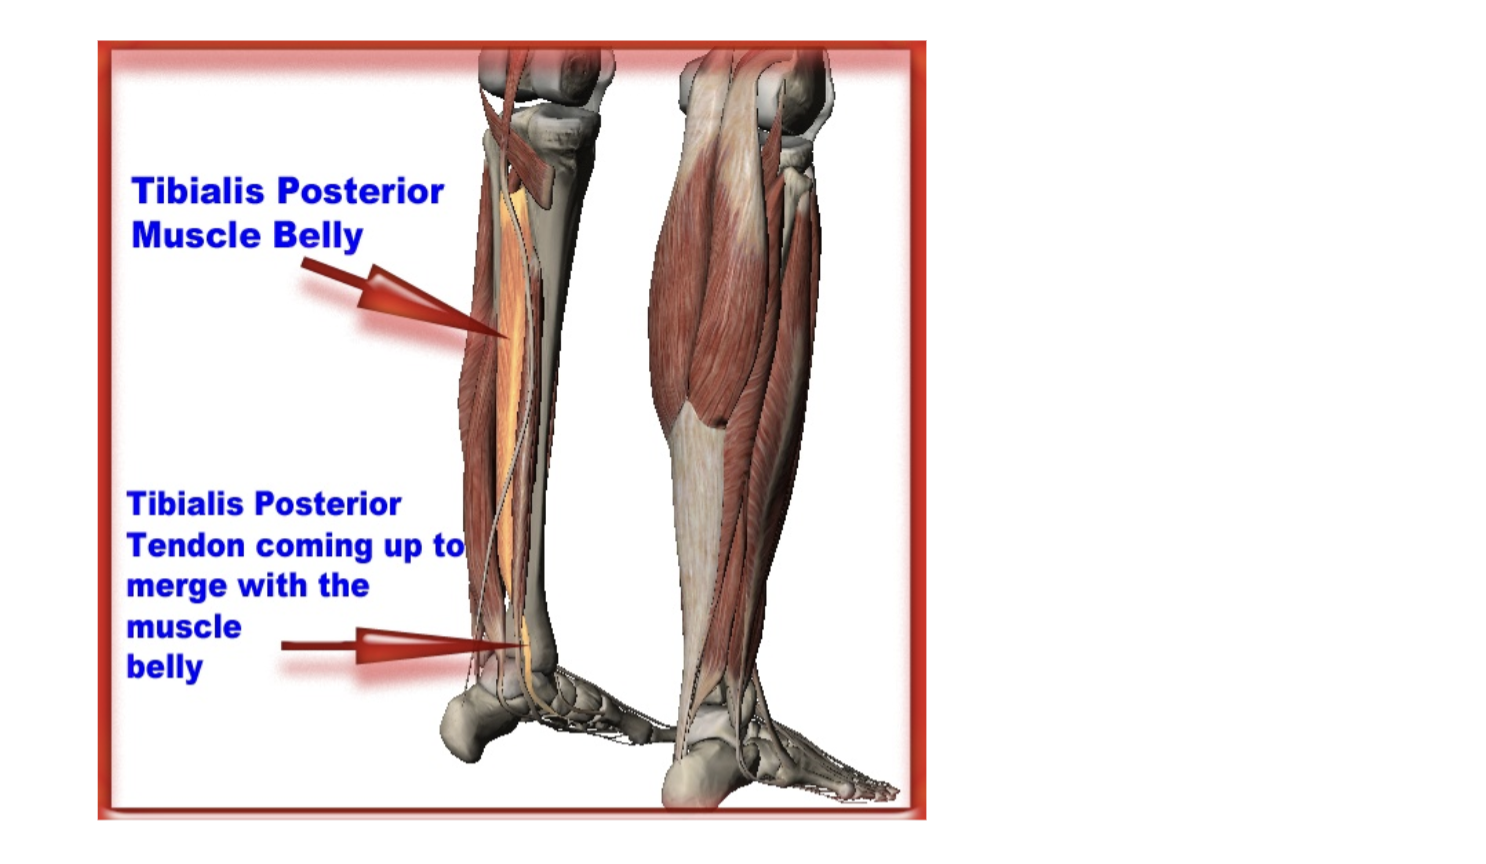
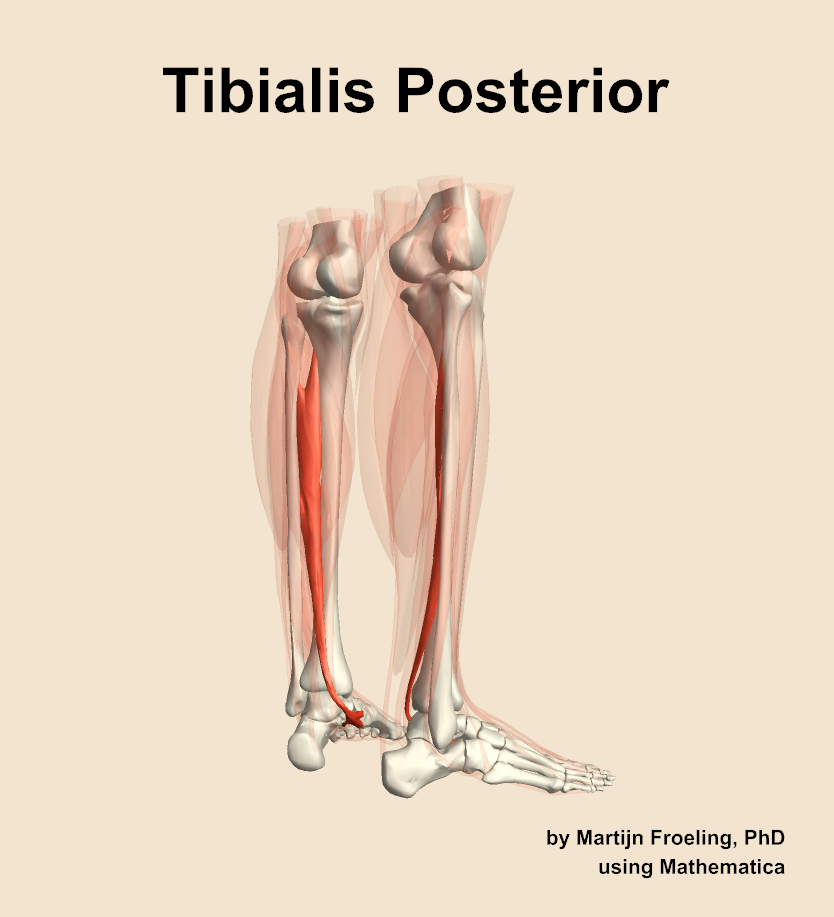
The tibialis posterior sits deep on the inside of your lower leg, running from just below the knee down to a cluster of bones in the midfoot. Most people have never heard of it. That's the point. It does its job in silence, holding your arch up, stabilizing the ankle, and keeping your lower extremity aligned. When it works, you notice nothing. When it fails, you start looking at everything except the right place. I spent years watching physical therapists and podiatrists chase symptoms up the chain — knee pain, hip pain, lower back pain — only to find the real culprit was a weakened tibialis posterior that had been silently misaligning the entire kinetic chain for months or years. Here is what most people miss about this muscle. The tibialis posterior isn't just an arch supporter. It is the primary invertor of the foot and a key plantarflexor. During normal gait, it fires eccentrically in mid-stance to control pronation. That means it lengthens under tension to prevent your arch from collapsing with every step. If it is weak or inhibited, your foot pronates excessively. Your tibia internally rotates. Your knee caves inward. Your hip compensates. Your lumbar spine follows. This is not theory. This is basic biomechanics that gets overlooked constantly.
I had a patient last year presenting with recurrent patellofemoral pain and what looked like a standard runner's knee pattern. Standard interventions — quad strengthening, IT band work, foam rolling — produced zero improvement after six weeks. I finally got her on an exam table, had her sit with legs dangling, and asked her to perform a single-leg heel raise. Her arch collapsed visibly on the left side. The tibialis posterior on that side was barely engaging. We spent three weeks targeting it directly with resisted inversion and eccentrics, added a temporary orthotic for support, and her knee pain dropped by about eighty percent without touching the knee itself. The working theory is sound: the muscle's influence on proximal joint tracking is far stronger than most clinicians account for. Here is the practical side. If you want to assess your own tibialis posterior function, stand barefoot and look at your medial arch from behind while bearing weight normally. Does the arch flatten significantly? Can you lift your big toe off the ground while keeping your other toes planted and your heel on the floor? If not, or if the movement is weak and shaky, the muscle is likely underperforming. Rebuilding it takes a specific sequence. Start with Isometrics: seated, cross your ankles so the affected foot is on top, press the sole of that foot into the opposite ankle and hold for thirty seconds. Three sets. Then eccentrics: single-leg heel raises with a slow three-count lowering phase, focusing on keeping the arch lifted the entire time. Ten reps, three sets daily. Progress to resisted inversion with a resistance band anchored to the outside of your foot, pulling the foot inward against resistance. Again, slow and controlled.
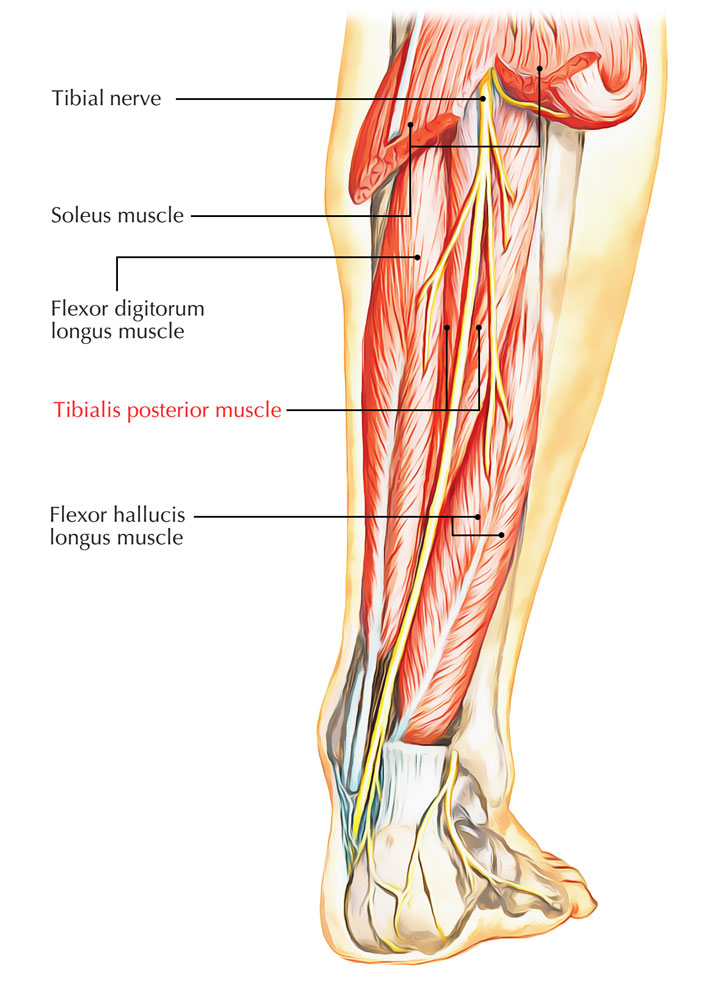
Footwear matters more than most people realize. Shoes with excessive cushioning and no structural support in the midfoot actually encourage the tibialis posterior to work harder because they remove proprioceptive feedback. Minimal shoes or barefoot work on safe surfaces can help retrain the muscle, but do not jump into that too fast. A sudden switch from heavily supported shoes to barefoot can overload the muscle and make things worse before they get better. There is a counterintuitive thing about aging and this muscle. People over forty often experience what we call adult-acquired flatfoot deformity, and the leading cause is tibialis posterior tendon dysfunction, not general wear and tear. The tendon thins, the muscle atrophies, and the arch progressively collapses. Once this reaches a certain stage, conservative treatment alone may not reverse it. Surgery becomes the only real option for restoring arch height. The early stages — and there is a window where intervention actually works — are frequently missed because the symptom is gradual. People assume their flat feet are just something they have always had, even if they did not. Another thing that catches people off guard: the tibialis posterior has a neural connection through the tibial nerve. If you have persistent calf tightness that does not respond to stretching, and you also notice reduced arch support, the issue might not be the calf at all. It could be neural tension referring through the tibial nerve. In those cases, nerve gliding exercises addressed earlier in the chain can produce faster results than direct muscle work. I learned this the hard way with a client who had spent two months aggressively stretching his calves with no change in arch stability. One session of proper tibial nerve mobilization and the arch support improved noticeably within days. That one was frustrating but instructive.
Get the Full Details
For public health reasoning, this is relevant because tibialis posterior dysfunction is underdiagnosed in primary care settings. People present with nonspecific foot or knee pain and get generic advice about rest and ice. A focused assessment of tibialis posterior strength and function during a routine visit would likely catch many of these cases earlier. The cost of an orthotic or a short course of targeted rehab is trivial compared to the downstream costs of corrected surgeries and chronic pain management that result from missed early intervention. If you are dealing with this yourself and the home program above produces no improvement after four weeks, or if you notice progressive flattening of the arch, swelling along the inside of the ankle, or pain that interferes with normal walking, seek a professional evaluation. There are imaging protocols — MRI and ultrasound — that can assess tendon integrity directly, and a podiatrist or sports medicine physician can give you a clear picture of where you are in the spectrum from dysfunction to tears.