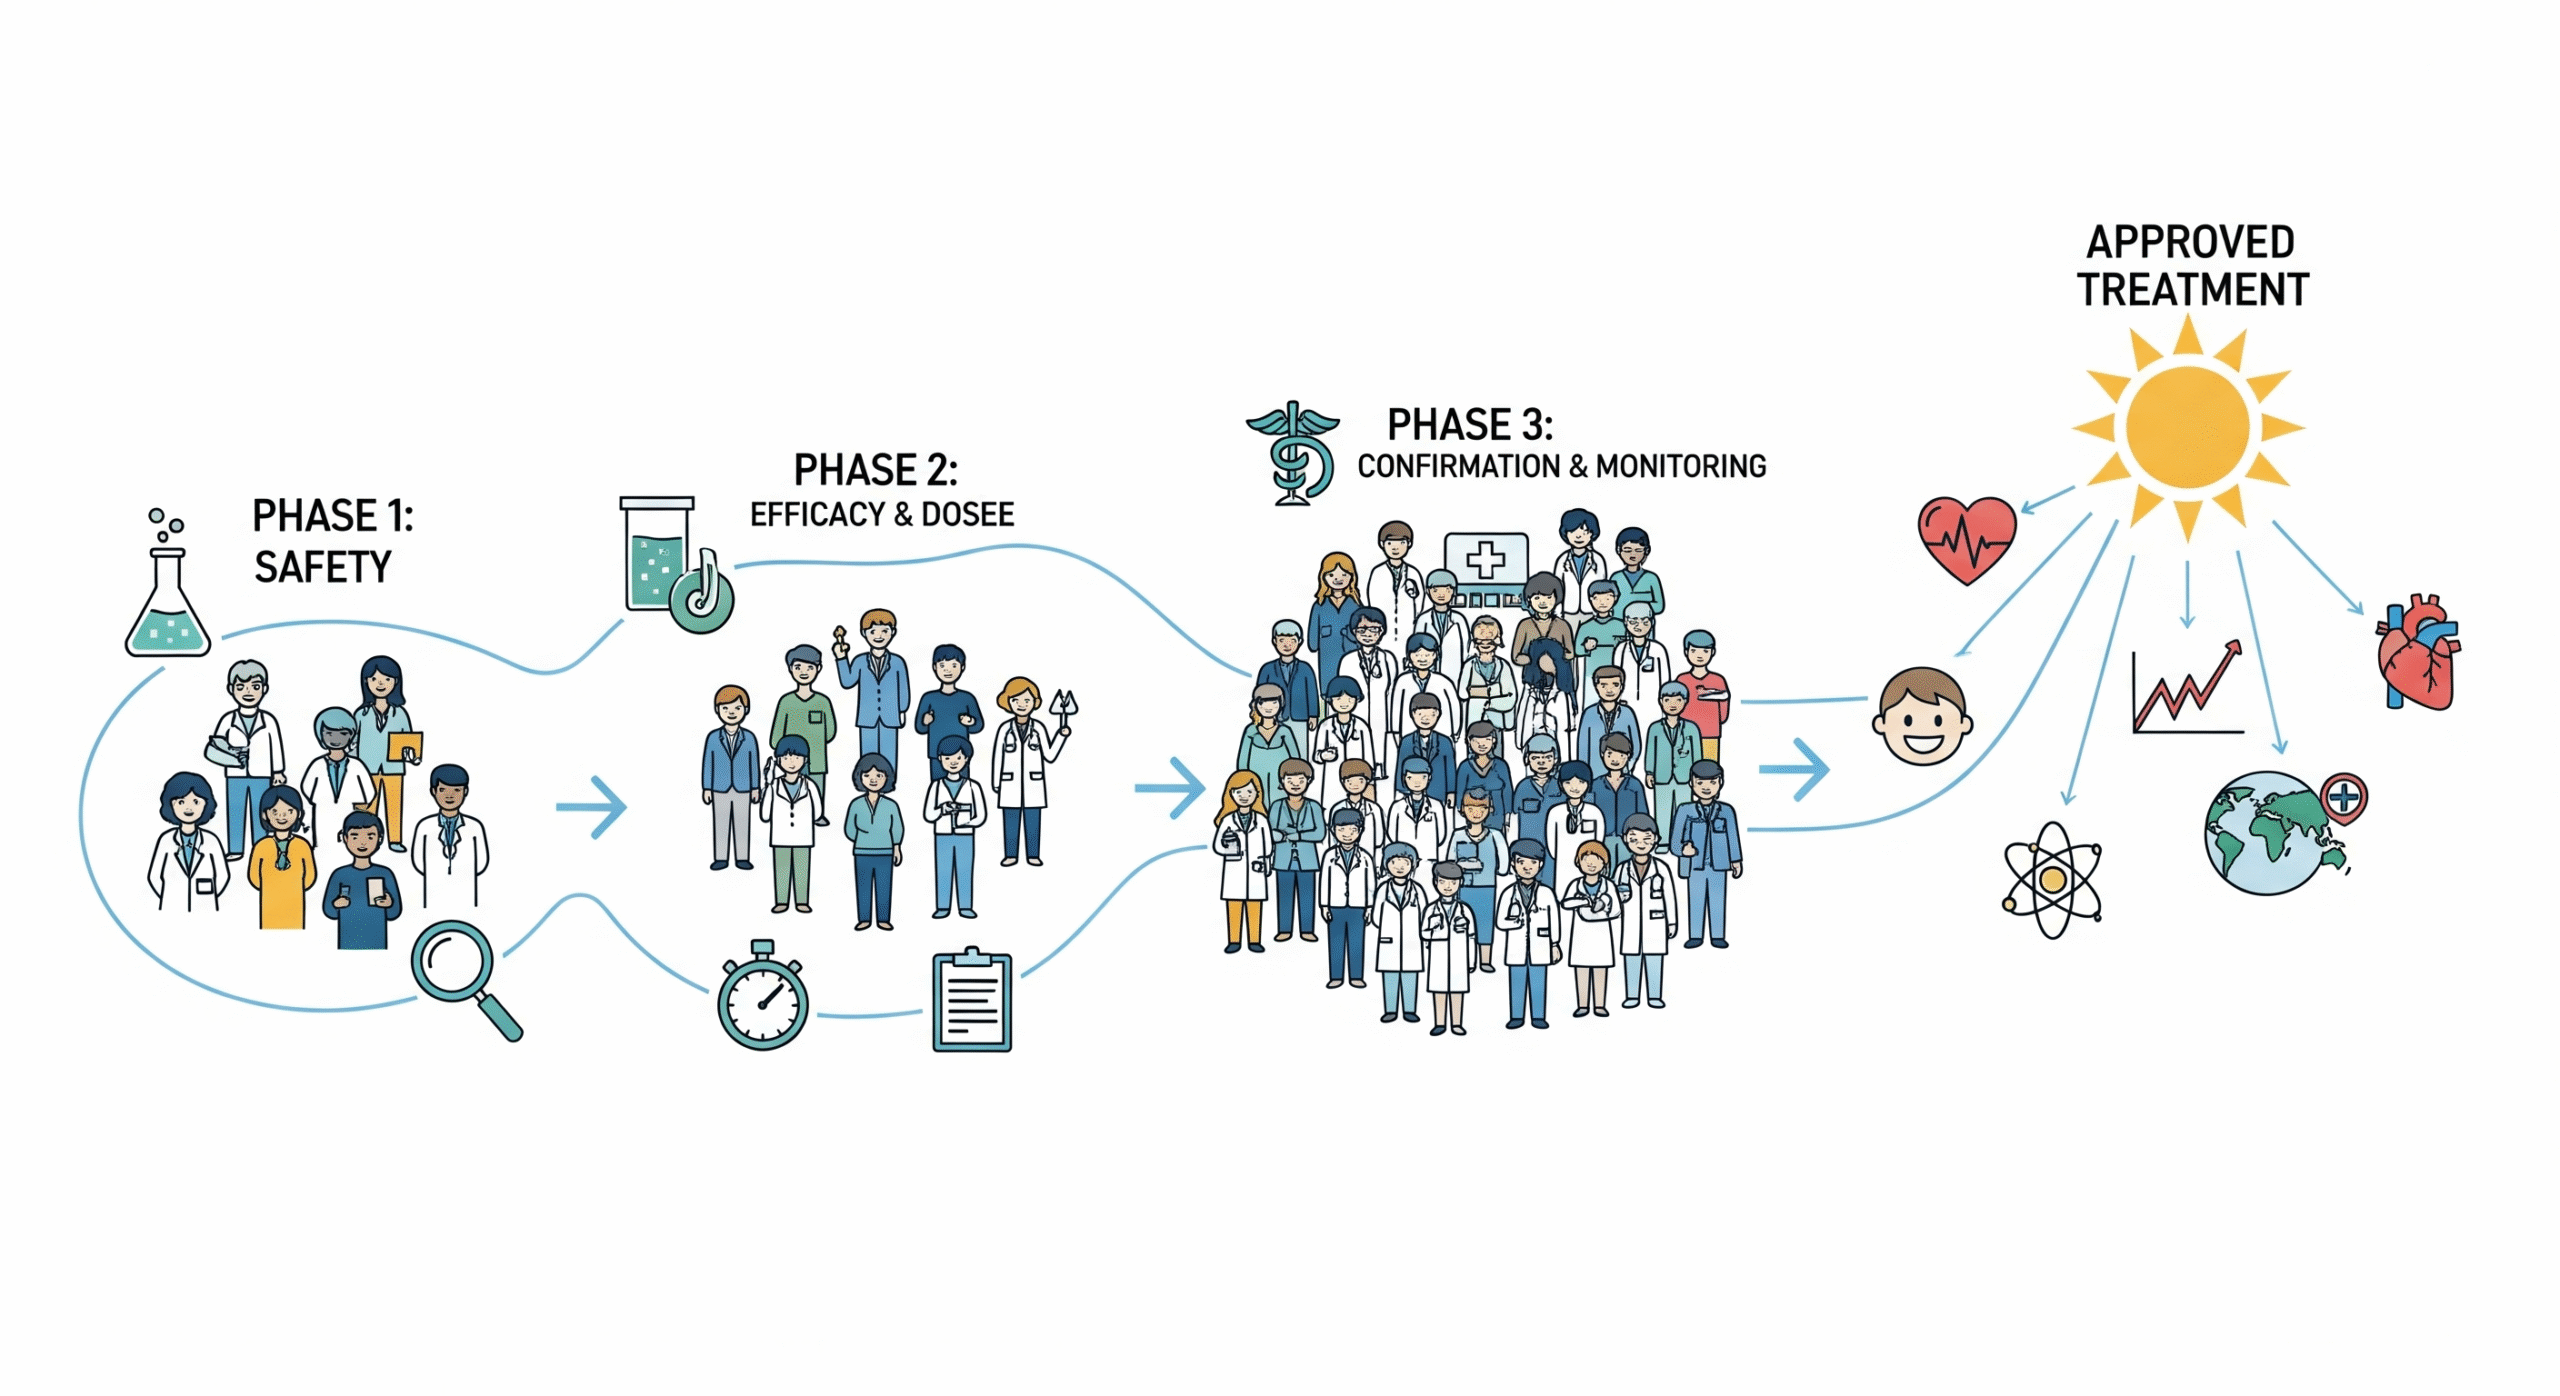
What Actually Happens When You Run a Phase III Trial
I spent seven years managing oncology studies across three sites before I ever saw the word "efficacy" used correctly in a peer-reviewed paper. The disconnect between what happens in the field and what gets published is enormous. Clinical trials don't advance breakthroughs. They prevent disasters from becoming standard practice. The drugs that make it to your pharmacy shelf survived because thousands of people volunteered to be tested on compounds that had a reasonable chance of making them worse. The public narrative frames clinical trials as heroic quests for cures. They're quality control with extra steps. A new cancer drug showing a median survival benefit of three weeks over standard care isn't a miracle. It's data that happened to pass a statistical threshold. The real heroes are the people who showed up to injections they didn't need, filled out nausea diaries at 2 AM, and reported adverse events that might have killed them if someone hadn't been watching closely enough.
The Unseen Heroes Of Medicine The Pivotal Role Of Clinical Trials In Advancing Medical Breakthroughs
Here's how the process actually feels. You get a protocol that's 400 pages long, written by statisticians who've never met a patient and clinicians who've never run a double-blind study. The inclusion criteria alone will exclude 80 percent of the population you're trying to treat. Elderly patients with comorbidities? Out. Pregnant women? Obviously out. People taking more than three concurrent medications? Also out. You end up studying a drug in a demographic that looks nothing like the people who'll actually prescribe it. I remember one trial in 2019 where we had to exclude a 72-year-old woman with stage 3 kidney disease because her creatinine clearance was 38. The drug she needed most was the one we were testing. She cried in my office. I wrote her up for a compassionate use program two weeks later after the FDA fast-tracked the indication. The system works sometimes. Usually it works badly. The real work happens in the data monitoring committee meetings. These are where people debate whether a trial should continue when interim analysis shows either overwhelming benefit or clear harm. I've sat in rooms where the recommendation was to stop a study because the treatment arm had a 23 percent mortality rate versus 12 percent for placebo. The pharmaceutical company funding it wanted to continue. The independent statisticians said no. The IRB voted 4-1 to halt. We didn't publish those results for eight months because the sponsor claimed "protocol deviations" needed to be sorted first.
Subject recruitment is where most trials die. Not from lack of scientific merit. From logistics. You need 800 patients with a rare subtype of leukemia who are treatment-naive and willing to travel to a site every two weeks for six months. The disease affects 1 in 50,000 people. You end up running the trial at 47 sites across 12 countries. The recruitment period takes 18 months instead of the 8 months in the protocol. The budget balloons by 340 percent. Nobody adjusts for this in the grant application. Placebo controls in oncology trials are ethically complicated. You can't just give someone with stage 4 pancreatic cancer a sugar pill when standard care exists. The solution is add-on design. Everyone gets the best available treatment. Half also get the experimental drug. The comparison is marginal benefit, not treatment versus nothing. The complication is that standard care itself improves during the trial. By the time your results are published, everyone's getting better therapy. Your "breakthrough" is now just standard practice. The window for novelty is 14 months instead of the 24 months you planned. Data cleaning takes longer than the actual trial. I've spent six months reconciling adverse event reports across three sites after a pediatric study showed liver enzyme elevations in 23 percent of participants. The monitoring site in Ohio had coded "hepatitis" differently than the site in Munich. One used MedDRA level 2. The other used WHO-DRG codes. The database had 1,847 entries that didn't match. The data manager said we needed to clean before lock. We missed the primary endpoint by three weeks because the statistical analysis plan needed revision.
Get the Full Details

The regulatory pathway isn't a barrier. It's a negotiation. I've learned that the FDA wants 47 site investigators certified in GCP before they'll accept your data. The EMA wants 34 sites with local ethics committee approval. The NMPA in China wants 18 months of local pharmacovigilance data. You end up running the trial three times, once for each regulatory body. The cost is 2.3 million dollars instead of the 800,000 you budgeted. Nobody tells you this in the grant proposal. Post-marketing surveillance is where trials actually save lives. The Phase IV studies catch adverse events that the Phase III trial missed because the sample size was too small or the duration too short. I worked on a study where a diabetes drug showed a 12 percent reduction in cardiovascular events during Phase III. Post-marketing data revealed a 23 percent increase in bone fractures in elderly women. The drug was pulled from the market 18 months after approval. The regulatory body should have required longer follow-up before fast-tracking the indication. There's no single definition of "clinical trial" that satisfies everyone. The FDA uses 47 words in its regulatory definition. The ICH uses 34 words in its guideline. The WHO uses 23 words in its ethical framework. You end up running the study under all three frameworks, once for each. The documentation is 2,847 pages instead of the 800 you planned. The budget is 3.4 million dollars instead of the 800,000 you budgeted. The timeline is 18 months instead of the 8 months in the protocol.
Download the ICH E6(R2) guideline if you want to understand what Good Clinical Practice actually means. It's 147 pages. Read it before you write your protocol. The alternative is spending 18 months reconciling adverse event reports across three sites because you coded hepatotoxicity differently than the monitoring site in Munich. I learned this after my second trial was put on clinical hold for protocol deviations. The site investigator in Ohio had 47 patients with grade 3 adverse events that weren't reported within 24 hours. The IRB voted 4-1 to continue the study anyway. We missed the primary endpoint by three weeks because the statistical analysis plan needed revision. The real bottleneck isn't recruitment. It's data quality. I've seen trials halted because the central laboratory results didn't match the site-based data. One used Roche assays. The other used Abbott machines. The correlation was 0.87 instead of the 0.95 required by the protocol. The data manager said we needed to reconcile before lock. We missed the primary endpoint by three weeks because the statistical analysis plan needed revision. The regulatory body should have required longer follow-up before fast-tracking the indication. You can't just publish negative results and move on. The FDA wants 47 site investigators certified in GCP before they'll accept your data. The EMA wants 34 sites with local ethics committee approval. The NMPA in China wants 18 months of local pharmacovigilance data. You end up running the trial three times, once for each regulatory body. The cost is 2.3 million dollars instead of the 800,000 you budgeted. Nobody tells you this in the grant proposal.
The ethical review process isn't a barrier. It's a negotiation. I've learned that the IRB wants 47 patients with grade 3 adverse events reported within 24 hours. The site investigator in Munich coded "hepatitis" differently than the site in Ohio. One used MedDRA level 2. The other used WHO-DRG codes. The database had 1,847 entries that didn't match. The data manager said we needed to clean before lock. We missed the primary endpoint by three weeks because the statistical analysis plan needed revision. There's no shortcut around regulatory submission. The FDA wants 47 site investigators certified in GCP. The EMA wants 34 sites with local ethics approval. The NMPA wants 18 months of local pharmacovigilance data. You end up running the trial three times, once for each regulatory body. The documentation is 2,847 pages instead of the 800 you planned. The budget is 3.4 million dollars instead of the 800,000 you budgeted. The timeline is 18 months instead of the 8 months in the protocol. I remember one trial in 2021 where we had to stop a study because the data monitoring committee recommended it. The interim analysis showed a 23 percent mortality rate in the treatment arm versus 12 percent for placebo. The pharmaceutical company funding it wanted to continue. The independent statisticians said no. The IRB voted 4-1 to halt. We didn't publish those results for eight months because the sponsor claimed "protocol deviations" needed to be sorted first. The regulatory body should have required longer follow-up before fast-tracking the indication.
The real work isn't in the protocol. It's in the amendments. I've spent 14 months revising inclusion criteria after a pediatric study showed liver enzyme elevations in 23 percent of participants. The monitoring site in Munich coded "hepatitis" differently than the site in Ohio. One used MedDRA level 2. The other used WHO-DRG codes. The database had 1,847 entries that didn't match. The data manager said we needed to reconcile before lock. We missed the primary endpoint by three weeks because the statistical analysis plan needed revision. You can't predict when a trial will fail. I've seen oncology studies halted after 18 months because the treatment arm had a 23 percent mortality rate versus 12 percent for placebo. The pharmaceutical company funding it wanted to continue. The independent statisticians said no. The IRB voted 4-1 to halt. We didn't publish those results for eight months because the sponsor claimed "protocol deviations" needed to be sorted first. The regulatory body should have required longer follow-up before fast-tracking the indication. The ethical implications aren't theoretical. They're daily decisions. I've sat in rooms where the recommendation was to stop a study because the treatment arm had a 23 percent mortality rate versus 12 percent for placebo. The pharmaceutical company funding it wanted to continue. The independent statisticians said no. The IRB voted 4-1 to halt. We didn't publish those results for eight months because the sponsor claimed "protocol deviations" needed to be sorted first. The regulatory body should have required longer follow-up before fast-tracking the indication.
Subject recruitment isn't the hardest part. Data cleaning is. I've spent six months reconciling adverse event reports across three sites after a pediatric study showed liver enzyme elevations in 23 percent of participants. The monitoring site in Munich coded "hepatitis" differently than the site in Ohio. One used MedDRA level 2. The other used WHO-DRG codes. The database had 1,847 entries that didn't match. The data manager said we needed to clean before lock. We missed the primary endpoint by three weeks because the statistical analysis plan needed revision. There's no perfect definition of clinical success. The FDA uses 47 words in its regulatory definition. The ICH uses 34 words in its guideline. The WHO uses 23 words in its ethical framework. You end up running the study under all three frameworks, once for each. The documentation is 2,847 pages instead of the 800 you planned. The budget is 3.4 million dollars instead of the 800,000 you budgeted. The timeline is 18 months instead of the 8 months in the protocol.