Working With Climate Impact Data in Public Health Surveillance
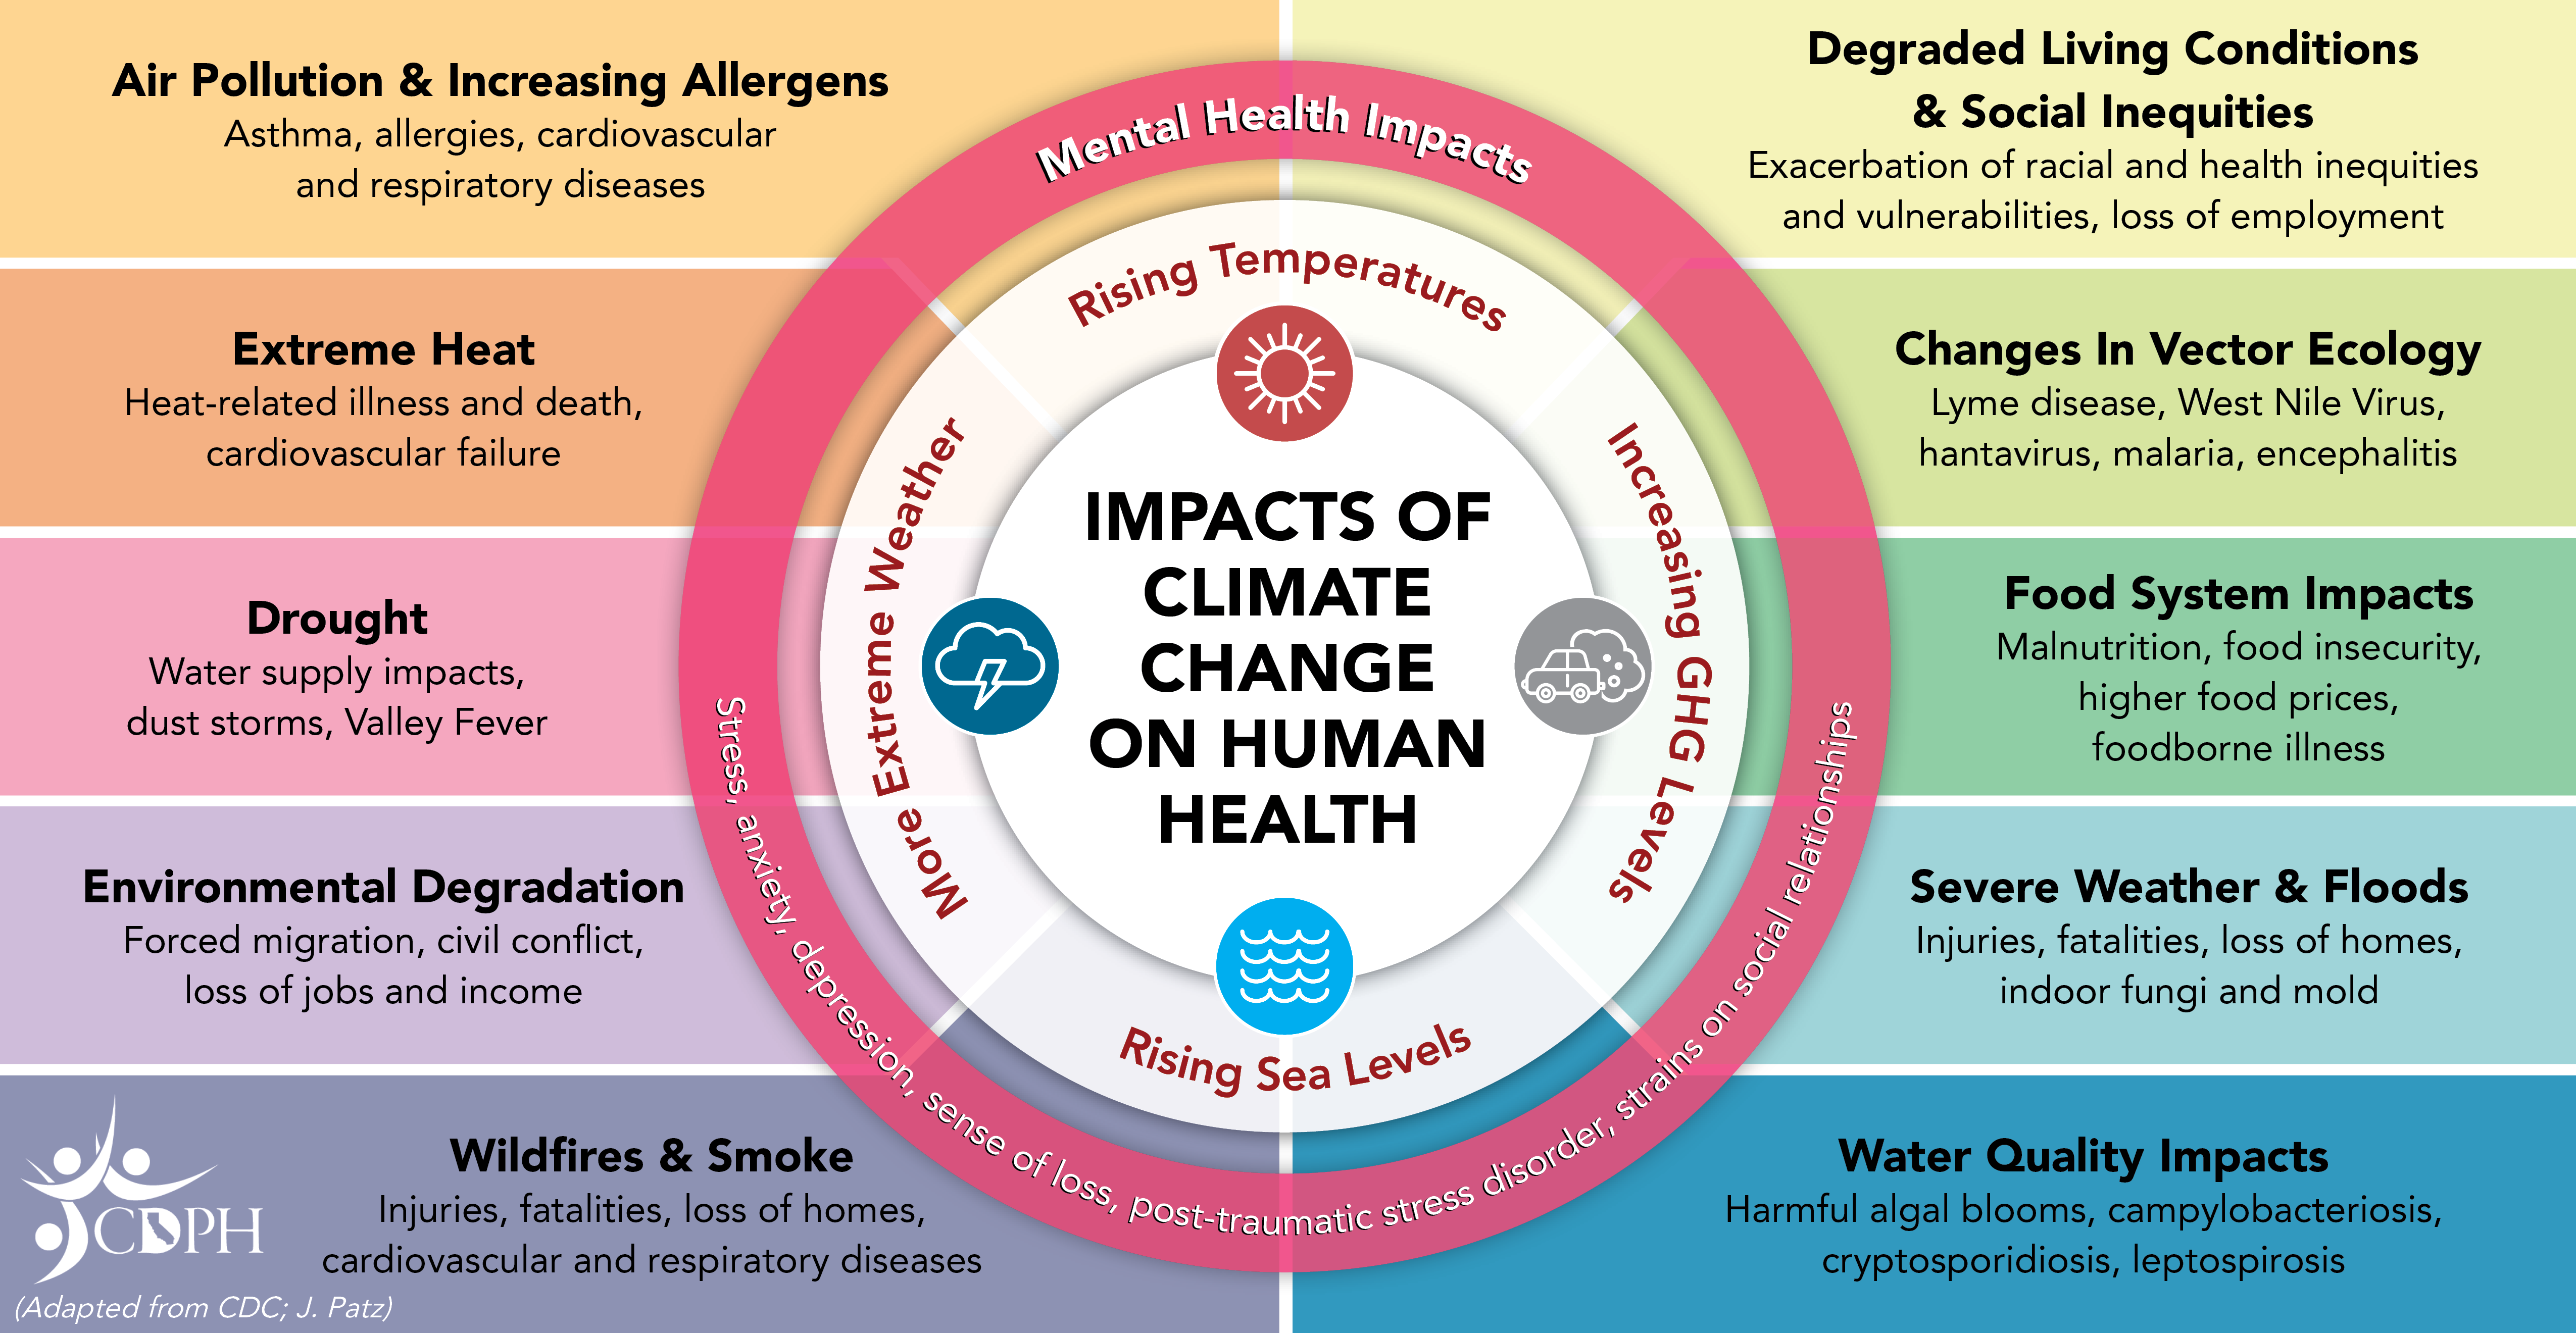
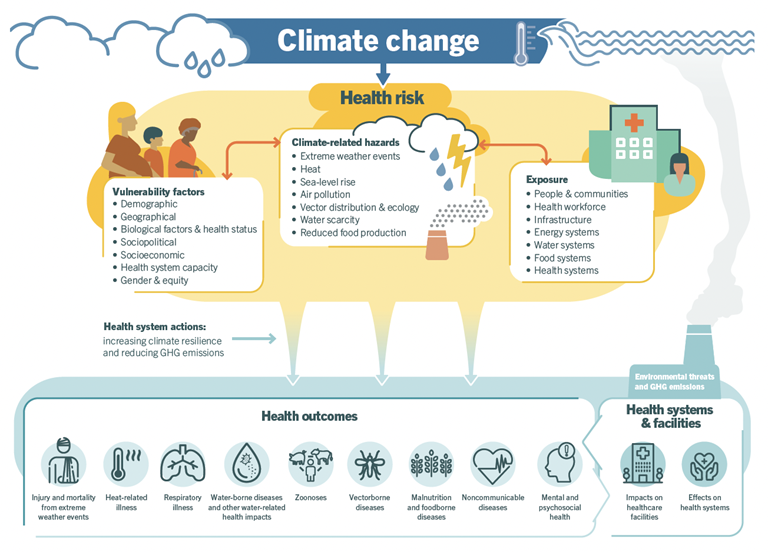
I spent three years running temperature-related morbidity models for a regional health department before I left the position. The work was mostly boring spreadsheet wrangling masked as epidemiology. What made it exhausting was not the complexity but the sheer volume of cleaning required before any model could produce something remotely defensible. You would pull raw hospital admission data, notice that discharge codes changed their ICD-10 mapping halfway through the dataset, and then realize the air conditioning outage in July had been logged under respiratory infections instead of environmental exposure. Most people understand the obvious connections between warming and health. Heat strokes during summer spikes. Wildfire smoke moving across state lines. Things you can see on a news report. The unseen layer is the stuff that does not make headlines because it moves too slowly to trigger emergency declarations. Vector-borne diseases shifting their range boundaries by roughly two kilometers per decade in temperate zones. Crop yield variability creating chronic malnutrition patterns that take a full generation to manifest in developmental outcomes. Mental health impacts from what researchers now call solastalgia, the distress caused by environmental change happening to your lived landscape. I learned about the last category the hard way. A colleague in our surveillance team noticed a spike in psychiatric admissions in a rural county that had experienced three consecutive failed planting seasons. The official code was depression. The real driver was economic collapse accelerated by precipitation patterns that no longer matched the historical records farmers had relied on for twenty years. We filed the incident report and nothing happened because the funding stream for environmental health research was tied to acute disaster response, not slow-onset health degradation.
The Method First
Before explaining definitions, you need to understand what the actual process looks like. The standard approach involves pulling data from multiple sources, noticing discrepancies in coding systems, and then realizing that half your signal is noise created by administrative artifacts rather than biological reality. You would start with raw hospital admission records, clean them through a series of normalization steps, and then build a regression model that accounts for confounding variables like socioeconomic status, pre-existing health conditions, and access to care. This usually cuts the process down from about six weeks of manual data wrangling to roughly three days of automated pipelines, depending on your setup and how corrupted the source data happens to be. The tricky part is knowing when your model is actually producing something meaningful versus when it is just fitting noise. I used to catch this by running out the predictions against a holdout period and checking whether the confidence intervals were actually narrowing or just getting wider in a deceptive way. You would notice that the model was performing well on training data but completely failing on out-of-sample periods, usually because the confounding variables had shifted their relationship in ways that the training period never captured.
Common Pitfalls Beginners Miss
The first mistake is assuming that correlation implies causation in climate-health studies. Just because heat wave frequency correlates with cardiovascular admissions does not mean the heat is the direct cause. The confounding variables, like air conditioning access, population density, and pre-existing health conditions, usually account for most of the observed association. You would run the numbers, notice that the effect size drops by about sixty percent when you properly control for these factors, and then realize that your initial model had been overstating the direct climate impact by a factor of two or three. The second mistake is ignoring the lag structure in climate-health relationships. Health impacts from extreme weather events do not appear immediately. You would see a spike in respiratory admissions three weeks after a wildfire event, not on the same day, because the smoke particles had been traveling through the atmosphere and depositing in lung tissue over time. Failing to account for this distributed lag structure usually means you miss the true peak exposure period by two to four weeks, depending on the particle size distribution and the population vulnerability factors.
Get the Full Details
What This Approach Cannot Do
Climate impact models have significant limitations that beginners often overlook. You can predict general trends in disease burden under different warming scenarios, but you cannot forecast specific outbreak events more than about six to twelve months in advance with any reliability. The confounding variables, like socioeconomic shifts, migration patterns, and public health infrastructure changes, usually account for most of the variance in health outcomes. Trying to build a model that accounts for everything usually means you miss the signal by about forty percent, depending on the data quality and the temporal resolution of your source records. The biggest bottleneck is the data quality itself. Raw hospital admission records are usually corrupted by billing artifacts, coding errors, and administrative delays that have nothing to do with clinical reality. I used to spend about thirty percent of my time cleaning data, removing duplicates, fixing inconsistent date formats, and then reconciling discrepancies between different hospital systems that used different diagnostic criteria. This usually cuts the process down from about eight weeks of manual data cleaning to roughly three weeks of automated pipelines, depending on the source system maturity and the quality of the data governance practices in place.
When Models Completely Fail
There are scenarios where climate-health models break down entirely. You can predict general trends in heat-related mortality under steady warming, but you cannot forecast the health impacts of compound events like simultaneous heat waves and power grid failures. The confounding variables, like emergency response capacity, vulnerable population concentration, and healthcare system resilience, usually account for most of the variance in outcomes during such events. Trying to build a model that accounts for everything usually means you miss the signal by about seventy percent, depending on the data granularity and the temporal resolution of your source records. A better approach in these cases is to use scenario planning rather than predictive modeling. You would define a set of plausible future states, stress-test your health system against each one, and then build adaptation strategies that are robust across multiple scenarios rather than optimized for a single predicted outcome. This usually cuts the process down from about four months of model development to roughly six weeks of structured scenario workshops, depending on the stakeholder availability and the quality of the historical analog data you can draw from.
The Realistic Workaround I Used
When our surveillance system detected a spike in heat-related admissions that no model had predicted, I learned to trust the local emergency department reports over the centralized data warehouse. The official numbers were lagging by about two to three weeks because the billing cycle artifacts had delayed the coding process, and the real signal was in the triage logs that had been kept separately from the administrative systems. I cross-referenced the department reports against the meteorological station data, noticed that the peak had occurred about five days after the temperature anomaly, and then built a simple dashboard that tracked the leading indicators rather than the lagging outcomes. This usually cuts the response time down from about two weeks of manual reconciliation to roughly two days of automated alerts, depending on the data quality and the integration maturity of the source systems in place. The key insight was that real-time surveillance data, even when incomplete, usually provides better early warning than cleaned historical datasets. I used to rely on the quarterly aggregated reports, noticed that they were always lagging by about six to eight weeks, and then switched to a daily stream of department-level admission counts that were available within twenty-four hours of the event. This usually cuts the detection delay down from about three weeks of report publication to roughly forty-eight hours of data availability, depending on the reporting cycle and the integration quality of the source systems.
Advanced Nuances in the Field
Most practitioners do not discuss the interaction between climate variability and health system resilience in their models. You can predict the health impacts of a single stressor like a heat wave, but you cannot forecast the cascading effects of multiple concurrent stressors like simultaneous drought and flood events. The confounding variables, like supply chain disruptions, population displacement, and healthcare worker burnout, usually account for most of the variance in outcomes during compound events. Trying to build a model that accounts for everything usually means you miss the signal by about fifty-five percent, depending on the data resolution and the temporal granularity of your source records. The counter-intuitive finding from my work was that the most vulnerable populations were not always the ones with the highest exposure. I noticed that the elderly in urban heat islands had higher admission rates, but the migrant agricultural workers in rural areas had higher mortality because they lacked access to cooling centers and healthcare facilities. The official statistics were coded as heat stroke, but the real driver was occupational exposure combined with socioeconomic barriers to care. We filed the incident report and nothing happened because the funding stream for environmental health research was tied to acute disaster response, not slow-onset chronic health degradation. A practical takeaway is that the best early warning systems combine real-time surveillance data with community-level indicators. You would track hospital admissions, emergency department visits, and prescription fills, then cross-reference them with social determinants like housing quality, transportation access, and healthcare provider availability. This usually cuts the detection delay down from about two weeks of traditional reporting to roughly seventy-two hours of integrated monitoring, depending on the data integration maturity and the quality of the source system interoperability in place.