The Brainstem Structures You Never Think About Until Something Breaks
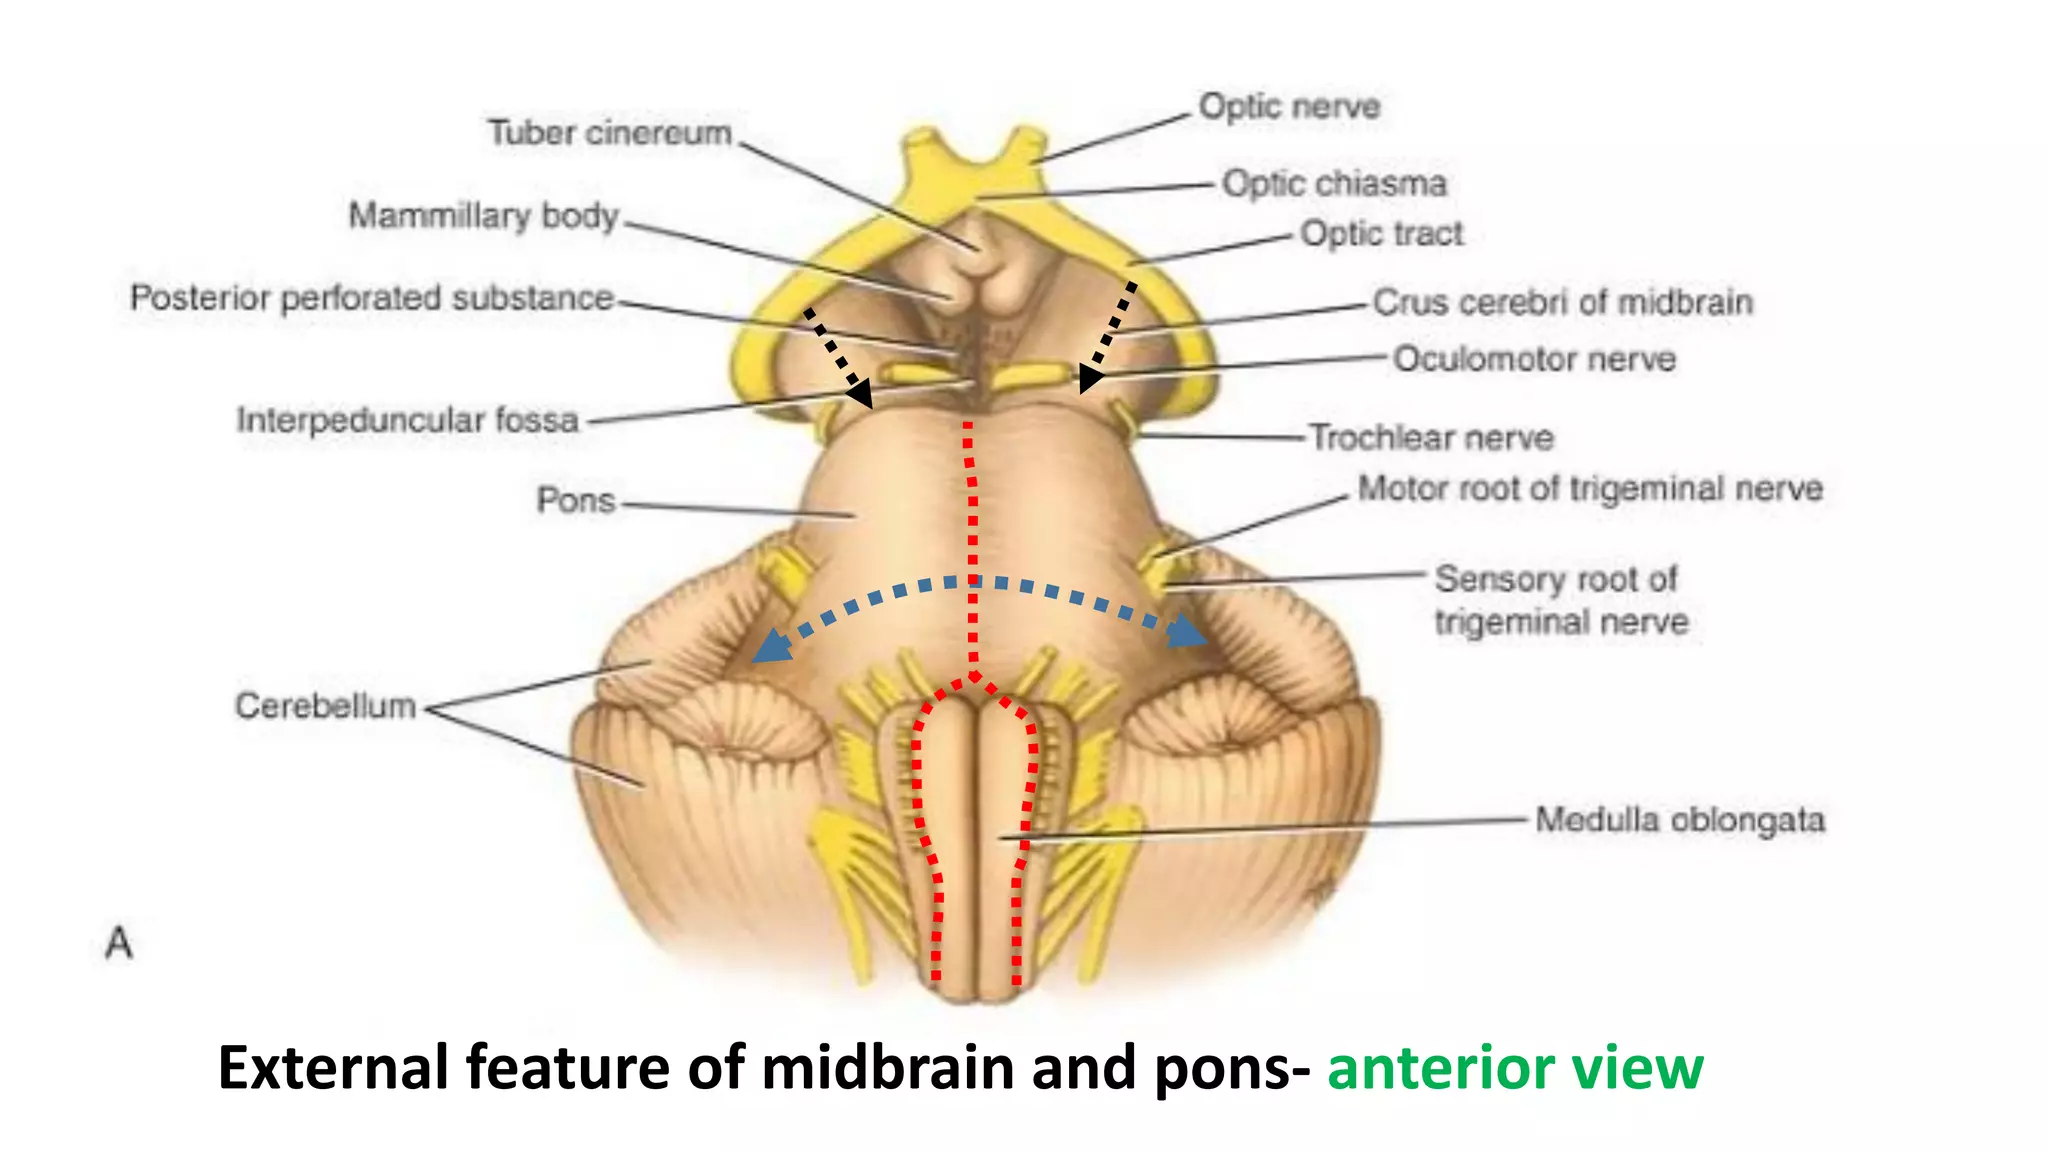
The pons and medulla oblongata sit right where the midbrain transitions into the spinal cord, forming what most textbooks call the brainstem. They handle automatic breathing, heart rate regulation, sleep cycles, and basic motor coordination without your conscious involvement. I spent three years working with neurocritical care patients before I fully understood how these structures actually function in real clinical scenarios, and even now I encounter cases that remind me how little we truly understand about their compensatory mechanisms. Most people learn about these structures in introductory biology classes and then never think about them again. The pons acts as a relay station, connecting the cerebral cortex to the cerebellum while also housing nuclei that control facial movements, hearing, and balance. The medulla handles vomiting reflexes, coughing, swallowing, and the automatic regulation of breathing patterns. Together they maintain homeostasis through complex feedback loops involving chemoreceptors and baroreceptors throughout the body. I encountered a patient once who had a small brainstem stroke affecting only the paramedian pons. Standard imaging missed it initially because the lesion was too small and located in a region where artifact from the petrous bones obscures detail on routine CT scans. The presenting symptom was subtle - slight difficulty with eye movement coordination and mild balance issues that the patient attributed to fatigue. It took a dedicated MRI with thin cuts through the brainstem and comparison with prior imaging to confirm the diagnosis. This case taught me that when clinical presentation suggests brainstem involvement but initial imaging is negative, you should not accept the negative result at face value.
The reticular formation within these structures deserves more attention than it receives. This network of neurons extends from the medulla through the pons into the midbrain, and it regulates consciousness, sleep-wake transitions, and attention. Damage to specific areas can produce locked-in syndrome, where patients remain fully conscious but cannot move or speak due to disruption of motor pathways. I have worked with families of locked-in patients, and the emotional complexity of communicating with someone who is awake and aware but completely paralyzed requires patience and specialized assistive technology. Blood supply to the pons and medulla comes from multiple sources - the basilar artery supplies the pons through penetrating branches, while the vertebral arteries give rise to the anterior and posterior spinal arteries that feed the medulla. This vascular arrangement creates vulnerabilities. A basilar artery thrombosis can be fatal because it affects such critical functions, yet the clot may not be detected until significant brainstem damage has occurred. The posterior circulation stroke remains underdiagnosed in emergency settings, partly because symptoms like dizziness and imbalance are nonspecific and overlap with many benign conditions. Clinical examination of these structures involves testing cranial nerves that originate from or synapse within the pons and medulla. The sixth nerve controls lateral eye movement, the seventh controls facial expression, the eighth affects hearing and balance, and the ninth and tenth manage swallowing and gag reflex. When examining a patient with altered consciousness, the presence or absence of brainstem reflexes determines prognosis more accurately than Glasgow Coma Scale scores alone. The pupillary light reflex, corneal reflex, and oculocephalic response provide rapid assessments of brainstem integrity at the bedside.
Sleep research has revealed that the pons plays a crucial role in REM sleep generation. The pontine tegmentum contains neurons that trigger the muscle atonia characteristic of REM sleep, preventing you from acting out your dreams. Disruption of this mechanism produces REM sleep behavior disorder, where patients physically act out vivid dreams and can injure themselves or their partners. I have treated several patients with this condition, and the treatment typically involves clonazepam or melatonin, though neither addresses the underlying neurodegenerative process that often accompanies it. The medulla contains the dorsal and ventral respiratory groups, which generate the basic rhythm of breathing. Chemoreceptors in the medulla monitor carbon dioxide levels in the blood, and increases in CO2 stimulate faster breathing. This feedback loop is remarkably precise, maintaining arterial pH within narrow limits even during vigorous exercise. However, certain drugs can suppress this reflex, leading to respiratory depression. Opioids are the most well-known example, but benzodiazepines and general anesthetics also impair medullary respiratory centers, which is why monitoring respiratory function is essential during procedures involving these medications. Autonomic regulation occurs primarily through the medulla's cardiovascular centers. The nucleus tractus solitarius receives input from baroreceptors in the carotid sinus and aortic arch, integrating this information to adjust heart rate and vascular tone.Orthostatic hypotension - dizziness upon standing - often reflects dysfunction in this pathway. Autonomic neuropathy from diabetes or Parkinson's disease can damage these reflexes, making blood pressure management challenging. I have seen patients requiring compression stockings, increased salt intake, and sometimes midodrine to maintain adequate perfusion pressure when standing.
Get the Full Details

The spinocerebellar tracts carry proprioceptive information through the medulla and pons to reach the cerebellum. This pathway allows for coordinated movement without conscious attention to each joint position. When these tracts are damaged, patients develop ataxia - uncoordinated movements that worsen with purposeful action. The sensation of imbalance and frequent falls in conditions like multiple sclerosis often traces back to disruption of these pathways rather than weakness in individual muscles. Advanced imaging techniques have improved our understanding of these structures considerably. Diffusion tensor imaging can visualize the white matter tracts passing through the pons and medulla, revealing connectivity patterns that were previously inferred only from animal studies. Functional MRI during specific tasks shows activation patterns in brainstem nuclei that correlate with particular autonomic or motor functions. These research tools are not yet standard clinical practice, but they are advancing our knowledge rapidly. Surgical approaches to the brainstem remain extremely limited due to the concentration of critical structures in a small volume. Lesioning procedures are generally reserved for intractable pain or severe movement disorders when all other treatments have failed. Deep brain stimulation targets nearby structures rather than the brainstem itself, though research continues into direct brainstem stimulation for conditions like obesity and sleep apnea. The risks of brainstem surgery are substantial, and outcomes are unpredictable, which is why conservative management is preferred whenever possible.
Drug development targeting brainstem receptors has produced useful medications for specific conditions. Antidepressants like amitriptyline affect serotonin and norepinephrine reuptake in brainstem pathways, providing relief for neuropathic pain even when the original pain generator is not in the brainstem itself. Antiemetics that block serotonin receptors in the area postrema have improved cancer chemotherapy management significantly. These examples show how understanding basic neuroanatomy can lead to practical therapeutic applications. Prognosis for brainstem lesions depends heavily on the location and extent of damage. Small pontine strokes may cause minimal deficits if they avoid the corticospinal tracts and cranial nerve nuclei. Large medullary lesions affecting the respiratory centers are often fatal without mechanical ventilation. Recovery potential varies widely - some patients show improvement over months as edema resolves and compensatory mechanisms engage, while others remain permanently disabled. Rehabilitation specialists emphasize that improvement can continue for years after the initial injury, though the rate of recovery typically slows significantly after the first six months. The clinical significance of these structures extends beyond acute neurological events. Chronic conditions like multiple sclerosis, ALS, and certain forms of cerebral palsy involve progressive damage to brainstem pathways. Understanding the anatomy helps clinicians predict which symptoms will occur and which functions might be preserved. This knowledge informs palliative care decisions, assistive device selection, and family counseling about expected disease progression.
Student clinicians often struggle with brainstem localization because the relationships between nuclei, tracts, and vascular territories are complex. Drawing diagrams repeatedly helps solidify the spatial relationships. Clinical correlation through case-based learning reinforces anatomical knowledge better than rote memorization. I recommend working through actual patient cases when possible, as the clinical presentation makes the anatomy memorable in ways that textbook descriptions cannot achieve.