What Actually Happens When Teeth Decay
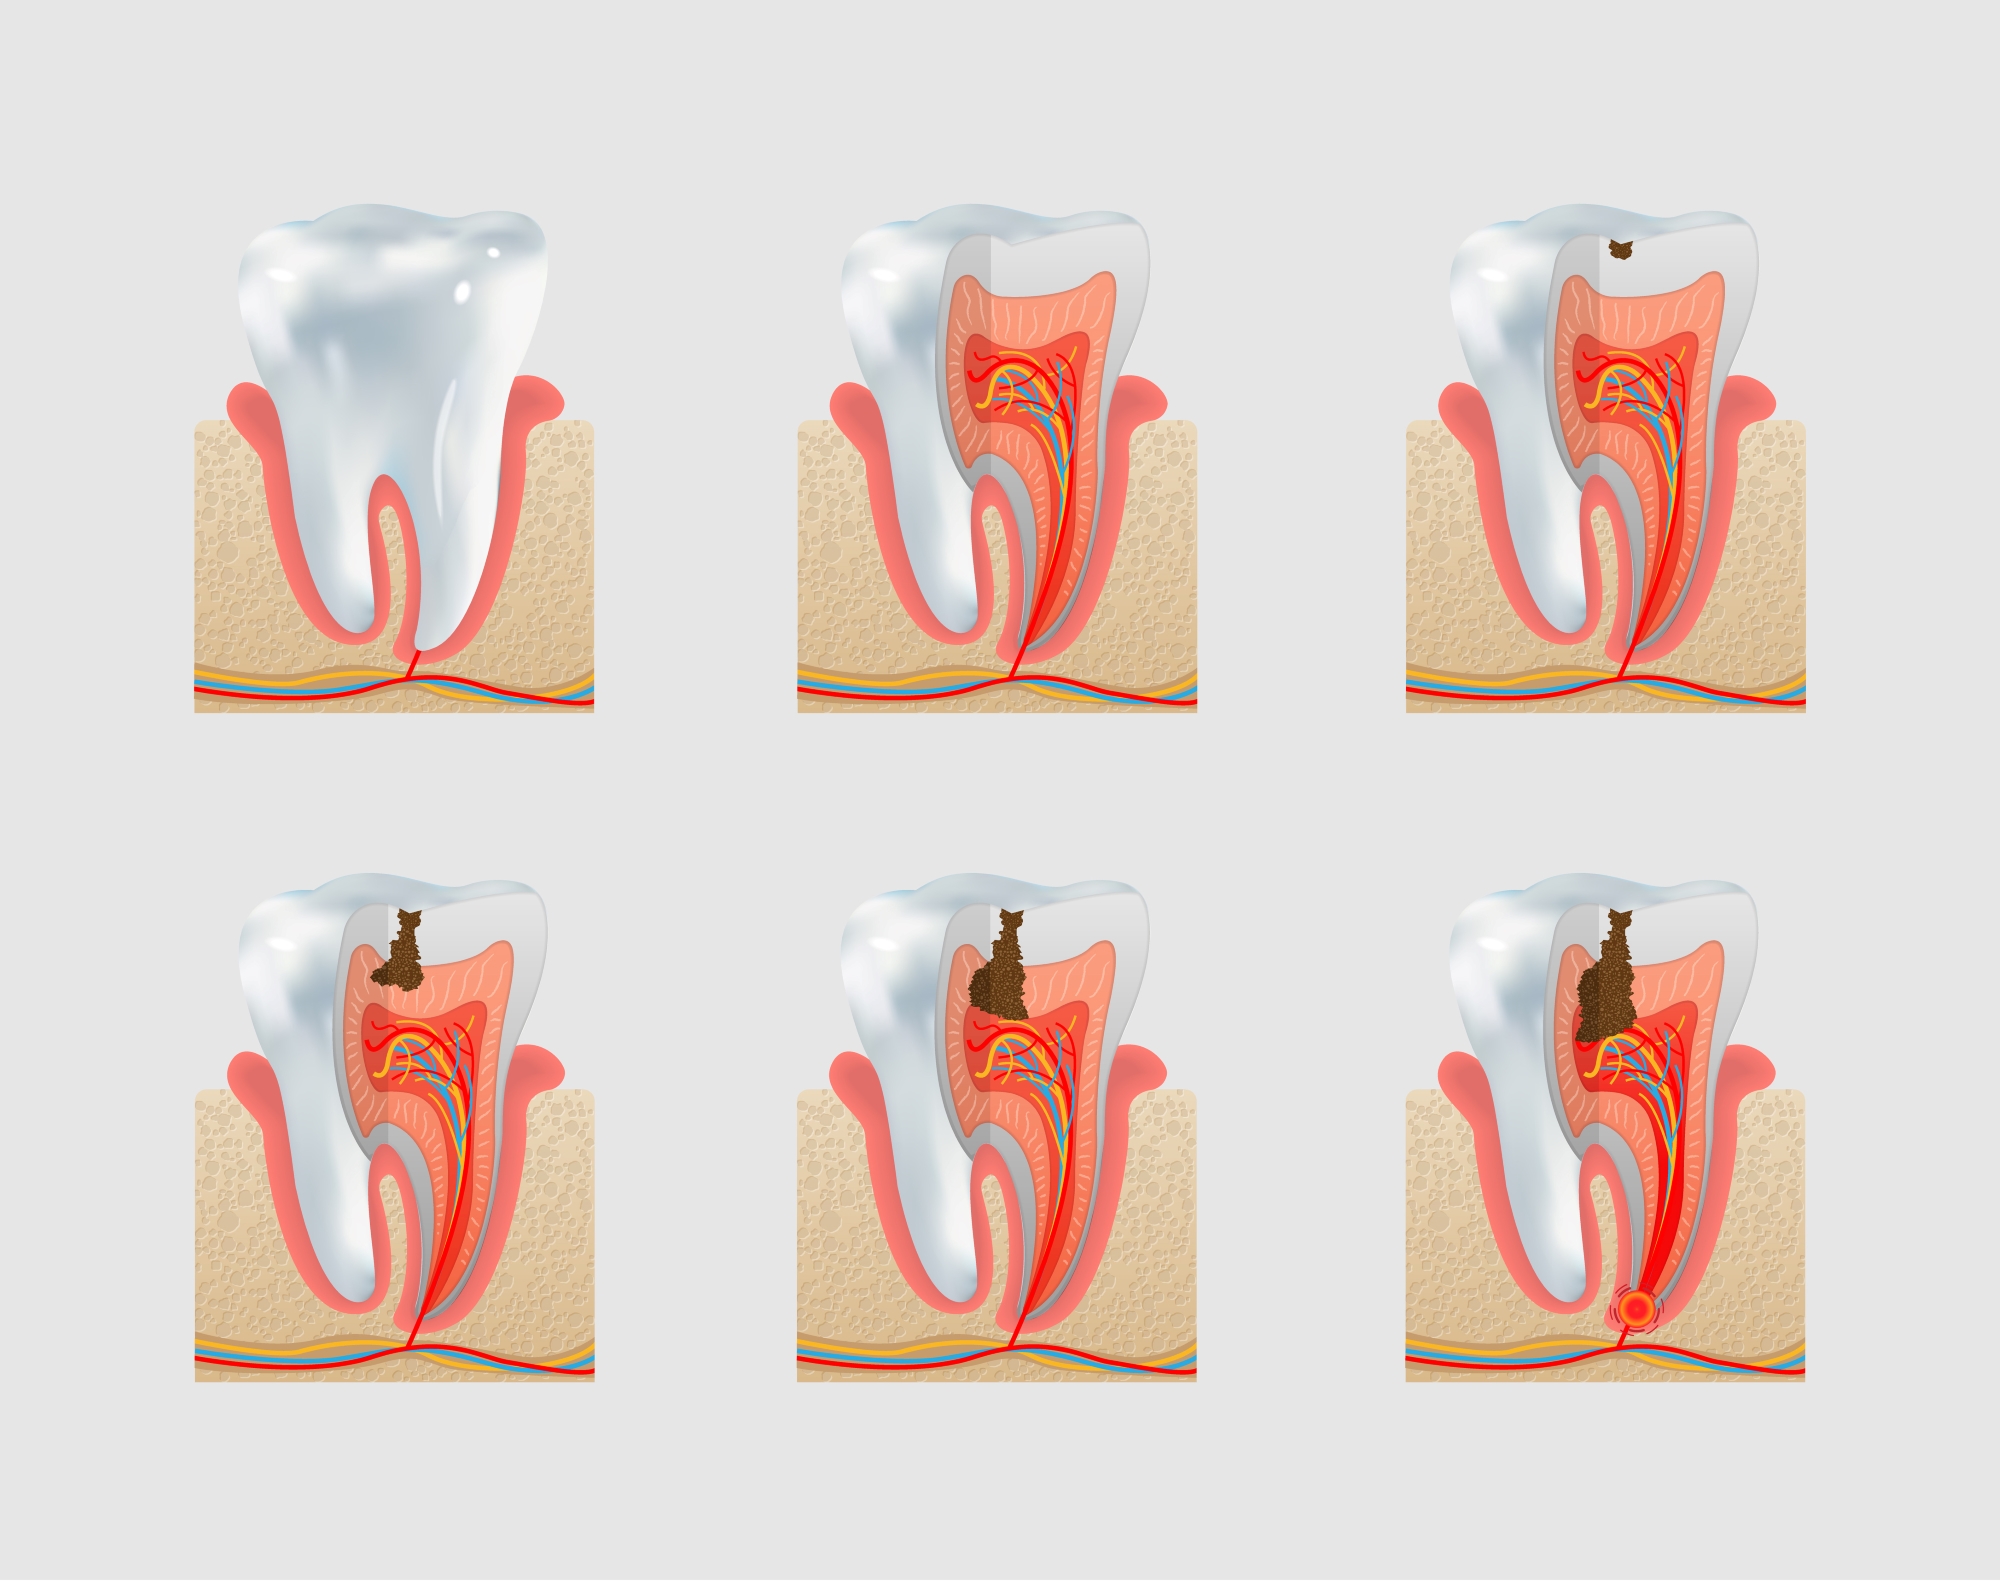
Most people treat tooth decay like a binary switch. Your tooth is either healthy or it has a cavity. That is not how it works. Decay moves through enamel at about 0.1 to 0.3 millimeters per year depending on your diet, saliva composition, and oral microbiome. It spends months being reversible before it ever reaches the point of no return. The problem is nobody checks during that window. I spent years watching patients come in with what they thought was their first cavity. They were wrong. The damage had been progressing for two to three years before it finally broke through the enamel layer and entered the dentin. By then, a simple fluoride treatment was no longer enough.
The Unconventional Genius Of Jackson Lamars Teeth All You Need Unlocking The Secrets Of Tooth Decay
The framework centers on a principle that sounds almost too simple to be useful. Most people focus on the end result of decay, which is the hole in the tooth. Jackson Lamar flips that timeline backward and treats the earliest stage, subsurface demineralization, as the actual problem to solve. He calls it the white spot phase, but that is just the visible marker of something happening beneath the surface. Here is the counter-intuitive part that most dentists do not spend enough time on. Fluoride does not prevent decay. It repairs it. The distinction matters because prevention and repair require completely different strategies. You can prevent a cavity by keeping plaque away from the tooth surface long enough for remineralization to win. Once plaque has been sitting there and acid has started leaching minerals out of your enamel, fluoride becomes the only thing that can reverse it before the structure collapses. The system outlines a specific sequence for intercepting that process. It starts with identifying your own risk level using a few straightforward markers. Things like how often you snack, whether your saliva feels thick or thin, and how your teeth feel after you eat something acidic. A common signal people miss is when your teeth feel fuzzy right after brushing instead of smooth. That fuzziness means biofilm is rebuilding faster than you are removing it.
I ran into an edge case last year that really tested this approach. A patient came in with what looked like early decay on four different teeth. Standard protocol would have been monitoring and possibly placing sealants or a prescription fluoride varnish. But his white spot lesions were not behaving normally. They were actually getting smaller between visits without any intervention on my part. The issue turned out to be a medication he was taking for anxiety. It was causing significant dry mouth, and the temporary relief he was getting was from increased water consumption and frequent rinsing. What looked like spontaneous remineralization was actually mechanical clearance of acid and plaque. I adjusted his protocol to include targeted xylitol use and timed his water intake around meals rather than treating it as a general habit. The practical steps from the material break down into a daily routine that takes roughly eight minutes. First, you remove the biofilm mechanically before applying anything chemical. That means brushing or flossing first, not after. Most people apply fluoride toothpaste and then rinse, which washes away most of the active ingredient within thirty seconds. The recommendation is to spit out the excess paste and not rinse at all. Let it sit on the tooth surface while you do the rest of your evening routine. That gives the fluoride contact time that actually matters for ion exchange in the enamel crystal structure. The second step is choosing the right concentration. Over-the-counter toothpaste runs about 1000 to 1450 parts per million of fluoride. That is fine for low-risk individuals who eat well and brush properly. If you have a history of cavities or visible white spot lesions, you need either a prescription strength paste at 5000 ppm or a separate fluoride gel applied with a tray for a few minutes before bed. I have seen people save teeth that would have needed fillings within a year by making this single switch.
Get the Full Details

The third component deals with the acid attack itself. Most people think sugar causes cavities. It does, but indirectly. Bacteria in plaque metabolize sugars and produce acid as a waste product. The real damage comes from the acid, not the sugar. That is why sipping soda over three hours is worse than drinking it in fifteen minutes. The pH in your mouth stays depressed for a much longer period. Each time it drops below 5.5, which is the critical pH for enamel dissolution, you start losing minerals. Saliva brings the pH back up, but that process takes twenty to thirty minutes after each exposure. Constant sipping means your enamel is in a near-constant state of demineralization with no recovery windows. There is a downside to this whole approach that the material does not dwell on. It requires consistency over months, not days. Remineralization is slow. A small white spot lesion that you catch early might take four to six months of proper protocol to fully remineralize and disappear. People expect results in two weeks and give up when they still see a visible spot. The spot does not mean it is not working. It just means the process is still ongoing. You cannot see subsurface hardening with the naked eye. That is one reason regular bitewing X-rays matter even when your teeth look fine. Another limitation is that this only works on enamel. Once decay enters the dentin, the process changes entirely. Dentin is softer, more organic, and bacteria can move through the tubules faster than they can through enamel. At that stage, you need a restoration. No amount of fluoride or dietary change will remineralize dentin. The framework is effective for interception, not for reversal of established cavities.
There is also a group of people for whom this will not work well regardless of how strictly they follow it. If you have hyposalivation from radiation therapy, Sjogren's syndrome, or certain medications, your mouth lacks the natural minerals and buffering capacity that make remineralization possible. In those cases, you need supplemental calcium and phosphate products, not just fluoride. Toothpaste alone will not compensate for the absence of saliva. I have seen people with severe dry mouth spend hundreds on advanced products while the underlying issue went unaddressed. A simple salivary flow test can tell you within fifteen minutes whether that is your bottleneck. If you want the full system laid out with all the details, product recommendations, and the reasoning behind each step, the source material is called The Unconventional Genius Of Jackson Lamars Teeth All You Need Unlocking The Secrets Of Tooth Decay. It is available through the usual digital product channels. I have not personally purchased it, but the core concepts align with what I have seen work in practice and what the literature supports. The value is mostly in the organization and the emphasis on the early-stage interception rather than the cavity-filling model that dominates most dental advice. The practical takeaway is that tooth decay is a chronic disease, not an acute event. Most people experience their first cavity somewhere between ages six and fourteen during the loss of baby teeth and the eruption of permanent ones. After that, the risk levels off and becomes more dependent on habits and biology. If you are in that higher-risk window or if you have a pattern of cavities as an adult, the interceptive approach described in the material is worth trying before you reach the drill-and-fill stage. It is not a miracle cure. It is a slower alternative to the default path, and sometimes slower is exactly what your teeth need.