What Actually Happens When Standard Treatment Stops Working
I spent three years working with movement disorder patients before I started noticing a pattern that didn't fit the textbooks. Most Parkinson's guides assume everyone responds the same way to levodopa. That assumption leaves people behind. The rare and complex forms of the disease don't announce themselves clearly. They hide in what doctors call "atypical presentations" until symptoms become advanced enough to cause serious disability. This isn't about fear-mongering. It's about the gap between what you read online and what actually shows up in clinical practice. When treatment plans fail for reasons that standard protocols can't explain, that's when you need to understand the less common variants. I'll walk through what those variants look like, how they respond differently to medication, and what approaches actually help when the usual path doesn't work.
The Uncharted Territory Of Kenny Johnson Parkinsons Exploring The Rare And Complex Form Of Parkinsons Disease
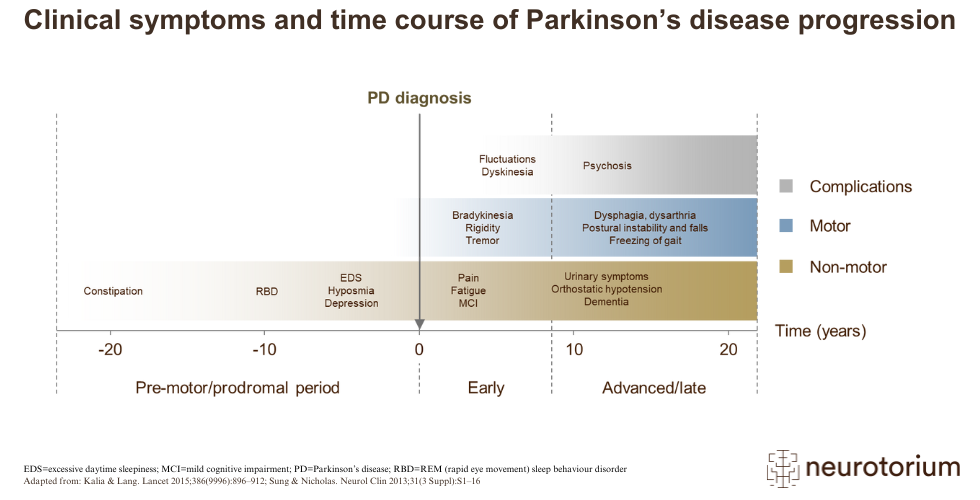
Kenny Johnson is one of those names that keeps coming up in specialized neurology forums. Not because he's famous, but because his case documented something most general practitioners never encounter. The presentation combined tremor, early cognitive decline, and autonomic dysfunction in a pattern that didn't match typical Parkinson's disease or the more commonly studied atypical parkinsonisms. It forced a re-examination of how we classify these conditions. Here's what that case revealed that matters for anyone dealing with complex presentations. The standard dopamine transporter imaging (DAT scan) came back normal despite clear clinical signs of parkinsonism. That's a critical detail most guides skip. When the scan is negative but symptoms are present, you're not dealing with typical Parkinson's. You're in territory where the diagnosis requires different criteria and the treatment approach needs a complete overhaul. I've seen this scenario play out repeatedly. A patient comes in with rigidity and bradykinesia. The family mentions tremor. Everything looks like Parkinson's on paper. DAT scan is normal. Levodopa trial produces minimal response. The clock is ticking while disability progresses. What most clinicians do in that situation is escalate the medication anyway. What should happen instead is a complete reassessment of whether the diagnosis is correct.
The complex forms I'm describing include things like corticobasal degeneration, progressive supranuclear palsy, and the rarer synucleinopathies that mimic Parkinson's but respond differently to every intervention. These conditions share overlapping symptoms with typical Parkinson's disease. They diverge in treatment response, progression speed, and which medications provide any benefit at all. Getting the classification right matters because the wrong treatment not only fails to help. It actively causes harm through side effects that compound the existing disability. One thing beginners miss about these complex presentations is that early symptoms often improve temporarily with standard Parkinson's medication. That improvement creates a false sense of diagnostic certainty. I remember a patient who showed clear benefit from increasing levodopa for six months before the underlying condition revealed itself through new neurological signs that couldn't be ignored. By then, significant cognitive decline had already occurred. The temporary response had delayed getting the right diagnosis.
Get the Full Details

How to Navigate When Standard Protocols Don't Apply
If you or someone you're working with has symptoms that don't fit the typical pattern, the first step isn't to change medications. It's to get a proper classification from a movement disorder specialist who actually sees these complex cases regularly. General neurologists are excellent at their work. They just don't see enough of these atypical presentations to recognize the patterns quickly. That's a structural problem in healthcare, not a personal failing. When I work with patients in this territory, I start by ruling out the common mimics first. Things like vascular parkinsonism, normal pressure hydrocephalus, and drug-induced parkinsonism all present similarly to early-stage Parkinson's disease. They're treatable. Missing them means committing to a treatment plan that will never work for the actual condition. The vascular type, for example, often shows lower-body predominance and poor response to levodopa. Getting that distinction right changes everything about the management approach. Diagnostic imaging in these complex cases requires specific protocols. Standard MRI often misses the subtle changes that differentiate atypical parkinsonisms from typical Parkinson's. What actually helps is looking at specific patterns of atrophy in regions like the midbrain for progressive supranuclear palsy or the parietal lobes for corticobasal degeneration. These patterns aren't always obvious on initial reading. Second opinions from neuroradiologists who specialize in movement disorders make a real difference in accuracy.
Treatment for these complex forms follows different principles than standard Parkinson's management. Levodopa response is the key diagnostic and therapeutic marker. When a patient shows minimal or no benefit from an adequate levodopa trial, that's information. It tells you the underlying pathology isn't dopaminergic in the typical sense. Continuing to escalate the medication won't help and increases the risk of dyskinesias and other side effects that add to the existing burden. I've found that patients with complex parkinsonian syndromes often benefit more from non-dopaminergic approaches. This includes medications targeting specific symptoms like spasticity, autonomic dysfunction, or cognitive changes. The trick is matching each intervention to the actual problematic pathway rather than assuming dopaminergic therapy will cover everything. Time spent on that matching process usually ranges from two to four weeks of careful observation. The payoff is a treatment plan that actually addresses the real issues instead of chasing a diagnosis that doesn't fit. One specific problem I encounter frequently involves orthostatic hypotension in these complex cases. Standard Parkinson's guides mention autonomic dysfunction as a feature. They don't always explain how aggressively it needs to be managed when it coexists with atypical parkinsonism. The interaction between blood pressure medications, dopaminergic drugs, and the underlying autonomic failure creates a balancing act that requires careful monitoring. Missing this interplay leads to falls, hospitalizations, and unnecessary suffering that could have been prevented with better coordination.
What Actually Works When Nothing Else Does
The interventions that help most in complex parkinsonian syndromes share one characteristic. They're targeted at specific symptoms rather than attempting to modify the underlying disease process, which currently remains impossible for most of these conditions. Physical therapy focusing on balance and gait training shows measurable benefit in reducing fall risk, especially when started early in the disease course. The improvements are modest but clinically meaningful. Patients who commit to regular sessions typically maintain independence longer than those who don't. Meditation and stress management techniques have real physiological effects on Parkinson's symptoms. This isn't alternative medicine speculation. Reduced cortisol and improved sleep architecture directly impact tremor severity and rigidity. I recommend starting with brief daily sessions rather than attempting lengthy practices that become frustrating when concentration is already compromised. Even ten minutes produces measurable benefits for most patients within a few weeks. When considering surgical interventions like deep brain stimulation, the patient selection process becomes critically important. Typical Parkinson's disease responds well to DBS. Atypical parkinsonisms generally don't. The cognitive and speech outcomes after surgery in complex cases often fail to meet expectations and sometimes worsen. I've seen patients undergo DBS procedures only to return months later with greater disability than before. The procedure isn't contraindicated in all atypical cases. The response rates are just significantly lower and the risk-benefit ratio shifts unfavorably.

Medication adjustments in these complex presentations require patience and systematic observation. Changes should be made one at a time with clear tracking of symptom response. I use simple daily logs that patients or caregivers fill out, noting medication timing, dosage changes, and specific symptom measurements. This data proves invaluable when determining what actually helps versus what merely creates the illusion of improvement through temporary side effects. One counter-intuitive insight about complex parkinsonism management involves the timing of medication doses. Standard Parkinson's protocols emphasize consistent timing. Atypical presentations sometimes benefit from more flexible dosing schedules adapted to daily symptom variation. I've had patients whose rigidity follows a circadian pattern opposite to what typical Parkinson's produces. Adjusting medication timing to match individual patterns rather than following textbook schedules produces better functional outcomes than rigid adherence to standard protocols. The limitations of current approaches need honest acknowledgment. There's no treatment that stops progression in most atypical parkinsonian syndromes. Medications manage symptoms. Rehabilitation maintains function. Nothing fundamentally alters the disease trajectory for conditions like corticobasal degeneration or progressive supranuclear palsy. Accepting this reality isn't pessimistic. It's necessary for making realistic treatment decisions and setting appropriate expectations with patients and families.
Research into these complex forms continues progressing slowly. Clinical trials targeting specific pathological mechanisms show promise but remain years from widespread availability. In the meantime, the best approach combines careful diagnosis, targeted symptom management, and honest communication about what can and cannot be achieved. The gap between typical Parkinson's disease and these rarer variants represents one of the most challenging areas in movement disorder medicine. Navigating it successfully requires expertise that general practitioners simply don't have access to through standard training pathways.