
Choosing Between Dobhoff and Nasogastric Tubes: A Practical Guide
The Ultimate Showdown Dobhoff Tube Vs Ng Tube Which Nasogastric Tube Reigns Supreme
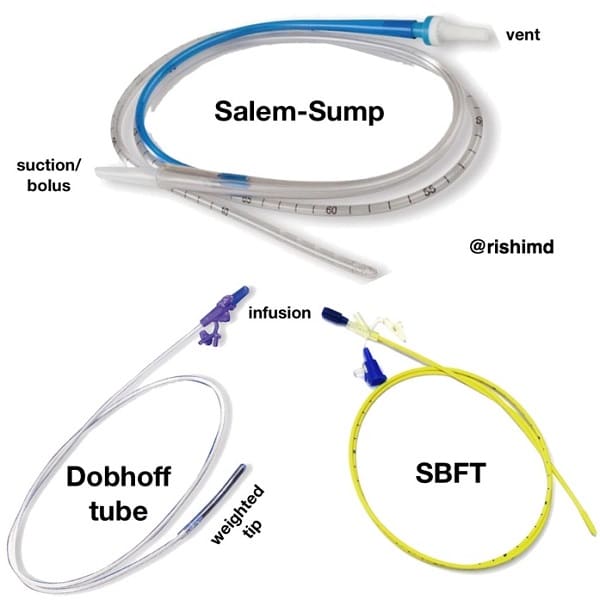
I've placed hundreds of these tubes over the years, and the choice between a Dobhoff and a standard NG tube comes down to three things: how long the patient needs enteral nutrition, what their anatomy looks like, and how much you trust blind placement. Neither tube is universally better. They serve different purposes. Understanding the tubes A Dobhoff tube is a small-bore feeding tube, usually 8 to 12 French, with a weighted metal tip at the distal end. The weight helps it navigate through the pylorus and into the duodenum or jejunum using gravity rather than force. It's designed for long-term enteral nutrition, typically weeks to months. The material is softer silicone or polyurethane, which means less irritation to the nasal passage and esophagus over time.
A standard NG tube is larger, usually 14 to 18 French, made of rigid PVC. It terminates in the stomach and is meant for short-term use—decompression, medication administration, or feeding that lasts days to maybe a couple of weeks. The rigidity is actually an advantage when you need to suction gastric contents or lavage the stomach. You won't get that from a Dobhoff. Placement technique for Dobhoff Measure the tube from the tip of the nose to the earlobe, then down to the xiphoid process. Mark it. Lubricate the distal two-thirds generously with water-soluble jelly. Have the patient sit upright at 90 degrees if they can tolerate it. Insert the tube along the floor of the nasal passage, pointing it slightly upward toward the orbit, not toward the septum. That angling matters because it follows the natural curvature of the inferior meatus and avoids trauma to the nasal mucosa.
Once you hit the pharynx, ask the patient to swallow if they're conscious and cooperative. Advance the tube during the swallowing phase. The weighted tip will tend to fall posteriorly into the esophagus. If resistance builds, don't push. Pull back slightly, reposition the head, and try again. I've seen people power through resistance and end up coiling the tube in the pharynx, which then gets mistaken for successful placement. For post-pyloric placement, you can use a few tricks. Inject warm water through the tube after it reaches the stomach—this sometimes stimulates peristalsis and helps the weighted tip migrate. Fluoroscopy gives you real-time visualization and is the gold standard when you need guaranteed duodenal or jejunal positioning. pH testing of aspirate helps confirm gastric placement but tells you nothing about post-pyloric positioning. A Dobhoff in the duodenum will still give you gastric pH readings because the tip is beyond the pylorus but the side holes may sit in the stomach. Placement technique for NG tube
Get the Full Details

The measurement and insertion are similar, but the larger bore means more discomfort and a higher risk of epistaxis. Advance the tube through the nasal passage and into the pharynx. Swallowing assists passage. Because this tube lacks a weighted tip, it won't self-direct past the pylorus. You stop at the stomach. Confirm placement with an X-ray before using it for anything other than decompression. When I reach for each one I use a Dobhoff when I know the patient needs nutrition for more than a week or two and when gastric emptying is adequate. It's my go-to for stroke patients with dysphagia, for those with prolonged ICU stays who can't maintain oral intake, and for palliative feeding where comfort matters. The smaller size means I can leave it in place through discharge to a skilled nursing facility without replacing it.
I reach for a standard NG tube for acute gastric decompression in bowel obstruction, for activated charcoal administration in overdose, for nasogastric lavage in upper GI bleeding, and for short-term feeding in patients who I expect to recover oral intake within days. The larger lumen handles viscous medications and charcoal slurry that would clog a Dobhoff instantly. A real problem I ran into I had a patient with a history of gastric surgery and altered anatomy where the Dobhoff kept looping in the stomach fundus no matter what I did. The weighted tip wasn't helping because the pylorus was scarred and narrowed. I switched to fluoroscopic placement with a guidewire through the Dobhoff's channel. That got the tip past the pylorus into the duodenum on the first attempt. The workaround is simple in hindsight, but it cost me two extra attempts and a frustrated patient beforehand.
Counter-intuitive things nobody tells you The X-ray confirmation myth is worth addressing. A lot of people think an abdominal X-ray proves the tube is in the stomach. It doesn't. A tube coiled in the esophagus, a tube in a hiatal hernia, and a tube actually in the stomach can all look identical on a plain film. You need to see the carina and the diaphragm as landmarks. If the tube tip is above the diaphragm, it's not in the stomach. If it crosses the diaphragm and the curve follows the greater curvature, it's likely gastric. Anything past the pylorus requires different interpretation. Another thing: pH testing is not as reliable as people think. If the patient is on proton pump inhibitors, gastric pH can be above 6 even with correct placement. Conversely, respiratory secretions aspirated from a misplaceedin the trachea can also read above 6 if the patient has a concurrent respiratory infection. Don't rely on pH alone, especially in critically ill patients on acid suppression.
What each tube does poorly Dobhoff tubes clog. Not sometimes, regularly. If you're administering enteral medications through one, you need to flush with 30 mL of water before and after every medication dose, and between different medications. Crushed pills don't always dissolve completely, and the small lumen catches the particulate matter. I've seen tubes occlude after a single dose of liquid suspension that wasn't properly diluted. Use syringe-style flushing, not push-button devices, which don't generate enough pressure to clear partial obstructions. NG tubes are miserable for the patient. The rigidity causes nasal ulceration, the larger size triggers gagging more easily, and they're obviously visible, which affects quality of life significantly. Leaving one in for more than a few weeks increases the risk of sinusitis and nasal alar necrosis. I've seen nasal cartilage damage from tubes left in place too long without rotation or replacement.
Bottom line Pick the Dobhoff for anticipated longer-term feeding when gastric or post-pyloric nutrition is needed and the patient can tolerate a smaller tube. Pick the NG tube for short-term decompression, lavage, or acute feeding when you need a wider lumen and don't care about patient comfort as much. Neither tube is a set-and-forget device. Both require confirmation of placement, both can fail in difficult anatomy, and both need monitoring for complications regardless of which one you choose.



