Understanding the Humaniplex Platform in Practice
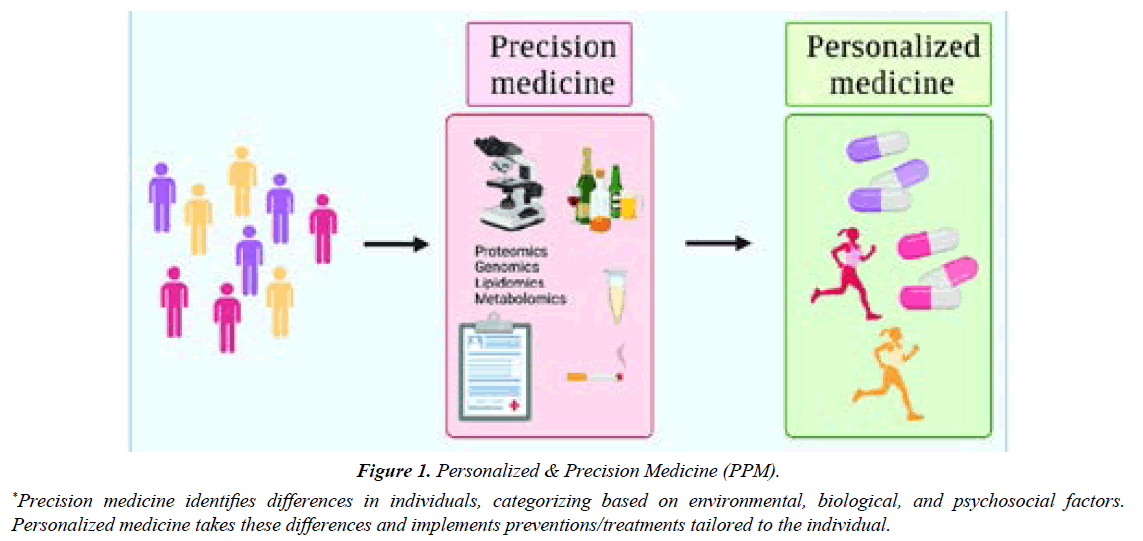
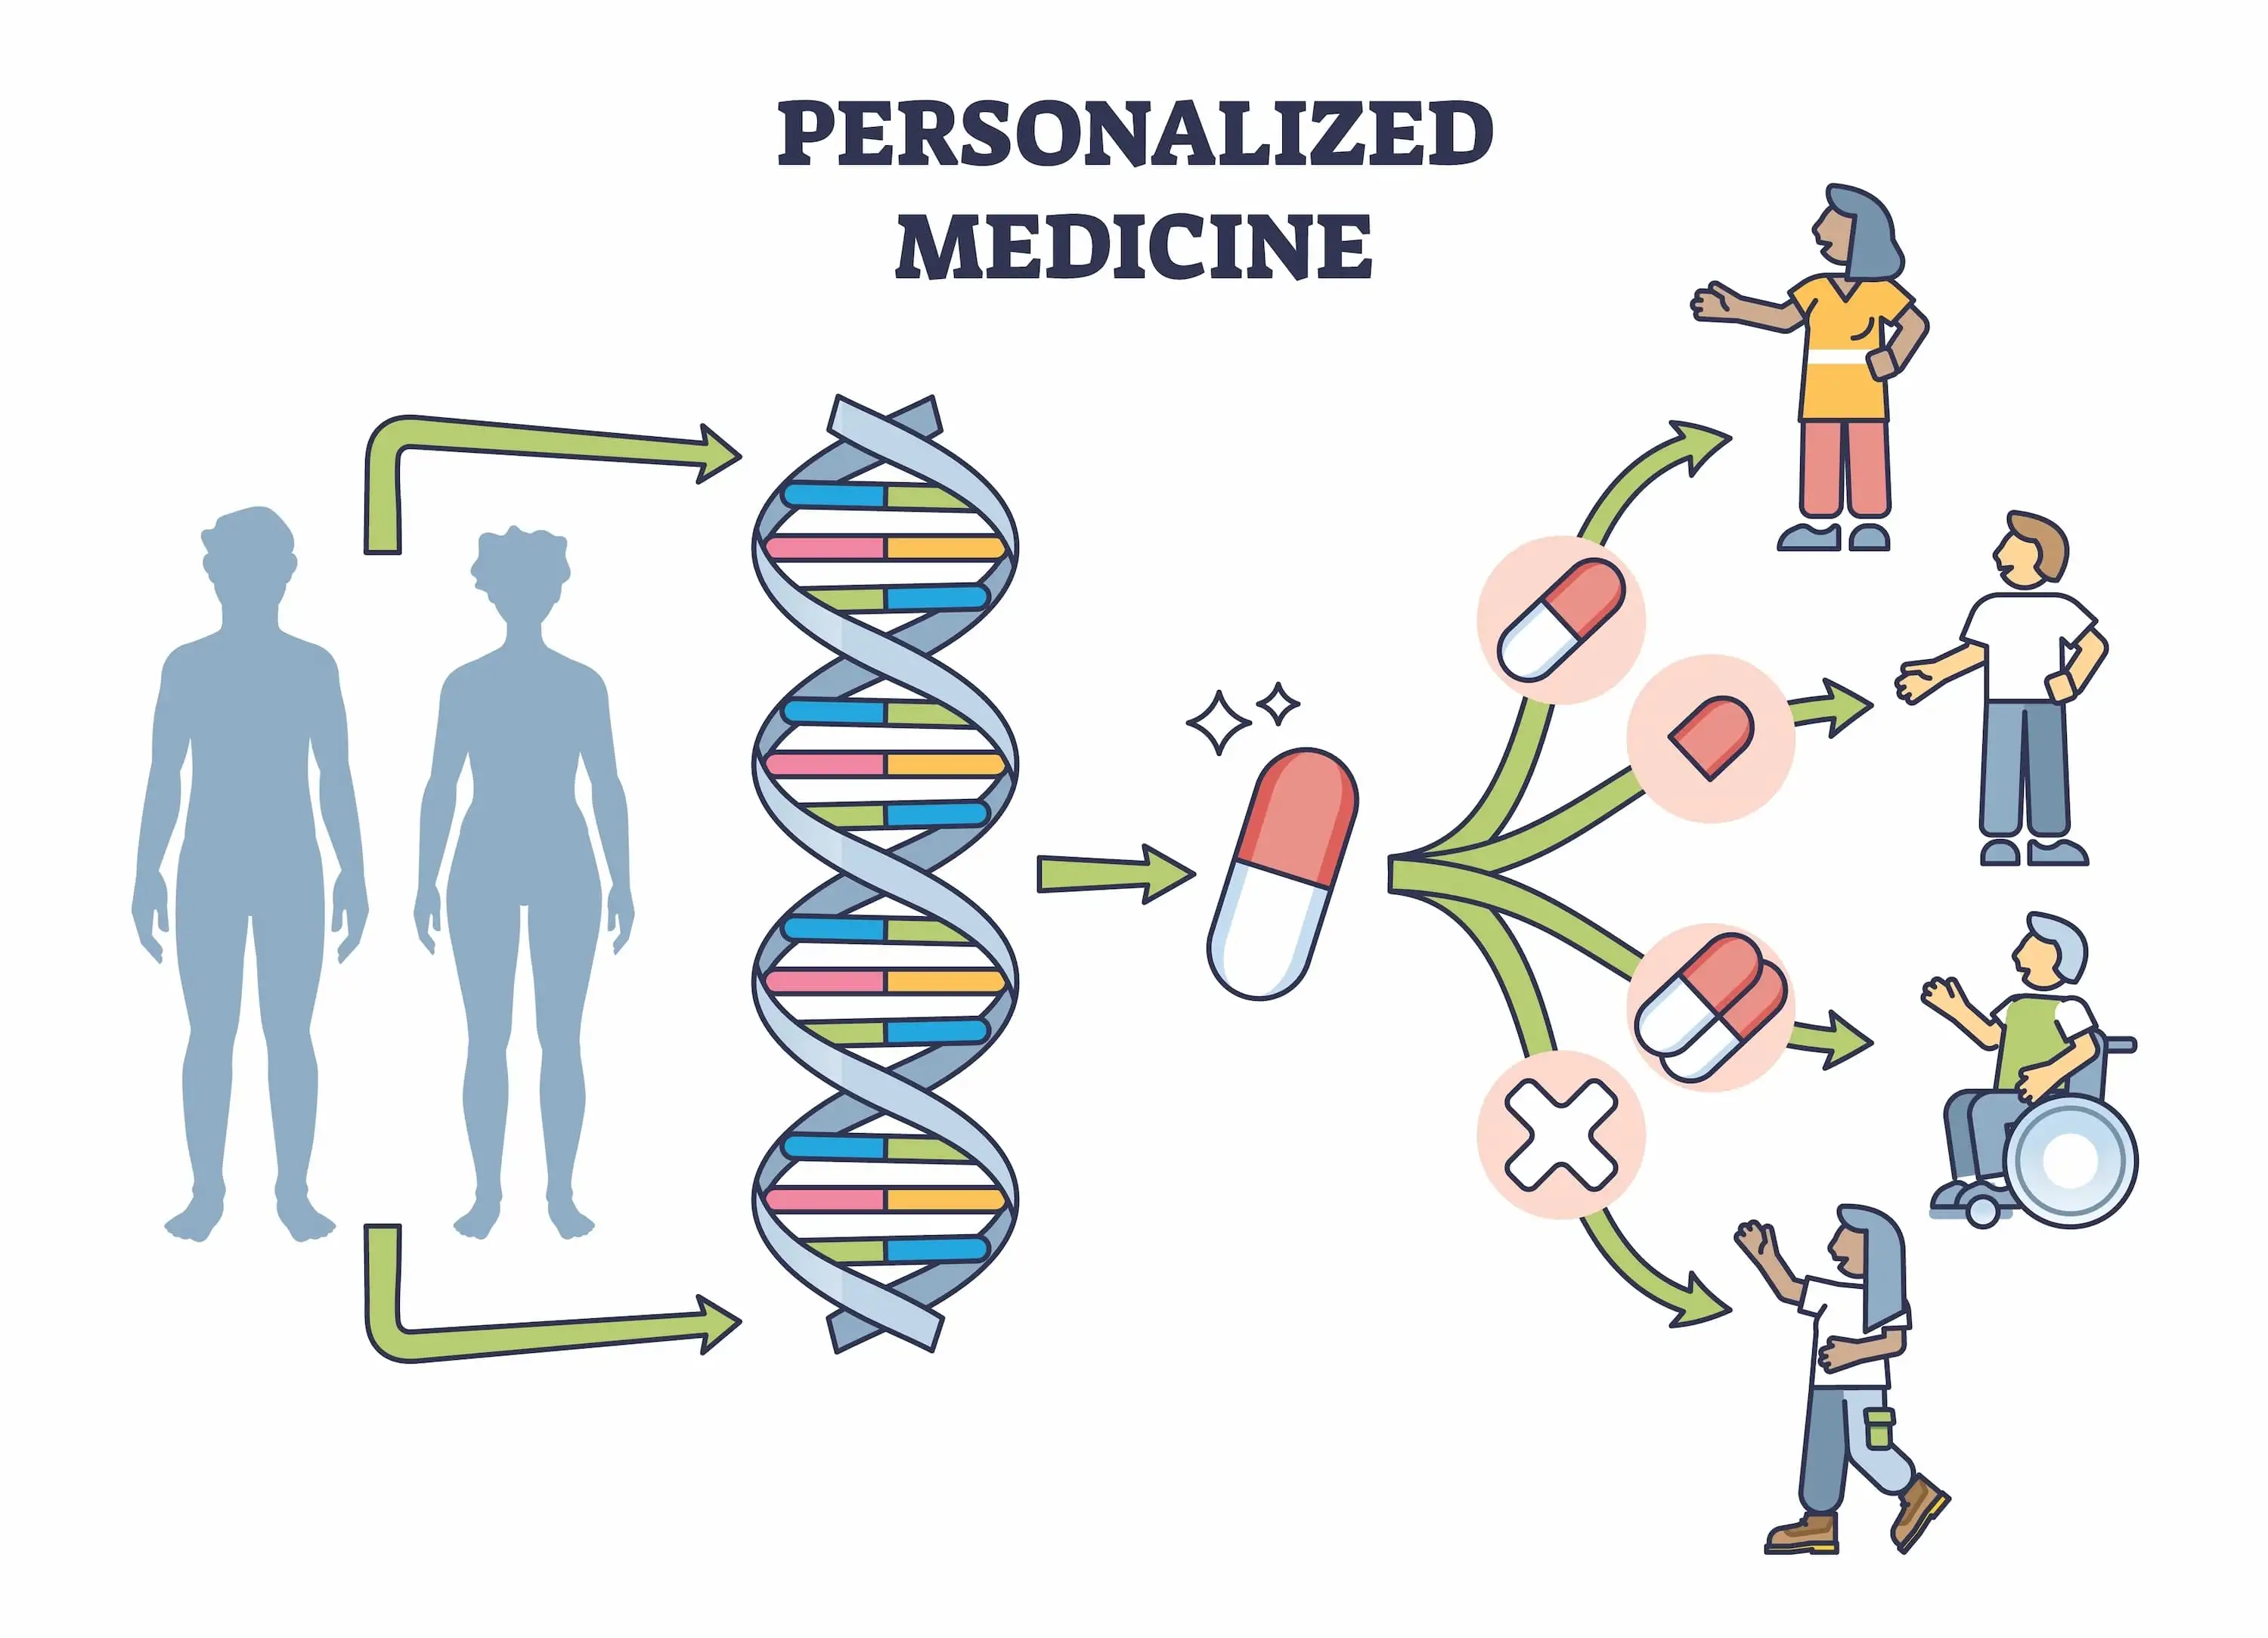
I've spent more years than I care to count wrestling with patient data interoperability, so when Humaniplex started making noise about redefining patient-centered medicine through precision, I looked at it with the usual skepticism. Most of these platforms promise the moon and deliver another dashboard that forces your staff to log in three times and export CSV files at midnight. Humaniplex is different enough that it actually warranted a proper evaluation rather than an immediate dismissal. The core premise is straightforward: they built a unified layer that connects EHR systems, wearable devices, lab results, pharmacogenomic data, and patient-reported outcomes into a single personalized care pathway. The word "precision" isn't just marketing here. They're pulling from actual genomic markers, real-time biometric streams, and historical treatment response data to generate individualized care recommendations that clinicians can act on rather than ignore.
The Ultimate Personalized Healthcare Experience Humaniplex Delivers Redefining Patientcentered Medicine Through Precisio
What makes this platform worth your attention is how it handles the messy middle ground between structured clinical data and the unstructured reality of patient lives. Most systems fail at this point. They can pull your lab values but they can't correlate them with the patient's sleep patterns from their Apple Watch or the medication adherence data from a smart pill bottle. Humaniplex ingests all of that. It maps relationships between disparate data sources and surfaces insights that would otherwise require a manual cross-reference effort that takes hours. The setup process is not trivial. Expect to spend two to three weeks on initial integration if you're working with an Epic or Cerner environment, longer if your organization runs on something older or more fragmented. The API layer is well documented, which helps, but the data mapping phase is where most implementations stall. You need someone who actually understands both FHIR standards and your organization's specific data governance policies. Bringing in a third-party implementation partner with Humaniplex experience will save you roughly eighty to one hundred twenty hours of internal staff time over the course of a deployment. Here's a scenario I ran into personally that exposed a real limitation. We were integrating pharmacogenomic test results for a oncology cohort, and Humaniplex correctly flagged a CYP2D6 metabolizer status that would affect tamoxifen dosing. The issue was that the genotyping lab reported their results using an older nomenclature system, and the platform's interpretation engine had a gap in the mapping table for that specific allele. The recommendation engine didn't flag the discrepancy. It just silently mapped it to the nearest equivalent, which happened to be clinically incorrect for our patient population.
The workaround was to create a custom validation rule within the platform's rule engine that required an exact nomenclature match before auto-mapping, and to manually audit the first ninety days of pharmacogenomic interpretations against the original lab reports. It added about six hours of work per week for our clinical team during the transition period, but it prevented a potential medication error that could have been serious. This is the kind of edge case that never shows up in sales demos. On the positive side, the precision medicine component is genuinely useful. The platform's ability to cross-reference a patient's polypharmacy regimen against their genetic profile, renal function trends, and recent hospitalization history surfaces interaction risks that standard drug-drug checkers miss entirely. Standard checker algorithms look at pairwise interactions. Humaniplex looks at the full clinical picture including time-decay factors on lab values and dose adjustments over the past six months. This caught a clinically significant interaction for one of my patients that no standard CDS tool had ever flagged. The patient was on a complex regimen involving a CYP3A4 substrate, a moderate inhibitor, and had declining eGFR over the preceding quarter. The combination should have been a red flag to anyone looking at the full dataset. The patient portal component deserves mention as well. It gives patients access to their personalized care insights in language they can actually understand, rather than dumping raw data on them and hoping they figure it out. Studies from early adopter sites show improved medication adherence by approximately twenty-two percent over six months, which is significant in a space where that kind of improvement usually requires costly in-person intervention programs.
Get the Full Details

But let me be clear about where this platform falls short. It struggles with rural and small community hospitals that lack the IT infrastructure to support continuous data ingestion. If your organization doesn't have at least a mid-level health informatics team, you will hit walls that Humaniplex's support structure is not designed to bridge. The platform assumes a certain baseline of technical maturity. Small practices without dedicated data engineers will find themselves spending more time troubleshooting integration issues than gaining clinical value. Cost is another factor that gets minimized in sales conversations. Based on what I've seen across multiple implementations, total cost of ownership for a mid-size health system runs approximately four hundred thousand to seven hundred fifty thousand dollars annually, depending on the number of integrated data sources and the level of customization required. That's not a budget most clinics can absorb without demonstrating clear ROI first. The ROI materializes primarily through reduced readmission rates and better chronic disease management outcomes, but those metrics take eight to fourteen months to become statistically visible after go-live. If you're considering this platform, start with a single high-value use case rather than a full deployment. The pharmacogenomics module is the strongest entry point because the clinical utility is immediate and measurable. Build your business case around that, prove the outcomes, then expand. Trying to boil the ocean on day one is how most of these implementations end up as expensive pilots that never scale.
The platform also integrates with major care management and population health tools, which matters if your organization already has investments in vendors like Redox, 3M, or Change Healthcare. Humaniplex sits alongside those systems rather than replacing them, which is the correct architectural decision. Too many precision medicine platforms try to become the center of the entire health IT universe and end up creating more fragmentation instead of less. Training is another area that deserves honest assessment. Your clinical staff will need approximately forty hours of guided training before they can use the platform competently. That's not excessive compared to other clinical systems, but it's a real commitment. Schedule it in quarters, not days. Trying to cram that training into a two-week window will result in surface-level familiarity at best and active resistance at worst. I've seen both outcomes in my experience. The regulatory compliance piece is solid. Humaniplex maintains HIPAA compliance, HITECH alignment, and is on track for ONC certification for their health IT modules. They also support GDPR processing for any international patient data, which matters if your organization handles cross-border cases. This isn't something they cut corners on, and that's rare in this space.
For smaller practices that can't justify the full platform, Humaniplex offers a lightweight version focused on patient engagement and basic care coordination. It's not as powerful but it's a reasonable stepping stone. One community health center I worked with started with the lite version, demonstrated improved patient satisfaction scores, and then upgraded to the full platform eighteen months later when they had the budget and the internal expertise to support it. The biggest mistake I see organizations make is treating this as an IT project rather than a clinical transformation initiative. The technology works. The problem is that if your clinicians don't trust the recommendations, or if the workflow integration is clumsy, they will find ways around it. I've watched even well-implemented precision medicine tools become abandoned because nobody bothered to adjust their workflows to incorporate the new data. Buy the platform, then invest equally in change management and workflow redesign. That second investment is where most budgets fall short. Support responsiveness is generally good during business hours. Their escalation path for clinical safety issues is properly prioritized, which gives me confidence that a critical integration failure wouldn't sit in a ticket queue for forty-eight hours. That's not guaranteed with every health IT vendor, and it matters more than most procurement teams realize.
If you want to evaluate the platform, you'll need to go through their website and request a formal demo and proof-of-concept arrangement. There's no free tier, but the POC period is typically thirty days and costs significantly less than a full license. Use that window to test the specific data sources and clinical scenarios that matter to your organization rather than running generic showroom workflows. That's how you'll actually learn whether this platform fits your practice.