
Understanding Sleep Disorders
I ran into a stubborn case last year involving a patient who had been diagnosed with insomnia for three years straight. They were on zolpidem nightly, taking it exactly as prescribed, yet their sleep quality scores on a sleep diary kept getting worse. The breakthrough came when I pulled the full polysomnography report and spotted frequent arousal patterns—micro-awakenings every 90 seconds or so. The patient literally had no idea these were happening. That became the pivot point for re-diagnosing them with Periodic Limb Movement Disorder, which turned out to be the real culprit behind the fragmented sleep they'd been treating as plain insomnia. That experience taught me something most guides don't emphasize enough: sleep disorders rarely present as cleanly as the textbooks describe. The same symptom—trouble falling asleep—can mask at least a dozen different underlying mechanisms. Knowing which mechanism you're actually dealing with determines whether the treatment you pick will help or do absolutely nothing.
What Sleep Disorders Actually Are
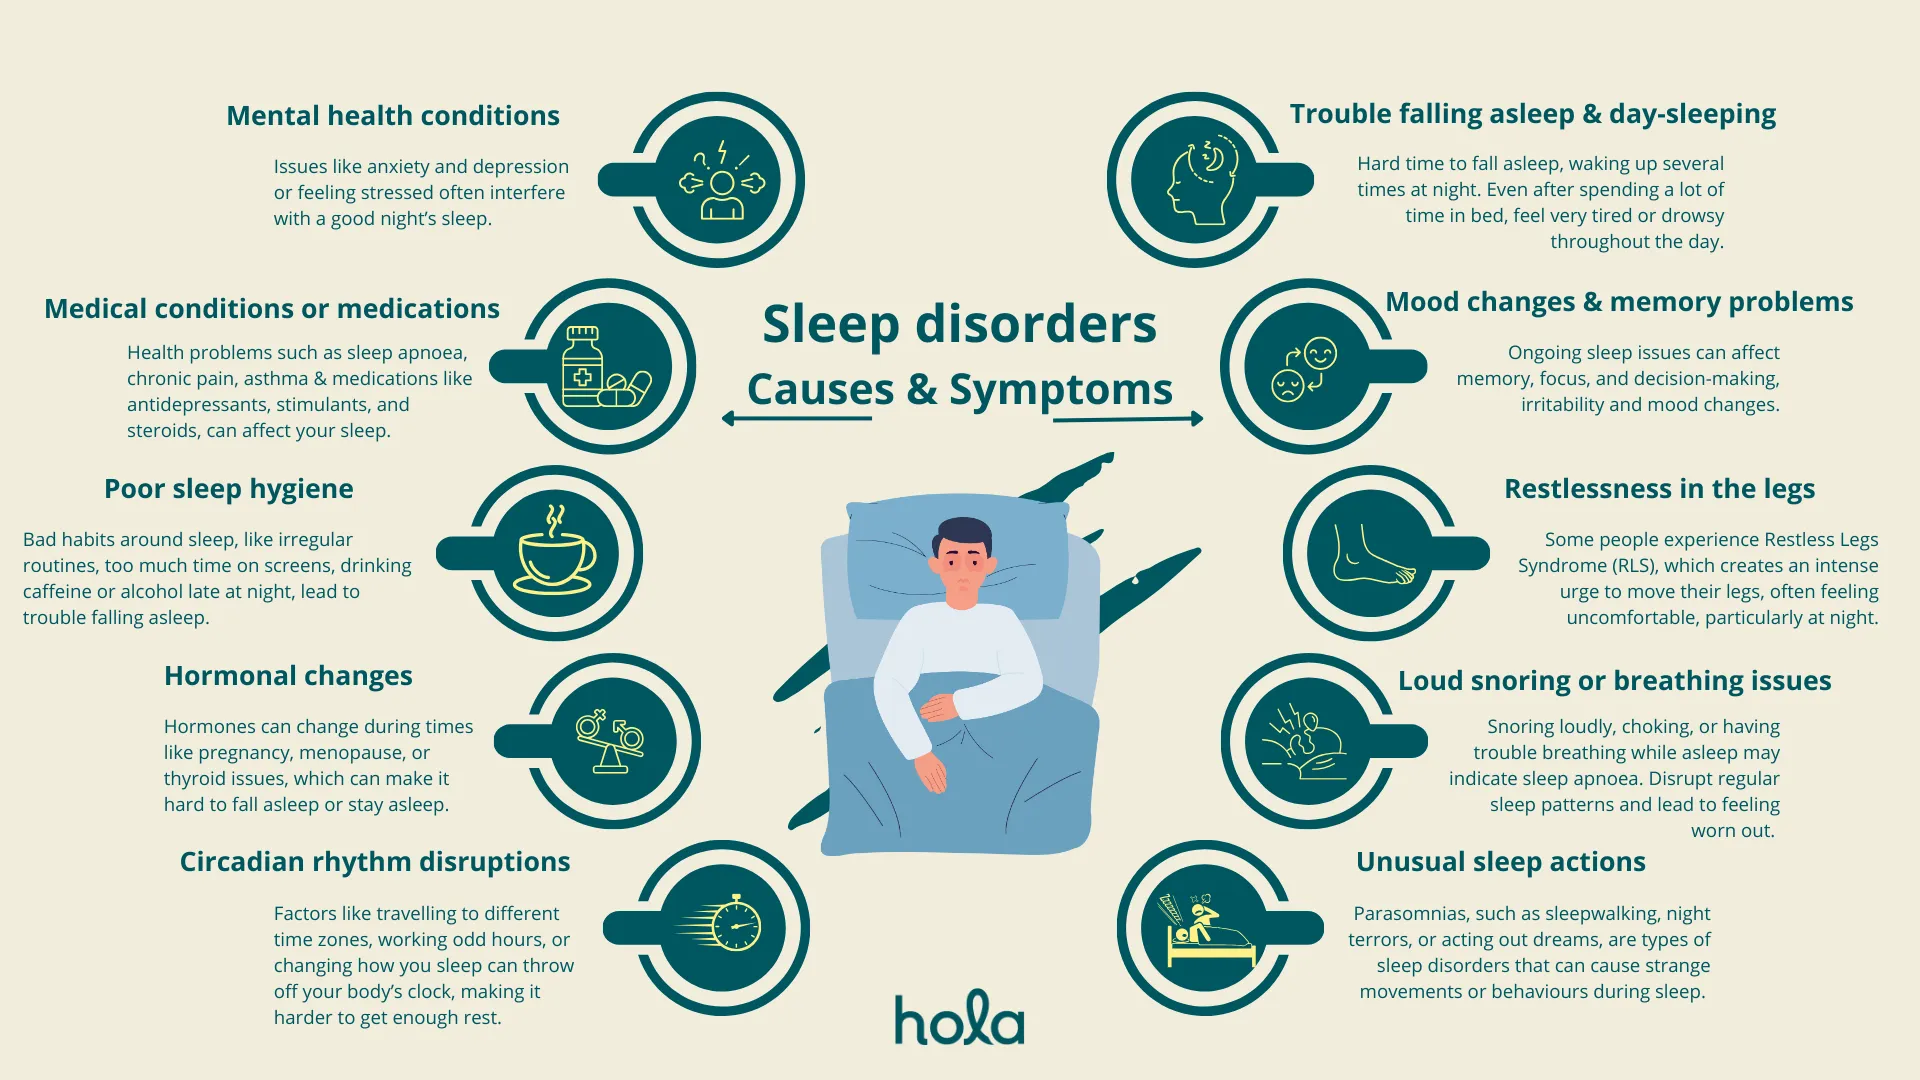
A sleep disorder is any condition that disrupts the normal quantity, timing, or quality of sleep on a recurring basis. That sounds straightforward, but the boundary between occasional poor sleep and an actual clinical disorder is defined by duration and functional impairment. If you wake up unrefreshed two nights a week after a stressful project, that's stress. If you've been waking up unrefreshed every night for three months and your concentration at work is declining, that crosses into clinical territory and warrants evaluation. The International Classification of Sleep Disorders, third edition (ICSD-3), recognizes over 100 distinct sleep disorders. They fall into seven broad categories: insomnia disorders, sleep-related breathing disorders, central disorders of hypersomnolence, circadian rhythm sleep-wake disorders, sleep-related movement disorders, parasomnias, and isolated sleep symptoms. Most people encountering sleep issues fall into the first two categories, but the others matter more than they get credit for.
The Ultimate Guide To Understanding Sleep Disorders What You Need To Know
Before diving into specific conditions, it helps to understand how sleep architecture works. Normal adult sleep cycles through four stages: N1, N2, N3, and REM. N1 is light sleep lasting a few minutes. N2 is the longest stage, making up roughly 45 to 55 percent of total sleep time. N3 is deep slow-wave sleep, critical for physical restoration and memory consolidation. REM sleep is where most dreaming occurs and plays a role in emotional processing. A complete cycle takes about 90 minutes, and you cycle through all four stages roughly four to six times per night. Disruptions at any single stage can cascade into problems that look like they're coming from somewhere else entirely. Insomnia disorder is characterized by difficulty initiating sleep, maintaining sleep, or waking too early with inability to return to sleep. The diagnostic threshold requires symptoms at least three nights per week for three months or more, plus daytime impairment. That daytime impairment is the key differentiator from occasional sleeplessness. Without it, you might just have acute insomnia triggered by stress, which often resolves on its own. Cognitive behavioral therapy for insomnia (CBT-I) remains the first-line treatment per clinical guidelines. It's not just recommended over medication as a policy preference. The data actually supports it: CBT-I shows durable effects that persist after treatment ends, while medication benefits tend to disappear once you stop taking the pill. A typical CBT-I program runs six to eight sessions over eight weeks and addresses the behavioral and cognitive factors maintaining the insomnia. I've seen patients who'd been on benzodiazepines for years reduce and eventually stop using them after completing CBT-I, something that seemed impossible before the therapy.
Get the Full Details

The medications people commonly expect to fix insomnia—zolpidem, eszopiclone, benzodiazepines—do help you fall asleep faster, but they don't improve sleep architecture the way you'd hope. They tend to reduce N3 sleep and can actually worsen sleep fragmentation over time. Tolerance builds within weeks. Dependency develops. And the underlying causes of the insomnia remain completely unaddressed. That's why clinical guidelines consistently put CBT-I ahead of pharmacotherapy as initial treatment.
Sleep-Disordered Breathing
Obstructive sleep apnea (OSA) affects roughly 10 to 15 percent of adults in many industrialized countries, though detection rates remain embarrassingly low. The condition occurs when the upper airway collapses repeatedly during sleep, causing oxygen desaturations and micro-arousals that fragment sleep. The classic triad is loud snoring, witnessed apneas, and excessive daytime sleepiness. But the presentation is far from uniform. Some people with severe OSA have none of those symptoms. They present instead with treatment-resistant hypertension, morning headaches, or nocturia. A diagnostic sleep study measures apnea-hypopnea index (AHI), which counts the number of complete breathing pauses (apneas) and partial reductions (hypopneas) per hour of sleep. An AHI below 5 is normal. Between 5 and 15 is mild, 15 to 30 is moderate, and above 30 is severe. Severity matters less than you might think for treatment decisions—some patients with mild OSA have significant cardiovascular consequences while others with severe OSA tolerate it surprisingly well. The presence of comorbidities like hypertension, atrial fibrillation, or metabolic syndrome often drives the urgency more than the AHI number alone. Continuous positive airway pressure (CPAP) is the gold standard treatment, and it works well when patients actually use it. The adherence data is brutally honest: roughly 40 to 60 percent of patients discontinue CPAP within a year. The reasons are mundane but real—mask discomfort, skin irritation, difficulty exhaling against pressure, noise complaints, and the general hassle of managing equipment. When CPAP fails, alternatives include mandibular advancement devices for mild to moderate OSA, weight loss programs, positional therapy for patients whose apnea is primarily supine-dependent, and in select cases, surgical interventions like hypoglossal nerve stimulation.
Circadian Rhythm Disorders
These disorders occur when your internal clock is misaligned with the social and environmental demands placed on you. Delayed sleep-wake phase disorder is the most common form I encounter. People with DSPD have a biological sleep window that falls much later than conventional schedules allow—often around 2 AM to 10 AM or later. They can sleep perfectly fine if given the opportunity but cannot fall asleep earlier no matter how hard they try. This is not laziness. This is a genuinely shifted circadian phase that shows up clearly on melatonin onset testing and actigraphy recordings. Treatment involves timed light exposure and melatonin administration. Morning bright light therapy pushes the phase earlier, while evening melatonin at low doses (0.5 to 3 mg) helps advance the sleep window. The protocol needs to be consistent for at least two to three weeks before meaningful improvement shows up. I've watched patients who gave up after a few days—because the effect isn't instantaneous—finally succeed when they stuck with it long enough for the phase shift to accumulate.
Restless Legs Syndrome
Restless legs syndrome (RLS), also called Willis-Ekbom disease, causes an irresistible urge to move the legs, usually accompanied by uncomfortable sensations. The symptoms worsen during periods of rest and in the evening. It affects roughly 5 to 10 percent of the population and is frequently misdiagnosed as growing pains, arthritis, or simple anxiety. The diagnostic criteria are specific: an urge to move accompanied by uncomfortable sensations, beginning or worsening during rest, relieved by movement, and worse in the evening. Secondary RLS is surprisingly common and often overlooked. Iron deficiency is the leading cause—I check ferritin levels on essentially every RLS patient. When ferritin falls below 75 micrograms per liter, RLS symptoms tend to flare regardless of other treatment. Iron supplementation at 65 to 100 mg of elemental iron taken with vitamin C on an empty stomach can resolve symptoms in deficient patients within weeks. Beyond that, dopamine agonists like pramipexole and ropinirole are effective, though I tend to reserve them because long-term use can cause augmentation, where symptoms actually worsen and spread to other body parts.
Parasomnias and Movement Disorders During Sleep
Parasomnias are unwanted experiences or behaviors that occur during sleep. REM sleep behavior disorder is one I take seriously because it's often a harbinger of neurodegenerative disease. Patients physically act out their dreams instead of being paralyzed during REM sleep. A man who's been sleepwalking and throwing punches at imaginary opponents is not just a hazard to his bed partner—he has a significant probability of developing Parkinson's disease or Lewy body dementia within the next decade. That association is strong enough that neurologists treat RBD as a prodromal marker. Night terrors, sleep walking, and confusional arousals are more common in children and usually resolve on their own. When they persist into adulthood or pose a safety risk, benzodiazepines at bedtime can reduce their frequency, though the goal is always to address underlying sleep fragmentation that triggers them.
How Diagnosis Actually Works
A sleep evaluation starts with a detailed clinical history and sleep diary. I have every patient log their sleep for at least one to two weeks before any testing. The diary reveals patterns that neither the patient nor their partner would normally notice—things like irregular bedtimes, caffeine intake timing, or how alcohol affects their sleep architecture. That data alone often points toward the diagnosis without needing expensive equipment. Polysomnography (PSG) is the overnight sleep study that measures brain waves, oxygen levels, heart rate, breathing, and eye and leg movements. Home sleep apnea testing is now widely available for uncomplicated suspected OSA and covers the essentials—breathing effort, airflow, and oxygen saturation—without measuring brain activity. Actigraphy, a wrist-worn device that tracks movement over days or weeks, helps assess circadian patterns and sleep-wake schedules without the artificial environment of a sleep lab. The Multiple Sleep Latency Test (MSLT) follows an overnight PSG and measures how quickly you fall asleep in quiet sitting positions throughout the day. It's the standard tool for diagnosing narcolepsy and idiopathic hypersomnia. A mean sleep latency under 8 minutes with two or more sleep-onset REM periods indicates narcolepsy. Without the preceding overnight PSG, the MSLT results can be misleading—if you're sleep-deprived from any cause, you'll fall asleep quickly on the test regardless of whether you actually have narcolepsy.

What Can Go Wrong With Self-Diagnosis
Online sleep quizzes and smartphone apps can flag potential problems, but they cannot distinguish between conditions that require very different treatments. Treating presumed insomnia with sleep hygiene advice when the real issue is untreated sleep apnea wastes months and leaves the cardiovascular risks of apnea completely unaddressed. Conversely, getting a full sleep study for what turns out to be a straightforward circadian rhythm issue is expensive and unnecessary. The balance depends on red flags: loud snoring with witnessed apneas, excessive daytime sleepiness that interferes with driving, periodic leg movements, dream-enacting behavior, or insomnia that persists despite good sleep habits and stress management. Effective treatment depends entirely on accurate diagnosis. Here's what the evidence base actually says about the most common interventions: CBT-I is first-line for chronic insomnia and remains effective for patients who've failed medication trials. Sleep restriction therapy, a core component of CBT-I, deliberately limits time in bed to match actual sleep time, building sleep pressure until sleep consolidates. It feels counterintuitive to tell someone who can't sleep to spend less time in bed, but the physiology behind it is sound and well-documented.
CPAP adherence improves dramatically when you address the practical barriers upfront. Mask fitting, pressure ramp features, heated humidification, and regular follow-up calls from a sleep coordinator can push adherence from that rough 40 percent up into the 70 to 80 percent range. If one mask style doesn't work, trying a different one almost always does. The equipment exists in enough varieties that nearly everyone can find something tolerable. Melatonin works best for circadian rhythm disorders at low doses administered at the right time. Higher doses don't produce better results and can cause next-day grogginess. The timing matters more than the dose—taking melatonin two hours before your desired bedtime shifts your phase, while taking it at midnight when your body is already producing melatonin does nothing. Dopamine agonists and alpha-2-delta ligands (gabapentin, pregabalin) are the main pharmacological options for RLS. Gabapentin enacarbil, approved specifically for RLS, has become a preferred first-line option in many guidelines because it avoids the augmentation risk associated with dopamine agonists. Iron replacement should come first if ferritin is low, before any of these medications are considered.
When to Seek Professional Help
Professional evaluation becomes necessary when sleep problems persist beyond a few weeks, interfere with daytime functioning, or involve any of the red flags mentioned earlier. A primary care physician can initiate basic workups including blood tests for thyroid function, iron studies, and metabolic panels. Referral to a sleep specialist is appropriate when the diagnosis is unclear, when OSA is suspected, or when first-line treatments have failed. The American Academy of Sleep Medicine maintains a directory of board-certified sleep medicine physicians. Sleep labs vary significantly in quality, and not all hospitals offer comprehensive testing. If you're referred for a sleep study, ask what type of study will be performed, who interprets the results, and what follow-up process looks like. A 45-minute read of a sleep study by someone who isn't sleep-trained misses details that change treatment decisions.

Prevention and Maintenance
Sleep hygiene education—consistent schedule, dark quiet cool bedroom, limited screen time before bed, avoiding caffeine late in the day—is foundational but insufficient as a standalone treatment for established disorders. It works best as prevention and as an adjunct to active treatment. Most people who improve their sleep hygiene alone are still dealing with an underlying disorder that needs targeted intervention. Regular exercise improves sleep quality in people with insomnia, reducing sleep onset latency by roughly 10 to 15 minutes in most studies. The timing matters—vigorous exercise within three hours of bedtime can actually worsen sleep for some people. Light to moderate exercise earlier in the day tends to be most beneficial. Managing comorbid conditions is often the most impactful thing you can do. Untreated depression and anxiety are the two biggest contributors to chronic insomnia. Gastroesophageal reflux can cause micro-aspirations that fragment sleep without causing noticeable heartburn. Nocturia from an enlarged prostate or uncontrolled diabetes shatters sleep continuity. Addressing these conditions alongside any primary sleep disorder routinely produces better outcomes than treating the sleep problem in isolation.

