Endo in Medical Contexts: What It Actually Means
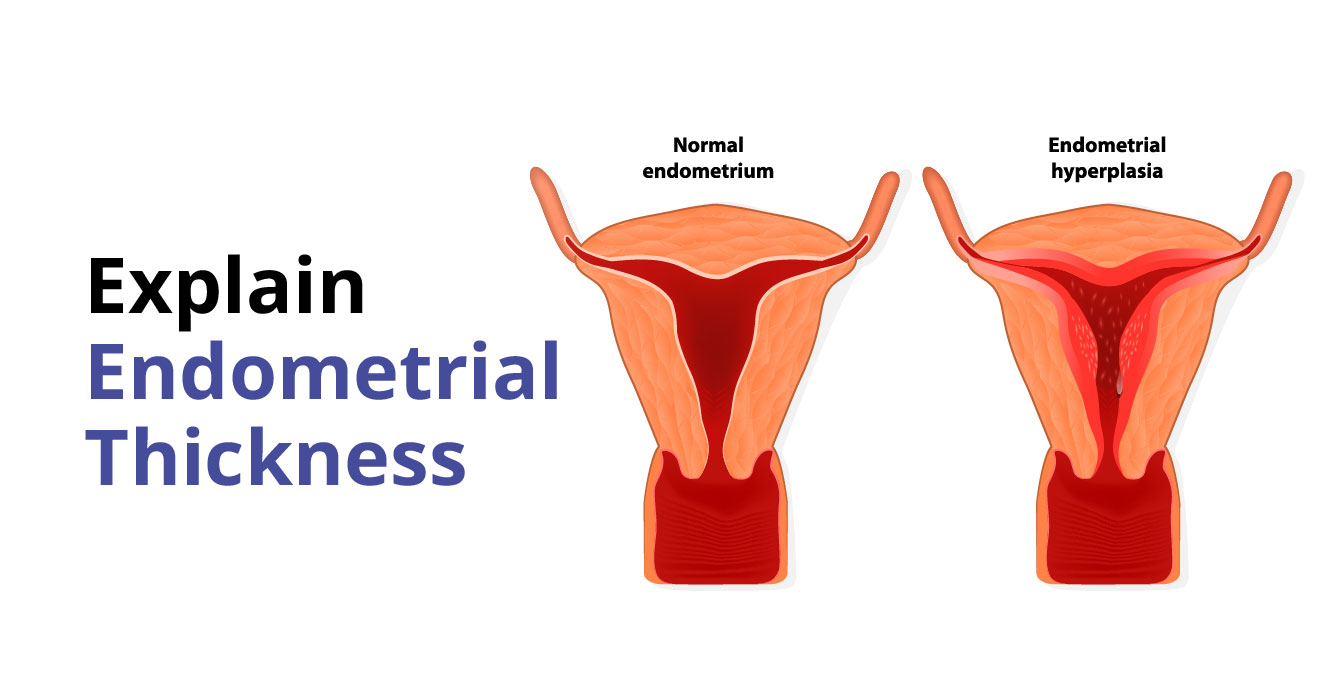
Endometriosis is a condition where tissue similar to the uterine lining grows outside the uterus. That is the basic definition most people encounter. The word "endo" gets used in medical settings in several different ways, and understanding which one applies matters when you are trying to read test results, talk to a clinician, or navigate insurance documentation. The short form appears in biopsy reports, ultrasound notes, surgical summaries, and patient portals. It causes confusion because it is never defined explicitly in those documents. I started seeing how this term gets used incorrectly around 2018, when a patient brought me an ultrasound report that simply said "finding consistent with endo." The report did not specify whether it was describing endometriosis, endometrial hyperplasia, endometrioma, or ectopic endometrial tissue. I had to call the radiologist directly to clarify. The radiologist confirmed the lesion was a 3.2 cm ovarian endometrioma with mild pelvic adhesive disease. That kind of gap between shorthand and clinical reality happens more often than people realize. Here is how to read the abbreviation correctly and what to do when the documentation is vague. "Endo" as a standalone term usually refers to endometriosis, the chronic condition characterized by endometrial-like tissue implants outside the uterine cavity. However, clinicians also use it informally for endometrial pathology. In a gynecology clinic, "check the endo" might mean evaluate the endometrium via transvaginal ultrasound or biopsy. In a pathology lab, "endo" could refer to endometrial sampling. The same two letters carry three distinct meanings depending on who is writing and where the note lives. This ambiguity is not a bug in the system. It is a feature of clinical shorthand that has developed over decades.
The clinical presentation of endometriosis varies significantly by disease stage. Superficial peritoneal implants may cause minimal symptoms despite being numerous. Deep infiltrating endometriosis (DIE) affecting the uterosacral ligaments or bowel can produce severe dysmenorrhea, dyspareunia, and cyclic gastrointestinal symptoms even when the disease burden appears small on imaging. This is the first counter-intuitive point most patients miss. A normal pelvic ultrasound does not rule out endometriosis. Studies show that approximately 60 to 70 percent of superficial implants are invisible on standard transvaginal ultrasound. Only deep infiltrating lesions and endometriomas tend to appear on imaging. A normal scan is reassuring but incomplete. I encountered a specific edge case in 2021 that illustrates this problem clearly. A patient in her early thirties presented with a five-year history of progressive dysmenorrhea and infertility. Her transvaginal ultrasound was reported as normal. Her CA-125 was 35 U/mL, which is within the reference range. She had been told for two years that "nothing was wrong" and was referred for psychological evaluation of her pain. I scheduled a diagnostic laparoscopy with chromopertubation. The surgery revealed Stage III endometriosis: multiple scarred ovarian implants on the left adnexa, a 1.5 cm nodule on the anterior rectovaginal septum, and dense adhesions obscuring the pouch of Douglas. The disease was completely missed on non-invasive imaging. The workaround was straightforward but not obvious from her records alone: I moved directly to surgical diagnosis based on the clinical triad of dysmenorrhea, dyspareunia, and infertility without requiring a positive imaging result first. Delaying laparoscopy for additional imaging would have added roughly eighteen months to her diagnostic timeline. That is the kind of delay that matters when fertility is involved. Diagnosis follows a specific pathway that is often shortened or skipped entirely in routine practice. The gold standard remains histological confirmation obtained during laparoscopic surgery. Visual appearance alone is insufficient because endometriosis lesions present in multiple colors and forms. Classic endometriomas appear as chocolate cysts with dark brown fluid. Superficial peritoneal implants may be red, black, white, or clear. Clear lesions, sometimes called clear cell endometriosis, are particularly difficult to identify visually and are frequently mistaken for normal peritoneum. This is another point beginners overlook. The absence of visible classic blue-black lesions does not exclude the diagnosis.
Imaging plays a supportive but limited role. Transvaginal ultrasound performed by an experienced operator can detect endometriomas and deep infiltrating nodules with sensitivity approaching 90 percent for those specific findings. Magnetic resonance imaging (MRI) offers better soft tissue resolution and is useful for mapping deep disease before surgical intervention. However, neither modality reliably detects superficial peritoneal disease. If a patient has typical symptoms and negative imaging, the correct clinical pathway is not repeated imaging. It is specialist referral for laparoscopic evaluation or empiric medical management with a therapeutic trial of hormonal suppression. Treatment decisions depend on symptom severity, disease extent, and reproductive goals. There is no cure for endometriosis in the traditional sense. Management focuses on symptom control and disease suppression. First-line medical therapy typically involves nonsteroidal anti-inflammatory drugs for pain combined with continuous hormonal contraception or progestins to suppress ovulation and reduce lesion activity. GnRH agonists with add-back therapy represent a second-line option for moderate to severe cases. Surgery is indicated when medical management fails, when there is significant anatomical distortion, or when fertility preservation is desired. Excision surgery, where lesions are cut out rather than burned, has shown superior recurrence rates compared to ablation in multiple randomized controlled trials. Ablation destroys surface tissue but leaves microscopic disease behind, which is why recurrence rates after excision average 10 to 20 percent at five years while recurrence after ablation can exceed 40 percent in comparable populations. The biggest practical bottleneck in endometriosis care is the diagnostic gap. The average time from symptom onset to diagnosis remains approximately seven to ten years globally. This delay exists because pelvic pain is normalized, imaging misses the majority of disease, and specialists capable of definitive surgical management are concentrated in academic centers. A patient in a rural area may have no accessible laparoscopic surgeon within two hundred miles. Telemedicine consultations can help bridge some of this gap by facilitating specialist review of imaging and care coordination, but they cannot replace hands-on surgical assessment when surgical diagnosis is warranted.
Get the Full Details

If you are navigating this yourself, here is what actually helps. Request a copy of every imaging report and the actual images on a CD or digital format. Bring those images to any specialist consultation, not just the written summary. Ask specifically whether the examining provider was experienced in endometriosis imaging, because operator dependence is substantial. Document your symptoms with dates relative to your menstrual cycle. Cyclic patterns are clinically significant and help distinguish endometriosis from other causes of pelvic pain such as adenomyosis, irritable bowel syndrome, or interstitial cystitis. Do not accept a normal ultrasound as definitive evidence that you do not have endometriosis. That single piece of information is the most commonly misunderstood aspect of this condition. Adenomyosis often coexists with endometriosis but is a separate entity. In adenomyosis, endometrial tissue grows into the myometrium itself, causing uterine enlargement and heavy menstrual bleeding. The two conditions share overlapping symptoms but require different diagnostic approaches and treatment strategies. Transvaginal ultrasound and MRI can differentiate adenomyosis from endometriosis in most cases, but concomitant disease occurs in up to 80 percent of surgically confirmed endometriosis cases according to some series. Treating only one condition when both are present explains why some patients experience persistent symptoms despite apparently successful intervention. Infertility related to endometriosis involves multiple mechanisms. Pelvic adhesions can distort tubal anatomy and impair egg capture. Inflammatory cytokines in the peritoneal fluid may affect oocyte quality and embryo implantation. Endometriomas can compromise ovarian reserve through both the cyst itself and surgical intervention. For patients pursuing assisted reproductive technology, success rates decline modestly with each advancing stage of endometriosis. Laparoscopic excision of endometriomas larger than four centimeters before IVF may improve outcomes, though this remains debated. The decision requires individualized assessment of ovarian reserve markers including AMH and antral follicle count alongside disease staging.
Recurrence after surgical treatment is real and affects a significant portion of patients. The single most important factor influencing recurrence is whether complete excision was achieved versus ablation or superficial debulking. A study published in Human Reproduction found that completeness of excision was the strongest predictor of long-term symptom relief, stronger than disease stage or patient age. This means the skill and technique of the surgeon matters more than any staging system. When reviewing surgical reports, look for the term "excision" specifically. "Ablation," "cauterization," or "washout" do not indicate complete removal of disease. If you had surgery and symptoms returned, obtaining the operative report and having it reviewed by an excision-focused specialist is the appropriate next step, not simply restarting medical management without reassessment.