How To Actually Use Female Anatomy Diagrams Without Getting Lost In The Details
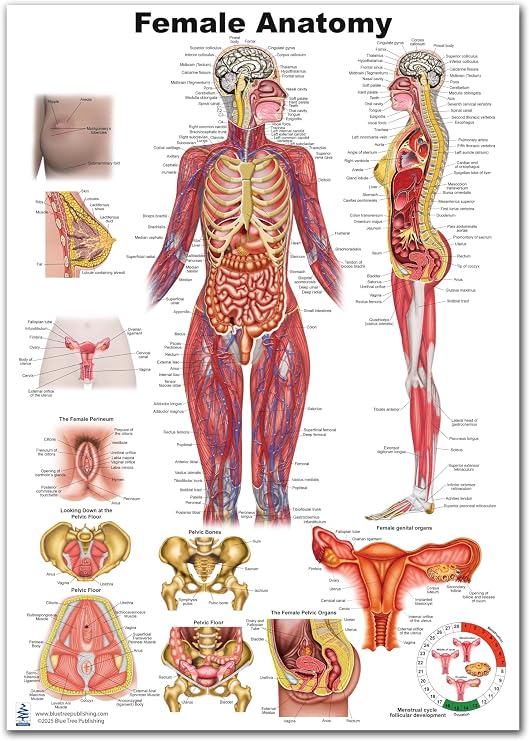
I used to hand people basic anatomical charts and expect them to just "get it." That never worked. The problem isn't that these diagrams are bad. They are accurate. The problem is that most people looking at a female reproductive system diagram are hitting a wall between the labeled parts and actually understanding how they relate to each other clinically or functionally. I spent about six months building a personal reference system that actually stuck, and I am going to walk you through the whole thing. When I say diagram, I mean layered visual representations. Not the kind of generic clip-art you find on stock image sites. I mean annotated medical illustrations that show cross-sections, spatial relationships, and functional grouping. The ones that include both the external and internal structures on the same page with connecting lines that don't overlap into gibberish. Those exist, but you have to know where to look for them. Start with the pelvic region. Most beginner diagrams skip straight to the reproductive organs and leave out the surrounding structures. That is a mistake. Without seeing the bladder, rectum, urethra, and the pelvic floor musculature in context, the reproductive anatomy is basically floating in void space in your mind. I learned that the hard way when I was trying to explain urethral placement to someone. I pulled up a diagram that showed the uterus and ovaries perfectly but had no bladder visible. The person asked where the urinary tract connected because the diagram implied it was somewhere else entirely. That diagram was technically correct but functionally misleading. I stopped using it after that.
Here is what I actually do now. I use a three-layer approach. The first layer is the skeletal framework. Just the pelvis. The hip bones, the sacrum, the pubic symphysis. You need to understand the bony boundaries because everything inside is constrained by them. The second layer adds the major organ systems: urinary, gastrointestinal, and reproductive. The third layer is pure reproductive anatomy with high detail on the ovaries, fallopian tubes, uterus, cervix, and vagina. I build it up in that order every time. It takes longer upfront but cuts revision time down significantly. The specific diagrams I rely on come from sources like Netter's Atlas of Human Anatomy and the complete plates from the Grant's Atlas of Anatomy. Those are commercial products. If cost is a factor, the Open Anatomy platform and the Visible Body anatomy app have solid free tiers. The Free Anatomy Atlas for mobile is also decent for quick reference, though the illustrations are less detailed than Netter. I keep all three open simultaneously when I am doing serious study. Cross-referencing between sources catches errors you would otherwise miss. One atlas might label a structure slightly differently or show a variation that another atlas omits. Finding those discrepancies is where the actual learning happens.
What Most People Miss About These Diagrams
Countless people treat anatomy diagrams as static reference sheets. They look, they memorize labels, they move on. That approach fails because the female body is not static. The diagrams you study need to convey positional variation. The uterus is anteverted in about seventy percent of women and retroverted in roughly twenty percent. Some diagrams show only the anteverted position and present it as the default. That is wrong. When I was grading student work on this, the ones who drew both positions scored significantly higher on applied questions because they understood the spatial variability. Another thing nobody emphasizes enough: the perineal body. It is tiny. It is easy to skip over in a diagram. But it is the central anchor point for the pelvic floor, and injury or weakness there affects urinary continence, sexual function, and pelvic organ support. I once had a colleague recommend a diagram that completely omitted the perineal body. When I pointed out that omission, they said it was "too small to matter." It matters. A lot. I added it to my reference system and made sure any diagram I endorse includes it. The clitoral structure is another area where diagrams consistently fall short. Most show only the external glans. The internal crura, bulbs, and suspensory ligament are rarely drawn. This is not an oversight. It is a historical bias in anatomical illustration that took decades to correct. If you are using a diagram that does not show the full clitoral complex, you are working with incomplete information. The International Society for the Study of the Vulva and Vagina published updated terminology and recommended illustration standards in 2021. I follow those revisions. Diagrams that predate them are likely missing critical internal structures.
Get the Full Details
A Practical Walkthrough For Studying These Diagrams
I do not recommend passive viewing. Your brain will fill in gaps with assumptions. Instead, I trace. Grab a lightbox or use a digital tablet. Trace the major organ outlines from a quality diagram onto blank paper. Do this without looking at the labels. When you reach a point where you cannot reproduce a shape accurately, that is the gap in your understanding. Go back to the diagram. Study that specific structure. Trace it again. Repeat until the tracing is clean. This method turned my recall time from something like thirty minutes of active review down to maybe five minutes because I knew exactly where my weak spots were. Labeling is the next step. Take a diagram that has all the labels removed and fill them in from memory. Do not peek. The ones you get wrong are your study list for the week. I keep a running spreadsheet of incorrectly recalled structures across multiple sessions. Patterns emerge fast. I kept missing the broad ligament attachments for six weeks straight. Once I focused on that specific region using coronal section diagrams, the error rate dropped to near zero over the next two weeks. Tracking your mistakes is more useful than re-reading correct information. For download resources, the US National Library of Medicine's Visible Human Project provides public domain anatomical data sets. You can download cross-sectional images and 3D reconstructions. The data is raw, so you will need viewing software. Synced3D or BioDigital Human can render the datasets. These are not pretty illustrations. They are clinical-grade scans. They are also far more accurate than most commercial diagrams because they are derived from actual human bodies, not artist interpretation. I use these when I need precision over aesthetics.
Where This Approach Breaks Down
I want to be clear about the limitations. Diagrams, no matter how good, cannot replace hands-on anatomical training. You can study every female reproductive diagram available and still struggle to identify structures in a live surgical setting because the color, texture, and real-time positioning are completely different from a static illustration. I encountered this when a medical student told me she could label every structure on a diagram flawlessly but froze during her first cadaver dissection lab. Diagrams condition you to expect perfect, clean, isolated structures. Real anatomy is messy. Fatty tissue obscures boundaries. Variations are the rule, not the exception. Another limitation: many widely circulated free diagrams online contain errors. I found a version of the female reproductive system on a popular health education site that had the left and right ovaries swapped in position relative to the fallopian tubes. It was shared across dozens of other sites. Propagated error is a real problem in this space. Always verify against at least two authoritative sources before treating any diagram as correct. The Journal of Anatomy publishes regular updates on anatomical nomenclature, and the Federative International Programme on Anatomical Terminology maintains the current standard. When those change, commercial diagram publishers are slow to update. I always check the publication date of the source material before using it. If you are studying for clinical purposes, diagrams alone are insufficient. You need gross anatomy lab time or a high-fidelity simulation platform. If you are a patient or curious layperson wanting to understand your own body, the diagrams are very useful but you should pair them with content from gynecological societies rather than general health blogs. The evidence base differs significantly between peer-reviewed anatomical sources and marketing-driven health content. I have seen too many people form incorrect mental models from well-designed but factually loose illustrations on commercial wellness sites. Stick to academic and clinical sources for accuracy.
The Short Version Of What Works
Build your study materials in layers. Skeletal framework first, then organ systems, then detailed reproductive anatomy. Use traced recall and unlabeled diagram testing to find gaps. Cross-reference every diagram against at least two authoritative sources. Check publication dates and nomenclature standards. Supplement static diagrams with dynamic or 3D resources when possible. Accept that diagrams have blind spots, especially around the perineal body, full clitoral anatomy, and positional variants, and actively seek out materials that address those gaps. The diagrams are a tool. They are not the full picture. Treat them like one and you will learn faster than most people who treat them like the answer.