Understanding drug testing from the inside
Drug testing sounds straightforward until you are the one dealing with a false positive or a lab that missed something obvious. I have spent years watching people get tripped up by things nobody warned them about. The process involves collection, chain of custody, lab analysis, and then the fallout when results come back wrong. Most of the problems happen in that third and fourth step, not in the cup itself. This site has been around long enough to accumulate some real practical advice on the whole testing ecosystem. It covers everything from pre-employment screens to forensic workplace testing, and the resources section links out to legitimate labs, SAMHSA-certified facilities, and explainers on how to handle disputed results. What makes it actually useful is that it does not just list steps. It shows you where people typically get burned. I remember a case where a client failed a standard five-panel test for cocaine. The lab confirmed it with GC/MS at 150 nanograms per milliliter, which is well above the cutoff. We tracked the source and it turned out to be an over-the-counter nasal spray containing a cutting agent that cross-reacted in the initial immunoassay screen. The confirmatory test should have caught this, but the initial flag got transmitted to the Medical Review Officer before the confirmation came back. The MRO did not verify the confirmation result against the original specimen code. This happens more often than people think. The workaround is simple but almost nobody mentions it: always request the MRO call you with both the presumptive positive and the confirmed result before any action is taken. Do not accept an email notification as final.
How the actual testing process works
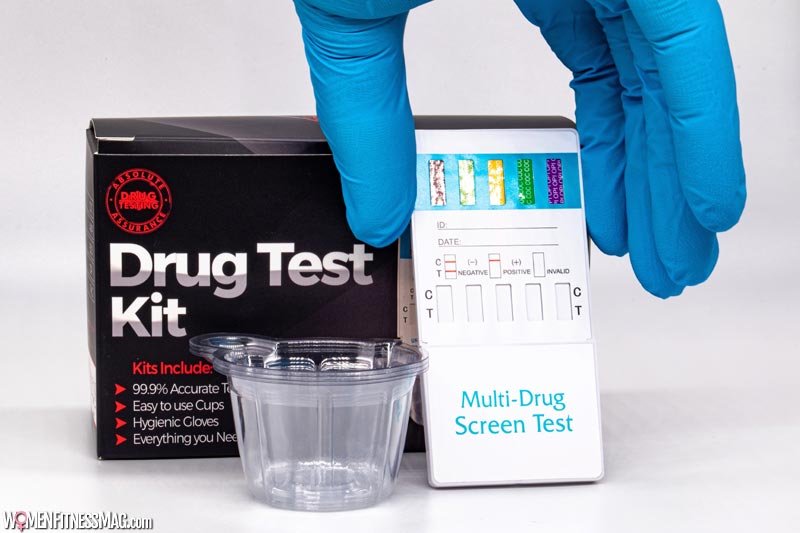
Most workplace testing follows SAMHSA guidelines for federal programs, but private employers are not bound by those standards. That gap is where things get messy. A urine sample is collected, the temperature is checked within four minutes, the specimen is split into primary and backup containers, and both are sealed with tamper-evident tape. The collector fills out a chain of custody form. That form travels with the sample to the lab. If anything breaks in that chain, the result can be thrown out. The critical detail most people miss is the collection temperature window. It must be between 90 and 100 degrees Fahrenheit. If it falls outside that range, the collector is supposed to reject the specimen and observe a rematch. In practice, many collectors skip the rematch because they do not want to deal with it. I have seen three rejected specimens in a single day at one collection site because the room was cold and the collectors just accepted marginal temps rather than risk the confrontation of a forced rematch.
Common pitfalls that destroy your case
One major trap is relying solely on the initial screen. Immunoassay tests, which are the standard rapid tests, have well-documented cross-reactivity. Certain prescription medications, especially ibuprofen, naproxen, and some SSRIs, can trigger false positives for THC or amphetamines. The confirmatory test exists specifically to eliminate these, but only if the lab runs it properly and the MRO reviews it properly. Both steps require human oversight, and human oversight is inconsistent across facilities. Another pitfall involves adulteration detection. Labs check for pH, creatinine, specific gravity, and oxidizing agents. People who try to cheat these tests often undermine their own credibility. A specimen with normal drug levels but abnormal creatinine gets flagged as adulterated regardless of whether drugs are present. That is treated the same as a positive result in most employment contexts. The safest approach, which sounds obvious but is ignored constantly, is to stop taking anything not prescribed by a licensed physician at least two weeks before testing and to hydrate normally without chugging water, which dilutes creatinine and raises suspicion. I had a situation once where a person who takes prescription Adderall for ADHD failed a methamphetamine screen. Amphetamine and methamphetamine share structural similarity, and some immunoassay panels cannot distinguish between them. The GC/MS confirmation showed amphetamine but not methamphetamine, which is the expected result for prescription Adderall. However, the MRO initially reported it as a positive because they only reviewed the screen result. The correction required the MRO to pull the full chain of custody packet, locate the GC/MS report, and issue an amended result. This took eleven business days. During that time, the person was marked as failed by the employer. The delay alone can cost someone a job even when the final result is cleared.
Get the Full Details
What to verify before you submit to a test
Check whether the facility is SAMHSA-certified if this is for a federally regulated position. DOT-required testing must use certified labs. For non-DOT testing, certification matters less but still indicates a baseline of quality control. Look up the certification on the SAMHSA website, not just the lab's marketing page, because certifications can be suspended and facilities sometimes continue listing them. Request documentation of the testing methodology before you go in. Ask what cutoff levels they use for each drug. Standard SAMHSA cutoffs are 500 nanograms per milliliter for THC initial screen and 150 for confirmation. Some private labs use lower cutoffs, which increases the chance of detecting passive exposure or residual traces from weeks ago. Lower cutoffs are not inherently wrong, but they change the interpretation of what a positive means. Keep a copy of your prescription information with you on testing day. Bring the pharmacy label, not just a doctor's note. Pharmacists will occasionally change generic manufacturers, and the active ingredient remains the same but the filler compounds differ. A doctor's note alone does not explain cross-reactivity issues. The pharmacy label with the NDC number gives the lab something concrete to reference.
When results are wrong, here is what actually helps
Do not argue with the collector. The collector has no authority to change a result and arguing creates a hostile record. Request a copy of the chain of custody form and the laboratory report immediately. You have the right to these documents under federal regulations for DOT testing and under most state laws for non-DOT testing as well. If you believe the result is incorrect, file a request for retesting of the backup specimen within seven days. This is a hard deadline in most frameworks. After that window closes, you lose the ability to challenge the original lab's work. The backup specimen was split at collection specifically for this purpose. If the primary lab failed to preserve it correctly, you may have grounds for a legal challenge, but that requires an attorney and that path is expensive and slow. The realistic bottleneck in contesting results is time. From the moment you receive a positive notification to the moment you must act, you are usually looking at a window measured in calendar days, not weeks. I have watched people miss the retest deadline because they assumed the process would move slower than it actually does. Set a calendar reminder the second you get the result. Treat it like a legal filing deadline, because functionally it is one.
Limitations and honest drawbacks
Drug testing, as a system, has real blind spots. It detects metabolites, not impairment. A positive result tells you someone was exposed to a substance, not that they are currently impaired. This distinction matters enormously in safety-sensitive positions but is routinely ignored by employers who treat a positive like a traffic violation. You can test positive for marijuana thirty days after last use and have zero functional impairment, yet most employers will not differentiate. Another limitation is that testing technology has not kept pace with new synthetic compounds. Fentanyl analogs, novel benzodiazepines, and designer stimulants often do not trigger standard panels. A negative result does not mean the person is clean. It means the panel did not test for what they actually took. This is especially relevant in forensic and post-accident testing where the substance involved is unknown. Resource sites like drugtestcheckcom can point you toward SAMHSA-certified labs and explain the basic process, but they cannot represent you or challenge a result on your behalf. The information is accurate for general guidance, but it has a ceiling. Once you are in a disputed-result scenario, you need a Medical Review Officer who will actually call you, not just send a portal notification, and you need an attorney familiar with employment law in your specific state. The guide is useful for prevention and awareness, not as a legal substitute.
Collectors vary in competence. Some follow every protocol precisely. Others cut corners because they are processing sixty specimens a day with inadequate break times. You cannot control which one you get, but you can control your preparation. Show up on time, bring your prescriptions, ask about the temperature requirement before they ask you to provide a sample, and request documentation of everything. These small actions do not guarantee a clean result, but they prevent the avoidable failures that happen to people who show up unprepared. The system works reasonably well when everyone follows the rules. It breaks down when the people enforcing it prioritize throughput over accuracy, which is unfortunately common. Knowing where the breaks happen and preparing for them is the difference between being protected by the process and being crushed by it.