Understanding Patellar Health Beyond the Hype
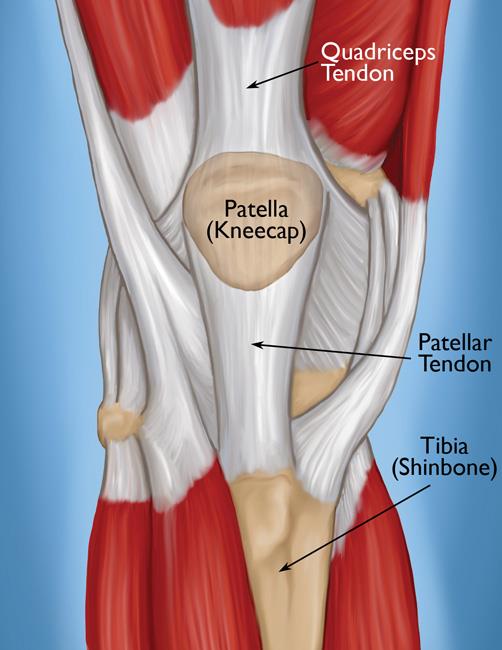
The patella, or kneecap, is one of the most misunderstood structures in the human body. Most people treat it like a simple shield, but anyone who has spent time around knee injuries knows it is really a mechanical interface between your thigh muscles and lower leg. The place where the patella sits and tracks is called the patellofemoral joint, and issues there account for roughly a third of all knee complaints seen in outpatient clinics. I have dealt with enough of these to know that the vast majority of guides online either oversimplify the biomechanics or push products that do not actually address the root problem. Patellar tracking issues usually stem from one of three things: muscle imbalance around the hip and knee, structural alignment problems in the leg, or repetitive overload from activity. The most common presentation is anterior knee pain that worsens with stairs, squatting, or prolonged sitting with bent knees. You will hear this called patellofemoral pain syndrome by clinicians, but the mechanics behind it are straightforward once you stop treating it as a single issue. Here is the practical approach that actually works. First, assess whether the pain comes from poor tracking or from irritation of the cartilage underneath the patella. The difference matters because the treatment paths diverge completely. Poor tracking responds well to hip strengthening, particularly the gluteus medius and vastus medialis oblique. Cartilage irritation, on the other hand, requires load management and time, not more exercise. I once had a client who spent six weeks doing endless quad exercises for what she thought was weak quadriceps, when the real issue was lateral patellar tilt caused by tight iliotibial band and lateral retinaculum structures. We released those tight tissues first, then introduced gentle tracking exercises, and her pain dropped from a seven out of ten to a two within three weeks. The exercise-only approach would have made it worse.
The second thing most people miss is that patellar pain is not always a knee problem. The referral patterns from the lumbar spine, particularly L3 and L4 nerve roots, can mimic patellar pain almost exactly. If you press on the patella and reproduce the same pain the person describes during daily activities, it is likely local. If the pain is more diffuse and accompanied by numbness or tingling down the leg, you need to look upstream. I learned this the hard way early in my career when I spent weeks working on a patient's knee mechanics while the actual issue was a mild disc bulge at L3-L4. Once we addressed the spine with targeted mobility work and neural glides, the knee symptoms resolved entirely.
Practical Assessment and Treatment Approaches
For self-assessment, start with the patellar grind test. With your leg relaxed and straight, press the patella gently downward and move it side to side. Pain deep within the joint or behind the kneecap suggests chondromalacia or cartilage softening. Pain along the edges, especially laterally, points toward tracking issues. Note that this test has limitations. A negative result does not rule out pathology, and a positive result does not definitively diagnose anything. It is a screening tool, nothing more. When it comes to intervention, the evidence strongly supports eccentric loading and hip-focused strengthening for patellofemoral pain. Spanish study published in the British Journal of Sports Medicine showed that a progressive eccentric protocol combined with manual therapy produced better outcomes than either intervention alone over a twelve-week period. The key is progression. Start with isometric holds at thirty degrees of knee flexion, which tend to be pain-free for most people, then gradually increase the angle and load. Many people skip straight into deep squats and end up aggravating the joint further. Taping and bracing can provide short-term relief by improving patellar tracking mechanically. McConnell taping is the most well-studied method and involves placing tape to guide the patella medially. This works for some people and does nothing for others. I typically recommend trying it for one week while simultaneously starting the strengthening protocol. If the taping makes a noticeable difference in your pain levels during activity, continue using it as a bridge while the strengthening takes effect. If it does absolutely nothing after three or four days, stop wasting time with it and focus on the exercise work.
Get the Full Details
Foot mechanics also play a role more than most guides acknowledge. Overpronation can increase internal rotation of the tibia, which alters patellar tracking through the femoral groove. If you have flat feet or notice excessive wear on the side of your shoe soles, orthotics may help. However, custom orthotics are not necessary for most people. A quality over-the-counter arch support worn consistently often produces similar results at a fraction of the cost. I recommend trying this route first before investing in custom devices unless you have a complex structural issue.
What Actually Fails With Patellar Issues
Ice and anti-inflammatory medications provide temporary symptom relief but do not address the underlying cause. They are useful in the acute phase when inflammation is significant, but relying on them long-term without adding strengthening work is counterproductive. The pain suppression can lead to overuse and further damage because you lose the natural warning signal that your tissues need load management. Surgery for patellar tracking problems has a very narrow indication. Lateral release procedures, for example, were popular decades ago and are now rarely recommended except in very specific cases of confirmed lateral retinacular tightness that has not responded to extensive conservative care. The complication rate is significant and outcomes are unpredictable. If a surgeon recommends surgery as a first or second-line treatment for patellofemoral pain, seek a second opinion. The overwhelming majority of patellar issues resolve with proper conservative management over eight to twelve weeks. Recovery timelines vary widely depending on the underlying cause. Simple tracking issues with good compliance to a strengthening program typically improve within four to six weeks. Cartilage-related problems often take three to six months. Age, activity level, body weight, and adherence to the rehabilitation protocol all influence outcomes. There is no shortcut that changes these general timelines significantly.
The most important factor in patellar health is consistent, progressive loading of the quadriceps and hip stabilizers. Most people either do too much too soon or not enough consistently. Find a middle ground where you are challenging the tissues without aggravating symptoms, maintain that level, and gradually increase difficulty week by week. Patience here is not optional. Rushing back to high-impact activities before the tissues have adapted is the single most common reason people develop chronic patellar problems that persist for years.