Why Most People Skip Labeled Muscle Diagrams (And What They Miss)
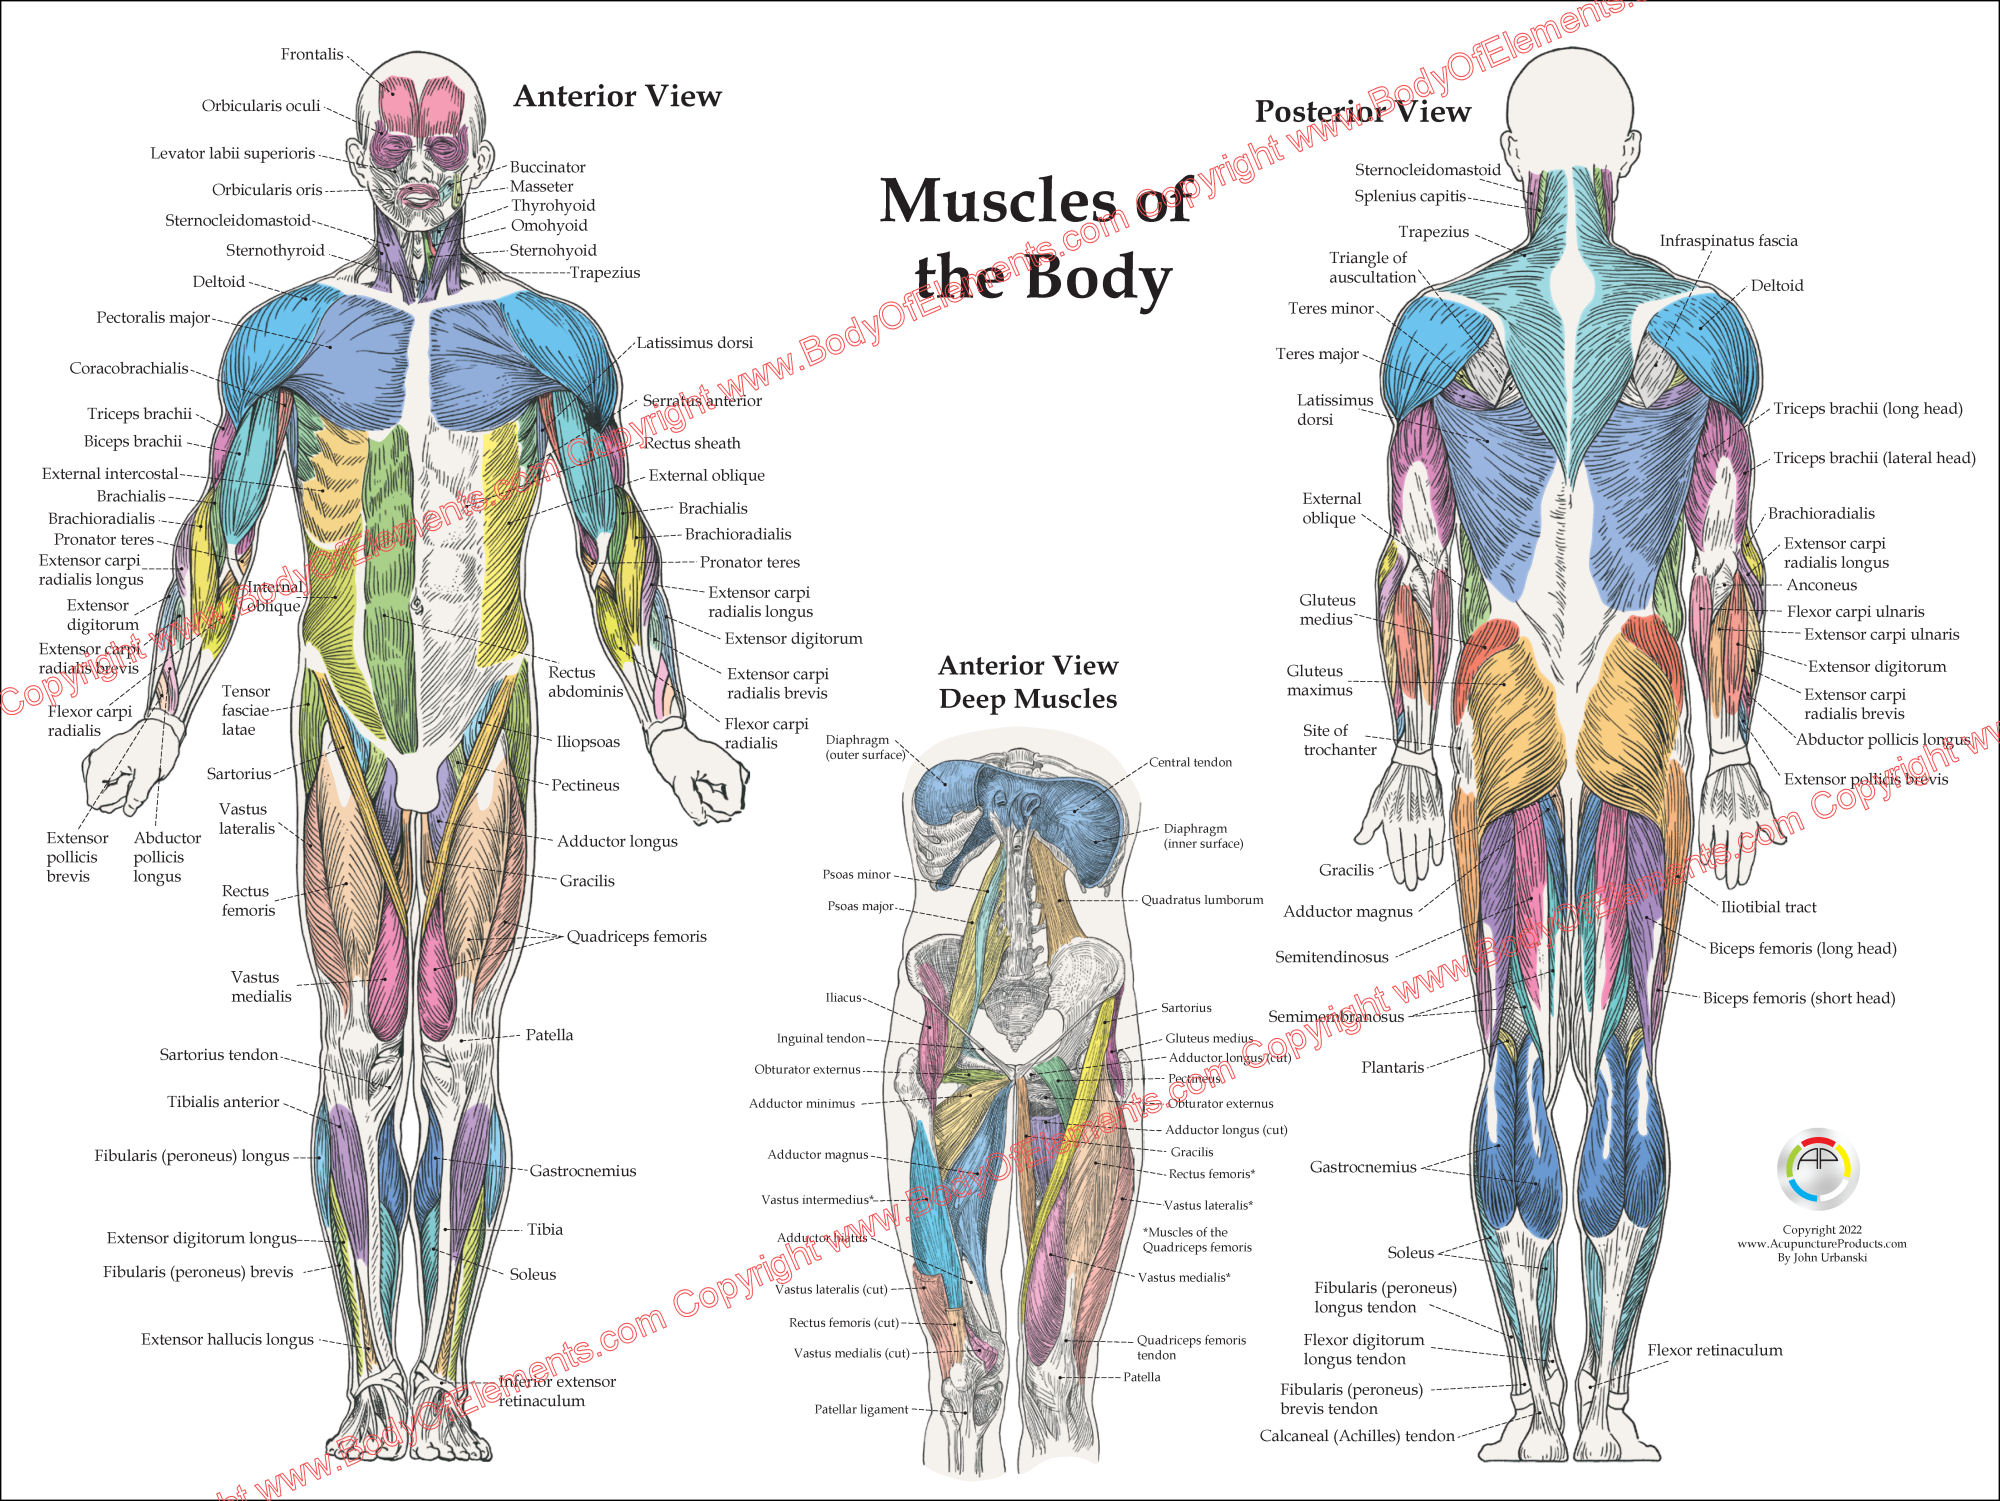
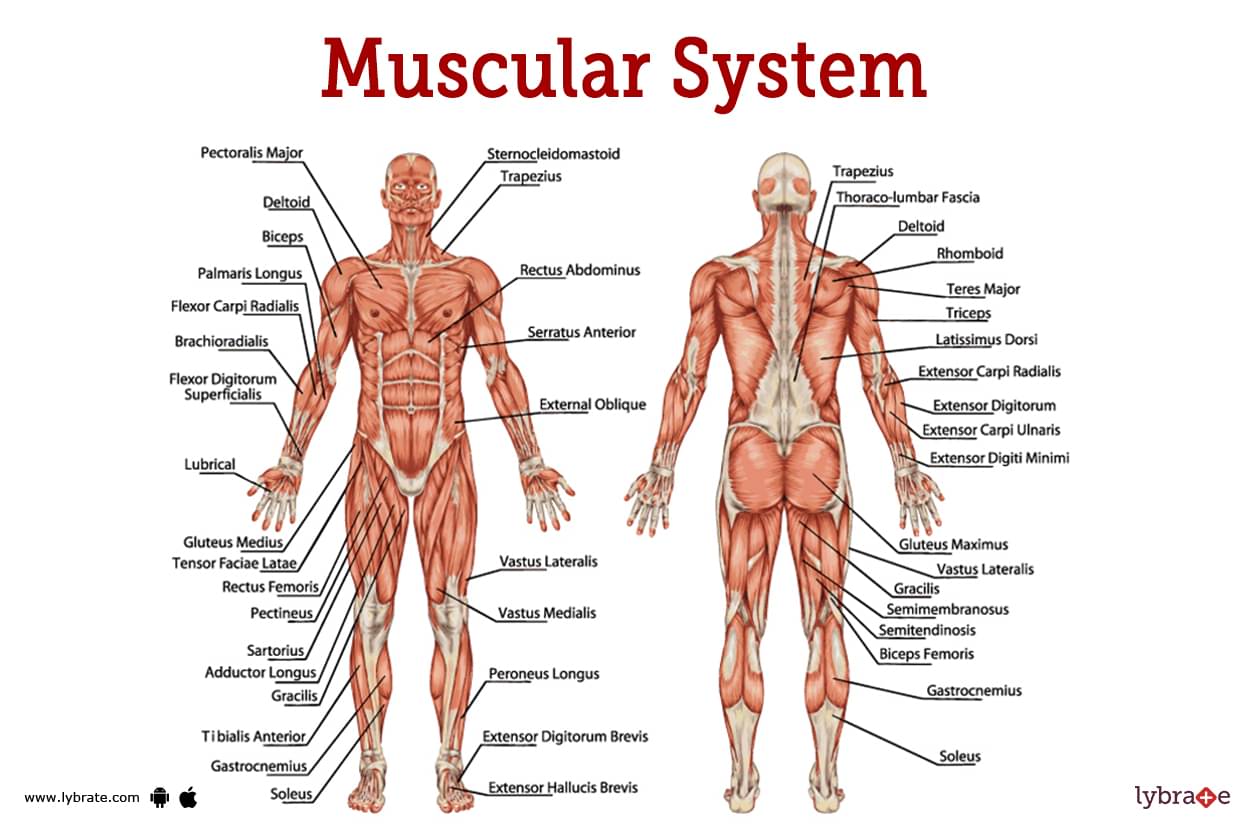
I used to think labeled diagrams were for beginners and that anyone with a pulse could find which muscle was which by just squinting at a picture long enough. That lasted about three weeks. I was working on a post-op recovery plan for a patient who kept calling the deltoid insertion "the shoulder bump area" and couldn't point to it on anything but a photo of a bodybuilder. That's when I realized how much ground we were covering without proper anatomical reference material. Labeled muscle diagrams are actually the backbone of everything from physical therapy documentation to sports medicine consultations, and honestly, most guides out there don't explain why the labels matter or how to use them past the surface level. Here's the thing nobody tells you about labeled diagrams. The labels themselves aren't the valuable part. It's the relationships between labels that make these tools useful. A diagram showing the trapezius sitting above the rhomboids means something totally different than two boxes side by side with no spatial context. When you're actually using these for clinical work or training purposes, you need to understand origin, insertion, and action — not just names. I've seen too many people memorize muscle groups without understanding why the serratus anterior gets labeled as both a scapular stabilizer and an accessory breathing muscle depending on how the diagram is constructed. The standard approach most people encounter online involves static images with callout lines. Fine for a one-time look. Useless if you're building a practice around anatomical literacy. The better approach is interactive layered diagrams where you can toggle superficial versus deep layers on and off. The latissimus dorsi hides half the thoracic wall beneath it. If you're only looking at a superficial view, you're learning an incomplete picture. I switched to layered diagrams about four years ago and the time it took me to locate a specific muscle during patient discussions dropped from maybe thirty seconds to under five.
How To Actually Use These Diagrams (Not Just Bookmark Them)
Download the diagram set and don't just open it once. Set up a reference workflow. I keep mine organized by region — upper extremity, lower extremity, trunk, head and neck. Within each region, I sort by function: movers, stabilizers, and accessories. This matters more than alphabetical order because it mirrors how clinicians and trainers actually think about these muscles. When someone comes in with shoulder impingement, I'm not looking for "b" muscles. I'm looking at the rotator cuff group and the scapular stabilizers together, cross-referencing their attachments on the diagram. One practical method I use consistently is the trace-back technique. Pick a point of pain or a movement limitation. Find the muscle attached there on the diagram. Then trace the line of pull to its origin. Usually the real issue sits at the origin or along the mid-belly, not at the attachment point the patient is pointing to. I did this with a client who had chronic lateral knee pain. The diagram made it obvious the IT band had a direct mechanical line running from the iliac crest through the vastus lateralis. The pain wasn't the problem. The tension chain originating at the hip was. Took us six weeks of addressing the proximal attachments instead of the knee.
Common Pitfalls That Waste Your Time
Most free diagram sets online have at least one of three problems. First, outdated terminology. Some still use "sternocleidomastoid" without noting the two heads separately, which matters for clinical precision. Second, poor resolution. You cannot do detailed work zooming in on a pixelated JPEG from a search result. Third, missing functional annotations. A diagram that shows the quadriceps but doesn't indicate which heads contribute to knee flexion versus extension is less useful than a simpler diagram with those notes included. I ran into a specific issue last year when a trainer sent me a diagram set for her clients and I noticed the gluteus medius and minimus labels were swapped on the lateral hip illustration. She'd been using it for months without catching it. This happens constantly with user-generated diagram collections. Always verify against a standard reference like Netter's or Gray's Anatomy before relying on any diagram set for anything beyond casual study. A mislabeled diagram taught one of her clients the wrong thing about hip abduction mechanics, and correcting that misunderstanding took about twenty minutes of direct explanation.
Get the Full Details

What I Recommend Instead of the Free Stuff
If you need something you can trust in a professional setting, invest in a proper anatomical atlas. Complete Anatomy, Visible Body, or even a solid printed reference like Grant's Atlas will save you hours of double-checking every label. For self-study or light training purposes, the free resources can work if you cross-reference. Download three different diagram sets and compare them. Where they agree, you can trust the information. Where they disagree, dig into a textbook or peer-reviewed source before moving forward. The cost of a proper resource ranges anywhere from a one-time purchase of around forty dollars for a digital atlas to subscription models around ten to fifteen dollars monthly. Compare that to the cost of a single incorrect diagnosis or a training program built on faulty anatomical assumptions. The math is straightforward.
When Diagrams Fall Flat
Here's the honest part. Labeled diagrams cannot teach you palpation. You can memorize every muscle name and location in the human body and still miss the infraspinatus on a live person because the fat distribution and muscle tone change where it sits relative to the bone. I learned this the hard way during a certification workshop where the instructor asked us to locate twelve different muscles on a volunteer blindfolded partner. I got seven right. The diagrams had shown me exactly where everything should be. My hands had no idea what to do with that information. Diagrams also fail you when individual variation comes into play. The brachialis muscle inserts slightly differently in roughly fifteen percent of the population. The pectoralis minor has accessory slips that some people have and others don't. A standardized labeled diagram will show the textbook version. Real bodies don't always cooperate. I've had to adjust my own reference materials when working with clients who had surgical scars, congenital variations, or previous injuries that altered the normal anatomical landmarks. So the practical takeaway is simple. Use labeled diagrams as your foundation. Build palpation skills alongside them. Verify labels against multiple sources. And recognize the limits — a diagram is a map, not the territory. The body doesn't read the labels.