KT Tape on Ankles Is a Mess If You Do It Wrong
I have taped enough ankles to know that most people overcomplicate it. They buy the roll, watch a four-minute YouTube video, and end up with a strip that peels off after twenty minutes or restricts circulation because they pulled too hard. The reality is simpler than the internet makes it look, but you need to get a few mechanics right or you are just wasting money and causing more problems than you solve. The goal of KT tape on an ankle is not to splint it rigid. That is what athletic tape does, and it has its place. Kinesiology tape is meant to provide sensory feedback, lift the skin slightly to improve lymphatic flow, and offer a gentle directional pull that reminds your brain where your joint sits. It will not hold a sprained ankle together. If you have a grade two tear, go see a professional and get properly braced instead of relying on adhesive fabric. The tape is a support aid, not a medical device for acute injuries.
The Ultimate Guide To Kt Taping An Ankle Expert Techniques For Support And Relief
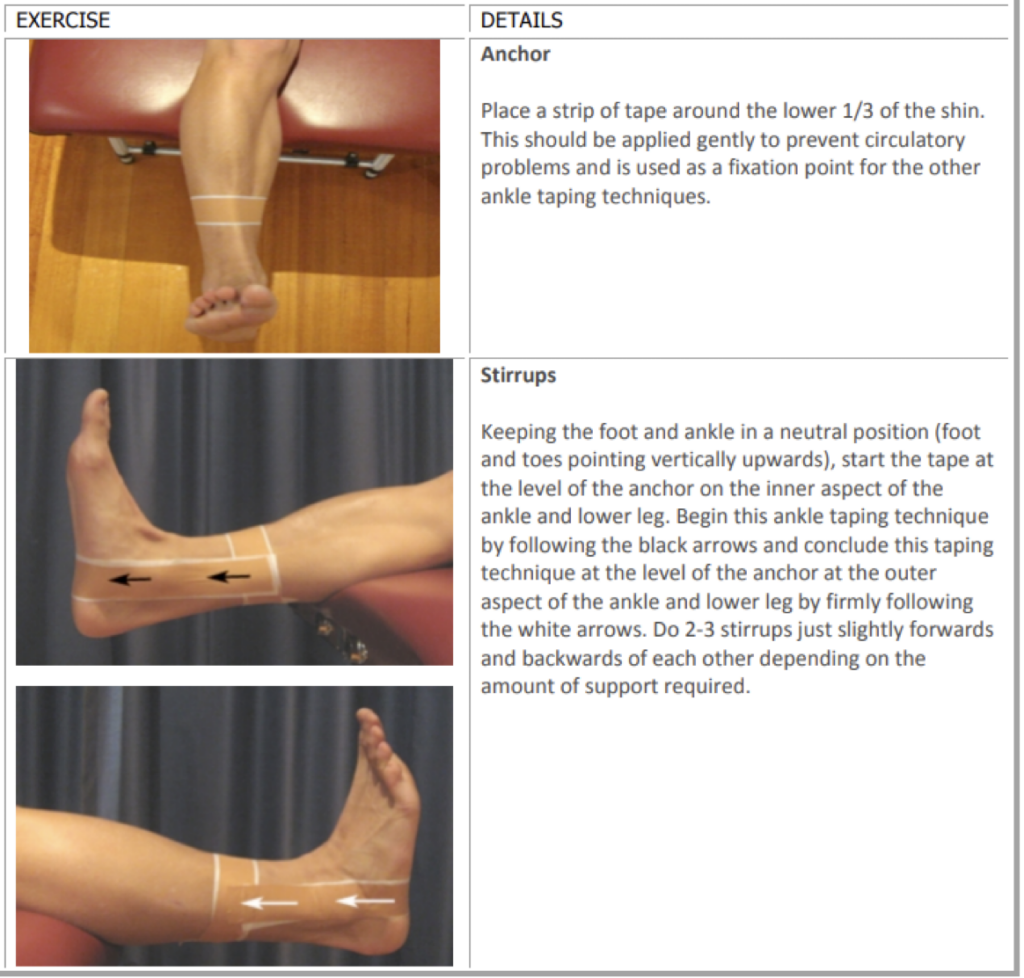
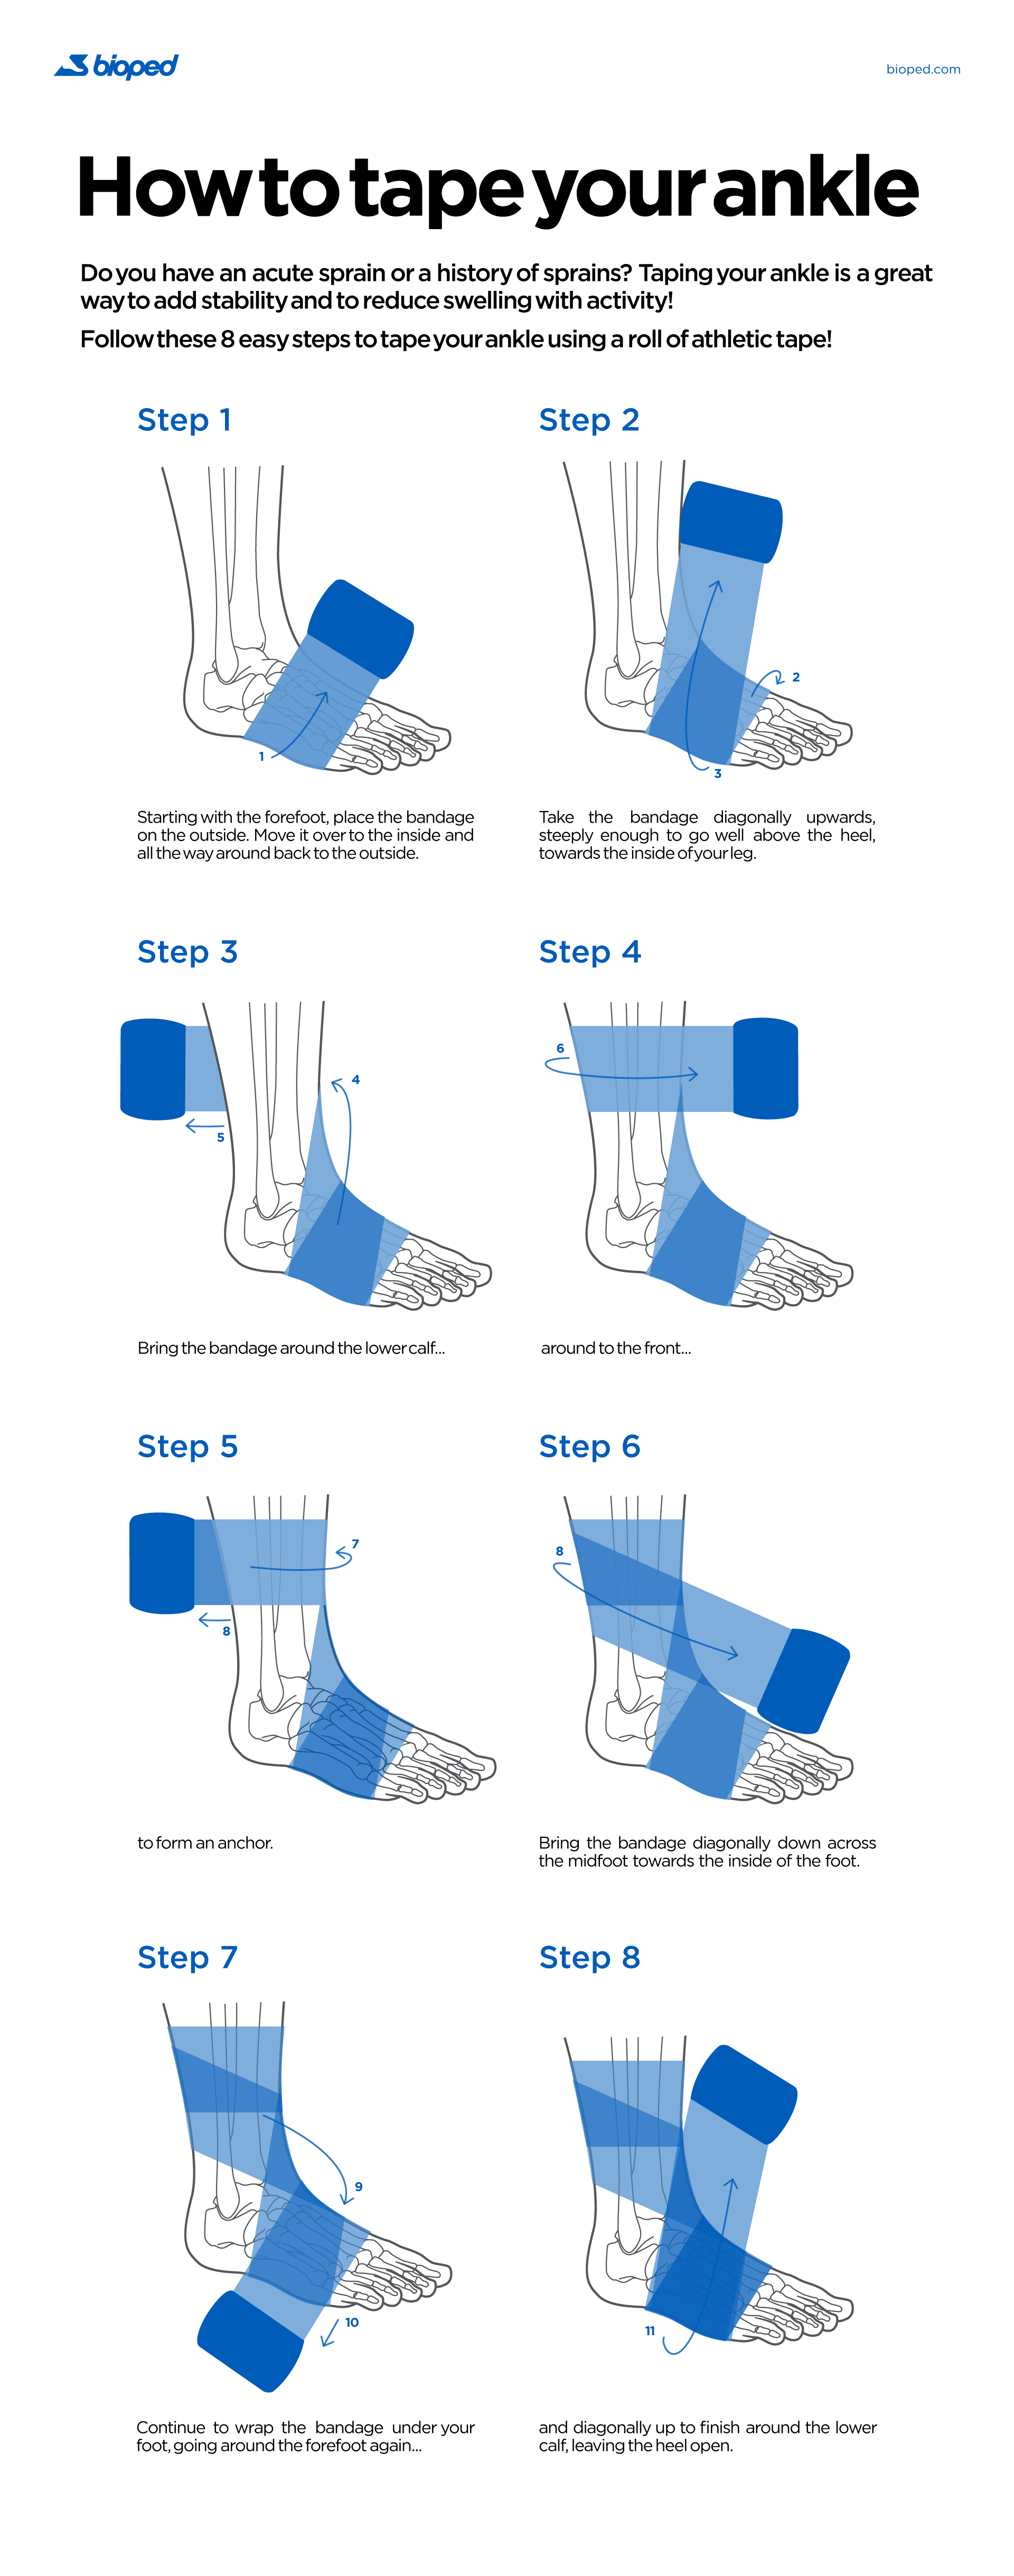
Here is how I actually do it. I keep my anchor point at the midfoot, just behind the ball of the foot where the foot transitions from flexible forefoot to rigid midfoot. This is non-negotiable. If you start the tape too far forward on the toes, it catches and wrinkles every time you flex your foot. If you start too far back on the arch, it loses leverage. The midfoot anchor gives you a solid foundation that moves with the foot without shifting under itself. For lateral ankle support, which is what most people want after a roll, you use three strips. The first strip runs from the midfoot anchor diagonally up and behind the lateral malleolus, then back down toward the calf. You apply this with about twenty-five percent tension. Not a stretch, not slack, just enough to create contact. The second strip comes from the same anchor point but angles higher, crossing over the back of the lateral malleolus toward the medial side of the calf. This one gets thirty percent tension. The third strip mirrors the second but comes from underneath the arch and angles up over the lateral malleolus toward the medial calf, also at thirty percent tension. This creates a gentle Y pattern that wraps around the outside of the ankle without constricting it. The critical detail nobody mentions is bone grounding. Before you apply the final strip, you need to press the tape down firmly over the bony prominence of the lateral malleolus. The tape needs direct skin contact over the bone to create that lifting effect. If it bridges over soft tissue instead of sitting on the bone, it does nothing for proprioception and just sits there like a bandage. I spend about ten seconds smoothing specifically over that bony bump on each strip. It makes the difference between tape that works and tape that is decorative.
I once had a client who was a rugby player with chronic lateral ankle instability. His tapes kept rolling up within an hour of play, no matter how carefully I applied them. The problem was not the tension or the anchor point. It was hair. He had significant hair on his lower legs and ankles. The tape adhesive was bonding to his hair, not his skin, so every time he moved, the tape pulled loose from the root rather than staying adhered to the skin. The workaround was straightforward: shave the application area on the lateral malleolus and lower calf. Not the whole leg, just the two-inch patch where the tape contacts. After that, his tapes lasted the entire game without migration. For dorsiflexion support, which is useful if you have tibialis anterior strain or need help with ankle dorsiflexion range during rehab, the technique changes. You position the ankle in slight dorsiflexion first. Then you anchor at the base of the toes and apply a single strip running up the front of the shin. This time you use sixty to seventy percent tension on the tape. The tape acts as a elastic brake, providing resistance against further dorsiflexion. This is more of a limiting mechanism than a stabilizing one, and it is commonly used in early-stage rehab to prevent the ankle from going into painful range during active motion. One counter-intuitive thing about kinesiology tape that beginners miss: the direction you pull the tape matters less than the direction the tape is allowed to recoil. When you apply a strip, you are not restraining the joint in the direction you pull. You are creating tension that pulls back toward the anchor point, which creates a gentle decompressive force on the skin and underlying tissue. So if you are applying tape for lateral ankle stability and you pull the tape upward and medially over the lateral malleolus, the recoiling force actually pulls laterally and downward on that tissue, which provides the stabilizing compression. Apply it the wrong way around and the recoil does the opposite of what you want.
Get the Full Details

Another thing people get wrong is the skin prep. I have seen people apply tape over dry, flaky skin or skin with body lotion residue and wonder why it falls off. Wipe the area with an alcohol pad or just clean water and let it dry completely before application. Even a thin film of natural oils from your skin can reduce adhesion by half. If you are in a field environment and do not have alcohol wipes, use the inside of your shirt to rub the skin vigorously until it feels clean and slightly warm. Friction generates heat, and warm skin accepts adhesive better than cold skin. There are limits to what this does. KT tape provides approximately two hundred to four hundred grams of supportive force depending on the product and tension used. A properly fitted lace-up brace provides significantly more mechanical restriction. If you are returning to sport after a significant sprain, tape alone is insufficient protection. Use the tape as an adjunct to bracing, not a replacement. The tape improves proprioception and reduces swelling. The brace prevents inversion and plantarflexion beyond safe ranges. Both together is the standard approach in sports medicine. Removal is equally important and almost always done incorrectly. People rip it off like a Band-Aid, which causes skin irritation and micro-tears in the stratum corneum. The correct method is to soak the tape with warm water or apply a adhesive remover solvent like Unstop or Durelease. Then lift a corner and pull the tape back on itself parallel to the skin, not away from it. Pulling perpendicular to the skin lifts the epidermis and causes damage. Pulling parallel to the skin, with the tape folded back, slides the adhesive off the surface without trauma. It takes longer but preserves the skin barrier, which matters if you are reapplying tape daily.
Duration-wise, a proper application lasts three to five days under normal conditions. Sweat, showering, and friction from socks and shoes degrade the adhesive gradually. If the edges start lifting within twelve hours, the skin was not prepped correctly or you applied it over hair that was not trimmed. If the tape causes itching or redness that persists after removal, you may have a mild adhesive sensitivity. Switch to a hypoallergenic brand like Kinesio Tex Classic or Pro Kinetic, which use a different adhesive chemistry. The performance difference is negligible for most users. The ankle is a complex joint with multiple ligamentous and tendinous structures converging in a small area. Taping it effectively requires understanding which structure you are targeting and applying the tape accordingly. Lateral ligament support uses the three-strip technique described above. Medial support uses a mirror image on the inside. Dorsiflexion limitation uses a single high-tension strip on the front. Each configuration serves a different biomechanical purpose and should be selected based on the specific complaint, not copied blindly from a generic tutorial.